Archive for the ‘research’ Category

Awaited Ivermectin Review is Out

https://www.medpagetoday.com/special-reports/exclusives/93485?xid=nl_mpt_DHE_2021-07-

Awaited Ivermectin Review Is Out

— Findings are positive, but critics still want a randomized controlled trial
Boxes and blister pack of Ivermectin Tablets USP Boxes and blister pack of Ivermectin Tablets USP and a prescription bottle.a

Proponents of ivermectin for COVID-19 have long been talking about an expected review and meta-analysis led by Andrew Hill, PhD, of the University of Liverpool.

These results were finally published this week in Open Forum Infectious Diseases, and they’re positive — but they haven’t escaped criticism, and most researchers still want results from a randomized controlled trial.  (See link for article)

___________________

**Comment**

The following was found from the review:

  • There was a 56% reduction in mortality (relative risk [RR] 0.44, 95% CI 0.25-0.77, P=0.004), with 3% of patients on ivermectin dying compared with 9% of controls
  • A 70% improvement in survival (RR 0.30, 95% CI 0.15-0.58, P=0.0004)
  • A reduction in time to recovery of 1.58 days compared with controls (95% CI -2.8 to -0.35, P=0.01) 
  • A shorter duration of hospitalization (-4.27 days, 95% CI -8.6 to -0.06, P=0.05).
But this still wasn’t good enough for critics.

And there’s been 32 randomized controlled trials done to date, but that still isn’t good enough for critics.

The key for this is found in the following quote:

“Of course, rolling out vaccination as quickly and widespread as possible would negate the need to use ivermectin as a treatment,” he added. “So big picture, vaccines are the better solution.”

This is completely backwards.

Rolling out effective treatments as quickly and widespread as possible negates the need for a vaccine!  But history is being rewritten to state natural immunity will only be achieved through vaccines – the magic bullet for mankind.

Despite what mainstream news and medical rag journals like Medscape state, current research shows:
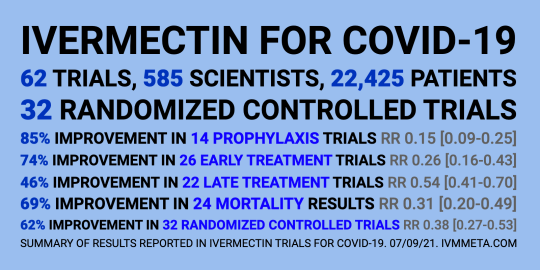
isummarySource: Database of all ivermectin COVID-19 studies – www.c19ivermectin.com – (constantly updated)

For the backstory on how Remdesivir obtained EUA status despite lack of effectiveness, while Ivermectin languished on shelves see this article for the sordid history.

In what can only be described as “shennanigans,” researchers changed the primary outcome measures in the study for Remdesivir to make it appear more successful.  Go here for more info.

For more on Ivermectin:

“We now have four large randomized control trials totaling over 1,500 patients each trial showing that as a prophylaxis agent [against COVID-19] it is immensely effective,” Kory said. “You will not get sick. You will be protected from getting ill if you take it in early outpatient treatment.”

Please see FLCCC’s COVID-19 treatment protocols for every stage of illness: https://covid19criticalcare.com/covid-19-protocols/  as well as the research on it:   https://covid19criticalcare.com/ivermectin-in-covid-19/
Lastly, the following was written about the Medscape piece:

I have years of experience with Ivermectin in the Brazilian Amazon. The drug in general, has acceptable safety profile. Ivermectin has few established mechanisms of action; chief among them are its immunomodulatory and antiinflammatory properties. Recently, Australian scientists conducted an in vitro study of the MOA of Ivermectin with respect to SARS-CoV-2 replication. The Australian study showed it interferes with a specific protein product which is essential in the viral replication cycle. Considering the benefit of this drug outweighs the risk, Ivermectin is a reliable and practical solution in resource-limited countries where access to COVID-19 meds is scarce. It is commonly understood that in the western countries, the Big Pharma resists prescription of Ivermectin for COVID19 cases.  – Prof. Dr. Nassiri, July 9, 2021

BINGO!

Lyme & Sudden Hearing Loss

https://danielcameronmd.com/lyme-disease-triggers-hearing-loss/

LYME DISEASE AND SUDDEN ONSET HEARING LOSS

lyme-disease-sudden-onset-hearing-loss

An article by Sowula and colleagues, published in the Journal of Clinical Medicine, describes nine patients with Lyme disease who had sudden sensorineural hearing loss (SSNHL), also referred to as sudden deafness.[1]

The study aimed to assess the prevalence of this type of sudden onset hearing loss, particularly among Lyme disease patients. The authors explain, “Sudden sensorineural hearing loss (SSNHL) is defined as sensorineural hearing loss of 30 dB or more over at least three adjacent audiometric frequencies occurring within a 72-h period of time.”

This type of sudden onset hearing loss can be caused by a viral infection, vascular insufficiency, autoimmune disorder, neoplasm, stroke and irradiation. 

Treatment is directed towards the cause with standard therapy typically involving corticosteroid, vasodilators, and ionotropic agents, the authors write. Unfortunately, the cause is unknown in 90% of the cases.

The study looked at 86 patients who were hospitalized, between 2017 and 2018, due to sudden sensorineural hearing loss. As part of their evaluation for sudden onset hearing loss, patients were tested for Lyme disease.

Out of 86 patients, 9 tested positive for Lyme disease. Other studies, however, indicate that up to 21% of patients with sudden sensorineural hearing loss test positive for Lyme disease, the authors write.

Hearing loss patients with Lyme disease

On average, the 9 patients were around 47 years old, with an age range between 30 and 70. None of the Lyme disease patients responded to intravenous corticosteroids, microcirculatory drugs, or ionotropic drugs.

Seven of the nine patients with sudden onset sensorineural hearing loss were treated with oral doxycycline or intravenous ceftriaxone.  

Four patients were treated with doxycycline. Hearing improved by 10dB for one of the patients.

Complete hearing recovery with IV ceftriaxone

The remaining 3 patients, who were treated with intravenous ceftriaxone, had complete improvement in their hearing loss.  

“Those three patients reported a complete recovery of hearing (PTA shows respectively 15.20 dB HL for low frequency and 28.35 dB HL for high frequency),” the authors write.

“Infections caused by Borrelia burgdorferi may contribute to the development of inflammatory and angiopathic lesions, which are a possible cause of [sudden sensorineural hearing loss].”

Unfortunately, 2 patients were left with high-frequency tinnitus. “In these patients, tinnitus was present from the beginning of the disease,” the authors write.

The group of 9 Lyme disease patients “was treated with antibiotics and experienced partial or complete regression of their deafness,” the authors conclude. “This may suggest a relationship between [sudden sensorineural hearing loss] and Lyme disease.”

“The longer the duration of the infection, the greater the likelihood of permanent and irreversible changes in the vessels of the cochlea or auditory nerve,” the authors caution.

References:
  1. Sowula K, Szaleniec J, Stolcman K, Ceranowicz P, Kocon S, Tomik J. Association between Sudden Sensorineural Hearing Loss and Lyme Disease. J Clin Med. Mar 8 2021;10(5)doi:10.3390/jcm10051130

___________________

For more:

What is Powassan Virus?

https://danielcameronmd.com/what-is-powassan-virus/

WHAT IS POWASSAN VIRUS?

what is powassan virus
The Powassan virus is a tick-borne illness transmitted by the same tick that harbors the Lyme disease bacterium. Although it is still considered rare, the number of cases is growing and if contracted the virus can have devastating and long-lasting effects.

In their article “Underrecognized Tickborne Illnesses: Borrelia Miyamotoi and Powassan Virus,”  Della-Giustina et al. explain what is the Powassan virus and why it’s raising concerns.  

“We chose to review the Powassan virus because it only requires 15 min. of tick attachment for transmission, and the sequelae of the neurologic disease are devastating, in addition to a 10% mortality rate.”¹

What is Powassan virus?

The Powassan virus (POW) is a tick-borne flavivirus that is related to other viruses including: dengue, yellow fever, West Nile encephalitis, and tick-borne encephalitis (primarily found in Europe). “Flaviviruses are a group of single stranded RNA viruses that cause severe endemic infection and epidemics on a global scale.”²

In recent years, other viruses transmitted by ticks have been identified including the Heartland virus (phlebovirus) and the Bourbon virus (thogotovirus).

POW is very similar genetically to the deer tick virus and the clinical presentations are identical.
How was it discovered?

Powassan was first discovered in the brain of a young child.

“Powassan virus is named for the Ontario, Canada, town where it was first isolated from the brain of a 5-year-old boy who died of severe encephalitis in 1958,” the authors write.

Where is it?

The second case was reported in New Jersey (1970) and then another in eastern Russia (1978). Although, there have been no reported cases in other countries, the virus has been identified in a growing number of states.

In 2019, 13 U.S. states reported cases: Connecticut, Indiana, Massachusetts, Maine, Minnesota, North Carolina, North Dakota, New Hampshire, New Jersey, New York, Pennsylvania, Rhode Island, and Wisconsin.

Ticks infected with Powassan virus can transmit the disease in only 15 minutes, causing long-lasting neurologic problems in some individuals, in addition to a 10% mortality rate.

How is the virus transmitted?

The Powassan virus is carried and transmitted by Ixodes scapularis ticks, also known as deer ticks or blacklegged ticks. These ticks can also transmit Borrelia burgdorferi, the bacteria which causes Lyme disease.

“Although many flaviviruses have mosquitos as competent vectors, there is no evidence of human POW virus disease transmitted by mosquitos,” the authors point out.

How fast can Powassan virus be transmitted?

Very fast. “Transmission in mice has been shown to occur within 15 min. of I. scapularis attachment,” the authors write.

This rapid transmission occurs because the virus is already present in the salivary glands, compared to other non-viral tick-borne diseases where the pathogen is typically harbored in the tick’s mid-gut.

What is the typical clinical presentation?

“Few people who become infected with the POW virus have clinically significant disease,” the authors write.

However, in some cases, “a Powassan infection can lead to disorientation, headache, neck stiffness, fever up to 40°C, clonus, ocular, and other motor palsies, obtundation and convulsions, and can mimic herpes simplex encephalitis.”

Can Powassan virus be serious?

Yes.  

“Approximately 50% of cases result in lasting hemiplegia, memory problems, and muscle wasting,” the authors explain.

“Ten percent of cases are fatal.”

Are there tests for it?

A PCR test is only positive in early stages of a Powassan infection. “IgG by enzyme-linked immunosorbent assay is the mainstay of diagnosis, but confirmation requires specialized testing,” write the authors.

Why are co-infections important?

Treatable tick-borne co-infections may be present. The authors describe a patient with a combination of Powassan encephalitis, Lyme carditis, and Babesia.

Yoon and colleagues described the case of a 17-year-old young man who died waiting for a Powassan virus test.³  He was not treated for a co-infection with Lyme disease. His autopsy showed Borrelia spirochetes, which cause Lyme disease, in his heart and liver. He also had PCR evidence of spirochetes in his brain and lungs.

What is the treatment for a Powassan infection?

There is no treatment for a Powassan virus infection other than supportive care.

References:
  1. Della-Giustina D, Duke C, Goldflam K. Underrecognized Tickborne Illnesses: Borrelia Miyamotoi and Powassan Virus. Wilderness Environ Med. Jun 2021;32(2):240-246. doi:10.1016/j.wem.2021.01.005
  2. Chong HY, Leow CY, Abdul Majeed AB, Leow CH. Flavivirus infection-A review of immunopathogenesis, immunological response, and immunodiagnosis. Virus Res. 2019 Dec;274:197770. doi: 10.1016/j.virusres.2019.197770. Epub 2019 Oct 15. PMID: 31626874.
  3. Yoon EC, Vail E, Kleinman G, et al. Lyme disease: a case report of a 17-year-old male with fatal Lyme carditis. Cardiovasc Pathol. Sep-Oct 2015;24(5):317-21. doi:10.1016/j.carpath.2015.03.003

____________________

**Comment**

Regarding transmission time – ALL pathogens can reside in the salivary glands of ticks due to partial feeding, which will result in quicker transmission times, but this fact is continually downplayed:  https://madisonarealymesupportgroup.com/2019/04/26/three-strains-of-borrelia-other-pathogens-found-in-salivary-glands-of-ixodes-ticks-suggesting-quicker-transmission-time/

It’s also important to note that minimum transmission times have NEVER been established:   https://madisonarealymesupportgroup.com/2017/04/14/transmission-time-for-lymemsids-infection/

https://madisonarealymesupportgroup.com/2021/06/01/cdc-lying-again-tuttle-drops-the-mic/  Within this important letter, Lyme advocate Carl Tuttle shows rapid transmission has occurred in under 4 hours:

  1. Clinical evidence for rapid transmission of Lyme disease following a tick bite:  https://www.sciencedirect.com/science/article/abs/pii/S0732889311004159?via%3Dihub
  2. B. Patmas, MA, Remora, C. Disseminated Lyme Disease After Short-Duration Tick Bite. JSTD 1994; 1:77-78: https://www.lymedisease.org/hard-science-on-lyme-ticks-can-transmit-infection-the-first-day/
  3. Lyme borreliosis: a review of data on transmission time after tick attachment:  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4278789/  The claims that removal of ticks within 24 hours or 48 hours of attachment will effectively prevent LB are not supported by the published data, and the minimum tick attachment time for transmission of LB in humans has never been established.
  4. Regarding Tick Attachment Times –  https://history.nih.gov/display/history/Burgdorfer%2C+Willy+1986
There are about 5 to 10 percent of infected ticks that have a generalized infection, including salivary glands and saliva at the time of attachment. In such cases, transmission of spirochetes would and does occur immediately at time of attachment.” —Willy Burgdorfer

According to this study by Coppe Labs, right here in Wisconsin, 85% of Powassan infected ticks come from Northern Wisconsin. Another study by Coppe showed that when 95 patients were tested for suspected tick-borne disease, 66% showed evidence of current or prior Lyme infection.  Of those patients, 17% had serologic evidence of acute POWV infection, demonstrating that POWV may affect more patients than we know.

For more on Powassan:

Lyme Disease, Autoimmune Encephalopathy, & Basal Ganglia Encephalitis

http://  Approx. 1 hour, 15 Min.

Nov. 23, 2020

The Links between Lyme Disease and Autoimmune Encephalopathy and Basal Ganglia Encephalitis (BGE) – Presentation and Q&A Part of the PANS/PANDAS webinar series
Professor Craig Shimasaki,
CEO of Moleculera Labs,
Oklahoma USA Presentation

Evaluating Effects of Minimal Risk Natural Products for Control of Black-Legged Ticks

https://pubmed.ncbi.nlm.nih.gov/33044507/

Evaluating the Effects of Minimal Risk Natural Products for Control of the Tick, Ixodes scapularis (Acari: Ixodidae)

Affiliations

Abstract

Knockdown and residual activity of 10 minimal risk natural products (MRNPs), one experimental formulation of nootkatone, and two bifenthrin labels were evaluated against host-seeking nymphal Ixodes scapularis Say using a novel micro-plot product screening system placed in a landscape setting similar to a wooded residential property. The MRNPs evaluated included Tick Stop, EcoPCO EC-X, Met52 EC, CedarCide PCO Choice, EcoEXEMPT IC2, EcoSMART Organic Insecticide, Essentria IC3, privately labeled products 1 and 2 (based on EcoEXEMPT IC2 and sold as a professional pest control application), and Tick Killz.

Just the nootkatone and 4 of these 10 products tested (EcoPCO EC-X, Met52 EC, EcoEXEMPT IC2, and Essentria IC3) had statistically significant (P < 0.05) knockdown effects (killed ticks while active in the arenas) when compared to water-only controls, but only 2 of these, EcoPCO EC-X and nootkatone, displayed significant residual tick-killing activity after weathering naturally in the landscape for 2 wk prior to tick application/testing.

Moreover, botanical oil-based products with the same active ingredients provided inconsistent results when tested multiple times across study years.

For more:
