Archive for the ‘research’ Category

New Study: Pretty Much Everyone Is Getting Heart Damage From COVID Shots

https://stevekirsch.substack.com/p/new-study-shows-that-pretty-much

New study shows that pretty much everyone is getting heart damage from the COVID vaccines

They just aren’t letting you know that. In Canada, the medical community is very smart about this: they don’t let doctors measure troponin levels before you are vaccinated so nobody is the wiser.

Executive summary

A new study shows that nearly everyone getting the mRNA COVID vaccines are experiencing some amount of heart damage.

Introduction

Watch this episode from Vinay Prasad before YouTube censors it.

You only need to look at 6:21 into the video:
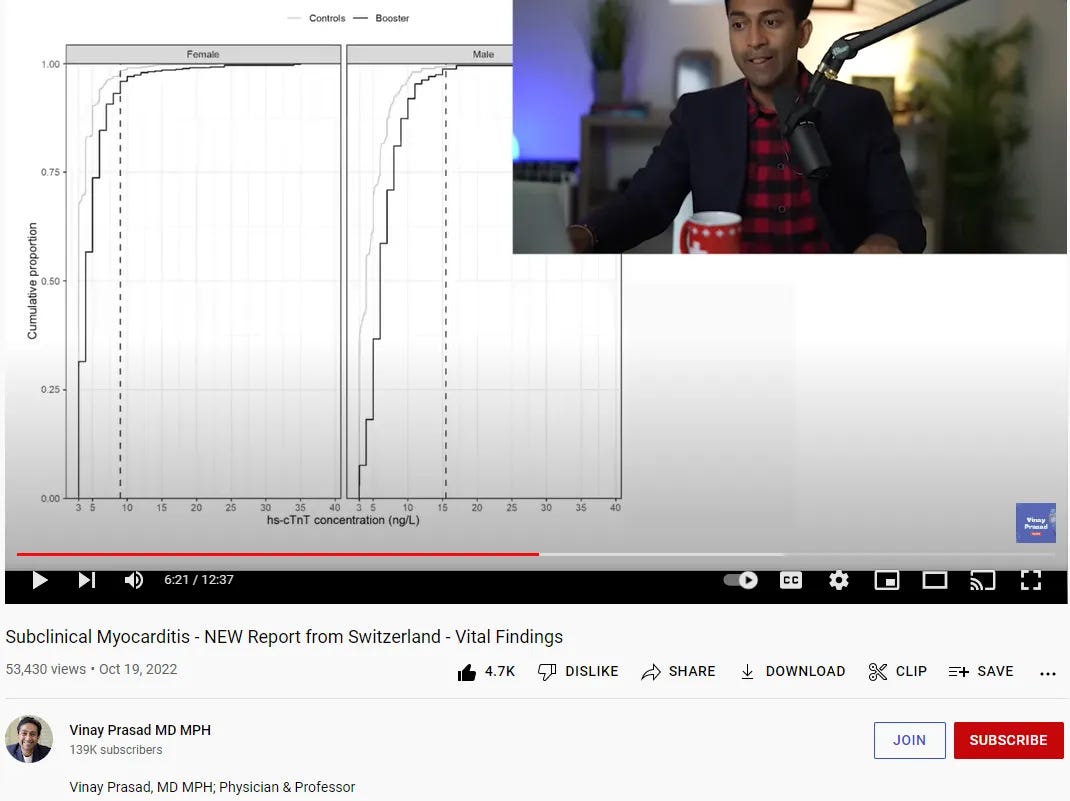
A new study out of Switzerland shows that vaccinated people have uniformly higher troponin levels than their unvaccinated peers.

In the graph shown at 6:21, we see that the 777 people who got the booster in this study have uniformly higher troponin levels than their matched unvaccinated peers. That is not supposed to happen. If the vaccines are safe, the troponin levels should be nearly identical between vaccinated and unvaccinated groups.

Here are Professor Prasad’s exact words:

It’s not just the tip of the distribution that has elevated high sensitivity troponin, it’s that the entire distribution is right shifted. Everybody’s having a little bit of elevation in high sensitivity troponin. That’s what this graph would have you infer.

You get a troponin elevation when there is damage to your heart:

Troponin is a type of protein found in the muscles of your heart. Troponin isn’t normally found in the blood. When heart muscles become damaged, troponin is sent into the bloodstream. As heart damage increases, greater amounts of troponin are released in the blood

What the study shows is that nearly everyone is getting a little heart damage when they get the COVID vaccine, some get a lot more damage than others.  (See link for article)

__________________

SUMMARY:

  • Actual damage is likely much higher as they are measuring on days 3 & 4 when the slope is going down.
  • The article mentions the Thailand study, summarized in the video, which showed 1 in 28 boys developed subclinical myocarditis.  It also showed that 1 in 43 teens got myocarditis. Nearly 30% had cardiac symptoms.
    • Anish Koka MD (Cardiology) really digs into the Thailand data and points out that it has long ago been established that the messenger RNA vaccines cause myocarditis.  This is the real punchline:
I can assure you, and the mostly ER doctor contingent on twitter that brays about “mild myocarditis”, that there are no cardiologists who want to see their child have a cardiac troponin that is 2x normal or 40x normal after administration of some therapeutic.

It is absolutely head-spinning to see that the public conversation now is geared to dismiss cardiac injury in young healthy children as “mild”. ~ Dr. Anish Koka

  • Dr. Linda Wastila also asks why are we accepting myocarditis as an acceptable side effect after the COVID shots.
  • Kirsch points out that it’s highly likely the study author, Professor Christian Mueller, a highly respected scientist, will face attacks on the study due to his findings.
  • Canada is simply not letting doctors measure troponin levels before the shots are given.  Ignorance after all, is bliss.  Levels can only be checked if someone is admitted to the hospital, so no comparisons can be made.
“Authorities”, once again, are turning a blind eye to science, data, and reality.

For more:

Boston University Lab Creates New Deadly COVID Strain

https://thehighwire.com/videos/boston-university-lab-creates-new-deadly-covid-strain/  Video Here (Approx. 9 Min)

BOSTON UNIVERSITY LAB CREATES NEW DEADLY COVID STRAIN

Oct. 24, 2022

Is Boston University the new Wuhan? Researchers there have skipped the required NIH framework for dangerous pathogens to create a chimeric SARS virus strain on American soil.

Boston University researchers are taking that stance that it’s not ‘gain of function’ due to the fact their merging of the original Wuhan COVID strain with Omicron only caused an 80% kill rate in rats vs. the 100% kill rate in the original strain – essentially a “reduction in function.”

However, there is no way they could have known the outcome and as Dell succinctly points out, they could have created a more deadly virus and then accidentally carried it out of the lab similarly to how many believe is what happened in Wuhan.

Dell is not alone.  Other experts have slammed the research:

“This is playing with fire – it could spark a lab-generated pandemic.” ~ Daily Mail

Of course mainstream media is coming to bat (no pun intended) for the dangerous research as they are bought-out by Big Pharma and Big government – all of which are paid by the same entities and have the same agenda.  While mainstream media admits the research involved creating a hybrid COVID-19 strain, it’s all well and good because of the purpose of the study and the supposed safety measures that were taken.

Sorry.  No dice.

For more:

Anaplasmosis & Stabbing Headache

https://danielcameronmd.com/anaplasmosis-leading-to-neurological-symptoms-of-trigeminal-neuralgia/

Anaplasmosis leading to neurological symptoms of trigeminal neuralgia

anaplasmosis-neurological-symptoms

Anaplasmosis, formerly called human granulocytic anaplasmosis (HGA) is a co-infection from a tick that typically causes acute disease. In their article, “Trigeminal Neuralgia As the Principal Manifestation of Anaplasmosis: A Case Report,” LeDonne and colleagues described human granulocytic anaplasmosis in an 80-year-old woman with neurological symptoms. [1]

According to the authors, the woman experienced a “sudden onset of severe, lancinating headache in the distribution of the fifth cranial nerve bilaterally.”¹ She had been treated for Lyme disease two months earlier following a tick bite and a rash on her torso. She had since been bitten by a non-engorged tick.

Her neurologic exam was felt to be consistent with a diagnosis of trigeminal neuralgia. Trigeminal neuralgia (TN) is a type of chronic pain that affects your face. It causes extreme, sudden burning or shock-like pain. It usually affects one side of the face.²

The patient’s mother had a history of trigeminal neuralgia. The doctors did not see any evidence of Lyme disease.

“However, anaplasmosis and ehrlichiosis can both develop over a shorter timeframe and without a noticeable rash, making these infections a more likely explanation of the patient’s signs and symptoms,” wrote the authors.

They added, “To confirm the suspected diagnosis, a tick-borne disease panel was ordered and was positive for Anaplasma phagocytophilum DNA by PCR.”

“Although severe headache is a common presenting symptom in patients with anaplasmosis, prior studies have not linked anaplasmosis and trigeminal neuralgia,” the authors explained.

“Our case suggests that anaplasmosis was the cause of our patient’s new-onset trigeminal neuralgia.”

The woman was treated with a 3-week course of doxycycline for Anaplasmosis and was prescribed gabapentin 300 for her trigeminal neuralgia.

She had marked improvement in her headaches. Her leukopenia, thrombocytopenia and abnormal hepatic enzymes returned to normal.

In their article, the authors reviewed the literature on Anaplasmosis, pointing out that the symptoms of Anaplasmosis are non-specific and may include fever, myalgia, and headache but no rash. In addition, patients may present with leukopenia, thrombocytopenia, elevated transaminases, and elevated lactate dehydrogenase.

“Rare cases of Anaplasmosis showcase post-infectious complications such as demyelinating polyneuropathy and brachial plexopathy,” wrote the authors. “However, this patient’s presentation of anaplasmosis with new onset trigeminal neuralgia appears to be unique and rare.”

The authors urge clinicians to consider Lyme disease, anaplasmosis, and Ehrlichia in “a patient presenting to the hospital with non-specific symptoms of fever, myalgia, and headache in tick endemic areas.”

Autopsy Shows Pericarditis & Aortic Inflammation After COVID Shot

https://www.sciencedirect.com/science/article/pii/S1344622322001420

An autopsy case report of aortic dissection complicated with histiolymphocytic pericarditis and aortic inflammation after mRNA COVID-19 vaccination

https://doi.org/10.1016/j.legalmed.2022.102154Get rights and content

Highlights

•An autopsy case report of pericarditis after COVID-19 vaccination is presented.
•Extended inflammation of the aortic wall was histologically confirmed.
•Macrophages and lymphocytes infiltrated, along with a small number of eosinophils.

Abstract

A male in his 90 s consulted a doctor because he experienced several days of general fatigue and dyspnea. He was diagnosed with heart failure, and diuretic medications taken for 3 days relieved his symptoms. However, he was found dead on the morning of the fourth day after consultation. He had received a third dose of coronavirus disease 2019 (COVID-19) vaccine approximately 2 weeks before death. An autopsy revealed dissection of the ascending aorta and pericardial hemotamponade. The heart showed a white villous surface, and the pericardium was fibrously thick. Microscopic examination revealed pericarditis with predominantly macrophage and lymphocyte infiltration. These histological findings were compatible with those of post-vaccination myocarditis. To the best of our knowledge, histopathologically proven pericarditis after COVID-19 vaccination has not been reported. In the present case, extended inflammation of the aortic adventitia was a possible cause of aortic wall fragility followed by dissection.

_______________

For more:

Facial Nerve Dysfunction After Treatment For Lyme Disease

https://danielcameronmd.com/facial-nerve-dysfunction-after-treatment-lyme-disease/

Facial nerve dysfunction after treatment for Lyme disease

By Dr. Daniel Cameron

facial-nerve-dysfunction-lyme-disease

Some individuals with Facial Nerve Palsy (Bell’s palsy) have reportedly had facial nerve dysfunction, as long as one year after antibiotic treatment for Lyme disease. Some suffer from synkinesis, where patients present with unwanted contractions of the muscles of the face during attempted movement. They may notice forceful eye closure when they attempt to smile or other muscle spasms during routine facial movements.

In their study, Wormser and colleagues found that 6 of the 11 Lyme disease patients (54.5%) suffered from facial nerve dysfunction an average of 13.1 months following the onset of treatment with corticosteroids.¹

  • 52-year-old man with “tearing of left eye when eating (Bogorad’s syndrome); mild residual weakness left side.”
  • 51-year-old man with “mild residual left sided weakness; dryness left eye; after speaking a lot, left sided facial muscles feel abnormal.”
  • 56-year-old man with “narrowed palpebral fissure right eye; dry mouth; sensation of muscles around right eye being squeezed; tearing of right eye; twitching of the area between the eyes on the forehead; new dimple right cheek; intermittent lisp.”
  • 25-year-old man with “narrowed palpebral fissure left eye; reduced forehead movement; right sided jaw discomfort with eating; tearing of the left eye when eating (Bogorad’s syndrome).”
  • 61-year-old man with “narrowed palpebral fissure right eye; difficulty whistling; right eye discharge at night.”
  • 70-year-old woman who had “surgical facial nerve decompression nearly 3 months after onset of the LDFP (Lyme disease facial palsy).”

“Facial synkinesis presents following injury to the facial nerve and manifests as involuntary movement during volitional or spontaneous movement. This phenomenon may become clinically apparent 3 to 4 months following facial nerve injury,” wrote Shokri et al.²

Additionally, LeWitt described a case of hemifacial spasm (HFS) from Lyme disease and concluded that “Because its diagnosis can be occult (hidden) and antibiotic therapy can be both diagnostic and therapeutic, Lyme disease should be a consideration for cases of HFS.”³

Ramsey and colleagues examined acute peripheral facial palsy (APFP) in Lyme disease patients and found that “10% of patients with APFP testing positive for Lyme disease may be an underestimate, since several other studies in endemic areas have reported rates varying from 14.7% to 33%.” The authors did not indicate how many of their patients had incomplete eyelid closure or abnormal facial movement from aberrant regeneration.4

“We recommend screening patients with APFP for associated and treatable factors, especially Lyme disease in regions where the disease is endemic.”4

References:
  1. Wormser GP, McKenna D, Scavarda C, Karmen C. Outcome of facial palsy from Lyme disease in prospectively followed patients who had received corticosteroids. Diagn Microbiol Infect Dis. Aug 2018;91(4):336-338. doi:10.1016/j.diagmicrobio.2018.03.016
  2. Shokri T, Azizzadeh B, Ducic Y. Modern Management of Facial Nerve Disorders. Semin Plast Surg. Nov 2020;34(4):277-285. doi:10.1055/s-0040-1721824
  3. LeWitt TM. Hemifacial Spasm From Lyme Disease: Antibiotic Treatment Points to the Cause. Clin Neuropharmacol. Nov/Dec 2016;39(6):329-330. doi:10.1097/WNF.0000000000000193
  4. Ramsey DJ, Haas LP, Tucker SM. Long-term Outcome After Acute Peripheral Facial Palsy. Ophthalmic Plast Reconstr Surg. Jan 27 2022;doi:10.1097/IOP.0000000000002134

For more: