Archive for the ‘Activism’ Category

Mosquito Resistant Clothing Prevents Bites in Trials

https://news.ncsu.edu/2021/07/mosquito-resistant-clothing-prevents-bites-in-trials/

Mosquito-Resistant Clothing Prevents Bites in Trials

Bite-resistant textiles
Mosquitoes landing on bite-resistant fabric during an in vivo bioassay in which they fail to probe through the fabric due to its small pore size. The proboscis bends when mosquitoes try to push through the fabric. Credit: Matt Bertone.
FOR IMMEDIATE RELEASE
R. Michael Roe
Grayson Cave
Laura Oleniacz, NC State News Services

North Carolina State University researchers have created insecticide-free, mosquito-resistant clothing using textile materials they confirmed to be bite-proof in experiments with live mosquitoes. They developed the materials using a computational model of their own design, which describes the biting behavior of Aedes aegypti, the mosquito that carries viruses that cause human diseases like Zika, Dengue fever and yellow fever.

Ultimately, the researchers reported in the journal Insects that they were able to prevent 100 percent of bites when a volunteer wore their clothing – a base layer undergarment and a combat shirt initially designed for the military – in a cage with 200 live, disease-free mosquitoes. Vector Textiles, an NC State startup company, has licensed the related patent rights and intends to make clothing for commercial sale in the United States.

The researchers think their computational model could be used more widely to develop clothing to reduce transmission of diseases.

“The fabric is proven to work – that’s the great thing we discovered,” said study co-author Andre West, associate professor of fashion and textile design at NC State and director of Zeis Textiles Extension for Economic Development. “To me, that’s revolutionary. We found we can prevent the mosquito from pushing through the fabric, while others were thick enough to prevent it from reaching the skin.”

To develop the computational model to design textile materials that could prevent A. aegypti bites, researchers investigated the dimensions of the head, antenna and mouth of A. aegypti, and the mechanics of how it bites. Then, they used the model to predict textile materials that would prevent bites, depending on their thickness and pore size. Researchers said they believe the materials could be effective against other mosquito species in addition to A. aegypti because of similarities in biology and biting behavior.

“There are different uses for clothing,” said the study’s first author Kun Luan, postdoctoral research scholar of forest biomaterials at NC State. “The idea is to have a model that will cover all possible garments that a person would ever want.”

To test the accuracy of their model, the researchers tested the materials predicted to be bite-proof. In experiments with live, disease-free mosquitoes, the researchers surrounded a blood reservoir with plastic materials made according to parameters predicted by the model. They then counted how many mosquitoes became engorged with blood.

One material they initially tested was very thin – less than one millimeter thick – but had a very small pore size to prevent the mosquito from sticking its mouth parts, or proboscis, through the material. Another material had a medium pore size to prevent the mosquito from inserting its head through the textile far enough to reach the skin; and a third material had larger pores, but was sufficiently thick that the mosquito’s mouth still couldn’t reach the skin.

In a subsequent test, the researchers chose a series of knitted and woven fabrics that met the bite-proof parameters determined by the model, and validated they worked in experiments using both the blood reservoir and human volunteers. The researchers tested the number of bites received by volunteers when study participants inserted an arm covered by a protective sleeve into a mosquito cage. The researchers also compared the fabrics’ ability to prevent bites and repel mosquitoes to fabrics treated with an insecticide.

From what they learned in early experiments, researchers developed the bite-resistant, form-fitting undergarment made with a thin material, as well as a long-sleeved shirt, which was initially envisioned as a combat shirt for the military.

When a volunteer wore the garments sitting for 10 minutes and standing for 10 minutes in a walk-in cage with 200 hungry mosquitos, the volunteer found the combat shirt was 100 percent effective at preventing bites. In the first trial testing the base layer, the volunteer received bites on the back and shoulders – seven bites for 200 mosquitoes. The researchers attributed the bites to the fabric stretching and deforming, so they doubled the material layer around the shoulders, and were ultimately able to prevent 100 percent of bites. They also tested the clothing for comfort, and to see how well it trapped heat and released moisture.

“The final garments that were produced were 100 percent bite-resistant,” said Michael Roe, William Neal Reynolds Distinguished Professor of Entomology at NC State. “Everyday clothing you wear in the summer is not bite-resistant to mosquitoes. Our work has shown that it doesn’t have to be that way. Clothes that you wear every day can be made bite-resistant. Ultimately, the idea is to have a model that will cover all possible garments that person would ever want – both for the military as well as for private use.”

The study, “Mosquito-textile physics: A mathematical roadmap to insecticide-free, bite-proof clothing for everyday life,” was published online July 13, 2021, in the journal Insects. It was authored by Luan, Roe, West, Charles Apperson, Marian McCord, Emiel DenHartog, Quan Shi, Nicholas Travanty, Robert Mitchell, Grayson Cave, John Strider and Youngxin Wang from NC State University and Isa Bettermann, Florian Neumann and Tobias Beck from Aachen University, Germany. The study was supported by the National Science Foundation, the Department of Defense Deployed War Fighter Program, Natick Contracting Division of the U.S. Department of Defense, the Chancellor’s Innovation Fund at NC State, the Southeast Center for Agricultural Health and Injury Prevention, PILOTS and the NC Agriculture Research Experiment Station.

-oleniacz-

Note to editors: The abstract follows.

“Mosquito-textile physics: A mathematical roadmap to insecticide-free, bite-proof clothing for everyday life”

Authors: Kun Luan, Andre J. West, Marian G. McCord, Emiel DenHartog, Quan Shi, Isa Bettermann, Jiayin Li, Nicholas V. Travanty, Robert D. Mitchell III, Grayson L. Cave, John B. Strider, Yongxin Wang, Florian Neumann, Tobias Beck, Charles S. Apperson and R. Michael Roe.

Published online in Insects on July 13, 2021.

DOI: 10.3390/insects12070636

Abstract: Garments treated with chemical insecticides are commonly used to prevent mosquito bites. Resistance to insecticides, however, is threatening the efficacy of this technology, and people are increasingly concerned about the potential health impacts of wearing insecticide-treated clothing. Here, we report a mathematical model for fabric barriers that resist bites from

Aedes aegypti mosquitoes based on textile physical structure and no insecticides. The model was derived from mosquito morphometrics and analysis of mosquito biting behavior. Precision polypropylene plates were first used to simulate woven and knitted fabrics for model validation.

Then based on model predictions, prototype knitted textiles and garments were developed that prevented mosquito biting and were tested for comfort. Our predictive model can be used to develop additional textiles in the future for garments that are highly bite-resistant to mosquitoes.

_____________________

For more:

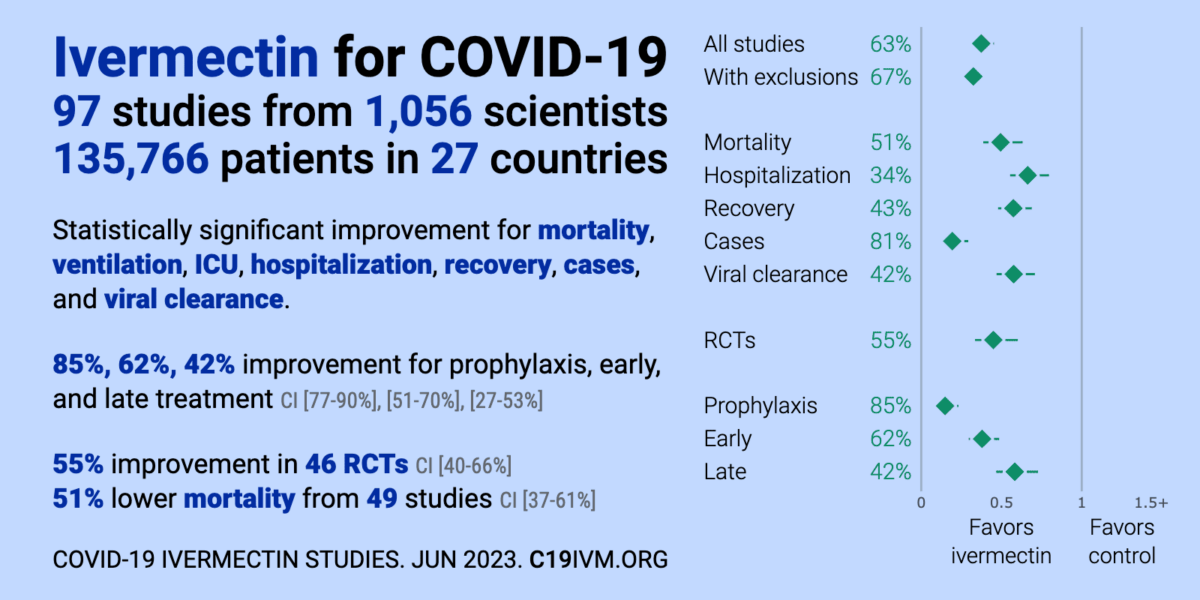
The Story of Ivermectin & COVID-19 “Must See” Video

**UPDATE Feb. 21, 2022**

It’s gotten so bad, state attorney generals have had to call out the FDA, CDC, Fauci, and the media for ‘fueling confusion and misinformation’ by interfering with the treatment of COVID patients.  Both Nebraska and Oklahoma doctors are now free to prescribe off-label medications such as ivermectin and HCQ for COVID without fear of disciplinary action from corrupt groups like the AMA and state medical boards.

This legal action needs to happen in each and every state in the U.S.

https://www.bitchute.com/video/cv86JlBir91g/  Video Here Approx. 25 Min.

The Story of Ivermectin & COVID-19

The story of the powerful players colluding together to suppress any knowledge of a drug that could end the pandemic

This “must see” video not only goes through Ivermectin research but reveals the players censoring it, while pushing their own lucrative drug Remdesivir which doesn’t work.

The story is actually a familiar one to Lyme/MSIDS patients.

Regarding COVID, a similar smear campaign occurred over hydroxychloroquine (HCQ) in which a fraudulent study had to be retracted from a prestigious science journal. Currently, the FDA , DOJ, AMA, APhA, ASHP are trying to ban any treatments that help with COVID, but support mandated COVID injections, despite the record-breaking adverse reactions such as antibody dependent enhancement, microclotting, risk of prion and parkinson’s disease, and deaths. These injections are less than 1% effective when absolute risk is taken into account. Conflict-riddled ‘authorities’ are completely ignoring natural immunity, and have manipulated data to blame the pandemic on the unvaccinated when it is the “vaccinated” who are driving COVID to mutate and causing the explosion in ‘break-through cases‘ resulting in hospitalization and death, which have been vastly underreported.

  • The author points out that Fauci made the unusual move of announcing at a press conference from the White House in April, 2020 that the anti-viral Remdesivir for COVID diminishes time to recovery.  He doesn’t discuss mortality at all. 
  • NIAID (where Fauci works) actually paid for the NIH study he alludes to.  Being fully aware of the study he also knew that midway through it the primary end-point was changed from mortality to time to recovery. This was obviously done because researchers saw that remdesivir had no significant impact on mortality. Changing endpoints midway in a study should raise a lot of red-flags.
  • Meanwhile, using evidence based on much larger studies, the WHO did not recommend remdesivir as they stated that there is no evidence that it improves survival or any other metric in patients.
  • ‘Slight of hand’ statistical trickery such as:
    • changing study end points
    • using non-infection efficacy numbers
    • and omitting absolute risk are continually being used to mislead the public into believing the accepted narrative that HCQ and Ivermectin are ineffective and/or dangerous, but that the COVID-19 injections are safe and effective.
  • Remdesivir is manufactured by Gilead Sciences, a California-based company which has been accused of bioterrorism.
  • The video then explains how at least 7 members of the COVID-19 treatment panel have financial ties to Gilead Sciences.
  • The three co-chairs who select the other panel members do not disclose financial ties to Gilead, but two of the chairs both receive financial support from Gilead. The third co-chair was one of the authors of the NIAID funded remdesivir study.  His name is not listed as a study author, you have to dig for it by looking at the financial disclosure form of conflicts of interest.
  • These conflict-riddled panelists push the drug they make money from but know full well it has no effect on COVID-19 survival. This is professional negligence of the worst sort that has potentially resulted in millions of deaths globally.
  • They choose to suppress ivermectin with study after study proving its effectiveness on mortality, and push their own ineffective drug.
  • Similarly to how Sweden has acted as a placebo arm in this vast evil experiment by refusing to lock down and force masks, resulting in ZERO COVID deaths, the state of Uttar Pradesh, India, which has about 70% of the U.S. population, chose to authorize ivermectin for those testing positive, for their primary contacts and for health care workers. Ivermectin brought COVID deaths down to ZERO.
  • Ivermectin could have ended the pandemic LAST SUMMER.
  • The suppression and censorship of Ivermectin is a crime.
Spread the word.  Effective treatments are purposely being withheld from the public causing needless deaths.

Teaching Physical Therapists When and How to Suspect Lyme Disease

https://www.lymedisease.org/shea-physical-therapists-lyme/

Teaching physical therapists when and how to suspect Lyme disease

By Jennifer Shea, PT, ATC-R

I practiced physical therapy for many years prior to becoming ill with Lyme disease and babesiosis. My education included a course in clinical pathology and a unit on infectious disease.

Less than one page in my medical textbooks was devoted to Lyme disease. The text described an acute flu-like illness experienced by individuals following a tick bite.

Key diagnostic features included a bull’s eye rash, facial nerve palsy and a swollen knee. Treatment consisted of a short course of doxycycline. It all seemed pretty straight forward. It wasn’t until I contracted the disease myself that I began to understand its elusive nature.

Unrecognized Lyme disease?

Reflecting back on my career, I recall several patients whom I treated that likely had Lyme disease and/or co-infections. I failed to recognize it at the time.

One patient had been diagnosed with fibromyalgia. As I examined her, she couldn’t tolerate even the lightest touch due to skin sensitivity. She reported profound weakness, fatigue, muscle twitching, and wandering joint pain.

In an effort to improve her strength and endurance, I developed a treatment plan involving gentle aquatic exercise. The water would provide resistance she could tolerate, and the buoyancy could be used to our advantage. She appeared to do well at our first session but chose not to return. She explained that despite the gentleness of the intervention, she experienced overwhelming fatigue and malaise after any type of exercise.

Another patient came to the clinic with a diagnosis of neck pain. Patients can often associate the onset of symptoms with a precipitating event, but this patient’s pain came on gradually and without apparent cause. X-ray and MRI results were normal except for mild age-related changes. The location of her pain shifted randomly, moving from the upper to the lower neck region appearing on the right one day and the left another.

Typically, patients experience symptoms that improve or worsen in a predictable pattern associated with posture, repeated movements, or activities, but this patient’s symptoms fit no such pattern. She experienced numbness and tingling that migrated. During several treatment sessions, she complained of intense headaches and felt generally unwell due to a virus she recently caught that she “just couldn’t shake.” Whenever she appeared to improve in response to treatment, she would regress for reasons unknown.

Horowitz symptom questionnaire

I’ll never know if those patients had Lyme disease. At the time, I didn’t know enough about the disease to consider it as a possible underlying cause for their symptoms.

Today I am alert to its varied manifestations and have the benefit of using a tool called the Horowitz Multiple Systemic Infectious Diseases Syndrome Questionnaire to help sort things out.

The Horotwitz questionnaire has been shown to be a valid, efficient, and low-cost screening tool to assist practitioners in deciding if additional testing is needed to distinguish between Lyme disease and other illnesses. The results of a 2017 study showed that this questionnaire accurately differentiated those with Lyme disease from healthy individuals. It can be used by medical practitioners or laypersons.

According to the CDC, some 476,000 individuals in the United States are diagnosed and treated for Lyme disease annually. According to MyLymeData, most patients see more than four physicians prior to being diagnosed, and 36% do not receive a diagnosis before at least six years of illness.

It’s reasonable to assume that many individuals with Lyme disease who have not yet been diagnosed seek physical therapy services to address the manifestations of the infection. Given that early treatment is associated with better outcomes, raising awareness among health care professionals is imperative.

It’s also important to make people aware of the limitations of diagnostic testing and that they have a choice when seeking treatment. They can choose to be treated under the guidelines set forth by the Infectious Diseases Society of America or those established by the International Lyme and Associated Diseases Society.

Early diagnosis is critical

To that end, I wrote an article that was recently published in Physical Therapy Journal to guide physical therapists in the recognition and referral of individuals with suspected Lyme disease. I hope that by educating physical therapists about the disease, many individuals will be diagnosed sooner than they might be otherwise.

Click here to read the article in Physical Therapy Journal.

Click here for the Horowitz Questionnaire: MSIDS-QUESTIONNAIRE-FINALR

Jennifer Shea, PT, ATC-R is a retired adjunct faculty member of Springfield College in Massachusetts.

References

Shea J. Physical therapist recognition and referral of individuals with suspected Lyme disease. Physical therapy. 2021;101(8). doi:10.1093/ptj/pzab128

Horowitz RI. Horowitz Lyme Questionnaire. CanGetBetter. Accessed February 12, 2021. https://cangetbetter.com/wp-content/uploads/2021/02/MSIDS-QUESTIONNAIRE-FINALR.pdf

Citera M, Freeman PR, Horowitz RI. Empirical validation of the Horowitz multiple systemic infectious disease syndrome questionnaire for suspected Lyme disease. Int J  Gen Med. 2017;10:249-273. doi: 10.2147/IJGM.S140224

_________________

**Comment**

While treatment wasn’t the focus of this article, please understand it would be very unwise to “choose” IDSA Lyme treatment, as you will be given an insufficient course of doxycycline. This abysmal, monotherapy has shown to fail in nearly every antibiotic study ever done for the simple reasons that Lyme is a persistent, stealthy pathogen, and it rarely comes alone. 

Far wiser, is to locate a Lyme literate doctor specifically trained in tick-borne illness who appreciates and understands the complexities of treating this monster. These doctors diagnose and treat clinically based upon symptoms, not an antiquated, faulty test that misses anywhere from 50-90% of cases.

If you are new to this game, please read the sordid back-story and why there is polarization within the medical community on nearly every aspect of the illness. 

WARNING: Regarding tick-borne illness, all you will get from mainstream medicine is heartache, abuse, and poverty.

Former ‘Bachelor’ Contestant Reveals Lyme Disease Diagnosis in Emotional Video

https://www.today.com/health/kelley-flanagan-reveals-lyme-disease-diagnosis-emotional-video-

Former ‘Bachelor’ contestant reveals Lyme disease diagnosis in emotional video

Kelley Flanagan, who competed for Peter Weber’s heart on season 24 of “The Bachelor,” told fans she knew something had felt “off.”

Former “Bachelor” contestant Kelley Flanagan has revealed she’s been diagnosed with Lyme disease.

The attorney, who competed for Peter Weber’s heart on season 24 of the ABC reality dating series and later rekindled her romance with him, shared her health update in an emotional selfie Instagram video on Monday. (Warning: Flanagan’s video contains profanity)

(See link for article and video)

____________________

**Comment**

The fact she mentions her two brothers are infected that that she’s been more sensitive to things since she was young should hopefully direct her and her doctor to consider congenital transmission as a possibility.

True Colors of AMA, APhA & ASHP Show After Going on Warpath Against Ivermectin: Doctors Threatened Yet Again for Spreading COVID “Misinformation”

Doctors Are Not Trained to Be Critical Thinkers

According to journalist and author Robert Whitaker who wrote “Anatomy of an Epidemic: Magic Bullets, Psychiatric Drugs, and the Astonishing Rise of Mental Illness in America”, and who was in the documentary “Medicating Normal,” doctors are trained to accept whatever is the wisdom of the day, which changes due to politics.  Whitaker reveals how false science has invaded woke medical schools that offer modules on “climate change” and “equity” but won’t touch critical issues for health, and how journals are being exploited by drug companies that bury trial data making drugs appear more effective than they really are. Academic researchers are contracted to sign their names on pharmaceutical industry publications but are not allowed to look at the raw data being used to craft conclusions.  It has been repeatedly and firmly established that Big Pharma funded research strongly biases published results favoring the company’s products, and the whopping 40% of published drug articles that are “ghost managed” during key marketing periods, amplifies this bias.

When you understand these pertinent facts, it becomes easier to understand why doctors blindly march in line behind the corrupt American Medical Association which is run by a powerful private, nonprofit mob which has a long history of instructing doctors to deceive patients, monopolizing medicine, and punishing dissenters.  It is the medical mafia.

AMA Releases Statement Against Ivermectin for COVID

The American Medical Association (AMA), the American Pharmacist Association (APhA) and the American Society of Health-System Pharmacists (ASHP) have released a statement strongly opposing the ordering, prescribing, or dispensing of ivermectin to prevent or treat COVID outside of a clinical trial.

“Ivermectin has not been shown to be one of those to be effective for the COVID-19 virus,” Dr. Gerald Harmon, president of the AMA, told MSNBC’s Chris Hayes. Harmon he understands “the zeal” for embracing drugs like ivermectin and hydroxychloroquine for off-label use, but “right now the safest thing for you to do is take the current approved courses … If you require more treatment, there are established safe, very well-approved treatments.”

As for the success of Ivermectin and other protocols for COVID:

I also share our story using it successfully here in the comment section.

Please remember the sordid history of the AMA, founded by true quacks who weren’t even doctors, which seeks to be the exclusive provider of medicine, by eliminating anything it considers a threat. It was found guilty of conspiring against the chiropractic profession.

  • AMA has a long history of attacking any alternative practitioner as a “quack” through their Committee on Quackery, and using the full weight of their AMA Journal to expose the practitioner as a fraud in order to stop their work.
  • Their consultation clause threatened to expel any physician who consulted with “irregulars.”
  • Doctors wanting to join the AMA had to pledge allegiance to their dogma.
  • The AMA admits it was a racist organization.  In fact, the AMA president practiced vaginal surgeries on enslaved women without anesthesia!
  • AMA’s corrupt “Seal of Approval” on drugs occurred if drug companies made a substantial donation to the AMA.
  • The AMA bought up huge sums of stock on drugs they were about to give the “Seal of Approval” to so once the approval was released stock prices would soar allowing the head of the AMA to reap the rewards.
In short, The AMA does not play nicely with others and now is taking part in a witch hunt against its own.

I just learned that the World Medical Association (WMA), created by the British Medical Association in 1945 and established in Paris in September 1947, controls every medical doctor in the world in medical affairs and practice.

As at 2013, it represented 102 National Medical Associations, 106 Constituent Members and 1013 Associate Members representing more than 10 million physicians around the world.  Today its Secretariat is situated in Ferney-Voltaire, France, adjacent to Geneva so that it can carry out close official relations and help control the UN World Health Organization (WHO). 

Behind the scenes, it is controlled by the world’s biggest pharmaceutical companies, in turn controlled by a handful of incredibly wealthy international banking pirates and the rich families that own them, domiciled mainly in New York and London.

The  same goes for the International Federation of Pharmaceutical Manufacturers & Associations (IFPMA) which represents and controls every pharmaceutical association and pharmaceutical company in the world. Formed in 1968, it is based in Geneva, Switzerland.  It also works closely with the UN.

GO HERE:  HOW WHO, WEF, AND GAVI ARE ALL IN GENEVA, HAVE DIPLOMATIC IMMUNITY, AND SCRATCH EACH OTHER’S BACKS. 

Go here to listen to a brief message by Sayer Ji, founder of Greenmedinfo.com, emphasizing the need for information so people can make the best most informed health decisions. He also admits they and others have been attacked, censored, and deplatformed like never before.  Mainstream media is complicit in all of this.

Proving this point, America’s Frontline Doctors recently released a statement in response to inaccurate and slanderous reporting by Time Magazine and NBC News.  Excerpt:

AFLDS has been maliciously attacked as part of an ongoing, orchestrated effort by media outlets who are making billions from Big Pharma and pandemic-related government advertising. The CDC’s own data debunks the government and pharmaceutical industry’s narrative that only vaccines can save us from from Covid-19. In fact, the CDC’s own numbers reveal the truth, which is that your own immune system can virtually always manage this virus. According to the CDC, even without treatment, the survival rate is 99.98% under age 50 and almost 95% over age 70. Both numbers approach 100% with early treatment.

To further delineate the state of COVID madness in the world, the ACLU on one hand states inmates who were uninformed about being prescribed ivermectin for COVID are prepared to file a lawsuit to halt its use, but out of the other side of its mouth states that forcing people to take “vaccines” is a victory for civil liberties.  Huh?

https://www.medpagetoday.com/special-reports/exclusives

Emergency Medicine Docs Will Face Consequences for Spreading COVID Lies

— ABEM threatens action, echoing warning from Federation of State Medical Boards
A young female physician yells through a megaphone.

Physicians who publicly spread misinformation about the COVID-19 pandemic could be sanctioned by the American Board of Emergency Medicine (ABEM), including potentially losing board certification, the organization said Thursday.

“Making public statements that are directly contrary to prevailing medical evidence can constitute unprofessional conduct and may be subject to review by ABEM. Should ABEM determine that a physician is promulgating inaccurate information that is contrary to the interests of patients and that adversely impacts public safety, ABEM may withdraw or deny certification for that physician,” they stated.

This warning echoes a statement that focused on COVID-19 vaccines specifically from the Federation of State Medical Boards (FSMB) issued earlier this month. Both follow reports of some physicians deliberately spreading misinformation about the pandemic — especially regarding the safety and efficacy of the vaccines.  (See link for article)

____________________

The AMA is not our friend, but is a political organization that wants to monopolize medicine, and cares more about money and power than patients.

Thankfully, State legislators are pushing back against the draconian AMA:

  • Colorado  HB 22-1015 restates a prescriber’s ability to use off-label treatments, including hydroxychloroquine and ivermectin, and would keep licensing boards from disciplining a prescriber or pharmacist for doing so.
  • Florida HB 687 and SB 1184, which would keep state medical licensing boards from disciplining, or threatening to discipline, a medical provider for what they say on social media and other platforms, unless the regulatory board could prove that it resulted in “direct physical harm” of a patient who they’ve treated in the last 3 years.
  • Idaho  HB 613 prohibits a medical licensing board from taking action against a provider for COVID-19 treatment recommendations, including off-label drugs, and also from requiring a provider to report their vaccination status for licensure.
  • Indiana  HB 1372 lets a doctor or an advanced practice registered nurse (APRN) make a standing order for pharmacist to dispense ivermectin, and prevents multiple licensing boards from disciplining a licensee because of the order. The bill also stipulates that no information given out by the pharmacy’s information sheet “may discourage the recipient from using ivermectin for the treatment of COVID-19.”
  • Iowa  SF 2031 protects physicians who prescribe ivermectin or hydroxychloroquine from actions by licensing bodies. HF 2266 lets pharmacists prescribe these drugs with a standing order if they request it, and protects them from any liability if the drugs cause harm.
  • Kansas SB 211 and HB 2280 requires patients wanting an off-label drug to sign a waiver protecting the prescribing physician from liability if any harm occurs. Both bills were referred to the Committee on Public Health and Welfare. Also, SB 381 would allow prescriptions for ivermectin and hydroxychloroquine for COVID, and specifies that a prescription, recommendation, or opinion of a provider related to any COVID-19 treatment can’t be considered “unprofessional conduct.” The bill would also rescind any disciplinary actions related to off-label treatment that started in March 2020. State legislators also pushed for a budget change that would slash the budget for state medical board investigations into prescribers of ivermectin.
  • Kentucky  HB 352 prevents medical boards from disciplining a physician or physician assistant (PA) based on their treatment for COVID-19, including treatments not approved by the FDA, as long as they believe it’s in the best interest of a patient who has given written consent.
  • Missouri  SB 1133 keeps a state medical licensing board from disciplining a provider for dispensing ivermectin or hydroxychloroquine, and also prevents the provider from asking why the patient needs the medication.
  • New Hampshire  HB 1022 prevents licensing boards from taking action against providers for prescribing ivermectin with a standing order. HB 1466 prevents action by licensing boards against physicians for off-label use of FDA-approved drugs or devices.
  • Oklahoma  HB 4294 keeps medical licensing boards from suspending, revoking, or not renewing a license based on a physician’s treatments or recommendations for COVID-19.
  • Pennsylvania  HB 1741 was introduced in July 2021, but tabled in February 2022. The bill states that doctors may prescribe ivermectin and hydroxychloroquine to treat COVID-19, and prohibits the state medical licensing board from disciplining any doctor or pharmacist for using off-label treatments for COVID-19. The wording was later amended to remove the latter language, but kept the language on licensing boards. FSMB publicly opposed this bill, stating, “Restricting a state medical board’s authority to assess the quality of patient care — as this bill would — limits recourse for patients that have suffered harm.”
  • Tennessee  HB 1870/SB 1880 prevents medical licensing boards or subcommittees from taking any disciplinary action against physicans related to COVID-19 treatment, if the provider thinks the treatment is in the patient’s best interest. HB 2506/SB 2621 allows doctors, PAs, and APRNs to prescribe ivermectin, and lets pharmacists dispense it, without facing discipline from licensing boards. HB 2744/SB 2630 stipulates the same for pharmacies to dispense ivermectin and hydroxychloroquine. The state’s medical board pulled their policy with the FSMB language from its website in response to pressure from Republican lawmakers. According to a Tennessee state representative who spoke to MedPage Today previously, the medical board was being given too much power, and he’d heard from doctors in his area that it was “just unheard of and unprecedented that this board of medical examiners would review things that we’re saying.”
  • Virginia  HB 102/SB 711 keep medical licensing boards from disciplining providers who prescribe FDA-approved drugs for off-label use.
  • Washington  HB 2065 allows providers, including naturopathic practitioners, to recommend or prescribe hydroxychloroquine, ivermectin, the steroid budesonide, monoclonal antibodies, zinc, vitamin D, and vitamin C for COVID-19 without facing disciplinary action.
  • West Virginia  HB 4309 lets providers prescribe hydroxychloroquine, chloroquine, or ivermectin off-label; specifies that no action can be taken against prescribers; and that such prescriptions don’t constitute “unprofessional conduct or otherwise grounds for discipline. HB 4455/SB 605 allows pharmacists to prescribe ivermectin through a doctor or APRN standing order, and states that no data on the information sheet about the drug can discourage the use of ivermectin. Medical boards would not be able to take action against the standing orders.
  • Wisconsin  Introduction of a bill that would amend the state statute to protect healthcare providers from any action from their credentialing board in the Department of Safety and Professional Services. The bill proposes that no credentialing board can retaliate, discriminate, or otherwise take any action against a provider for expressing their “professional opinions.”

**Comment**

Just to pound the nail in the coffin, doctors are reminded yet again if they happened to forget, Big Brother is watching them closely and anyone stating anything that isn’t in the accepted narrative script will be hunted down and persecuted. The article goes on to list many of the 20 “notable” super spreader physicians giving this “misinformation,” and that they had yet to be disciplined by their state boards as of last week.

The catch of course is what actually constitutes “misinformation?” Look no further.  ABEM’s Code of Professionalism states:

“ABEM certification requirements for professionalism includes an ethical requirement to … Refrain from conduct that the Board determines, in its sole judgment, to be sufficiently egregious that it is inconsistent with ethical behavior by a physician.”

They clearly spell out that behavior, solely determined by the board to be inconsistent, will result in decertification.

The Federation of State Medical Boards (FSMB) has also stated earlier that doctors and health professionals could be at risk of losing their medical licenses if they spread COVID-19 vaccine misinformation on social media, online and in the media.  Excerpt:

“They also have an ethical and professional responsibility to practice medicine in the best interests of their patients and must share information that is factual, scientifically grounded and consensus-driven for the betterment of public health.”

In essence they are stating that medicine is to be consensus-driven, and anyone outside the group-think will be axed.  
If you are a Lyme/MSIDS patient, please pause here and reflect.  Consensus-driven medicine outlaws anyone who has a different thought or approach in medicine.  Ponder history for just a moment:
  • Remember Florence Nightingale, aka, The Lady With the Lamp, who through organization, cleanliness, and warmth reduced hospital death rate by two-thirds, but defied current convention?
  • How about Dr. Lister, the man who changed the world by hand-washing & cleanliness when ‘experts’ were happily going from surgery to surgery with bloody aprons and without a thought or concern over bacteria.
  • What about Antony van Leeuwenhoek, an uneducated man without a scientific background who was the first to expose the world of bacteria to the ‘experts’?
  • Or better yet, what about the crazy Barry Marshall who defied the ‘stress causes ulcers’ consensus, drank a patient’s organisms in a “cloudy broth”, biopsied his own gut!, and cured it with antibiotics?
  • And more currently, how the Alzheimer’s Cabal that thwarted progress for decades, due to a dogmatic, singular belief in the ‘amyloid hypothesis’ prevented any competing ideas.

Lyme/MSIDS of course fits perfectly into this picture as there are currently two standards of care with continued polarization that doesn’t appear to be changing. Doctors and researchers who do not “toe the line” and follow the antiquated and unscientific CDC/IDSA Lyme treatment guidelines are still being hunted down, persecuted, fined, and can lose their medical license. Wisconsin has a long history with tick-borne illness and represents the first published case in a medical journal. Further, an IDSA founder who was a Wisconsin physician, disagreed with the CDC/IDSA stance and regularly treated his patients with high doses of IV antibiotics for tick-borne illness. We are in the thick of this ongoing battle.

Unfortunately, Dr. Waisbren is no longer with us, but I’m eternally grateful for his, and so many others, willingness to defy consensus-based medicine – fully realizing that the human body is complex and variable. He, and many others, also fully realize that medicine is not nor ever should be “one size fits all,” and will require intelligence and savvy on the part of doctors in treating individual patients.  To show the seriousness of this, just today, there are allegations that a judge stripped a mother of her parental rights until she gets “vaccinated” for COVID.  This judge is not a medical professional and has no clue of her previous medical history of adverse reactions.  The world has truly gone mad.

I would further argue that what started out as “guidelines” have effectively become “mandates” which are preventing doctors from treating the individual.

Please remember that progress would not have been made if these fore-thinking people hadn’t defied consensus medicine. After all, science is continually evolving as evidence becomes available.

But herein lies the catch: evidence must be allowed to be gathered, debated, shared, and tested. 

Now they are shuting down the very people who can, and have found a way out of COVID madness.

Of course, there are guilty people, but not the ones listed by our corrupt public health ‘authorities’, and complicit mainstream medicine, and media.  The FDA and CDC have attacked every single therapy and test presented by others, the latest of which is ivermectin, a cheap, safe, proven drug against COVID with the media playing along by twisting and omitting facts. Rather than focus on the fact ‘authorities’ are bad mouthing and preventing successful treatments, they focus on the fact that desperate patients with nowhere to turn are self-treating with the animal form of ivermectin and are taking too much.  Further, they are completely ignoring the thousands upon thousands who have suffered harm from the COVID jabs and would rather blame “anxiety” for causing anaphylaxis, blood clots, hemorrhaging, heart inflammation, strokes, Bell’s Palsy, convulsions, and myocarditis (among a host of other reactions) rather than the injections.

For 40 years Lyme/MSIDS patients have often been told they were simply imagining their illness.
COVID madness looks a lot like Lyme/MSIDS madness.