“It was like the flu, but for only four days straight,” recalled Allyn, 22, of Skaneateles. “They would test for strep, they would test for mono, and everything would be negative. We thought it was just some weird virus.”
Every few months, the fever returned and disappeared after four days. Until the fall of 2017, when Allyn was a junior at Colgate. This time, the fever stayed, and brought along fatigue and excruciating pain in her joints and muscles.
“You know when you have the flu and your body aches? It was like that times a million,” said Allyn, who was a runner in high school. “I was an extreme athlete, and I couldn’t walk up my stairs to my room anymore. We could tell something was terribly wrong.”
The quest to understand what was wrong, and how to cure it, has consumed Allyn’s life. Since that first fever, Allyn has suffered severe migraines, tingling in her arms and legs that felt like bugs crawling beneath her skin, extreme fatigue, heart palpitations, shortness of breath so constricting that she gasped for air after a flight of stairs, inability to concentrate, and anxiety attacks that convinced her she was dying.
Allyn has seen neurologists, Lyme disease specialists, acupuncturists and chiropractors. She’s been diagnosed with strep throat, chronic fatigue syndrome and Lyme disease. She took dozens of supplements and antibiotics, drank celery juice every morning for four months, and even shut herself inside a claustrophobic hyperbaric chamber in Florida.
Nothing worked.
No one could understand what had turned a star high school athlete into a young woman so sick she couldn’t climb the 10 stairs to her childhood bedroom, or why she wasn’t getting better.
“Those are the darkest days, when you’re trying everything and nothing is working,” said Allyn’s mother, Meg O’Connell. “As a parent you want to shake the doctors and say, ‘You have to take care of my child right now!’”
Finally, this summer, Allyn got a definitive answer. She was diagnosed as one of the first two people in Central New York to contract an emerging tick-borne disease called miyamotoi.
Miyamotoi is so new that, unlike Lyme disease, it doesn’t have a common name, but is referred to simply the species of the bacterium that causes it. It’s in the same genus as the Lyme bacterium, but is more closely related to a group of diseases known as tick-borne relapsing fever.
Tick populations are increasing in Upstate New York, and they are bringing debilitating disease to tens of thousands of people. If it wasn’t bad enough that deer ticks already carried six bacteria and viruses, they and miyamotoi have now evolved to add a new weapon to the arsenal.
Miyamotoi infections were first found in humans in 2011 and confirmed in the Northeast in 2013. Scientists are still studying how it’s transmitted, and many doctors are unfamiliar with the disease, said Brian Leydet, a professor and tick expert at SUNY College of Environmental Science and Forestry, in Syracuse.
“That’s what’s terrifying about it: knowing so little about it, and it’s in our back yard,” Leydet said.
Like many people suffering from tick-borne diseases, Allyn doesn’t remember being bitten. She suspects she picked up the tick while hiking or running trails, and that it hid beneath her long blond hair. Ticks seek out hard-to-see places on the body, like the scalp or behind the knees, and then attach to the skin for 24 to 48 hours, sucking blood and disgorging pathogens.
Allyn also doesn’t remember the date of the first fever, but she lucidly recalls the day the illness took over her life: Oct. 6, 2017, a date she mourns each year. She was walking down the long hill from Colgate to the village of Hamilton when she was overcome with pain and massive fatigue.
“I had to sit down because I didn’t think I could walk the rest of the way home,” she recalled. “I was just having shooting pain all through my muscles and knees and elbows. It felt like everything was breaking in my body.”
She couldn’t focus enough to drive, so her parents brought her home to Skaneateles. She saw a nurse practitioner in Syracuse whom Allyn had worked for, Carolyn Christie-McAuliffe. She drew 30 vials of blood, Allyn recalled.
Allyn returned to Colgate, hoping it was just a case of mononucleosis that would go away so she could finish her junior year. Then the test results came in. The first one, Allyn recalled, counted the markers of inflammation in her body.
“The normal range is about 40 to 60. Mine was 800,” she said. “Carolyn called me and said, ‘You have to go home immediately. Something is really wrong.’”
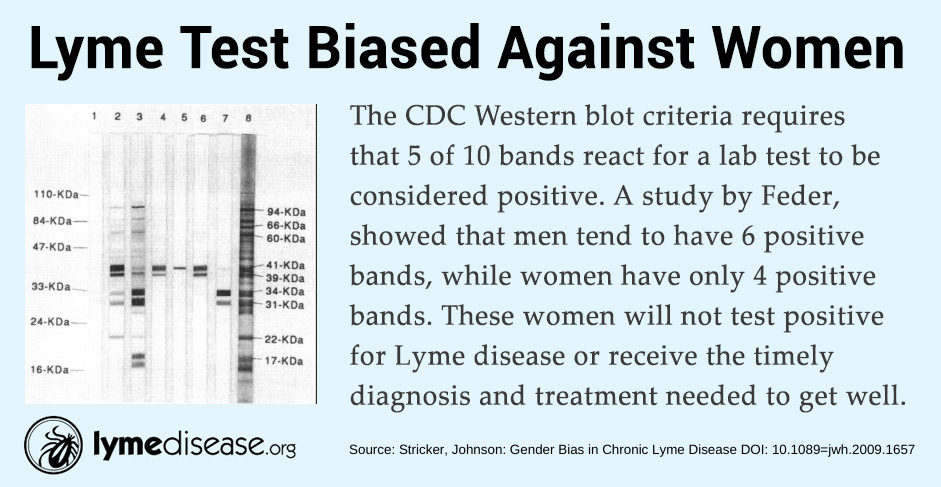
Allyn took a medical leave from Colgate and returned home yet again. Three days later McAuliffe called with a diagnosis: Lyme disease. There was something odd about the test results, though, that would later become an important clue. While the initial screening test was positive for Lyme, the confirmatory test, called the Western blot, was abnormal, but negative for Lyme, Allyn said.
Allyn went on a four-week course of doxycycline, the standard regimen for Lyme patients. She only felt worse; now the disease was enveloping her brain in a fog.
“I would wake up every morning and not remember what I did,” she recalled. “I’d be watching a TV show I’d been watching for years and I wouldn’t know what was happening. I couldn’t read because I couldn’t concentrate, and I couldn’t really understand words. Most of the days I would lay awake in bed staring at the wall.”
The shattering knee and elbow pain returned. She had “horrible migraines.” She was short of breath and her heart started skipping beats. Her legs and arms tingled with pins and needles. Sitting home alone, Allyn developed paranoia and panic attacks, calling her parents in the middle of the day to say she was dying.
O’Connell remembers her own pain watching her daughter’s.
“It’s just so sad to see someone struggle for two-plus years,” said O’Connell, executive director of the Allyn Foundation. “When you have an ill child, you just want to take that burden from them. You ask, ‘Why couldn’t that have happened to me instead?’”
O’Connell had joined the CNY Lyme and Tick-Borne Disease Alliance. At an early meeting of the alliance, O’Connell met Dr. Kris Paolino, a new physician at Upstate Medical University who specialized in Lyme cases. Paolino, an infectious disease specialist, had helped develop vaccines for Ebola and malaria at the Walter Reed Army Institute of Research in Washington, D.C.
“I happened to say to him that my daughter has Lyme and we can’t get rid of these fevers,” O’Connell recalled. “He said, ‘Make an appointment and come see me.’”
At that first appointment, Allyn recounted her frustrating and painful journey.
“The main thing I try to do is to listen to the patient’s story first,” said Paolino, hired in 2016 as part of Upstate’s battle against the growing threat of tick-borne disease. “In many cases you’re trying to figure out what’s real and what’s not.”
As Allyn’s story unfolded, Paolino noted the clues that raised doubt about the Lyme diagnosis: the relapsing fevers, the neurological symptoms, and that ambiguous Western blot test.
Those suggested miyamotoi. Another round of tests confirmed it.
“I’m not sure if she had ever had Lyme,” Paolino said. “I think it was probably miyamotoi all this time.”
It’s not hard to understand why doctors would suspect Lyme over miyamotoi. The abnormal Western blot test result after a positive Lyme test can be confounding, and miyamotoi is almost unheard of. Just 10 cases of miyamotoi were reported to the state health department from 2001 to 2016, compared to nearly 80,000 cases of Lyme disease.
Paolino said he has now four miyamotoi patients.
“I think there’s probably more people that are undiagnosed than we think,” he said. “It is a fairly new emerging pathogen in the region.”
Paolino prescribed an intense regimen of intravenous antibiotics for Allyn. First doctors inserted a thin tube that ran from Allyn’s upper right arm to her heart. Every night for seven weeks, she said, she spent a half hour pumping two syringes of the antibiotic ceftriaxone into the tube.
The treatment seems to be helping, Allyn and O’Connell said.
“As Dr. Paolino said, ‘Don’t go out and run a marathon yet,’ but we have been really encouraged,” O’Connell said. “She has not had a fever, her blood work is better, her glands are not swollen. She can take longer walks. It will still be another six to 12 months to build up her body because all of it’s been through, but I would say we’re hopefully optimistic.”
No one knows yet if Allyn is cured, what damage the years of treatments might have caused, or if her symptoms will linger even if the bacteria are gone. Paolino said there’s reason for optimism because relapsing fever diseases similar to miyamotoi can be cured by antibiotics. Miyamotoi is so new, however, there’s little research on how patients fare if the disease has been left untreated for years.
“The longer the symptoms are present, you see more damage to the nerves and more damage to the joints that could be more of an irreversible process,” Paolino said. “The hope is that she’ll continue to feel well and she won’t relapse, but I don’t have a definitive answer.”
Fatigue remains a constant presence, Allyn said, but she is slowly regaining strength. She can take her 8-month-old German shepherd, Oaklie, for two walks a day now. She has been attending Colgate part-time, and can do homework in the morning before she gets too tired.
“I’ve gotten a little bit better, but how much better will I get?” she wonders.
It’s time, she said, to find out. On Saturday, she and her boyfriend moved to Boulder, Colorado, where Allyn has an aunt and uncle. She plans to complete her Colgate degree in education and cellular neuroscience by taking her final three classes at the University of Colorado. She’s not ready for a 9-to-5 job, and doesn’t know when she will be, but she hopes to start part-time in a café or bakery. And as she gets stronger, Allyn hopes to put on skis and hiking boots again.
“Life is so short and you could get sick any day,” she said. “Why not go for a hike or go skiing?”
__________________
For more: https://madisonarealymesupportgroup.com/2018/08/17/borrelia-miyamotoi-found-to-occur-nationwide-in-japan/
https://madisonarealymesupportgroup.com/2018/02/15/b-miyamotoi-in-ca-ticks-for-a-long-time/The following article explains that Borrelia Miyamotoi is not new to California.
First considered nonpathogenic, it wasn’t even reported until 2011 in Russia. http://www.nejm.org/doi/full/10.1056/NEJMc1215469 Diagnosis relies on PCR testing during acute infection and two-tiered testing for Lyme will not pick it up.
It is not a reportable illness so prevalence is pure conjecture.
Dr. Horowitz states clinicians should be vigilant for clinical pictures that look like viral infections such as high fever, headache, and muscle and joint pain.
In publications, only 16% of patients presenting with BMD were seropositive for IgG and/or IgM antibody to B. miyamotoi rGlpQ, so PCR should also be considered in patients with a history of tick bites and appropriate clinical manifestations.
This is also an important reminder that new strains and species are being discovered continually, so nothing about Tick Borne Illness should be set in stone and open minds are a must.
https://madisonarealymesupportgroup.com/2018/02/14/borrelia-miyamotoi-in-ca-serodiagnosis-is-complicated-by-multiple-endemic-borrelia-species/ (Study found here)
https://www.lymedisease.org/lyme-sci-study-finds-lots-b-miyamotoi-california-ticks/