The Coronavirus disease 2019 (COVID-19) pandemic was marked by an increase in diagnosis and treatment delays for a range of medical conditions. Yet the impact of the pandemic on the management of tick-borne diseases, which frequently manifest as an acute febrile illness similar to COVID-19, has not been well described.
Methods
In this retrospective cohort study of patients with suspected tick-borne disease attending the University of North Carolina Health facilities, we compared the timeliness of diagnosis and treatment in a “pre-COVID” period (March 2019 to February 2020) and a “post-COVID” period (March 2020 to February 2021). Participants included patients with an ICD-10 diagnosis code of spotted fever group rickettsiosis or ehrlichiosis and a positive Rickettsiarickettsii or Ehrlichia indirect immunofluorescence assay immunoglobulin G antibody test result. Of the 897 patients who had an eligible diagnosis, 240 (26.8%) met the inclusion criteria. The main outcome was time from initial presentation to definitive diagnosis and treatment.
Results
During the 2-year study period, 126 (52.5%) patients were grouped in the pre-COVID period and 114 (47.5%) were grouped in the post-COVID period; 120 (50.0%) were female; and 139 (57.9%) were aged > 50 years. Comparing the post-COVID to the pre-COVID period, the adjusted odds ratio (aOR) for delay in treatment > 0 days was 1.81 (95% confidence interval [CI] 1.07–3.07, P = 0.03), and for a treatment delay > 7 days, 1.65 (95% CI 0.94–2.90, P = 0.08). The odds of a delay in diagnosis were similar for patients in the post- and pre-COVID periods, with an aOR of 1.61 (95% CI 0.96–2.72, P = 0.07) for delays > 0 days, and aOR of 1.72 (95% CI 0.99–3.00, P = 0.05) for delays > 7 days.
Conclusions
The odds of a delay in treatment > 0 days were significantly higher in the post-COVID period than in the pre-COVID period. However, the odds of a delay in treatment > 7 days, or a delay in diagnosis, were similar between these two periods. Shifts in care-seeking, alternative care delivery models and prioritization of COVID-19 may contribute to diminished timeliness of treatment for patients with tick-borne diseases.
Borrelia burgdorferi, the causative agent of Lyme disease, has a highly reduced genome and relies heavily on glycolysis for carbon metabolism. As such, established inhibitors of lactate dehydrogenase (LDH) were evaluated in cultures to determine the extent of their impacts on B. burgdorferi growth. Both racemic and enantiopure (AT-101) gossypol, as well as oxamate, galloflavin, and stiripentol, caused the dose-dependent suppression of B. burgdorferi growth in vitro. Racemic gossypol and AT-101 were shown to fully inhibit spirochetal growth at concentrations of 70.5 and 187.5 μM, respectively. Differences between racemic gossypol and AT-101 efficacy may indicate that the dextrorotatory enantiomer of gossypol is a more effective inhibitor of B. burgdorferi growth than the levorotatory enantiomer. As a whole, LDH inhibition appears to be a promising mechanism for suppressing Borrelia growth, particularly with bulky LDH inhibitors like gossypol. (See link for article)
_______________
**Comment**
Lactate dehydrogenase inhibitors (LDH) are used in various assays for cancer and other research areas. They are also a promising target for cancer therapy.
SAPI2022AONM_221203_013821 Go here for Eva Sapi’s slides titled, “Potential Connection of Borrelia Infection and Breast Cancer“. She also addresses “Mixed Biofilm in Other Infected Skin Tissues.” There is a particular slide that shows where in the human body that Borrelia biofilm is found.
Numerous studies indicate that it is not the free alpha-gal sugar that is responsible for alpha-gal syndrome, more commonly known as red meat allergy, but the attached tick proteins — and not just from the lone star tick.
By Angelo DePalma, Ph.D.This article was originally published by The Defender — Children’s Health Defense’s News & Views Website.
Editor’s note: This is part 3 (read part 1 and part 2) of a three-part series on red meat allergy, a serious, lifestyle-limiting disorder that causes individuals to experience mild- to life-threatening allergic symptoms several hours after eating red meat. Also known as alpha-gal syndrome (AGS), meat allergy has no cure — the only “treatment” is to avoid certain meats and animal products.
However, the alpha-gal sugar by itself does not cause AGS.The culprit is specific proteins in tick saliva attached to alpha-gal. Since none of the four “ingredients of concern” discussed in part 2 — gelatin, albumin, glycerin, and stearate — contain tick proteins, they cannot induce AGS.
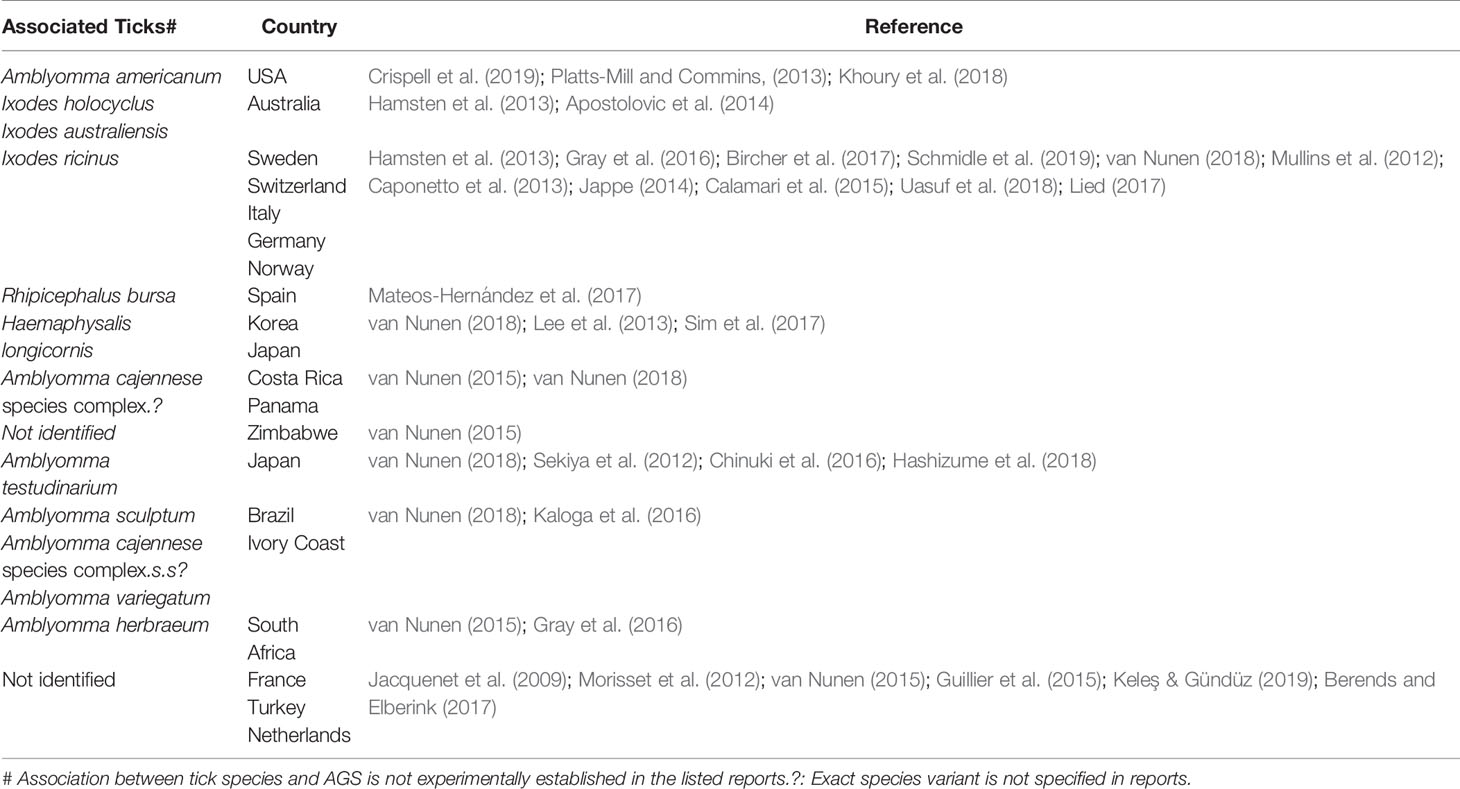
More than 35 studies conducted in 19 countries have established the tick-AGS connection.
Additional studies strengthen the AGS-tick-protein connection. A 2015 Japanese paper reported that 24 of 30 patients with red meat allergies were sensitized to a specific alpha-gal-linked protein in tick saliva.
Two drugs mentioned in part 1, heparin (a blood thinner) and cetuximab (a cancer drug), may cause serious reactions in individuals with AGS but these episodes are similar to reactions after eating meat: they are a manifestation of AGS, not the cause. If they caused AGS this effect would be widespread among people taking these drugs, and would certainly have been noticed decades ago.
We also noted in parts 1 and 2 the special case of gelatin, a common ingredient in drugs and vaccines, which also causes allergic reactions in individuals with AGS.Since the alpha-gal sugar can only cause AGS when it is attached to specific tick proteins, gelatin by itself is highly unlikely to cause the illness.
If gelatin in injected drugs caused meat allergy someone would have noticed decades before 2009, when AGS was first described.
Another clue that alpha-gal protein, and not sugar, causes AGS is the unusual hours-long delay in symptomatology after eating meat. In contrast, allergies to common foods usually occur within minutes of exposure.
According to one hypothesis, alpha-gal attached to fats, as opposed (or in addition) to proteins, may be responsible for the delayed allergic response because fats take longer to digest than proteins.
Another possible explanation for the delay is the time required to digest meat, remove alpha-gal, and attach it to another molecule that can carry it into and through the bloodstream.
Some evidence suggests that after digestion and release, alpha-gal enters the bloodstream either directly attached to or surrounded by fats.
How about injectable drugs, like vaccines?
We also know from parts 1 and 2 that many vaccines contain alpha-gal, so connecting AGS to vaccines seems reasonable.
But if vaccination caused AGS the association would have been apparent decades ago.
Meat allergy is still extremely rare, with only around 110,000 “suspected cases” reported in the U.S. in the 13 years between 2010 and 2022. This calculates to fewer than 8,000 cases per year, or an incidence of about 2.5 cases per 100,000 people per year (based on the average U.S. population of 310 million during that time period).
During those same 13 years, Americans received more than a billion vaccine doses, including 667 million COVID-19 shots.
There are approximately 50 million U.S. children ages 12 and under. The Centers for Disease Control and Prevention (CDC) vaccination schedule lists 29 different injections through age 6 (excluding COVID and flu), and compliance is between 80% and 90% for the various shots.
This means U.S. children in that age group have already received more than 1.2 billion vaccine doses.
About half the U.S. population receives a flu shot annually. Over those 13 years, Americans received more than 1.86 billion flu shots.
Adding up all the doses (and for now ignoring all other vaccinations) and dividing by 12 years, we see that every year Americans receive, on average, 311 million doses of vaccines but experience just 8,000 cases of meat allergy.
That comes out to 1 case of meat allergy for every 39,000 shots.
Also, note that the four “ingredients of concern” have been used in oral and injected medicines for decades, but meat allergy has been known only since 2009. If exposure to gelatin, albumin, stearate and glycerin caused meat allergies to any significant degree this would surely have been noticed before 2009.
Finally, all biotech therapies at some point use products from cows to sustain the engineered cells that express these products. Although many processes have switched to animal-derived component-free cell culture media, 64% of current biomanufacturing processes still use “classical media,” which include bovine-derived ingredients.
Recombinant protein treatments have been used since the mid-1980s, and virtually all are injected or infused, typically at very high doses.
If injected cow-derived vaccine ingredients caused meat allergies they would have been identified and confirmed long before 2009.
This is not to vouch for the safety of vaccines generally but to emphasize that avoiding vaccines will not protect you from meat allergies.
One could also argue that, like the “four ingredients of concern” in vaccines and other injected drugs, tick species that transmit AGS have also been around for eons. If they were the sole cause of meat allergy someone should have noticed before 2009.
The same could be said for Lyme disease, which was first described in the medical literature in 1975 after a cluster of cases emerged around Lyme, Connecticut. The infectious Lyme agent, a bacterium, was only identified in 1981.
But according to genetic studies that microbe — the Lyme spirochete — has been around for at least 60,000 years. A sharp rise in the deer population, particularly in the northeastern U.S., has increased the natural host population for Lyme-carrying ticks. At the same time deforestation has brought people and deer — and the ticks they carry — closer together.
These factors might also explain the mysterious emergence of AGS in 2009 although ticks have been plaguing humans since Biblical times.
What if you’re not in ‘lone star territory’?
The lone star tick is found primarily in about 30 U.S. states within a geographic region bounded by Maine at its northeast corner, Florida (southeast), Texas (southwest) and Missouri (northwest).
This creature shares its extensive habitat with about half the U.S. population, as shown in Figure 1:
Figure 1. Habitat of the lone star tick. Credit: Centers for Disease Control and Prevention.
But AGS is a worldwide problem and in every instance, an endemic tick is the culprit.
Separate alpha-gal-carrying tick species have been found in Japan, Sweden and Australia. In the U.S., at least four tick species other than the lone star tick have been implicated.
A 2019 study confirmed three of these and added a fifth species to the suspect list.
So tick bites generally, and not the lone star tick, in particular, appear to be responsible for alpha-gal sensitization.
The message to people who enjoy the outdoors is simple: living outside the lone star tick habitat provides no guarantee against contracting AGS as this allergy is found all over the U.S.
What do antibodies tell us?
AGS diagnosis relies on patient history, skin tests, oral food or drug challenges and the presence of immunoglobin E (IgE) antibodies, which are mainly involved in allergic responses. But 30+% of Americans already carry AGS-specific IgEs and only a tiny fraction become allergic — so the IgE test provides very little actionable information.
All humans also carry IgG, IgM and IgA antibodies to alpha-gal-linked proteins. These antibodies make up about 1% of all the antibodies carried by humans.
These antibodies normally provide immunological defense against pathogens and “foreign” chemicals entering the body. Their presence signifies exposure to alpha-gal proteins but carries no clinical significance in terms of AGS.
The only difference between merely carrying antibodies and getting sick is a tick bite.
And therein lies the main mystery behind AGS: What is the biological switch that causes allergy in sensitized individuals, and how is it activated? What factors in tick saliva cause previously asymptomatic antibody carriers to get seriously ill?
Scientists believe that activation of basophils, a type of immune cell involved in allergy, initiates this process. Basophils release histamine, a well-known mediator of allergic reactions.
Independent of IgE status, evidence of basophil recruitment and activation very nearly confirms that someone has AGS and not merely antibodies, according to a 2019 paper.
The authors concluded:
“The basophil activation test should be considered as an additional diagnostic test before performing time-consuming and potentially risky oral provocation tests. The [test endpoints] were the best parameters for distinguishing patients with alpha-gal syndrome from subjects with asymptomatic alpha-gal sensitization.”
Conclusion
People who enjoy red meat are understandably concerned about an AGS diagnosis. Vegetarianism is not for everyone, and the potential presence of minute quantities of allergy triggers in non-meat foods can also be a source of ongoing anxiety.
Examination of the available evidence on how people develop AGS leads to conclusions that may surprise some readers:
The main culprit in sensitization and allergy is not the free, unbound alpha-gal sugar but alpha-gal attached to specific tick proteins.
Until further evidence is found: no tick, no AGS.
People with AGS may also experience severe reactions to products containing the “four ingredients of concern,” but these reactions are a consequence, not a cause, of AGS.
Many vaccines contain alpha-gal according to the CDC but it is unclear whether this is the free alpha-gal sugar or alpha-gal attached to proteins (most likely from cows). Regardless, the attached proteins are not from ticks so, according to the current paradigm, they cannot cause AGS.
Most news reports implicate the lone star tick to the exclusion of other tick species, which may lead to a false sense of security for individuals who live outside that species’ natural habitat. The safest course is to avoid encounters with ticks whenever possible.
Sensitization, as determined by a test for alpha-gal IgE antibodies, only rarely means a person will develop AGS. The overwhelming majority of people with IgA, IgE, IgG and IgM antibodies to alpha-gal will never develop a food allergy.
A basophil activation test can confirm AGS in individuals with alpha-gal antibodies whose response to eating meat is mild or sporadic.
https://madisonarealymesupportgroup.com/2022/11/02/when-alpha-gal-syndrome-is-not-related-to-a-tick-bite/ This person doesn’t ever remember a tick bite and lives in CA. “Since my alpha-gal diagnosis, I have been diagnosed with multiple other food and medication allergies, including an uncommon allergy to PEG (polyethylene glycol) and polysorbate. Neither one has a diagnostic test. In addition, my Alpha-Gal test is now negative, but my sensitivity and reactions are still severe.”
A riveting thriller reminiscent of The Hot Zone, this true story dives into the mystery surrounding one of the most controversial and misdiagnosed conditions of our time – Lyme disease – and of Willy Burgdorfer, the man who discovered the microbe behind it, revealing his secret role in developing bug-borne biological weapons and raising terrifying questions about the genesis of the epidemic of tick-borne diseases affecting millions of Americans today.
While on vacation on Martha’s Vineyard, Kris Newby was bitten by an unseen tick. That one bite changed her life forever, pulling her into the abyss of a devastating illness that took 10 doctors to diagnose and years to recover: Newby had become one of the 300,000 Americans who are afflicted with Lyme disease each year. (Recent estimates suggest that 476,000 people get infected with Lyme each year in the U.S.)
As a science writer, she was driven to understand why this disease is so misunderstood and its patients so mistreated. This quest led her to Willy Burgdorfer, the Lyme microbe’s discoverer, who revealed he had developed bug-borne bioweapons during the Cold War and believed that the Lyme epidemic was started by a military experiment gone wrong.
In a superb, meticulous work of narrative journalism, Bitten takes listeners on a journey to investigate these claims, from biological weapons facilities to interviews with biosecurity experts and microbiologists doing cutting-edge research, all the while uncovering darker truths about Willy. It also leads her to uncomfortable questions about why Lyme can be so difficult to both diagnose and treat and why the government is so reluctant to classify chronic Lyme as a disease.
A gripping, infectious pause-resister, Bitten will shed a terrifying new light on an epidemic that is exacting an incalculable toll on us, upending much of what we believe we know about it.
________________
“The fact that the EU, UK, and US are currently engaged in projects to sequence nearly 2 million of their citizens’ genomes provides a hint that they may want to collect additional genomes of Africans, Asians, and others.” ~ Dr. Meryl Nass
Experimenting upon innocents has been going on for decades, but the ‘powers that be’ gaslight anyone with an individual thought of their own and shout “misinformation” and “conspiracy theorist” to frighten everyone into mute complacency. None of it would be possible without academic, political, religious, and scientific communities silently watching and saying nothing. Evil flourishes when people do nothing.
The People’s Declaration
RIGHT NOW would be a very good time to stand up and publicly declare your opposition to the international plan to share the “benefits” derived from “pathogens with pandemic potential.“
The possibility that these agreements could actually facilitate, fund and support gain-of-function research is absolutely unacceptable. (click on the links below to download the documents)
Welcome to another selection from my book “An Expert’s Guide on Navigating Lyme disease.” The book highlights the findings of my first 600 Lyme disease Science blogs. In this episode, I will discuss pregnancy, breast feeding, and Lyme disease.
Pregnancy and breast feeding are particularly concerning topics for Lyme disease patients and their doctors. Here are few findings to help with discussions.
Pregnancy and Lyme.
If a woman is bit by a deer tick or contracts Lyme disease (LD) while pregnant, she must immediately alert her treating physician. Poor outcomes have been described for newborns whose mothers contracted Lyme disease during pregnancy. Studies have found that stillbirths occurred when LD was contracted during the first trimester. Markowitz et al., 1986, Schlesinger et al., 1985, and MacDonald et al., 1987) Gestational Lyme borreliosis has been described in 5 of 19 pregnancies (26%) resulting in “syndactyly, cortical blindness, intrauterine fetal death, prematurity, and rash” (Markowitz et al., 1986).
A newborn died at 39 hours of life with a left-sided hypoplastic heart and the presence of spirochetes consistent with Bb [Borrelia burgdorferi] “in the spleen, kidneys, and bone marrow” (Schlesinger et al., 1985). Bb was also cultured from fetal liver tissue in 4 stillborn infants (MacDonald 1986). There was insufficient evidence to determine the risk to a child if their mother contracted Lyme disease before pregnancy (Mylonas 2011). A study of 2,000 women with a history of LD did not show an increased risk of fetal death, decreased birth weight, or length of gestation at delivery. There was an increase in the number of congenital defects but the risk may have been by chance alone (Strobino et al., 1993).
Choosing an antibiotic regimen for pregnant women with Lyme disease can be a complex challenge. Amoxicillin, cefuroxime, azithromycin, and IV ceftriaxone have been prescribed for pregnant women (Maraspin et al., 2009).
Author’s note: More studies will be needed to understand pregnancy and breast feeding concerns.
Breast feeding and Lyme.
The CDC addressed the question “Can Lyme disease be transmitted through breast milk?” They announced, “No reports of breast milk spreading Lyme disease to infants exist” (CDC 2022). There is insufficient data to determine if breastfeeding can transmit Bb to the child. Certain antibiotic classes, such as tetracyclines, should not be used in breastfeeding women being treated for Lyme disease to avoid the risk of side effects, such as tooth discoloration. The child’s clinician can help guide treatment options for a breastfeeding mother. Read more.
Diversity of clinical presentations of Lyme and pregnancy.
Doctors followed 11 pregnant women with Lyme disease from 2008 to 2020. “In the present study, we report our case series, which includes 11 pregnant women, 6 of whom developed erythema migrans during pregnancy (between weeks 8 and 34), 3 had monoarticular or neurological symptoms, and 2 had positive serology but did not develop any clinical symptoms” (Trevisan et al., 2020).
All mothers were treated with amoxicillin 1g 3x/ day for 14 days. One child was born prematurely at seven months. Another child was born with angiomatoid patches that regressed spontaneously 18 months later. One of the pregnant women with Lyme disease, confirmed by spinal tap and labs, experienced articular and neurologic involvement and improved with amoxicillin. However, she required treatment with intravenous ceftriaxone because of persistent symptoms. Read more.
Two mothers transmit Lyme to their babies.
Babesia can be contracted from the bite of a deer tick, a blood transfusion, or during pregnancy. This podcast reviews a case in which Babesia was transmitted from mothers to their babies during pregnancy.
Questions raised in the podcast include: • How often do mothers contract Babesia from a tick bite during pregnancy? • Is there an effective and safe treatment for Babesia in pregnant women? • How does a mother or doctor recognize Babesia in a pregnant mother? • Should doctors follow pregnant mothers with a tick bite or Lyme disease for Babesia and what evidence should be investigated? • Will the mothers develop complications of Babesia in the future if not treated? • Should the two mothers have been treated for Babesia? Read more.
A baby girl with Lyme disease.
Slovenian researchers investigated whether Borrelia burgdorferi bacteria, the pathogen causing Lyme disease, might impact pregnancy outcomes. Pregnancy outcome was unfavorable in 13.8% (42/304) of patients. They found that the outcome of pregnancy in Lyme disease patients was not significantly worse.
There were 22 pre-term births, 10 fetal/perinatal deaths, and/or 15 anomalies. Several mothers had potential explanations for their unfavorable pregnancy outcomes. The poor outcome for Lyme disease patients was not significantly different compared to the general population (Maraspin et al., 2020).
Author’s note: The study did not follow the 262 women who gave birth with a favorable outcome for any long-term problems. Nor did the authors describe the outcome for women who were not treated for early Lyme disease. Read more.
Little information on treatment of tick bites during pregnancy.
Smith et al., (2020) argue that “high-level evidence” supports using a single 200 mg dose of doxycycline for tick bites during pregnancy. The evidence they cited is not high-level. Instead, they focused on a small Meta-Analysis study. Regrettably, there is no evidence that a single 200 mg dose of doxycycline prevents other manifestations of Lyme disease, such as heart block, 7th nerve palsy, Lyme arthritis, Lyme encephalopathy, or Neuropsychiatric Lyme disease. Read more.
Congenital transmission of Babesia to a 5-year-old twin.
A baby girl was born to a mother who showed no evidence of Lyme or a related tick-borne illness during her pregnancy (Walker et al., 2022). The 5-week-old female diamniotic dichorionic twin was born at 36 5/7 weeks by C-section and diagnosed with Babesia. Her twin brother was asymptomatic. The mother described several trips to Cape Cod, Massachusetts, an area endemic to Lyme disease.
“The patient’s mother had one febrile illness during pregnancy, occurring at approximately 23-24 weeks of gestation, associated with a maculopapular rash that resolved spontaneously” (Walter et al., 2022). The daughter was treated with a blood transfusion, intravenous atovaquone twice daily, and azithromycin daily. The authors of the article pictured a blood smear with intraerythrocytic inclusions consistent with Babesia microti. Read more.
Delayed onset Babesia in two newborns.
A study from the Mayo clinic described two newborn infants diagnosed with Babesia several weeks after the mothers were treated for Lyme disease (Hoversten and Bartlett, 2018). Infant 1: A baby boy was diagnosed with Babesia at 4-1/2 weeks. His mother had been diagnosed and treated for early Lyme disease at 32 weeks gestation. Infant 2: A baby girl was diagnosed with Babesia at 18-days-old. Her mother had been diagnosed and treated for early Lyme disease at 37 weeks gestation. Neither mother was treated for Babesia during their pregnancy. Read more.
________________
**Comment**
Lyme/MSIDS has recognized for over 40 years, yet very little has been done relating to pregnancy, breastfeeding, effective treatments, persistence, and transmission. The fact so much work on supposed ‘climate change’ should prove to anyone with a functioning brain that something isn’t right. While thousands suffer, the only thing we have to show for it is mountains of data on ticks and the climate, despite independent research proving ticks are marvelously ecoadaptive as well as pointing out erroneous, biased, shoddy research being used to support a faulty model to push a climate narrative.
The fact that infected moms have had babies die, and the fact they have cultured spirochetes in the heart, liver, spleen, kidneys, and bone marrow of infants should raise alarming red flags.
Regarding the CDC’s statement on breastfeeding – just because something hasn’t been reported, doesn’t mean it doesn’t happen.
Any red flags simply get buried under climate data.