Archive for the ‘Lyme’ Category

Live Tonight: Lyme Disease & Chronic Pain Webinar

Live Webinar: Lyme Disease & Chronic Pain – Dr. Bill Rawls

erasing pain, hand written word on blackboard being erased concept

The list of symptoms that can come with chronic Lyme disease is long and varied, but pain — in the joints, muscles, nerves, neck, eyes, even teeth — seems to be a common denominator.

Why are Lyme sufferers so prone to chronic pain, and what can you do to find fast and lasting relief?

Join a live webinar with Dr. Bill Rawls, author of the bestselling book Unlocking Lyme, who knows firsthand what it’s like to live with chronic Lyme disease and related aches and pains. He’ll shed new light on the underlying forces that drive persistent pain, and share natural ways to resolve them so you’re not just managing discomfort, but overcoming it.

PLUS: Don’t miss an exclusive gift for webinar attendees, and have your questions ready for a LIVE Q&A on Lyme and chronic pain with Dr. Rawls.

Watch June 17th, 8pm EDT

Lyme & Chronic Pain – Live Webinar

  • The causes and telltale symptoms of different types of pain
  • How Borrelia burgdorferi and common Lyme coinfections like Mycoplasma, Bartonella, and Babesia contribute to pain
  • The best herbs and natural remedies for immediate and long-term relief
  • Additional diet and lifestyle tips to help keep symptoms at bay 
  • Numerous insights during the live Q&A with Dr. Rawls 

RESERVE MY SEAT »

___________________

For more:

Borrelia Miyamotoi Infection in a Highly Endemic Area of Lyme Disease

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7260789/

Published online 2020 May 30. doi: 10.1186/s12941-020-00364-0
PMCID: PMC7260789
PMID: 32473652

Presence of Borrelia miyamotoi infection in a highly endemic area of Lyme disease

Abstract

A series of cases in the Northeast of the US during 2013–2015 described a new Borrelia species, Borrelia miyamotoi, which is transmitted by the same tick species that transmits Lyme disease and causes a relapsing fever-like illness. The geographic expansion of B. miyamotoi in the US also extends to other Lyme endemic areas such as the Midwestern US. Co-infections with other tick borne diseases (TBD) may contribute to the severity of the disease. On Long Island, NY, 3–5% of ticks are infected by B. miyamotoi, but little is known about the frequency of B. miyamotoi infections in humans in this particular region. The aim of this study was to perform a chart review in all patients diagnosed with B. miyamotoi infection in Stony Brook Medicine (SBM) system to describe the clinical and epidemiological features of B. miyamotoi infection in Suffolk County, NY. In a 5 year time period (2013–2017), a total of 28 cases were positive for either IgG EIA (n = 19) or PCR (n = 9).

All 9 PCR-positive cases (median age: 67; range: 22–90 years) had clinical findings suggestive of acute or relapsing infection.

All these patients were thought to have a TBD, prompting the healthcare provider to order the TBD panel which includes a B. miyamotoi PCR test.

In conclusion, B. miyamotoi infection should be considered in the differential diagnosis for flu-like syndromes during the summer after a deer tick bite and to prevent labeling a case with Lyme disease.

__________________

**Comment**

https://madisonarealymesupportgroup.com/2018/09/04/borrelia-miyamotoi-in-immunocompetent-patient/

Dr. Cameron states:  “Until now, there have been no treatment guidelines for B. miyamotoi and regimes have been empirically based on the treatment for Lyme disease. ‘The antimicrobial susceptibility of B. miyamotoi has not yet been elucidated, due to difficulties with cultivation of B. miyamotoi spirochetes in vitro,’ according to Koetsveld.  http://danielcameronmd.com/best-antibiotics-treat-borrelia-miyamotoi/  The study authors demonstrated that B. miyamotoi is susceptible to doxycycline, azithromycin, and ceftriaxone but resistant to amoxicillin in vitro. The next step would be to show whether these drugs work in patients.”

For more:  https://madisonarealymesupportgroup.com/category/borrelia-miyamotoi-relapsing-fever-group/http://danielcameronmd.com/dont-count-on-a-relapsing-fever-to-diagnose-borrelia-miyamotoi/
“You might assume a patient infected with Borrelia miyamotoi, a relapsing fever spirochete, to present with a relapsing fever. However, your assumption would be wrong 48 out of 50 times, according to a case series published in the Annals of Internal Medicine. [1] The authors found that only 2 out of 50 patients infected with the relapsing spirochete B. miyamotoi actually presented with a relapsing fever. [1]….The individuals exhibited symptoms similar to those found in other tick-borne illnesses.
The majority presented with headaches, myalgias, arthralgias, and malaise/fatigue. ‘More than 50% were suspected of having sepsis, and 24% required hospitalization,’ states Molloy. [1]…..’Serologic testing using the rGlpQ EIA seems insensitive in diagnosing acute BMD infection given that it was positive for IgG or IgM in only 16% of the case patient samples at the time of clinical presentation,’ states Molloy. The rGlpQ was positive after the fact in 86% of the patients during convalescence. [1]….Elevated liver enzyme levels, neutropenia, and thrombocytopenia were common in 75%, 60% and 51% respectively.
‘Borrelia miyamotoi disease may be clinically similar to or be confused with human anaplasmosis,’ according to Molloy….B. miyamotoi has emerged as a leading cause of hard tick-transmitted infections but lacks a clear diagnostic criteria. According to Molloy, “Infection with B. miyamotoi is the fifth recognized Ixodes-transmitted infection in the northeastern United States and should be part of the differential diagnosis of febrile patientsfrom areas where deer tick–transmitted infections are endemic.’”

Next TBDWG Meeting July 8: Make Sure To Pop Popcorn

https://www.lymedisease.org/next-online-meeting-of-tbd-working-group-is-july-8/

Next online meeting of TBD Working Group is July 8

 “IF the CDC posts any Lyme treatment guidelines, that they include guidelines on persistent Lyme disease.

The recommendation regarding persistent Lyme disease was moved and seconded. Then, for unstated reasons, five panel members abstained from voting. The vote was announced as five abstaining, five yes votes and three no votes.”

tbdwg vote on persistent lyme

https://madisonarealymesupportgroup.com/2020/05/11/persistent-lyme-a-sticking-point-for-tbd-working-group/

Excerpt:

Remarks made after the vote made it clear that the abstainers felt they had defeated the measure, because “yes” votes didn’t comprise a majority of panel members. But, oops, guess what? Abstentions don’t count one way or the other. So, the recommendation passed, 5-3.

As that reality sank in, pandemonium broke out. Panelist Scott Commins stoutly announced that he wanted to change his abstaining vote to “no.” He was told that Robert’s Rules of Order don’t allow you to change your vote after the fact.

Things then got very bizarre very fast, with many people talking at once. Some wanted to vote on the original question again. Others didn’t. Some wanted to re-open discussion, others didn’t. It was confusing to the listener at home.

However, the five abstainers sure gave the impression they had been trying to game the system—to gain a “no” vote without having to publicly own up to it. When that ploy didn’t work, they scrambled to recoup their original objective— to deep-six the proposal regarding persistent Lyme disease.

The upcoming meeting should be entertaining.

Unfortunately, lives are at stake. We really don’t want entertainment – we need answers.


Lyme Community Has Lost a Hero & Friend: Dr. Neil Spector

https://www.lymedisease.org/dr-neil-spector-has-died/

The Lyme community has lost a hero and a friend: Dr. Neil Spector

June 15, 2020

_____________________

For more on Dr. Spector:


Mystery Complicates Lyme Disease Treatment

https://triblive.com/opinion/corey-may-mystery-complicates-lyme-disease-treatment/

Corey May: Mystery complicates Lyme disease treatment

On Sept. 22, 2015, I received a kidney transplant at Allegheny General Hospital. Ever since, I have done everything within my power to be grateful for and reverent to my new kidney, which has served me well — until now. It is under attack.

Even with total clothing cover, I got bit by a nymph deer tick, the size of a pinhead. Today, Lyme disease had turned my health upside down. This is only partially because of the antibiotic resistance to the coinfections of bacteria, viruses, fungi and parasites that ticks carry; it is also because of the lack of doctors in the Pittsburgh area qualified to treat the complications. (See link for article)

_____________________

**Comment**

Important quote:

Even in Pittsburgh, one of the greatest medical cities in the world, you are left alone to figure out a myriad infection like Lyme disease.

The main reason for the lack of qualified doctors is because the same CDC in charge of the current COVID-19 health fiasco is ALSO in charge of setting up Lyme/MSIDS treatment guidelines which doctors follow.  They use antiquated and biased science which has harmed thousands upon thousands of patients.  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/

Also, due to this ‘iron curtain,’ doctors who depart from the controlled narrative are sought out and persecuted:  https://madisonarealymesupportgroup.com/2012/03/04/dr-hoffmann-updated/  This has happened in nearly every state in the U.S. as well as worldwide.

Yet, these same authorities are locking down the entire United States over COVID-19. Ponder this for a moment.

This stone wall has gone on unabated for over 40 years.  Lyme/MSIDS is a true pandemic that is not going away, yet authorities haven’t changed their tune. Research continues to focus on the acute stage of Lyme and completely denies chronic infection, which new research has estimated to be 63% of all who get infected:  https://madisonarealymesupportgroup.com/2020/06/12/formidable-evidence-for-sexual-transmission-of-lyme-disease-first-study-to-document-aca-rashes-in-canadian-patients/

Another study shows the chronically infected to be between 40-60% of all patients:  https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/

Yet, these authorities, who have been around as long as the disease itself, do asinine studies like this:  https://madisonarealymesupportgroup.com/2020/06/14/oral-penicillin-for-lyme-patients-with-em-rash-in-the-u-s/

And this:  https://madisonarealymesupportgroup.com/2019/02/22/why-mainstream-lyme-msids-research-remains-in-the-dark-ages/

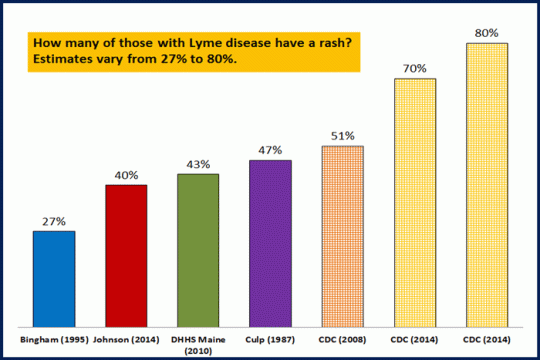
They just can’t get over the EM rash, even though research shows it’s appearance is highly variable and clearance of the rash does not mean the systemic infection has been cleared:

Rashes-larger-blog-4

Scott’s study puts that percentage even lower at 9-39%, hardly a symptom to base ALL research upon. If you have the rash, you HAVE Lyme, but if you don’t have the rash you may STILL have Lyme.

Until authorities change their fixed ideas of this disease patients will suffer – just like the one in this article.