Last night I had an end-of-summer ice cream with someone who said, “I’ve probably met fifteen people this summer who have Lyme disease. It’s such an urgent problem.” Though I was sorry to hear these individuals were sick, I was glad to hear that they had all been properly and efficiently diagnosed. Patients and doctors alike are becoming more aware of this urgent health threat.
What many don’t realize, however, is that the Lyme disease threat doesn’t disappear with warm summer days. Tick season, and active ticks, are a year-round problem, and it’s important to remain vigilant in the fall as we are in the summer. While it’s the nymphal-stage ticks of spring and early summer we worry about most—predominantly because they’re so microscopic that we often miss them—the larger adult ticks of the current season also transmit tick-borne diseases.
Ticks are especially a danger during this time of year to school children who undertake outdoor sports—or any child who plays outside, be it at home, a park, or school recess. As the weather turns colder, ticks hide out in thick brush and leaf piles. They live in long grass, in wooded areas, and in your garden.
If you, your children or pets spend any time outdoors this fall, keep the following tips in mind:
Continue to wear bug spray: We don’t just need repellent for summer hikes and campfires; we need it in the autumn, too. Before going on a fall hike, walking to a playground, or letting your child roll in the grass, be sure to apply repellent.
Use repellent wipes: Instead of or in addition to bug spray, you can wipe down your skin with repellent wipes before going outdoors. These are great to put in your child’s backpack or in your own purse—you never know when you might need to walk through a grassy area.
Spray your clothes and gear: Bug spray isn’t just for exposed skin. You can buy clothes that are pre-treated with permethrin at many outdoor retailers, or you can buy a bottle and spray everything yourself. Include shoes, clothes, sports bags, and any other type of gear.
Carry a tick removal kit: In case of a tick bite, make sure to bring tweezers or tick removal tool, alcohol wipes, and a Ziploc baggie to put the tick in once you’ve pulled it out (see how to properly remove a tick). Mark the date on the bag. It’s recommended you send tick(s) out for testing.
Wear long pants and sleeves: This is easier when the weather gets cooler. Light-colored clothing is best, because it’s easier to see a tick on a white shirt than a dark shirt. Nerdy as it may look, it’s also helpful to tuck pants into socks, thereby preventing ticks from climbing up your legs.
Carry a small lint brush: Run a lint brush over your hair, skin and clothing after spending time outdoors; the sticky paper can pick up ticks you might miss. I carry a lint brush in my purse and also keep one by my front door.
Wash and dry clothes and equipment immediately after use: As soon as you or your young athlete get home, throw clothes, shin guards, and other washable gear in the dryer on high heat for at least 10-15 minutes. Ticks require moisture to survive and will rapidly die in a quick spin in a hot dryer.
Bathe after outdoor activity: After stripping your clothes and doing a thorough tick check, shower as soon as you come inside (versus waiting even a few hours, and giving the tick time to sit on your body and feed).
Continue to do tick checks every night: Make sure you’re not bringing any bugs into bed. Do a head-to-toe check on yourself, children, and pets. Bath time is a great time to do a once-over on kids. Remember to check in spots like the groin, behind the knees, behind the ears, and the scalp. Always Be Tick AWARE!
Wishing you all a fun and tick-free fall!
Jennifer Crystal is a writer and educator in Boston. Her memoir One Tick Stopped the Clock is forthcoming. Contact her at lymewarriorjennifercrystal@gmail.com.
I believe InPower Movement’shttps://www.inpowermovement.com/ liability action is part of the long-term solution, its next phase is currently being developed. In the meantime, I recommend people
We the undersigned scientists, doctors, environmental organizations and citizens from ( ) countries, urgently call for a halt to the deployment of the 5G (fifth generation) wireless network, including 5G from space satellites. 5G will massively increase exposure to radio frequency (RF) radiation on top of the 2G, 3G and 4G networks for telecommunications already in place. RF radiation has been proven harmful for humans and the environment. The deployment of 5G constitutes an experiment on humanity and the environment that is defined as a crime under international law. ____________________
U.S. Senator Susan Collins of Maine, the Chairman of the Aging Committee, convened an official Senate field hearing on September 5, at the University of Maine Cooperative Extension Diagnostic and Research Laboratory Tick Lab.
Immediately prior to the hearing, Senator Collins toured the lab, which provides tick diagnostics, offers public outreach, and conducts applied research on ticks in Maine.
The hearing, titled “The TICK Act: An Urgent Public Health Response to Tick-Borne Diseases,” explored the growing public health crisis of Lyme disease and other tick-borne diseases. The legislation would apply a three-pronged approach to tackle Lyme and other tick and vector-borne diseases.
“I greatly appreciated our extraordinary group of witnesses who took the time to share their scientific expertise as well as their personal experiences with Lyme disease,” said Senator Collins.
“I was also very impressed to see firsthand the outstanding work being done by the University of Maine Cooperative Extension’s Tick Lab to better understand the diseases ticks carry and to protect Mainers.”
She continued: “A correct and early diagnosis can reduce costs and improve the prognosis, but we have a long way to go. Lyme disease was identified more than 40 years ago, yet there is still no gold standard for treatment. Existing prevention, education, and diagnostic efforts are helpful but remain fragmented. The TICK Act would help unite our efforts against ticks.”
Patients tell their stories
Chris Philbrook of Cumberland contracted Lyme disease in 2007 on a trip to Hogback Mountain in Virginia. He could barely move a muscle the next day and experienced debilitating pain and partial paralysis of his face.
After a CAT scan showed nothing abnormal, Mr. Philbrook visited a dentist for his tooth pain, who said his symptoms could be due to Lyme disease. Mr. Philbrook was tested for Lyme, but the results came back negative. It was only after Mr. Philbrook’s symptoms progressed and paralysis affected both sides of his face that he received a spinal tap and was properly diagnosed.
“I didn’t realize how important smiling was to my mental health until I couldn’t do it anymore,” said Mr. Philbrook. “I was lucky that my dentist spoke up, that I had a spinal tap—which is not a normal Lyme testing protocol—and that my Lyme disease was treated quickly, within the first month and a half. I’m happy to say that after my antibiotic treatment, I was cleared of the disease, although residual effects remain, mainly sleep disturbances and facial paralysis.”
Unlike Mr. Philbrook, Paula Jackson Jones of Nobleboro faced a frustrating diagnostic odyssey after she contracted Lyme disease while doing yard work in 2009. Over the next two years, she was misdiagnosed by 23 doctors and specialists. Although Ms. Jackson Jones tested negative for Lyme disease on four occasions, she was finally diagnosed with Lyme, Babesia, Bartonella, Rocky Mountain Spotted Fever, and Erlichiosis after a clinical examination and additional blood work and tests.
She co-founded Midcoast Lyme Disease Support & Education to make patients’ search for resources easier, accessible, and affordable. Ms. Jackson Jones said that Senator Collins’ TICK Act would “provide a lifeline” to patients and doctors by funding increased research and education.
Medical experts testify
Dr. Sean McCloy provided a physician’s perspective on the difficulty of diagnosing Lyme. As a young resident at Maine Medical Center, he felt equipped to spot the classic signs of the disease, such as the bull’s-eye rash, but he began seeing more patients who didn’t fit the typical scenario. Dr. Peterson described how he became a “detective doctor” to determine how to help his patients and learned that there is no one-size-fits-all approach that works for every case.
Dr. Jim Dill, a Pest Management Specialist who oversees UMaine’s Tick Lab, spoke about the work the UMaine Cooperative Extension is doing to minimize the occurrence and spread of ticks and tick-borne diseases in Maine.
The Tick Lab monitors tick populations and allows Maine residents to send tick samples for identification and testing. Dr. Dill noted that funding for tick research has been a challenge, but said the TICK Act will “inject a much-needed investment” that will allow the Tick Lab to expand its work.
Dr. LylePetersen, theDirector of the Division of Vector-Borne Diseases at the Centers for Disease Control and Prevention’s (CDC) National Center for Emerging and Zoonotic Infectious Diseases, spoke about the CDC’s efforts to reverse the upward trend in vector-borne disease by focusing on preventing infections.
He pledged that the CDC will continue supporting state and local jurisdictions’ initiatives to address tick-borne disease, and he expressed his commitment to supporting the development of an effective vaccine.
Last year, an estimated 450,000 Americans were diagnosed with Lyme disease, a staggering 1,400 percent increase since 2003. In the last year in Maine alone, there were approximately 1,400 new cases of Lyme disease, a sharp increase from the 752 cases in 2010. Other tick-borne diseases are also on the rise in Maine.
Maine has the highest rate of Lyme disease in the country, with per capita diagnoses 10 times higher than the national average. Tick-borne diseases disproportionately affect people over age 65, who are afflicted at higher rates than any other age group.
Medical costs of Lyme disease are estimated at $1.3 billion per year. When accounting for indirect medical costs, including loss of work, the annual costs balloon to $75 billion per year.
The Ad Hoc Patient and Physician Coalition against IDSA Proposed Lyme Guidelines
SEP 7, 2019 —
From: CARL TUTTLE <runagain@comcast.net>
To: tickbornedisease@hhs.gov
Cc: (91 Undisclosed recipients)
Date: September 7, 2019 at 8:48 AM
Subject: The Ad Hoc Patient and Physician Coalition; Comments of the IDSA Proposed Lyme Guidelines September 6, 2019
To the Tick-Borne Disease Working Group;
Please follow the link below to see comments to the IDSA Proposed Lyme Guidelines. These comments are endorsed by members around the world because what has been established here in the United States has adversely affected public health globally.
The link provided is from my personal Dropbox storage area.
The Ad Hoc Patient and Physician Coalition
Comments of the IDSA Proposed Lyme Guidelines September 6, 2019
About the Ad Hoc Patient and Physician Coalition: The Ad Hoc Patient and Physician Coalition consists of patients and physicians who are concerned that the proposed Lyme disease guidelines of the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR) will further restrict access to care and harm patients by leaving them undiagnosed and undertreated.The coalition consists of over 75 organizations, from 8 countries: the US, Canada, Australia, UK, France, Netherlands, Germany, Belgium (including LymeDisease.org, the national Lyme Disease Association, Bay Area Lyme Foundation among others) and the International Lyme and Associated Diseases Society, which represents clinicians who treat Lyme disease nationwide. (List of signatories attached.)
These comments were authored by Lorraine Johnson, JD|MBA, CEO LymeDisease.org and Dr. Elizabeth Maloney, who represents the International Lyme and Associated Diseases Society. The comments were filed on August 8, 2019 and revised on September 6, 2019.
Page 56
Ad Hoc Patient and Physician Coalition Members As of September 6, 2019
The following 77 organizations have endorsed the Ad Hoc Patient and Physician Coalition Comments of the IDSA Proposed Lyme Guidelines. (List updated Sept. 6, 2019)
Countries represented: United States, Canada, Australia, France, United Kingdom, Netherlands, Germany, and Belgium.
Alabama Lyme Disease Association
Arkansas Lyme Coalition
Arkansas Lyme Foundation
Association Québécoise de la Maladie de Lyme (Canada)
Bay Area Lyme Foundation
BC Lyme (British Columbia, Canada)
Brookfield/Wolfeboro New Hampshire support group
Borreliose-Bund, Germany
Canadian Lyme Disease Foundation
Central Massachusetts Lyme Foundation
Charles E. Holman Morgellons Disease Foundation
Chronic Lyme Disease Support and Protest UK.
ChroniLyme (Lyon, France)
Colorado Tick-Borne Disease Awareness Association
Dean Center for Tick Borne Illness, Massachusetts
Dutch Lyme Association (Lymevereniging), Netherlands
Florida Lyme Disease Association
France Lyme, Association de Lutte Contre les Maladies Vectorielles à Tiques (France)
Howard County Lyme Awareness Group, Maryland
Hudson Valley Lyme Disease Association
Illinois Lyme Association
International Lyme and Associated Diseases Society
Kentucky Lyme Disease Association
Le Droit de Guerir (“The right to heal”), France
Litchfield County Lyme Network (Connecticut)
Living with Lyme, London/Middlesex (Canada)
LivLyme Foundation
Lyme Action Network
Lyme Alliance of the Berkshires
Lyme Association of Greater Kansas City
Lyme Center, Chico, California
LymeDisease.org
Lyme Disease Association (US)
Lyme Disease Association of Australia
Lyme Disease Association of Southeastern Pennsylvania
Lyme Disease Association, Rhode Island Chapter
Lyme Disease Education & Support Groups of Maryland
Lyme Disease UK
Lyme Hope (Canada)
Lyme-int Association (Belgium)
Lyme Newport (Rhode Island)
Lyme Ontario (Canada)
Lyme Stats 57
LymeConnection.org
LymeLight Foundation
Madison Lyme Support Group
Massachusetts Lyme Legislative Task Force
Memphis Tennessee Lyme Network
Midcoast Lyme Disease Support & Education
Military Lyme Support
MSIDS, Inc, Australia
NE Ohio Lyme Foundation
New Brunswick Lyme Disease Association Inc.- LymeNB (Canada)
New Jersey Lyme Resource
New York City Lyme Disease Support Group
OnLyme-Aktion.org (Action Alliance Against Tick-borne Diseases), Germany
Ontario Lyme Alliance (Canada)
PA Lyme Resource Network (Statewide)
PA Lyme Resource Network, Bucks County
PA Lyme Resource Network, Columbia County
PA Lyme Resource Network, Lehigh Valley
Patient Centered Care Advocacy Group
Pennsylvania Lyme Disease Awareness Committee of Chester-Delaware County Farm Bureau (PLDAC)
Penticton, BC area Lyme Group (Canada)
Sam’s Spoons Foundation for Lyme Support & Education
Southern Arizona Lyme Disease Association
Southern Oregon Lyme Disease
Texas Lyme Alliance
Tick Wise Education, Inc. (501c3)
Time for Lyme, ASBL (Belgium)
TxLyme Yahoo Online Support Group (Texas)
Utah Coalition for Lyme Disease
Vernon Lyme Disease Support Group, Vernon, BC (Canada)
Patients with Bartonella species infection (bartonellosis) complain of a variety of nonspecific vision problems that can affect every function of the eye. Making diagnosis and treatment decisions even more difficult, these problems can be caused by a variety of other pathogens and diseases. Fortunately, many peer-reviewed case publications, especially in ophthalmology journals, are available that describe both common and uncommon eye symptoms caused by bartonellosis.
Documented links between Bartonella species infection and vision problems focus on Bartonella henselae (cat scratch disease) and Bartonella quintana (trench fever). B. henselae is associated with contact with animals and vectors, especially cats and fleas, while B. quintana is associated with body lice. Additional species implicated include B. elizabethae and B. grahamii.
Overview
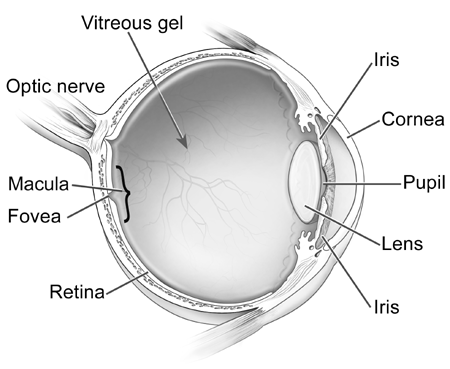
The eye consists of structures that focus light on nerve receptors at the back of the eye, nerves that feed into the optic nerve which connects to the brain, and a blood supply that connects through a central artery and vein into the body’s blood circulation. Bartonellosis can affect each of these parts of the eye.
Patients with bartonellosis-related eye problems may have symptoms in other organs as well that can help clarify whether the eye symptoms are caused by bartonellosis. Ophthalmologists and other physicians look for these additional signs because all of the eye conditions that can be caused by bartonellosis can be caused by a variety of bacteria and viruses, as well as other health conditions including autoimmune disorders.
It can be difficult to narrow down the possible causes of bartonellosis. Sometimes patients can’t remember any events that would have exposed them to Bartonella species. Other times the event, such as a cat scratch, may have occurred weeks to a month or more before symptoms appear and the patient may not think there is a connection. It can take detailed questioning by physicians to identify the possibility of Bartonella species exposure.
Structural Eye Symptoms
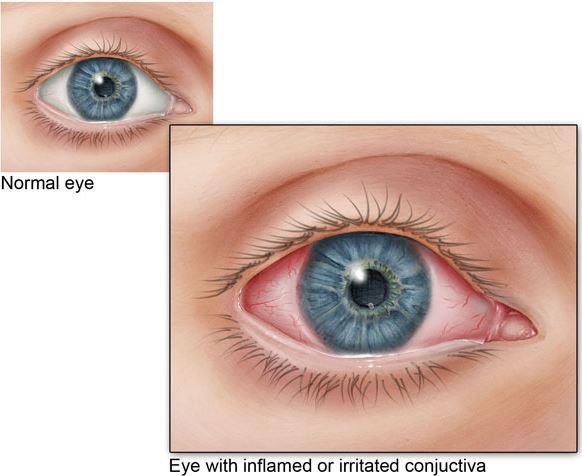
The most common way bartonellosis is seen in the eye is called Parinaud oculoglandular syndrome (POGS). About five percent of patients with acute cat scratch disease have this syndrome, which is characterized by follicular conjunctivitis (pink eye) with swollen lymph nodes nearby. It is often accompanied by a fever, and there may be bumps on the eyelid. Other symptoms known to be caused by bartonellosis, such as endocarditis (swelling of the inner lining of the heart), may also indicate that bartonellosis should be suspected.
Conjunctivitis results in easily seen inflammation of the usually white part of the eye (Source: CDC).
Inflammation of the middle layer of the structure that surrounds the eyeball is called uveitis. Uveitis causes redness of the eye and can cause light sensitivity, pain and floaters. Uveitis is sometimes associated with bartonellosis.
While case reports of eye symptoms caused by bartonellosis generally describe a sudden-onset condition, one case report describes a woman who had symptoms of bartonellosis in various body organs for more than five years, including chronic conjunctivitis (pink eye). She had multiple tests and treatments over that time including a Bartonella species test that was positive but considered nonspecific. It was only after other treatments didn’t work that antibiotics were administered. The antibiotics resolved her various symptoms.
Neurological Eye Symptoms
Neuroretinitis, an inflammation of the optic nerve head, occurs in about 2% of people with cat scratch disease (acute Bartonella henselae infection). Two-thirds of cases of neuroretinitis are caused by bartonellosis.
Neuroretinitis is usually characterized by sudden, complete vision loss and swelling that creates a star pattern in the macula (the light-sensitive tissue at the back of the eye that feeds information into the optic nerve). Though this is the typical case of neuroretinitis caused by bartonellosis, it can vary greatly. It can cause changes such as seeing odd shapes or colors Furthermore, case reports have included people who lose their vision with no other symptoms, have blurry vision with a headache, and more.
Treatment can usually, but not always, restore vision, but it can take months to resolve and there can still be long-term consequences. Complications can also occur. In one case, a child was diagnosed with neuroretinitis. Treatment was started six weeks after the diagnosis, but his vision in one eye got worse. After treatment, a full-thickness macular hole was discovered. The hole was monitored and resolved after six months.
Vascular Eye Symptoms
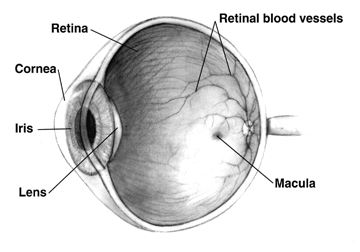
The eye has an important network of tiny blood vessels that provide nourishment to the tissue, but unnecessary growth of new capillaries can lead to a range of symptoms such as vision problems. Vasoproliferation (irregular growth of new blood vessels) may be more common in immunocompromised people, such as those being treated with chemotherapy products. These symptoms can be observed on the skin and in the liver and spleen and may also occur in the eye.
Tiny blood vessels in the eyes supply nutrients to cells. In the above image, larger retinal blood vessels can be seen (Source: NIH).
Vasoproliferative symptoms seem to be caused by vascular endothelial growth factor (VEGF) stimulated by bartonellosis. More research on the relationship between VEGF and bartonellosis is needed. Meanwhile, anti-VEGF agents have been used to treat vasoproliferative eye symptoms.
Conclusion
Bartonellosis can affect every part of the eye, and symptoms can be sudden and severe. Diagnosis and treatment decisions are complicated by other pathogens and diseases that can cause similar symptoms. It is important for patients and physicians to be aware of any prior animal or insect exposure that may indicate Bartonella infection. Considering additional systemic symptoms of bartonellosis may also help to clarify the diagnosis.
Learn more about bartonellosis and the testing that Galaxy Diagnostics offers here.
References
Kalogeropoulos, C. et al. (2011). Bartonella and intraocular inflammation: A series of cases and review of literature. Clinical Ophthalmology, 5, 817-829. doi:10.2147/OPTH.S20157 https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3130920/
Woo, M. et al. (2018). A case of retinal vessel occlusion caused by Bartonella infection. Journal of Korean Medical Science, 33(47), e297. doi:10.3346/jkms.2018.33.e297 https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6236082/
Fairbanks, A. M. et al. (2019). Treatment strategies for neuroretinitis: Current options and emerging therapies. Current Treatment Options in Neurology, 21(8), 36. doi:10.1007/s11940-019-0579-0 https://www.ncbi.nlm.nih.gov/pubmed/31278547
Michel, Z. et al. (2019). Multimodal imaging of two unconventional cases of Bartonella neuroretinitis [epub ahead of print]. Retinal Cases & Brief Reports. doi:10.1097/ICB.0000000000000893 https://www.ncbi.nlm.nih.gov/pubmed/31348120
Gunzenhauser, R. C. et al. (2019). The development and spontaneous resolution of a full-thickness macular hole in Bartonella henselae neuroretinitis in a 12-year-old boy. American Journal of Ophthalmology Case Reports, 15, 100515. doi:10.1016/j.ajoc.2019.100515 https://www.ncbi.nlm.nih.gov/pubmed/31341998
Toumanidou, V. et al. (2017). Neuroretinitis secondary to Bartonella henselae in a patient with myelinated retinal nerve fibers: Diagnostic dilemmas and treatment. Ocular Immunology and Inflammation, 27(3), 396-398. doi:10.1080/09273948.2017.1409357 https://www.ncbi.nlm.nih.gov/pubmed/29283743
Mabra, D. et al. (2018). Ocular manifestations of bartonellosis. Current Opinion in Ophthalmology, 29(6), 582-587. doi:10.1097/ICU.0000000000000522 https://www.ncbi.nlm.nih.gov/pubmed/30124532
Beckerman, Z. et al. (2019). Rare presentation of endocarditis and mycotic brain aneurysm [epub ahead of print]. The Annals of Thoracic Surgery. doi:10.1016/j.athoracsur.2019.06.073 https://www.ncbi.nlm.nih.gov/pubmed/31425670
_________________
**Comment**
Another great article by Galaxy Lab. Please read the following article for more information on Bartonella, as various strains are suspected to be transmitted by ticks, mites, various flies and spiders, and other modes, and it is far more prevalent than thought: https://madisonarealymesupportgroup.com/2016/01/03/bartonella-treatment/ Fifteen species of gram-negative aerobic Bartonella are known to infect humans; however Dr. Ricardo Maggi’s statement is quite telling, “This case reinforces the hypothesis that any Bartonella species can cause human infection.”


 Jennifer Crystal is a writer and educator in Boston. Her memoir One Tick Stopped the Clock is forthcoming. Contact her at lymewarriorjennifercrystal@gmail.com.