https://indiatimespost.com/deadly-ticks-carrying-ebola-like-congo-fever-found-in-uk-after-spreading-across-europe/

Deadly ticks carrying Ebola-like Congo fever ‘found in UK after spreading across Europe’

NINTCHDBPICT000498772073This is one of the so-called Hyalomma ‘super ticks’ which have been found in Germany

A TICK capable of carrying killer Ebola-like viruses has been found in the UK after spreading across Europe, health officials say.

The blood-sucking Hyalomma rufipes tick is usually only found in Africa, Asia and parts of southern Europe.

Central European News

But Public Health England says that one, which was 10 times larger than average, was discovered in Dorset last year.

Tests found the creature was carrying Rickettsia spotted fever, which can cause headaches, cramps and blisters in humans.

But the ticks are also known to carry the deadly Crimean-Congo haemorrhagic fever virus (CCHF) – a deadly disease dubbed the “next Ebola.”

The horrific virus, which is also known as Congo Fever, results in death in around two fifths of all cases – and there are no proven vaccines available to prevent it.

Those unlucky enough to catch the disease often suffer from internal bleeding, before organ failure strikes down the sufferer.

Ebola is also categorised as a hemorrhagic fever virus, according to the World Health Organisation.

A recent outbreak of the disease in Uganda has left two people dead, including a five-year-old boy, while nearly 1,400 have died in Congo since August.

Tick found in Dorset

The tick was removed from a horse by a vet at The Barn Equine Surgery in Wimborne, Dorset, last September and sent to PHE for analysis.

Kayleigh Hansford, who led the agency’s tick surveillance team, writing in the journal Ticks and Tick-borne Diseases, said:

“This is the first time Hyalomma rufipes has been reported in the United Kingdom.

“The lack of travel by the horse – or any in-contact horses – suggests that this could also be the first evidence of successful moulting of a Hyalomma nymph in the UK.”

She said it is suspected that the tick hitched a ride on a migratory bird before landing in the UK.

Neither the infested horse, nor other horses in the stable had travelled anywhere and no further ticks were detected on any of the horses.

It is thought the tick probably travelled on a swallow because they tend to nest in the stables of horses and migrate from Africa to the UK for summer.

‘Threat to public health’

The worrying find could “present a threat to public health in the UK”, the PHE said.

It’s not known whether any more of the ticks have been found in Britain this year, but so far there have been six reported cases in Germany.

Experts in Munich believe the bugs have mutated to survive cold winters – and don’t believe they could have been brought to the country by birds.

Dr Ute Mackenstedt, a parasitologist at the University of Hohenheim, said:

“If the development cycle is taken into account, this cannot be the case here, as the ticks would have had to have been introduced at a time where the migratory birds had not even arrived.

“According to the latest evidence, we have to presume that these animals are able to survive the winters in Germany.”

But he also pointed out that this does not mean that the Hyalomma are home grown.

What is Crimean-Congo haemorrhagic fever?

Crimean-Congo haemorrhagic fever (CCHF) is a widespread disease caused by a tick-borne virus.

It’s usually carried by a wide range of wild and domestic animals such as cattle, sheep and goats.

The virus is transmitted to people either by tick bites or through contact with infected animal blood.

The majority of cases have occurred in people involved in the livestock industry, such as agricultural workers, slaughterhouse workers and veterinarians.

Human-to-human transmission can occur resulting from close contact with the blood, organs or bodily fluids of someone infected.

Signs and symptoms

The time between catching the infection and symptoms appearing is usually one to three days.

Onset of symptoms is sudden and can include:

  • Fever
  • Muscle ache
  • Dizziness
  • Neck pain
  • Backache
  • Headache
  • Sore eyes
  • Nausea
  • Diarrhoea
  • Stomach pain
  • Sore throat
  • Sharp mood swings
  • Confusion

After two to four days, the agitation may be replaced by sleepiness, depression and the stomach pain may have moved.

Other clinical signs include fast heart rate, enlarged lymph nodes and a petechial rash – caused by bleeding into the skin – on internal mucosal surfaces, such as in the mouth and throat, and on the skin.

There is usually evidence of hepatitis, and severely ill patients may experience rapid kidney deterioration, sudden liver failure or pulmonary failure after the fifth day of illness.

Mortality rate is 30 per cent, with death occurring in the second week of illness.

In patients who recover, improvement generally begins on the ninth or tenth day after the onset of illness.

Source: World Health Organisation

Dr Mackenstedt added:

“For the population to expand, a male and a female tick would have to find each other. This is very difficult with such a small number.”

However, five of the Hyalomma ticks were found on a horse at a stables, meaning there is the possibility of a possible pairing – and as a result, the emergence of an independent population.

Last year, German scientists warned about several tropical ticks living in the country – thought to be because of rising temperatures.

Scientists registered a total of seven specimens of the genus Hyalomma in Lower Saxony and Hesse in August 2018.

Meanwhile only two tropical ticks have been found in Germany before, one in 2015 and one in 2017.

The Hyalomma ticks are very noticeable and can grow to as long as 2cm, substantially larger than the local common wood tick.

NINTCHDBPICT000498772067The massive Hyalomma tick, right, compared to a normal-sized deer tick
Central European News

They are recognised by their unusual size and their striped legs.

Hyalomma originated from Iran or the southern part of the former Soviet Union and spread into Asia, the Middle East, southern Europe, and Africa.

Tick bites can cause a number of diseases which in some cases can be fatal such tick-borne encephalitis and Lyme disease.

Hyalomma species can also carry Crimean-Congo hemorrhagic fever, which has already claimed one Brit victim back in 2012.

The 38-year-old man died hours after returning from a wedding in Afghanistan.

_________________

For more on the Monster Tick & CCHF:  https://madisonarealymesupportgroup.com/2018/08/19/monster-ticks-found-in-germany-threaten-europe-with-deadly-disease-crimean-congo-fever/  The one within this link is H. marginatum.  

https://madisonarealymesupportgroup.com/2019/05/23/crimean-congo-hemorrhagic-fever-outbreak-in-africa/

H. rufipes on the UK horse:  https://madisonarealymesupportgroup.com/2019/04/11/african-tick-found-on-untraveled-u-k-horse/

https://madisonarealymesupportgroup.com/2018/06/14/crimean-congo-the-asian-ebola-virus/


https://www.wcax.com/content/news/Adirondack-researcher-raises-the-alarm-on-tick-incursion-511909882.html?ref=882

Adirondack researcher raises the alarm on tick invasion

PLATTSBURGH, N.Y. (WCAX) Ticks are gaining ground in the Adirondacks like never seen before and experts are trying to get the word out.

Courtesy: Adirondack Watershed Institute

They want to make sure people living there including visitors and medical providers know how to spot and treat ticks.

Paul Smith’s College tick researcher Lee Ann Sporn helped organize a panel this week — “A Ticking Time Bomb: The Tick Crisis in the Adirondacks” — and is traveling around different parts of the North Country presenting her latest research.

“The lore, the common lore is still that there isn’t ticks and there are no risk of tick borne diseases here in the North Country. Physicians are still failing to treat people with tick bites because they say this is a no risk, or low risk tick borne disease area, which now is really untrue, so we’re really trying to get that word out,” Sporn said.

The best way to protect yourself from ticks includes covering your skin by wearing light and bright colors, use an insecticide like pyrethrin, and do a tick check from head-to-toe when you get home.

_________________

**Comment**

At this point, any doctor who fails to treat people with tick bites should be turned into the medical board.
Ticks are everywhere.

https://madisonarealymesupportgroup.com/2019/03/09/danish-study-shows-migrating-birds-are-spreading-ticks-their-pathogens-including-places-without-sustainable-tick-populations/

https://madisonarealymesupportgroup.com/2019/04/03/ticks-lyme-are-in-cities-too/

https://madisonarealymesupportgroup.com/2019/06/07/ny-tick-study-challenges-belief-that-tickborne-disease-risk-is-only-in-natural-settings/

Please watch this video of how ticks were found in the cracks of sidewalks in CA:  https://madisonarealymesupportgroup.com/2019/05/17/video-showing-questing-ticks-in-the-middle-of-the-sidewalk/

Ticks have been found in caves, on rocks, underneath picnic benches, and have fallen from trees onto patios:  https://madisonarealymesupportgroup.com/2018/06/07/ticks-on-beaches/

Ticks found on eyeball, butt, and penis:  https://madisonarealymesupportgroup.com/2017/07/30/ticks-found-on-eyeball-buttocks-and-penis/

https://madisonarealymesupportgroup.com/2019/06/19/a-creepy-bed-time-story-from-stephen-king/ (Tick on eye)

Tick in ear had to be surgically removed:  https://madisonarealymesupportgroup.com/2019/05/02/tick-in-boys-ear-had-to-be-surgically-removed/

It’s a good thing they don’t fly.  But, they do blow in the wind. Advocates have told me stories of ticks blowing into their swimming pools. My neighbor with a farm field mowed his lawn, blowing the grass toward my house. I found ticks crawling on my basement screens and a few found their way inside the house on the walls.

The tick maps should be thrown into the trash.

For far too long patients have been denied diagnosis and treatment based on a piece of paper telling them where ticks are supposed to be.

This is STILL happening as this is being written:  https://madisonarealymesupportgroup.com/2019/04/22/its-just-crazy-why-is-lyme-disease-treatment-so-difficult-to-find-in-mississippi/


https://www.thechronicleherald.ca/opinion/opinion-how-many-cases-of-lyme-disease-are-we-missing-327404/

OPINION: How many cases of Lyme disease are we missing?

 Black-legged, or deer ticks are not the only kind of tick that can transmit disease, dog ticks like the one shown here and have been found to carry a number of things, writes Donna Lugar. - 123RF
Black-legged, or deer ticks are not the only kind of tick that can transmit disease, dog ticks like the one shown here and have been found to carry a number of things, writes Donna Lugar. – 123RF

DONNA LUGAR

I participated in a “Tick Talk” in Bedford with Lisa Ali Learning of AtlanTick on June 25. One takeaway from that meeting, for me anyway, is that we are not doing enough to ensure Nova Scotians are adequately aware of the risks associated with tick bites. One family, new to the country, had never even heard of ticks before one recently attached to their child.

Although there has been a steady increase in awareness initiatives over the past few years, we need to continue to do more to reduce the number of new cases of Lyme and tick-borne diseases. One way to do this is through more “in your face” awareness, such as signage, print media and radio/TV alerts. Nova Scotians need to reach out to all three levels of government to request that more is done.

Nova Scotians need to know that any tick that bites them could potentially transmit an illness. Black-legged (deer) ticks are not the only kind of tick that can transmit disease, and Lyme is not the only thing we need to worry about. Dog (wood) ticks have been found to carry a number of things, and Lone Star ticks have been found sporadically within the province. As well, migratory birds could be dropping other types of ticks within the province that we haven’t even discovered yet. Any tick that bites a human could potentially be carrying disease — sometimes multiple illnesses.

Symptoms can vary from person to person, with some not showing any outward, visible signs, so medical professionals need to listen to their patients and start to put two and two together.

Please learn what preventative measures to take and how to properly remove attached ticks. This document, which I prepared, provides a lot of information, including how to remove a tick, what to do to prevent tick bites, as well as outlining a number of potential co-infections.

We also need to do more to ensure that those bitten receive a quick diagnosis and appropriate treatment. It’s time our doctors learn that, according to the Canadian Adverse Reaction Newsletter, Volume 22, Issue 4, October, 2012, there are at least three possible reasons for a false negative ELISA/Western Blot.

  • The fact that the test is performed too early (which most are aware of)
  • It could be a different strain of the Borrelia bacteria not picked up by the test (we also have Borrelia miyamotoi in the province, which can cause a Lyme-like illness and doesn’t generally present with a rash)
  • Antibiotic use. If you were put on antibiotics for something between the bite and the test, or only received a one-day prophylactic treatment upon the bite, you could always test false-negative.

According to Conquering Lyme Disease, a book by doctors at the Columbia University Medical Center, “false negative rates on the ELISA have been reported as high as 67 per cent in early Lyme disease and 21 per cent in early neurologic Lyme disease.” The potential for people to not form enough antibodies to be picked up by the test is also possible.

If your test is negative, it doesn’t mean you do not have Lyme!

There is a proviso in Guidance for Primary Care and Emergency Medicine Providers in the Management of Lyme Disease in Nova Scotia that states, on page five, No: 3, under IDEG Recommends: “Patients presenting with a non-specific febrile illness, but no EM–like rash, AND a recent, clear exposure in an area at moderate or higher risk for Lyme disease (https://novascotia.ca/dhw/CDPC/lyme.asp) should be tested and monitored for other symptoms suggestive of Lyme disease. Repeat testing in 4-6 weeks is suggested if there are still concerns that the patient has Lyme disease.” I have only heard from a few people who received repeat testing and that was usually at their own insistence.

Also very important to note is that Lyme is supposed to be a clinical diagnosis, with testing supplementary. Unfortunately, doctors may recognize the better-known bull’s-eye rash, but that is only seen in 20-30 per cent of cases (if that). Other types of erythema migrans rashes are more common. About 20 per cent do not get any rash (Borrelia miyamotoi, perhaps?), while many that do don’t see it because it is tucked away somewhere not easily visible, just like the ticks like to be.

Symptoms can vary from person to person, with some not showing any outward, visible signs (such as an erythema migrans rash, Bell’s palsy, or swollen, hot knees), so medical professionals need to listen to their patients and start to put two and two together. That includes changes in mental health, new digestive issues, new sensitivities to scents, sounds, light and food, migrating pain, more frequent headaches, changes to heartbeats, and so much more that can be suggestive of Lyme and tick-borne diseases.

Rather than immediately dismissing Lyme and tick-borne diseases, as many doctors are still doing to this day, they need to realize that this issue is not rare, hard to get or easy to treat.

In other words, it is very hard to get a diagnosis if you do not see the tick, get the bull’s eye rash version of the erythema migrans rash, and/or test positive on both the ELISA and confirmatory Western Blot.

How many are we missing?

Donna Lugar is Nova Scotia representative of the Canadian Lyme Disease Foundation and founder of the N.S. Lyme Support Group. She lives in Bedford.


https://wwwnc.cdc.gov/eid/article/25/8/19-0399_article

Volume 25, Number 8—August 2019
Research Letter

Polio-like Manifestation of Powassan Virus Infection with Anterior Horn Cell Involvement, Canada

Picheca C, Yogendrakumar V, Brooks JI, Torres C, Pringle E, Zwicker J. Polio-like manifestation of Powassan virus infection with anterior horn cell involvement, Canada. Emerg Infect Dis. 2019 Aug [date cited]. https://doi.org/10.3201/eid2508.190399

DOI: 10.3201/eid2508.190399

Original Publication Date: 6/3/2019

Abstract

Evidence of spinal cord involvement in Powassan virus infection is largely limited to mouse models. We report a case of a polio-like illness caused by Powassan virus infection in a 62-year-old man in Canada. Magnetic resonance imaging showed T2 hyperintensities in the anterior horns of the cervical spinal cord.

Powassan virus (POWV) is a tickborne flavivirus, named after Powassan, Ontario, Canada, the location of the first documented human infection in 1958 (1). Since then, ≈150 cases of POWV infection have been reported globally, and incidence has increased over time. A total of 125 POWV cases have been identified since 2008, 33 (26%) in 2017 (2). In Canada, most reported POWV infections have been in the Great Lakes regions. A small number of cases have been reported in the Maritime provinces (3).

POWV is transmitted by members of the Ixodes genus of ticks, including I. cookei and the more opportunistic and aggressive I. scapularis. POWV has 2 lineages; lineage 2 (deer tick virus) has emerged quickly in parts of North America, along with the expanding range of I. scapularis ticks.

POWV infection typically begins with prodromal symptoms including fever, nausea, headache, and myalgia. Central nervous system involvement includes an altered level of consciousness, paralysis, or ophthalmoplegia (4). POWV encephalitis has a 10% mortality rate, and <50% of survivors suffer residual deficits (5). Studies with mice have demonstrated that POWV can affect motor neurons in the anterior horns of the spinal cord (6). These same neurons are affected by poliovirus, West Nile virus, and enterovirus D68 (7). However, POWV infection with cord involvement in humans is not well documented; 1 human case demonstrated motor neuron pathology after POWV lineage 2 infection (8), and a second case with suspected motor neuronopathy was reported in 2018 (9).

We present the case of a 62-year-old man living in urban Ontario who experienced nausea, vomiting, and abdominal pain while vacationing in rural Newfoundland. He sought treatment at a hospital in Nova Scotia and experienced diplopia (double vision) and ataxia (movement disorder). A computed tomography scan of the head did not show any acute intracranial event.

The patient became febrile and experienced dysarthria (motor speech disorder) weakness, and respiratory distress. Cerebrospinal fluid analysis showed pleocytosis (159 × 106 total nucleated cells: 42% neutrophils, 43% lymphocytes) and elevated protein levels (0.79 g/L). He was started on empiric treatment with ceftriaxone, ampicillin, acyclovir, and dexamethasone. Results of tests for Cryptococcus, HIV, syphilis, Lyme disease, herpes simplex viruses 1 and 2, varicella zoster virus, and acid-fast bacilli were negative. Initial arbovirus serology results were negative. The patient worsened, requiring intubation and transfer to an intensive care unit.

Seven days after arriving at the hospital, the patient was unable to lift his arms and was transferred to a tertiary center in Ottawa, Ontario (The Ottawa Hospital). Neurologic exam showed facial and extraocular muscle weakness. He had flaccid tone and absent power in his upper extremities and reduced strength in his lower extremities. Sensation was preserved. Nerve conduction studies demonstrated diffusely low motor amplitudes, normal sensory amplitudes, and normal conduction velocities suggestive of a motor neuronopathy. Electromyography in the acute phase was not possible due to poor patient cooperation.

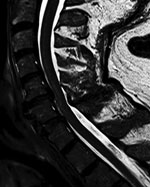
Thumbnail of Coronal T2-weighted image of cervical spinal cord in a patient with Powassan virus infection, Canada. A longitudinal hyperintensity of the anterior horn is visible from C3 to C6.Figure. Coronal T2-weighted image of cervical spinal cord in a patient with Powassan virus infection, Canada. A longitudinal hyperintensity of the anterior horn is visible from C3 to C6.

Results of paired convalescent arbovirus serology collected 1 month after symptom onset were positive. Testing at the National Microbiology Laboratory confirmed POWV infection (hemagglutination inhibition titer 1:80, plaque-reduction neutralization titer 1:160). Magnetic resonance imaging (MRI) of the brain showed infratentorial and supratentorial leptomeningeal enhancement. An MRI of the cervical spine showed increased T2-weighted signal involving the anterior horns from C3 to C6 (Figure; Appendix Figure).

Follow-up MRI of the brain and spine 1 month later showed interval resolution of leptomeningeal abnormalities, but abnormal signal within the anterior horn of the cervical spine remained. Electrodiagnostic testing repeated 6 months after symptom onset again showed normal sensory nerve conduction studies and abnormal motor nerve conduction studies. There was diffuse denervation in all cervical myotomes including the paraspinal muscles, confirming a motor neuronopathy consistent with a poliomyelitis-like presentation of POWV. We suspect that initial arbovirus serology was performed too early in the disease course, because paired serology 4 weeks later demonstrated seroconversion and confirmed diagnosis.

Our case shares similarities with a recently published report of POWV infection (9). In that case, a patient vacationing in the Luskville region of Quebec, Canada, experienced cranial nerve pathologies and flaccid weakness of the upper extremities. Electrodiagnostic testing showed evidence of diffuse denervation and reinnervation across multiple myotomes that was consistent with a motor neuronopathy. Imaging of the brain showed only mild hyperintensities that would not account for the patient’s disproportionate weakness. A spine MRI was not performed. As in our case, acute arbovirus serology results were initially negative but were positive in paired testing (9).

The incidence of POWV infection has increased since 2017 (7). I. scapularis ticks and deer tick virus may be becoming more widely disseminated in northern regions, potentially due to warming climates, whereas infection with prototypical POWV transmitted by I. cookei ticks remains rare and stable in distribution (10). It is possible that Canada will see an increasing number of cases similar to ours. Our findings emphasize the need to include POWV infection in the differential diagnosis for patients with polio-like symptoms in tick-endemic regions.

Dr. Picheca and Dr. Yogendrakumar are resident physicians specializing in neurology at the University of Ottawa. Dr. Picheca has an interest in infectious diseases. Dr. Yogendrakumar’s primary research interests are in stroke and intracerebral hemorrhage.

Top

References

  1. McLEAN  DM, Donohue  WL. Powassan virus: isolation of virus from a fatal case of encephalitis. Can Med Assoc J. 1959;80:708–11.PubMedExternal Link
  2. Centers for Disease Control and Prevention. Statistics & maps: Powassan virus. 2018 [cited 2019 Mar 13]. https://www.cdc.gov/powassan/statistics.html
  3. Corrin  T, Greig  J, Harding  S, Young  I, Mascarenhas  M, Waddell  LA. Powassan virus, a scoping review of the global evidence. Zoonoses Public Health. 2018 [cited 2019 Mar 13].
  4. Sung  S, Wurcel  AG, Whittier  S, Kulas  K, Kramer  LD, Flam  R, et al. Powassan meningoencephalitis, New York, New York, USA. Emerg Infect Dis. 2013;19:19. DOIExternal LinkPubMedExternal Link
  5. Ebel  GD. Update on Powassan virus: emergence of a North American tick-borne flavivirus. Annu Rev Entomol. 2010;55:95–110. DOIExternal LinkPubMedExternal Link
  6. Santos  RI, Hermance  ME, Gelman  BB, Thangamani  S. Spinal cord ventral horns and lymphoid organ involvement in Powassan virus infection in a mouse model. Viruses. 2016;8:220. DOIExternal LinkPubMedExternal Link
  7. Hermance  ME, Thangamani  S. Powassan virus: an emerging arbovirus of public health concern in North America. Vector Borne Zoonotic Dis. 2017;17:453–62. DOIExternal LinkPubMedExternal Link
  8. Tavakoli  NP, Wang  H, Dupuis  M, Hull  R, Ebel  GD, Gilmore  EJ, et al. Fatal case of deer tick virus encephalitis. N Engl J Med. 2009;360:2099–107. DOIExternal LinkPubMedExternal Link
  9. Sanderson  M, Lindsay  LR, Campbell  TM, Morshed  M. A case of Powassan encephalitis acquired in southern Quebec. CMAJ. 2018;190:E1478–80. DOIExternal LinkPubMedExternal Link
  10. Fatmi  SS, Zehra  R, Carpenter  DO. Powassan virus—a new reemerging tick-borne disease. Front Public Health. 2017;5:342. DOIExternal LinkPubMedExternal Link

Figure. Coronal T2-weighted image of cervical spinal cord in a patient with Powassan virus infection, Canada. A longitudinal hyperintensity of the anterior horn is visible from C3 to C6.

__________________

**Comment**

Polio-like systems include:

  • Loss of reflexes
  • Severe muscle aches or weakness
  • Loose and floppy limbs (flaccid paralysis)
  • Muscle wasting (atrophy)
  • Breathing or swallowing problems

Remember, ticks are everywhere. I do not like how the authors state to consider POWV in “endemic regions.” Birds are transporting ticks everywhere – despite the weather.

For more:  https://madisonarealymesupportgroup.com/2016/02/21/powassan-virus/

https://madisonarealymesupportgroup.com/2017/06/28/powassan-can-kill/

https://madisonarealymesupportgroup.com/2019/06/11/death-of-hampton-man-with-rare-tick-borne-virus-probed/  Read comment after article. 

https://madisonarealymesupportgroup.com/2017/05/18/powassan-and-bb-infection-in-wisconsin-and-u-s-tick-populations/

Nearly 80% of adult female I. scapularis ticks analyzed were collected from the northern half of the state (QNW and QNE) and accounted for 85% of POWV-positive ticks. While only 90 I. scapularis ticks were collected from the southern two quadrants, POWV-positive ticks were identified in both QSE and QSW. QNW I. scapularis ticks revealed the highest MLE of infection for both POWV and B. burgdorferi (4.67% and 23.42%, respectively).

Tick-Borne Illness Center

Air Date: Monday, July 1, 2019, 11:00am

Wisconsin Public Radio

There is much to learn about the diseases caused by ticks. We talk with a physician about a new Wisconsin clinic that will diagnosis and treat, but also focuses on research.

Related Links: 

Howard Young Foundation website

Info about the clinic in the Howard Young Foundation newsletter

Host(s): Larry Meiller

Guest(s): Dr. Andreas (Andy) Kogelnik

Producer(s): Jill Nadeau

_____________________

For more:  https://madisonarealymesupportgroup.com/2019/01/11/wisconsin-tick-borne-illness-center-of-excellence/

https://madisonarealymesupportgroup.com/2018/12/16/tick-borne-illness-center-of-excellence-set-to-see-patients-in-early-2019/

https://www.howardyoungfoundation.org/Howard-Young-Foundation-In-the-News/tick-center.html