Dr. Brooke Herndon of Dartmouth-Hitchcock Medical Center, shown at left this month, was told last spring that she appeared to have whooping cough.Credit…Jon Gilbert Fox for The New York Times
Dr. Brooke Herndon, an internist at Dartmouth-Hitchcock Medical Center, could not stop coughing. For two weeks starting in mid-April last year, she coughed, seemingly nonstop, followed by another week when she coughed sporadically, annoying, she said, everyone who worked with her.
Before long, Dr. Kathryn Kirkland, an infectious disease specialist at Dartmouth, had a chilling thought: Could she be seeing the start of a whooping cough epidemic? By late April, other health care workers at the hospital were coughing, and severe, intractable coughing is a whooping cough hallmark. And if it was whooping cough, the epidemic had to be contained immediately because the disease could be deadly to babies in the hospital and could lead to pneumonia in the frail and vulnerable adult patients there.
It was the start of a bizarre episode at the medical center: the story of the epidemic that wasn’t. (See link for article)
__________________
**Comment**
Testing fiascos are part and parcel of the CDC’s MO.
Pathologist: FDA ‘Misled the Public’ on Pfizer Vaccine Efficacy
In an amended reply to the FDA’s rejection of his concerns about Pfizer’s clinical trials, Dr. Sin Hang Lee says the FDA is glossing over potential risks of an mRNA vaccine while concealing its true efficacy.
“Until an accurate count of COVID-19 cases in the vaccinated and placebo groups has been determined for vaccine efficacy evaluation, we are asking the FDA to stay its decision regarding the emergency use authorization for this vaccine.”
Lee’s request was rejected by the FDA on Dec. 11, the same day the agency approved Pfizer’s vaccine for emergency use. On Feb. 8, Lee filed an amended reply.
In the petition and stay, Lee requested the FDA amend the study design for the late-stage trial of Pfizer’s COVID-19 vaccine. Specifically, Lee requests:
“Before an EUA or unrestricted license is issued for the Pfizer vaccine, or for other vaccines for which PCR results are the primary evidence of infection, all “endpoints” or COVID-19 cases used to determine vaccine efficacy in the Phase 3 or 2/3 trials should have their infection status confirmed by Sanger sequencing, given the high cycle thresholds used in some trials. High cycle thresholds, or Ct values, in RT-qPCR test results have been widely acknowledged to lead to false positives … All RT-qPCR-positive test results used to categorize patient as “COVID-19 cases” and used to qualify the trial’s endpoints should be verified by Sanger sequencing to confirm that the tested samples in fact contain a unique SARS-CoV-2 genomic RNA.”
The petition makes these requests because the phase 2/3 clinical trial of the Pfizer COVID-19 vaccine uses a presumptive RT-qPCR (“PCR”) diagnostic test, which is known to generate high rates of false-positive results.
In addition, the Pfizer vaccine trial primarily uses a PCR test that employs cycle thresholds up to 44.9 to identify COVID-19 “cases” despite the fact that “positive” results that require cycle thresholds greater than 30 to 35 are usually false positives, according to Lee.
Lee offered to re-test the residues of tested samples in his laboratory if Pfizer is unable to do so in order to confirm Pfizer’s stated vaccine efficacy rate of 95%.
Lee’s Sanger sequencing-based method for molecular diagnosis of SARS-CoV-2 was published in International Journal of Geriatrics and Rehabilitation.
On Dec. 11, 2020, the same day the FDA granted Pfizer Emergency Use Authorization for its COVID-19 vaccine, the FDA responded to Lee’s petition and request for stay. The agency “conclude[d] that the petitions do not contain facts demonstrating any reasonable grounds for the requested action” and denied the petitions.
The FDA, among other things, stated that “PCR testing does not need to be followed by Sanger or other sequencing for purposes of clinical diagnosis. Currently, reverse real-time PCR (RT-PCR) tests can both amplify and confirm the identity of viral genetic material in a single reaction, without a separate sequencing step.”
On Feb. 8, Lee, through ICAN’s counsel, submitted a detailed and thoroughly cited reply to the FDA’s denial of his petition and stay. This reply points out the inaccuracies, contradictions and omissions in the FDA’s denial of the petition.
Lee wrote that the FDA’s letter denying the petition and stay
“shows that the FDA has not conducted an adequate evaluation of the Pfizer vaccine’s efficacy, especially concerning issues about the accuracy of RT-qPCR testing of SARS-CoV-2 in clinical specimens.”
Lee’s detailed response, which can be read in full here, goes on to say:
“The FDA has misled the public. The key misleading statements are analyzed below point-by-point according to the sequence of their presentation in the Letter but under the following four categories for the convenience of the readers:
“A. Cherry-picking to eviscerate the guidance for issuance of an EUA for a COVID-19 vaccine.
B. Knowingly promoting inaccurate PCR tests for SARS-CoV-2.
C. Finding excuses for using PCR tests with high false-positive rates for this vaccine trial.
D. Glossing over potential risks of an mRNA vaccine while concealing its true efficacy.”
Lee, ICAN and others are weighing possible future actions.
_____________________
**Comment**
You may recognize Dr.Lee due to the following posts:
https://madisonarealymesupportgroup.com/2018/09/29/shocking-flaws-in-gardasil-trial-design-prevents-safety-assessment/Lee confirmed the presence of HPV-16 L1 gene DNA in the girl’s post-mortem blood and spleen tissue — the same DNA fragments found in the vaccine. According to Lee, the fragments were protected from degradation by binding to the aluminum adjuvant used in the vaccine. He suggested their presence might offer a plausible explanation for the high immunogenicity of Gardasil, meaning that the vaccine tends to provoke an exaggerated immune response. He pointed out that the rate of anaphylaxis in girls receiving Gardasil is far higher than normal — reportedly five to 20 times higher than any other school-based vaccination program. Also, According to Lee, vaccines target 70% of HPV strains (though new version targets more strains), and if vaccines were 100% effective, ONE death would be prevented out of 100,000 vaccinated women; 1.3 with newer versions. Cost to vaccinate 1 girl is about $700. $350 for vaccine & $350 for doctor visit. Cost to vaccinate 100,000 girls is approximately $70 million.
Dr. Sin Hang Lee is one of the true-blue researchers left who call a spade a spade.
(Natural News) Around the world, medical authorities are seeing a spike in elderly deaths, after covid-19 vaccination. Gibraltar, a nation located at the southern tip of Spain, is suffering from an unexplained surge in elderly deaths. In the second week of January, a subset of the elderly population suddenly started to die off. The new wave of unexplained elderly deaths is occurring at nearly three times the magnitude of covid-19 deaths that were recorded during 2020.
The new, unexplained surge in elderly deaths is occurring approximately forty times faster when compared to the overall timeline of covid-19 deaths that occurred since a pandemic was first declared. This surge in elderly deaths occurred after 5,847 doses of experimental mRNA injections were administered to the citizens of Gibraltar. In just one week, 17 percent of the country’s population had been inoculated with the first dose of Pfizer’s mRNA experiment.
Before the vaccine experiment began, the covid-19 related death toll accounted for ten people. After the vaccine rollout, the total number of deaths had skyrocketed to forty-five people. In the first eight days of the vaccination program, thirty-five seniors suddenly passed away. (See link for article)
Scientists Warn of Potential COVID Vaccine-Related ‘Ticking Time Bomb’
Studies suggest that COVID vaccines may trigger antibody-dependent enhancement in some people, a condition that could cause them to develop more severe symptoms when exposed to the wild virus than if they hadn’t been vaccinated.
Associate Professor of Health Sciences Adam MacNeil at Brock University, Canada and his Ph.D. student Jeremia Coish were among the earliest to warn, last June, of the dangers of not looking very carefully at the possibility that vaccines might trigger antibody-dependent enhancement(ADE) of disease. This could mean that people who are vaccinated might, paradoxically, suffer more severe disease when exposed to the wild virus than if they hadn’t been vaccinated.
In their aptly titled article, “Out of the frying pan and into the fire? Due diligence warranted for ADE in COVID-19,” published in the journal Microbes and Infection in June 2020, MacNeil and Coish argue that ADE is well known to be a risk for coronavirus-mediated infections, as well as dengue.
For those not already familiar with ADE, it is the paradoxical immune response that makes a person who was previously exposed to the disease, or a vaccine targeting it, more — not less — susceptible in the event that they’re subsequently infected.
Proceed with caution
Seemingly countering this view, in August 2020, was viral epidemiologist Leah Katzelnick Ph.D., a dengue and zika specialist now in the employ of the National Institute for Allergy and Infectious Diseases headed by Dr. Tony Fauci. Along with co-author Scott Halstead,. Katzelnick argued that ADE shouldn’t be something to be feared. Katzelnick and Halstead proposed that the fundamental differences between SARS-CoV-2 infection that can cause COVID-19 and other diseases, for which ADE has been shown, meant that ADE would be highly unlikely.
They supported their arguments with evidence from cases of classic, intrinsic ADE, notably infectious peritonitis, a coronavirus infection in cats, as well as from respiratory syncytial virus, dengue and SARS — suggesting significant differences in the pathology, epidemiology and immune responses involved in these diseases as compared with COVID and SARS-CoV-2 infection.
Careful readers of Halstead and Katzelnick’s paper will note that while the authors largely dismiss the ADE risk, they very clearly identify a risk of vaccine hypersensitivity (or VAH), a closely related immunological hyper-reaction that was first identified in the late 1960s when children developed atypical measles following measles vaccination.
Many who’ve used the paper to dismiss ADE risks may only have read the title and abstract and not picked up that Katzelnick and Halstead dismiss only intrinsic ADE or iADE (i.e. the risk of disease enhancement on re-infection in the absence of vaccination).
They also may not have read the sombre advisory in the paper’s last sentence:
“Given the magnitude of the repertoire of COVID-19 problems and the need for an effective vaccine, the full force of worldwide investigative resources should be directed at unravelling the pathogenesis of VAH.”
There is not much to suggest that this advisory has been heeded, other than the fact that thousands of volunteers have been put through Phase 3 trials and there has been no evidence of spikes in more severe reactions among those vaccinated with the real thing, as opposed to the placebo.
Herbert Virgin, Ann Arvin and colleagues, writing in Nature, one of the most influential journals in the world, made a not dissimilar call for caution back in July. These authors discuss the great difficulties in identifying the incidence and frequency of ADE (and VAH) and suggest that “… it will be essential to depend on careful analysis of safety in humans as immune interventions for COVID-19 move forward.”
Transparency is key
This requires full transparency of surveillance data so that cases of infection and reinfection post-vaccination can be correlated against severe reactions following infection or vaccination. It also requires time — much more time than we’ve had so far.
Presently, data released by VAERS (Vaccine Adverse Event Reporting System) in the U.S. and the MHRA (Medicines and Healthcare products Regulatory Agency) in the UK don’t come close to telling us anything about the ADE or VAH risk. In fact, there will have to be a lot more re-infection before we know conclusively one way or another. And will we be able to find out if there are genuine issues with ADE or VAH, or will the authorities manage to keep a lid on it by just not communicating them given many reactions will be substantially delayed following vaccination?
Timothy Cardozo from New York University and Ronald Veazy from Tulane University took it a step further in their article in the International Journal of Clinical Practice published in October, when Phase 3 trials for the COVID frontrunner vaccines were in full swing. They argued not only that vaccine-mediated ADE (i.e. VAH) risks were more than just theoretical, they also suggest that the risks may be greater following particular types of mutations in the circulating viruses.
In their discussion on SARS-CoV-2, they discuss how very tiny changes, such as changes in the conformity (shape) of its spike protein both before and after fusion with host cells, via ACE2 receptors might impact those who’ve been vaccinated. Several months on with emerging evidence that some variants are able to evade the immune response that has been trained to offer protection against the original Wuhan variants, there is cause for even greater concern. This risk also can’t be dismissed on the basis of the results of the Phase 3 trials
What Cardozo and Veazy also suggest is another point we’ve long been concerned about. That relates to the fact that trial subjects — let alone members of the public who’re now lining up for COVID vaccines — are just not being informed of these potential risks, and the delayed nature of possible ADE/VAH reactions.
What about vaccinees who become ill several months after being vaccinated, suffering the classic range of symptoms associated with many respiratory diseases (including COVID), such as fever, chills, cough, shortness of breath, headache, fatigue, and so on? Will they know that these symptoms might be related to enhanced COVID disease mediated by the vaccination given to them months before, something that didn’t occur to them because they thought the vaccine gave them protection from COVID?
Cardozo and Veazy then show how informed consent forms for volunteer subjects in vaccine trials fail to meet the required ethical standards for informed consent. While ADE is mentioned, it is generally added at the end of the list of possible risks and its implications and identification are unlikely to be adequately understood by the lay public.
With a tick in the box and a sense from regulators and vaccine makers that they’ve successfully negotiated the hurdle of ADE/VAH risks, there’s been no further discussion of the issue. The vast majority of pre-vaccinees lining up as part of the global mass vaccination roll out simply have no idea of the risk — because they’re not being told.
Could ADE be a ticking time bomb?
Does non-disclosure as part of the informed consent process constitute not only a breach of medical ethics, but also a breach of law? In our view, that’s highly likely and should evidence accrue in the future, this will be something the courts will need to grapple with.
Presently there is no evidence of any significant ADE/VAH signal — but it is too early to tell and many cases could have gone undetected.
Is it possible that some instances of ‘long COVID’ could be a form of ADE? This is a possibility we have been considering. Typically people who get long COVID don’t test as positive from nasopharyngeal swab tests. But in deep seated systemic infections the mucosa may not show evidence of viral multiplication, whereas the infection may become systemic in certain tissues and be enhanced. This possibility cannot easily be dismissed.
Could the problem increase with new variants of SARS-CoV-2? Yes, as explained above.
What you can do:
Anyone who is deciding to have the vaccine should inform themselves of the ADE and VAH risk, where there could be a considerable delay between vaccination and the experience of disease symptoms that may be more severe than those that would occur without the vaccine.
Wednesday, February 17, 2021 – 6 p.m. EST / 3 p.m. PST / 5 p.m. CST
In March 2020, the CDC abruptly changed how death certificates were recorded. While this might seem like a mere formality, the CDC only made this change for one type of death — COVID-19 — and circumvented multiple federal laws to do so.
Join our panel of experts — researchers, doctors, lawyers, medical ethicists, educators and lawmakers — as they take an in-depth look at the CDC’s actions and the dire consequences they’ve had on all of American society. This includes unending lockdowns, school and business closures, an increase in suicides and mental health issues, economic hardship and despair, loved ones being forced to die all alone, and many more atrocities that have been inflicted on individuals in the name of “protecting public health.”
Tune in to Learn:
Why we should be concerned about death certificate data.
Why accuracy, integrity and transparency are so important during a public health crisis.
How the CDC set the stage for widespread devastation — physical, psychological and economic.
Simple steps we can take so that incidents of this magnitude never happen again.
Watch the Live Event Here
Panelists
Sayer Ji (Moderator)
Founder of GreenMedInfo and Co-founder, Stand for Health Freedom
Dr. Peter Breggin
World-renowned psychiatrist and medical ethicist
Mary Starrett
Board of Commissioners Chair, Yamhill County, Oregon
Dr. David Martin
Founder and CEO of M·CAM Inc. and University of Virginia Batten Fellow
Mark Thielman
School superintendent, Alsea School District
Ana Garner, Esq.
Attorney and legal mediator
Dennis Linthicum
Oregon state senator
Dr. James Lyons-Weiler
Biomedical research scientist and public health policy journal editor-in-chief
Dr. Henry Ealy
Naturopathic physician and biomedical research scientist
We believe that a federal investigation would reveal that the CDC irreparably compromised data quality during a time of public crisis through its apparent failure to follow established laws for changing the recording of COVID-19 mortality metrics.
The CDC’s actions come with great costs to society. Had COVID-19 data not been manipulated, our state of emergency conditions and responses would have likely been vastly different, with far fewer negative consequences to the American public.
It is not acceptable that the agency that is entrusted with protecting the health of our country set the stage for widespread national devasta
_____________________
**Comment**
Many do not know that the CDC started out in 1946 as mosquito spraying company: https://www.cdc.gov/about/history/index.html A year later it paid $10 for 15 acres in Atlanta where headquarters have been ever since.
All tick-borness illnesses should be reportable to the state. Since many are not reportable, this too minimizes the problem. You can’t recognize something that isn’t being tracked or tracked properly. This is how the CDC/IDSA/NIH continues to downplay this plague. The continuing mythology surrounding all aspects of this devastating illness confines it into a simplistic box when in fact the only box it fits into is Pandora’s.
Meanwhile, they’veriggedeverything to be COVID – falsely inflating numbers. Don’t be duped. The CDC has a reason for everything it does, from downplaying Lyme/MSIDS to hyping COVID.
By referring to COVID-19 vaccines as “vaccines” rather than gene therapies, the U.S. government is violating its 15 U.S. Code Section 41, which regulates deceptive practices in medical claims
The mRNA injections are gene therapies that do not fulfill a single criteria or definition of a vaccine
COVID-19 “vaccines” do not impart immunity or inhibit transmissibility of the disease. They only are designed to lessen your infection symptoms if or when you get infected. As such, these products do not meet the legal or medical definition of a vaccine
Since a vast majority of people who test positive for SARS-CoV-2 have no symptoms at all, they’ve not even been able to establish a causal link between the virus and the clinical disease
By calling this experimental gene therapy technology a “vaccine,” they are circumventing liability for damages that would otherwise apply
Did you know that mRNA COVID-19 vaccines aren’t vaccines in the medical and legal definition of a vaccine? They do not prevent you from getting the infection, nor do they prevent its spread. They’re really experimental gene therapies.
I discussed this troubling fact in a recent interview with molecular biologist Judy Mikovits, Ph.D. While the Moderna and Pfizer mRNA shots are labeled as “vaccines,” and news agencies and health policy leaders call them that, the actual patents for Pfizer’s and Moderna’s injections more truthfully describe them as “gene therapy,” not vaccines.
Definition of ‘Vaccine’
According to the U.S. Centers for Disease Control and Prevention,1 a vaccine is “a product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.” Immunity, in turn, is defined as “Protection from an infectious disease,” meaning that “If you are immune to a disease, you can be exposed to it without becoming infected.”
Neither Moderna nor Pfizer claim this to be the case for their COVID-19 “vaccines.” In fact, in their clinical trials, they specify that they will not even test for immunity.
Unlike real vaccines, which use an antigen of the disease you’re trying to prevent, the COVID-19 injections contain synthetic RNA fragments encapsulated in a nanolipid carrier compound, the sole purpose of which is to lessen clinical symptoms associated with the S-1 spike protein, not the actual virus.
They do not actually impart immunity or inhibit transmissibility of the disease. In other words, they are not designed to keep you from getting sick with SARS-CoV-2; they only are supposed to lessen your infection symptoms if or when you do get infected.
As such, these products do not meet the legal or medical definition of a vaccine, and as noted by David Martin, Ph.D., in the video above, “The legal ramifications of this deception are immense.”
15 U.S. Code Section 41
As explained by Martin, 15 U.S. Code Section 41 of the Federal Trade Commission Act2 is the law that governs advertising of medical practices. This law, which dictates what you may and may not do in terms of promotion, has for many years been routinely used to shut down alternative health practitioners and companies.
“If this law can be used to shut down people of good will, who are trying to help others,” Martin says, “it certainly should be equally applied when we know deceptive medical practices are being done in the name of public health.”
Per this law, it is unlawful to advertise:
“… that a product or service can prevent, treat, or cure human disease unless you possess competent and reliable scientific evidence, including, when appropriate, well-controlled human clinical studies, substantiating that the claims are true at the time they are made.”3
What Constitutes ‘The Greater Good’?
Martin points to the 1905 Supreme Court ruling in Jacobson vs. Massachusetts,4 which essentially established that collective benefit supersedes individual benefit. To put it bluntly, it argued that it’s acceptable for individuals to be harmed by public health directives provided it benefits the collective.
Now, if vaccination is a public health measure that is supposed to protect and benefit the collective, then it would need to a) ensure that the individual who is vaccinated is rendered immune from the disease in question; and b) that the vaccine inhibits transmission of the disease.
Only if these two outcomes can be scientifically proven can you say that vaccination protects and benefits the collective — the population as a whole. This is where we run into problems with the mRNA “vaccines.”
Moderna’s SEC filings, which Martin claims to have carefully reviewed, specifies and stresses that its technology is a “gene therapy technology.” Originally, its technology was set up to be a cancer treatment, so more specifically, it’s a chemotherapy gene therapy technology.
As noted by Martin, who would raise their hand to receive prophylactic chemotherapy gene therapy for a cancer you do not have and may never be at risk for? In all likelihood, few would jump at such an offer, and for good reason.
Moreover, states and employers would not be able to mandate individuals to receive chemotherapy gene therapy for a cancer they do not have. It simply would not be legal. Yet, they’re proposing that all of humanity be forced to get gene therapy for COVID-19.
COVID-19 Vaccines — A Case of False Advertising
Now, if the COVID-19 vaccine really isn’t a vaccine, why are they calling it that? While the CDC provides a definition of “vaccine,” the CDC is not the actual law. It’s an agency empowered by the law, but it does not create law itself. Interestingly enough, it’s more difficult to find a legal definition of “vaccine,” but there have been a few cases. Martin provides the following examples:
• Iowa code — “Vaccine means a specially prepared antigen administered to a person for the purpose of providing immunity.” Again, the COVID-19 vaccines make no claim of providing immunity. They are only designed to lessen symptoms if and when you get infected.
• Washington state code — “Vaccine means a preparation of a killed or attenuated living microorganism, or fraction thereof …” Since Moderna and Pfizer are using synthetic RNA, they clearly do not meet this definition.
Being a manmade synthetic, the RNA used is not derived from anything that has at one point been alive, be it a whole microorganism or a fraction thereof. The statute continues to specify that a vaccine “upon immunization stimulates immunity that protects us against disease …”
So, in summary, “vaccine” and “immunity” are well-defined terms that do not match the end points specified in COVID-19 vaccine trials. The primary end point in these trials is: “Prevention of symptomatic COVID-19 disease.” Is that the same as “immunity”? No, it is not.
There Are More Problems Than One
But there’s another problem. Martin points out that “COVID-19 disease” has been defined as a series of clinical symptoms. Moreover, there’s no causal link between SARS-CoV-2, the virus, and the set of symptoms known as COVID-19.
How is that, you might ask? It’s simple, really. Since a vast majority of people who test positive for SARS-CoV-2 have no symptoms at all, they’ve not been able to establish a causal link between the virus and the clinical disease.
Here’s yet another problem: The primary end point in the COVID-19 vaccine trials is not an actual vaccine trial end point because, again, vaccine trial end points have to do with immunity and transmission reduction. Neither of those were measured.
What’s more, key secondary end points in Moderna’s trial include “Prevention of severe COVID-19 disease, and prevention of infection by SARS-CoV-2.” However, by its own admission, Moderna did not actually measure infection, stating that it was too “impractical” to do so.
That means there’s no evidence of this gene therapy having an impact on infection, for better or worse. And, if you have no evidence, you cannot fulfill the U.S. Code requirement that states you must have “competent and reliable scientific evidence … substantiating that the claims are true.”
Why Are They Calling Them Vaccines?
As noted by Martin, you cannot have a vaccine that does not meet a single definition of a vaccine. So, again, what would motivate these companies, U.S. health agencies and public health officials like Dr. Anthony Fauci to lie and claim that these gene therapies are in fact vaccines when, clearly, they are not?
If they actually called it what it is, namely “gene therapy chemotherapy,” most people would — wisely — refuse to take it. Perhaps that’s one reason for their false categorization as vaccines. But there may be other reasons as well.
Here, Martin strays into conjecture, as we have no proof of their intentions. He speculates that the reason they’re calling this experimental gene therapy technology a “vaccine” is because by doing so, they can circumvent liability for damages.
As long as the U.S. is under a state of emergency, things like PCR tests and COVID-19 “vaccines” are allowed under emergency use authorization. And as long as the emergency use authorization is in effect, the makers of these experimental gene therapies are not financially liable for any harm that comes from their use.
That is, provided they’re “vaccines.” If these injections are NOT vaccines, then the liability shield falls away, because there is no liability shield for a medical emergency countermeasure that is gene therapy.
So, by maintaining the illusion that COVID-19 is a state of emergency, when in reality it is not, government leaders are providing cover for these gene therapy companies so that they can get immunity from liability.
Under the Cover of ‘Emergency’
As noted by Martin, if state governors were to lift the state of emergency, all of a sudden the use of RT PCR testing would be in violation of 15 U.S. Code FTC Act, as PCR tests are not an approved diagnostic test.
“You cannot diagnose a thing [with something] that cannot diagnose a thing,” Martin says.“That a misrepresentation. That is a deceptive practice under the Federal Trade Commission Act. And they’re liable for deceptive practices.”
Importantly, there’s no waiver of liability under deceptive practices — even under a state of emergency. This would also apply to experimental gene therapies. The only way for these gene therapies to enjoy liability shielding is if they are vaccines developed in response to a public health emergency. There is no such thing as immunity from liability for gene therapies.
Propaganda and Vaccine Rollout Run by Same Company
Martin brings up yet another curious point. The middleman in Operation Warp Speed is a North Carolina defense contractor called ATI. It controls the rollout of the vaccine. But ATI also has another type of contract with the Department of Defense, namely managing propaganda and combating misinformation.
So, the same company in charge of manipulating the media to propagate government propaganda and censor counterviews is the same company in charge of the rollout of “vaccines” that are being unlawfully promoted.
“Listen,” Martin says. “This is a pretty straight-forward situation. You’re being lied to. Your own government is violating its own laws … They have thrown this book [15 U.S. Code Section 41] on more people than we can count.
They have shut down practitioners around the country, time and time again, for violating what are called ‘deceptive practices in medical claims’ … Guess what? They’re doing exactly that thing.”
Martin urges listeners to forward his video to your state attorney, governor, representatives and anyone else that might be in a position to take affirmative action to address and correct this fraud.
Defense contractors are violating FTC law, and gene therapy companies — not vaccine manufacturers — are conducting experimental trials under deceptive medical practices. They’re making claims of being “vaccines” without clinical proof, and must be held accountable for their deceptive marketing and medical practices.
CDC Owns Coronavirus Patents
On a side note, the CDC appears to be neck-deep in this scam pandemic, and is therefore wholly unsuitable to investigate the side effects of these experimental COVID-19 therapies. As noted by Martin, it’s like having a bank robber investigate its own crime.
Details about this came out in the documentary “Plandemic,” in which Martin explained how the CDC has broken the law — in one way or another — related to its patenting of the 2003 SARS virus.
Martin is a national intelligence analyst and founder of IQ100 Index, which developed linguistic genomics, a platform capable of determining the intent of communications. In 1999, IBM digitized 1 million U.S. patents, which allowed Martin’s company to conduct a review of all these patents, sending him down a proverbial “rabbit trail” of corruption.
In 2003, Asia experienced an outbreak of SARS. Almost immediately, scientists began racing to patent the virus. Ultimately, the CDC nabbed ownership of SARS-CoV (the virus responsible for SARS) isolated from humans.
So, the CDC actually owns the entire genetic content of that SARS virus. It’s patented under U.S. patent 7776521. They also own patents for detection methods, and for a kit to measure the virus.
U.S. patent 7279327,5 filed by the University of North Carolina at Chapel Hill, describes methods for producing recombinant coronaviruses. Ralph Baric, Ph.D., a professor of microbiology and immunology who is famous for his chimeric coronavirus research, is listed as one of the three inventors, along with Kristopher Curtis and Boyd Yount.
According to Martin, Fauci, Baric and the CDC “are at the hub” of the whole COVID-19 story. “In 2002, coronaviruses were recognized as an exploitable mechanism for both good and ill,” Martin says, and “Between 2003 and 2017, they [Fauci, Baric and CDC] controlled 100% of the cash flow to build the empire around the industrial complex of coronavirus.”
How the CDC Broke the Law
The key take-home message Martin delivers in “Plandemic” is that there’s a distinct problem with the CDC’s patent on SARS-CoV isolated from humans, because, by law, naturally occurring DNA segments are prohibited from being patented.
The law clearly states that such segments are “not patent eligible merely because it has been isolated.” So, either SARS-CoV was manmade, which would render the patent legal, or it’s natural, thus rendering the patent on it illegal.
However, if the virus was manufactured, then it was created in violation of biological weapons treaties and laws. This includes the Biological Weapons Anti-Terrorism Act of 1989, passed unanimously by both houses of Congress and signed into law by George Bush Sr., which states:6
“Whoever knowingly develops, produces, stockpiles, transfers, acquires, retains, or possesses any biological agent, toxin, or delivery system for use as a weapon, or knowingly assists a foreign state or any organization to do so, shall be fined under this title or imprisoned for life or any term of years, or both. There is extraterritorial Federal jurisdiction over an offense under this section committed by or against a national of the United States.”
So, as noted by Martin in the documentary, regardless of which scenario turns out to be true, the CDC has broken the law one way or another, either by violating biological weapons laws, or by filing an illegal patent. Even more egregious, May 14, 2007, the CDC filed a petition with the patent office to keep their coronavirus patent confidential.
Now, because the CDC owns the patent on SARS-CoV, it has control over who has the ability to make inquiries into the coronavirus. Unless authorized, you cannot look at the virus, you cannot measure it or make tests for it, since they own the entire genome and all the rest.
“By obtaining the patents that restrained anyone from using it, they had the means, the motive, and most of all, they had the monetary gain from turning coronavirus from a pathogen to a profit,” Martin says.
In the lecture above, Dr. Simone Gold — founder of America’s Frontline Doctors, which has been trying to counter the false narrative surrounding hydroxychloroquine — reviews the dangers discovered during previous coronavirus vaccine trials, and the hazards of current mRNA gene therapies, including antibody-dependent immune enhancement.
Antibody-dependent immune enhancement results in more severe disease when you’re exposed to the wild virus, and increases your risk of death. The synthetic RNA and the nanolipid its encased in may also have other, more direct side effects. As explained by Mikovits in our recent interview:
“Normally, messenger RNA is not free in your body because it’s a danger signal. The central dogma of molecular biology is that our genetic code, DNA, is transcribed, written, into the messenger RNA. That messenger RNA is translated into protein, or used in a regulatory capacity … to regulate gene expression in cells.
So, taking a synthetic messenger RNA and making it thermostable — making it not break down — [is problematic]. We have lots of enzymes (RNAses and DNAses) that degrade free RNA and DNA because, again, those are danger signals to your immune system. They literally drive inflammatory diseases.
Now you’ve got PEG, PEGylated and polyethylene glycol, and a lipid nanoparticle that will allow it to enter every cell of the body and change the regulation of our own genes with this synthetic RNA, part of which actually is the message for the gene syncytin …
Syncytin is the endogenous gammaretrovirus envelope that’s encoded in the human genome … We know that if syncytin … is expressed aberrantly in the body, for instance in the brain, which these lipid nanoparticles will go into, then you’ve got multiple sclerosis.
The expression of that gene alone enrages microglia — literally inflames and dysregulates the communication between the brain microglia — which are critical for clearing toxins and pathogens in the brain and the communication with astrocytes.
It dysregulates not only the immune system, but also the endocannabinoid system, which is the dimmer switch on inflammation. We’ve already seen multiple sclerosis as an adverse event in the clinical trials … We also see myalgic encephalomyelitis. Inflammation of the brain and the spinal cord …”
Making matters worse, the synthetic mRNA also has an HIV envelope expressed in it, which can cause immune dysregulation. As we discussed in previous interviews, SARS-CoV-2 has been engineered in the lab with gain-of-function research that included introducing the HIV envelope into the spike protein.
Are You in a High-Risk Group for Side Effects?
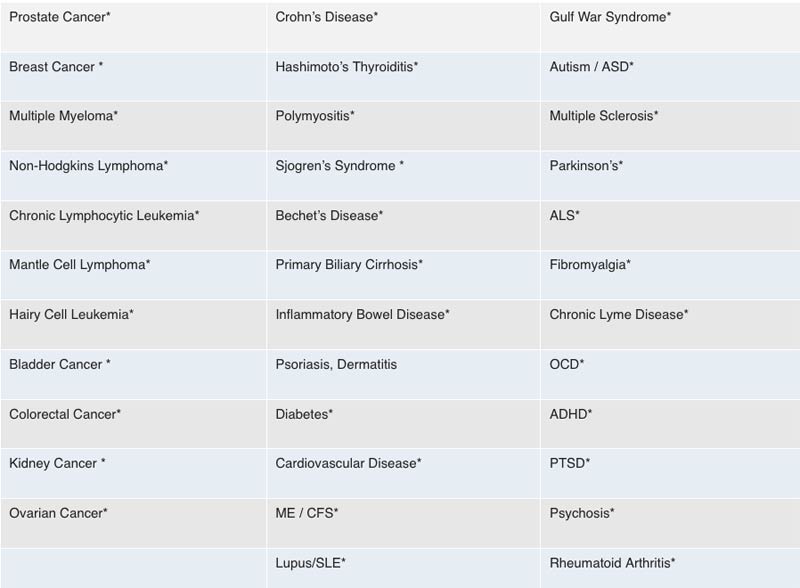
Mikovits’ hypothesis is that those who are most susceptible to severe neurological side effects and death from the COVID-19 vaccines are those who have previously been injected with XMRVs, borrelia, babesia or mycoplasma through contaminated vaccines, resulting in chronic disease, as well as anyone with an inflammatory disease like rheumatoid arthritis, Parkinson’s disease or chronic Lyme disease, for example, and anyone with an acquired immune deficiency from any pathogens and environmental toxins.
The chart below lists 35 diseases that are likely to render you more susceptible to severe side effects or death from COVID-19 gene therapy injections.
Many of the symptoms now being reported are suggestive of neurological damage. They have severe dyskinesia (impairment of voluntary movement), ataxia (lack of muscle control) and intermittent or chronic seizures. Many cases detailed in personal videos on social media are quite shocking. According to Mikovits, these side effects are due to neuroinflammation, a dysregulated innate immune response, and/or a disrupted endocannabinoid system.
Another common side effect from the vaccine we’re seeing is allergic reactions, including anaphylactic shock. A likely culprit in this is PEG (polyethylene glycol), which an estimated 70% of Americans are allergic to.
Experimental Gene Therapy Is a Bad Idea
Circling back to where we began, COVID-19 vaccines are not vaccines. They are experimental gene therapies that are falsely marketed as vaccines, likely to circumvent liability. World governments and global and national health organizations are all complicit in this illegal deception and must be held accountable.
Ask yourself the question Martin asked in his video: Would you agree to take an experimental chemotherapy gene therapy for a cancer you do not have? If the answer is no, then why would you even consider lining up for an experimental gene therapy for COVID-19 — a set of clinical symptoms that haven’t even been causally linked to SARS-CoV-2?
These injections are not vaccines. They do not prevent infection, they do not render you immune, and they do not prevent transmission of the disease. Instead, they alter your genetic coding, turning you into a viral protein factory that has no off-switch. What’s happening here is a medical fraud of unprecedented magnitude, and it really needs to be stopped before it’s too late for a majority of people.
_______________________
**Comment**
Remember, the same people/organizations behind the Lyme/MSIDS fraud are behind the current fraud surrounding COVID. They’ve been committing fraud for over 40 years and they haven’t stopped.
PLEASE NOTE CHRONIC LYME IS LISTED AS HIGH RISK FOR SIDE EFFECTS.
The entire house of cards is built upon faulty testing. Please see the following quote from the creator of the PCR test who states this fact:
It discusses the nanotechnology used in the COVID testing swab:https://www.sciencedirect.com/science/article/abs/pii/S0169409X08002640 (Are we being tested or vaccinated and nano chipped without our knowledge?) A Morgellons patient states that the same silver fibers coming out of her body are found in the COVID test swab. https://www.morgellonsexposed.com A doctor discusses this at about 12:00 (these fibers won’t burn).
Gene editing
At about 17:50 Dr. Lorraine Day states that this genetic modification makes you patentable. She states that the COVID test vaccinates you & hooks you up to the Cloud. The following patents are revealing: https://patents.google.com/patent/US10163055B2/enAbstract: Methods, systems, and products provide interfaces between intrahost networks and interhost networks within biological hosts. Neuroregional translations are performed to route communications to and from the biological hosts. Bioregional translations may also be performed to route communications to and from the biological hosts. Also see: https://madisonarealymesupportgroup.com/2020/04/29/gates-patent-for-body-activity-data-apparatus/Abstract:“Human body activity associated with a task provided to a user(1) may be used in a mining process of a cryptocurrency system. A server may provide a task to a device of a user which is communicatively coupled to the server(2). A sensor communicatively coupled to or comprised in the device(3) of the user may sense body activity of the user. Body activity data may be generated based on the sensed body activity of the user. The cryptocurrency system communicatively coupled to the device of the user may verify if the body activity data satisfies one or more conditions set by the cryptocurrency system(4), and award cryptocurrency to the user whose body activity data is verified.”(5)
Around 29:00 Dr. Martin goes into how the COVID injection is NOT a vaccine but a pathogen creator, and that the use of the term “vaccine” for this is unconscionable. A “packet of technology” is being inserted into the human body.
The Chinese biological lab in Wuhan is owned by GlaxoSmith Kline which merged with and owns 70% controlling stake in Pfizer (a COVID injection manufacturer). Pfizer manages the finances of Black Rock & Black Rock owns stakes in both Pfizer, AstraZeneca, and another company developing a COVID injection. Black Rock also has a partnership with Thompson Reuters, a multimillion dollar national media conglomerate, which essentially controls all the news.
The COVID-19 test kit (902780) was ordered back in 2018 by many countries including the U.S.
There’s an important section on anaphylaxis and a bit of history on Charles Richet’s work found here: https://www.nobelprize.org/prizes/medicine/1913/richet/lecture/ In short, it’s all about the importance of the interval between injections. Experiments by 1902 showed: (1) a subject that had a previous injection is far more sensitive than a new subject; (2) that the symptoms characteristic of the second injection, namely swift and total depression of the nervous system, do not in any way resemble the symptoms characterizing the first injection; (3) a three or four week period must elapse before the anaphylactic state results. This is the period of incubation. This 3 weeks is now what the UK is recommending for the second dose.
This alleged virus has never been isolated, has the same survival rate as the flu, many are asymptomatic or have mild symptoms, and those that die are typically elderly with comorbidities. Also – the seasonal flu has completely disappeared: https://madisonarealymesupportgroup.com/2020/11/03/why-is-cdc-scaring-us-to-death/ Yet our public ‘authorities’ want us to believe that we must get this shot due to some horrific threat.
At about 1:43 Dr. Cowan describes 31 papers from peer-reviewed journals claiming isolation of COVID-19. Here’s another similar article: https://blog.nomorefakenews.com/2020/10/19/dr-tom-cowan-explores-the-covid-virus-invented-out-of-sheer-nonsense/He states there is NOT ONE study proving COVID-19 exists. His explanation needs to be understood and shared. This is the root of the issue scientifically. Please listen to his explanation as he does a fantastic job explaining this to the lay-man.