Archive for the ‘Treatment’ Category

Depression Not Caused by Chemical Imbalance

https://articles.mercola.com/sites/articles/archive/2018/01/18/chemical-imbalance-theory-for-depression.aspx?

Depression Not Caused by Chemical Imbalance  

depression

January 18, 2018

Story at-a-glance

  • Many people believe depression is caused by a chemical imbalance in the brain; this chemical imbalance theory has been widely promoted by drug companies and psychiatrists alike — without evidence to back it up
  • Pharmaceutical companies were instrumental in bringing the chemical imbalance theory to the mainstream, heavily promoting it as a marketing gimmick to sell antidepressant drugs
  • Studies have repeatedly shown antidepressants work no better than placebo for mild to moderate depression, yet carry a significant risk of side effects
  • Depression is likely the result of multiple environmental and biological factors, including faulty mood regulation by the brain, genetic vulnerability, stressful life events, nutrition, medications and medical problems, among others

By Dr. Mercola

Do you know what causes depression? Many people would respond that it’s due to a chemical imbalance in the brain. This chemical imbalance theory has been widely promoted by drug companies and psychiatrists alike, to the extent that it’s accepted as fact. The glaring problem is that the chemical imbalance theory is just that — a theory — and worse still, it’s a theory that has been largely discredited.

The theory was first proposed by scientists in the 1960s after it appeared certain antidepressant drugs worked by altering brain chemicals, but it was stated that “the findings are inconclusive.”1 Yet, the theory was proposed at a time when treating mental illness via psychoanalysis was falling out of favor while viewing it as tied to a physical or biological mechanism was in vogue.

The idea quickly spread, becoming the medical dogma for depression, despite concrete evidence proving its worth. “The fact that practicing physicians and leaders of science bought that idea, to me, is so disturbing,” Steve Hyman, director of the Stanley Center for Psychiatric Research at the Broad Institute of MIT and Harvard, told Quartz.2 The news outlet continued:

“It’s not hard to see why the theory caught on: It suited psychiatrists’ newfound attempt to create a system of mental health that mirrored diagnostic models used in other fields of medicine. The focus on a clear biological cause for depression gave practicing physicians an easily understandable theory to tell patients about how their disease was being treated.”3

Prozac, Zoloft Bring Chemical Imbalance Theory for Depression to the Mainstream

The release of the antidepressant Prozac (fluoxetine) in the late 1980s was a game changer for depression treatment in that the drug’s maker, Eli Lilly, heavily promoted the chemical balance theory as a marketing gimmick to sell the drug. With fewer side effects than some of the earlier antidepressants, Prozac became a blockbuster drug and the poster child for the selective serotonin reuptake inhibitor (SSRI) class of antidepressants, which target the neurotransmitter serotonin.

“There was, of course, no demonstrable evidence showing that depressed patients had any imbalance, but Lilly ran with it,” Psychology Today noted. “Before long, psychiatrists and psychiatric patients alike came to identify with the idea that mental disorders are caused by chemical imbalances in the brain.”4

Zoloft (sertraline), another SSRI, was another major player in spreading and perpetuating the chemical balance theory, with their television ads going so far as to say, “While the causes are unknown, depression may be related to an imbalance of natural chemicals between nerve cells in the brain. Prescription Zoloft works to correct this imbalance.”5

It’s important to note that in the time since Prozac flooded the market, depression still remains poorly treated, despite a plethora of new antidepressant options to choose from. SSRIs work by preventing the reuptake (movement back into the nerve endings) of the neurotransmitter serotonin.

This makes more serotonin available for use in your brain, which is thought to improve your mood since low serotonin levels are said to lead to depression. Yet, as written in the Handbook of Experimental Pharmacology, it’s a largely disproven theory:6

“Antidepressants are supposed to work by fixing a chemical imbalance, specifically, a lack of serotonin in the brain. Indeed their supposed effectiveness is the primary evidence for the chemical imbalance theory. But analyses of the published data and the unpublished data that were hidden by the drug companies reveal that most (if not all) of the benefits are due to the placebo effect.

Some antidepressants increase serotonin levels, some decrease it, and some have no effect at all on serotonin … The serotonin theory is as close to any theory in the history of science having been proved wrong.”

Harvard: Depression ‘More Complex’ Than a Brain Chemical Imbalance

It’s quite possible that people who are depressed may have an imbalance of certain chemicals in their brain. But to speculate that that imbalance is the cause of their symptoms is overly simplistic. For instance, it’s known that psychological stress can cause biological changes in the brain, including a reduction in the size of the hippocampus, which is used for learning and memory.7 In turn, it’s known that some people with depression have a smaller-than-average hippocampus.8

“Evidence of biological changes correlating with environmental stressors is vastly different from evidence that mental illnesses are ‘caused’ by biological deficits,” scientists wrote in a 2008 report on the chemical imbalance theory,9 and this is an important point. Even Harvard Medical School acknowledges that while brain chemicals may play a role in your mood, it is not accurate to suggest that one being too high or too low is at the root of depression. They state:10

“Research suggests that depression doesn’t spring from simply having too much or too little of certain brain chemicals. Rather, there are many possible causes of depression, including faulty mood regulation by the brain, genetic vulnerability, stressful life events, medications, and medical problems.

It’s believed that several of these forces interact to bring on depression … There are millions, even billions, of chemical reactions that make up the dynamic system that is responsible for your mood, perceptions, and how you experience life.”

One theory posits, for instance, that stress could be a major contributor to depression because it suppresses the production of new neurons in the hippocampus. In order to feel better, people with depression may need to increase neurogenesis (the generation of new neurons), which takes weeks.

This would explain why many people who take antidepressants don’t notice any improvement for several weeks.11 If the action was really on neurotransmitters, the patient should feel better right away when levels increase. Instead, triggering the growth of neurons could be the secret, which is a process that can be triggered naturally via exercise.

Believing Depression Is Caused by Chemical Imbalance Worsens Outcomes

Aside from the serious implications of prescribing drugs under a false premise, the chemical balance theory is also dangerous in that it takes away ownership from the patient. If a person feels a chemical imbalance in their brain is to blame for their depression, they may believe taking medications is the only option to feel better. According to Todd Kashdan, professor of psychology at George Mason University in Virginia, upon “buying into a biomedical explanation for their depression:”12

“They become pessimistic that recovery is possible. They become less confident that they can manage and regulate negative moods that arise (and they always do). The notion that depression is their brain’s fault does not lessen the stigma or self-blame one bit.

And they no longer believe that psychotherapy is a credible or useful strategy for treating their depression and instead, are ready to be dispensed a pill cure. Essentially, they become less flexible in their options for treating depression and less confident that they will escape its clutches.”

Indeed, a 2014 study published in Behavior Research and Therapy revealed just that — attributing depressive symptoms to a chemical imbalance made people more pessimistic about their prognosis and led them to believe that drugs would be more effective than psychotherapy.13 At the same time, they still felt the same amount of self-blame. It’s important to note that –

feeling depressed is not anyone’s fault, nor should they feel blamed for or ashamed of their feelings.

However, pinning its cause on a chemical imbalance is likely to worsen outcomes rather than improve them. It’s a vicious cycle as well, because the chemical imbalance theory makes people assume that medications are the best course of treatment. But here again research has shown that people with depression who are treated with medication have poorer long-term outcomes compared to those who are not.14

Antidepressants Work No Better Than Placebo

Nearly 7 percent of U.S adults suffered from a depressive episode in the past year15 while, worldwide, 350 million people suffer from depression, making it a leading cause of disability.16 Despite this, only about one-third of Americans with depression get treated,17 which puts the remaining two-thirds left untreated at increased risk of suicide and with a lower quality of life.

That said, the antidepressant drugs that are supposed to work by fixing a chemical imbalance in the brain are largely ineffective, which means that even when some people attempt to get treatment, they’re left suffering. Studies have repeatedly shown antidepressants work no better than placebo for mild to moderate depression.18

Irving Kirsch, associate director of the Program in Placebo Studies at Harvard Medical School, has conducted meta-analyses of antidepressants in comparison to placebo and has concluded that there’s virtually no difference in their effectiveness, noting, “The difference is so small, it’s not of any clinical importance.”19 What is different, however, is the potential for side effects, which is far greater among antidepressants than placebos.

For instance, antidepressant users have an increased risk of developing Type 2 diabetes,20 even after adjusting for other risk factors, like body mass index (BMI).21 Antidepressant use has also been linked to thicker arteries, which could contribute to the risk of heart disease and stroke.

The results of a study of 513 twin veterans, presented at the American College of Cardiology meeting in New Orleans in 2011, found that antidepressant use resulted in greater carotid intima-media thickness (the lining of the main arteries in your neck that feed blood to your brain).22

This was true both for SSRIs and antidepressants that affect other brain chemicals. Further, the use of antidepressants is also associated with an increased risk of heart attack, specifically for users of tricyclic antidepressants, who have a 36 percent increased risk of heart attack.23

Meanwhile, the drugs are also linked to dementia, with researchers noting “treatment with SSRIs, MAOIs, heterocyclic antidepressants, and other antidepressants was associated with an increased risk of dementia,” and as the dose increased, so too did the risk.24

The drugs are also known to deplete various nutrients from your body, including coenzyme Q10 and vitamin B12 — in the case of tricyclic antidepressants — which are needed for proper mitochondrial function. SSRIs may deplete iodine and folate,25 and you’re even more likely to relapse if you’re treated with antidepressants than if you’re treated via other methods, including placebo or exercise.26,27Given the lack of effectiveness and the risks involved, Kirsch and colleagues concluded:28

“When different treatments are equally effective, choice should be based on risk and harm, and of all of these treatments, antidepressant drugs are the riskiest and most harmful. If they are to be used at all, it should be as a last resort, when depression is extremely severe and all other treatment alternatives have been tried and failed.”

Alternative Treatments for Depression

If the chemical imbalance theory is false, the case for choosing antidepressants as a first-line treatment for depression is incredibly weak. Fortunately, there are many alternatives to drugs for treating depression, including nutritional interventions, light therapy, exercise and more. If you’re struggling with depression, you needn’t suffer in silence. Seek help, from a counselor, a holistic psychiatrist or another natural health practitioner to start the journey toward healing.

That said, if you are feeling desperate or have any thoughts of suicide, please call the National Suicide Prevention Lifeline, a toll-free number: 1-800-273-TALK (8255), call 911, or simply go to your nearest hospital emergency department. You cannot make long-term plans for lifestyle changes when you are in the middle of a crisis. If you’re in a place where you feel you can begin to make positive changes, here are some of the top alternative treatments for depression to consider:

Exercise. Those who didn’t exercise were 44 percent more likely to become depressed compared to those who did so for at least one to two hours a week.29
Light therapy. Light therapy alone and placebo were both more effective than Prozac for the treatment of moderate to severe depression in an eight-week-long study.30
Omega-3 fats, which have been shown to lead to improvements in major depressive disorder.31 Make sure you’re getting enough omega-3s in your diet, either from wild Alaskan salmon, sardines, herring, mackerel and anchovies, or a high-quality animal-based omega-3 supplement.
Optimize your vitamin D levels, another factor linked to depression32
Magnesium. Magnesium supplements led to improvements in mild-to-moderate depression in adults, with beneficial effects occurring within two weeks of treatment.33
B vitamins. Low levels of B vitamins are common in patients with depression, while vitamin B supplements have been shown to improve symptoms.34
Mindfulness meditation35 and the Emotional Freedom Techniques (EFT). In a study of 30 moderately to severely depressed college students, the depressed students were given four 90-minute EFT sessions. Students who received EFT showed significantly less depression than the control group when evaluated three weeks later.36
Cognitive behavioral therapy, which works as well as antidepressants and may reduce your risk of relapse even after it’s stopped.37
Limit sugar. Men consuming more than 67 grams of sugar per day were 23 percent more likely to develop anxiety or depression over the course of five years than those whose sugar consumption was less than 40 grams per day.38
 _____________
**Comment**
A very helpful article for Lyme/MSIDS patients as we nearly always at some point suffer with depression.  
Some of you might be on antidepressants and this article has left you floundering.  Take a deep breath and decide you are going to take this information, study it, and talk to your practitioner before deciding upon any course of action.
Please seek help if you need it.  If possible find at least a “Lyme friendly” practitioner as the last thing you need is to be abused by another health professional when you are at your lowest.  Hopefully the word is getting out on the psychiatric manifestations of Lyme/MSIDS.  Start by going to your local Lyme support group and ask around for a good, reputable, understanding, and hopefully experienced practitioner.
For those of you in the trenches, I want to encourage you that this too shall pass.  I found my depression while in treatment for Lyme/MSIDS was directly aligned to how I felt physically.  The worse I felt physically the worse I felt emotionally.  I’ve said this before, but the best advice I ever received from someone who made it to the other side of health was, “Don’t get depressed about feeling depressed.”  Give yourself permission to feel lousy.  Your body is in a battle of epic proportions – you’re bound to feel like crap.
Treating for Lyme/MSIDS is unlike most other treatments that have linear improvement.  You are going to have starts and stops, good days and bad, and down right horribly miserable days.  You are going to have days where you beg to have it all end.
Persevere.  Don’t quit.  Better days are coming.  Do not give in to the moment.  
When I got really low I read books where others had it worse than me.  I watched cartoons, anything to get my mind off the pain and hopelessness.  For a long time I didn’t read anything about treatment outcomes, because frankly I couldn’t have handled the truth.  That’s OK.  You don’t need to know how the watch works when you are at your lowest.  There will come a day when you can handle all that information, but for today, take a nice bath.  Listen to your favorite music.  Read your favorite books.  Call an understanding friend.  Whatever it takes to get through this day, minute, and second.

There has been researching showing that probiotics help with depression as well:  http://www.spring.org.uk/2017/03/probiotics-depression.phpThe scientists found that when mice in the study were put under stress, they developed a reduction in Lactobacillus through the metabolite kynurenine, which is somehow involved with inflammation and was linked to depressed behavior.  Feeding them Lactobacillus almost completely stopped their depressive behaviors.  

All Lyme/MSIDS patients should be on good pro and prebiotics and doing all they can to lower inflammation.  Read here about the microbiome and MSM’s ability to lower inflammation & help heal the gut:  https://madisonarealymesupportgroup.com/2018/01/03/the-invisible-universe-of-the-human-microbiome-msm/

If the depression hangs on, seek help.  Also, if you need to take medication short-term – so be it.  No judgement here.  We are all different and take different things to make it to the other side of health.  But, I encourage you to get to the bottom of things rather than mask it with a pill.  
My experience has shown me that treatment for pathogens is just one prong of our healing journey, and while important, isn’t the end-all.  We must detox.  We must address diet and sleep.  We must learn everything we can about our personal imbalances and weaknesses and seriously address them.  We must address our mental health and all that entails – from lowering our stress to ditching harmful relationships.
Thank you to all the mental health practitioners and patients out there writing about your experiences with Lyme/MSIDS psychiatric issues.  We need to hear what you have to say!

Scary Side of Childhood Strep

https://www.washingtonpost.com/news/parenting/wp/2018/01/03/out-of-the-blue-the-scary-side-of-childhood-strep/?utm_term=.9c0483c2a253  by Deanne Haines Jan. 2018

I almost didn’t take my 7-year-old son, Luke, to the doctor right away when he experienced a sudden onset of excessive blinking. He had just started a new school and was having trouble adjusting so I figured the stress of trying to fit in was producing this psychological habit.

I had no idea at the time his tics were the result of a strep infection I never even knew he had. Thankfully, our pediatrician made the correct diagnosis and treatment began immediately. My son was one of the lucky ones.

Kristin Kutz’s daughter, Abigail, came home from her first day of third grade excited and eager to go back. “Best day ever!” she exclaimed. The next day — out of the blue — she cried uncontrollably, insisting she couldn’t go back to school even though she didn’t know why. This dramatic, uncharacteristic behavior kept up for weeks. A nurse eventually found strep in her system.

Extroverted and happy is how Tammy Dalsin described her 10-year-old daughter, Ella, until one November evening — just one week after completing antibiotic treatment for strep. That night — forever burned into Dalsin’s memory — is when Ella abruptly developed strange, obsessive compulsive disorder- or OCD-like behavior, resulting in a four-month nightmare of frustrating doctor visits until finally receiving a diagnosis of PANDAS.

PANDAS stands for Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal Infections. PANDAS occurs when a strep infection sets off a misdirected immune response in the child’s brain. Instead of fighting the infection, the immune system attacks the basal ganglia — a part of the brain that controls emotions and movement. This can result in extreme obsessive-compulsive characteristics, tics and other debilitating behavior.

“If it comes out of the blue and you’re struck by how odd it is, that’s a sign it may be PANDAS,” says Susan Swedo, chief of the Pediatrics & Developmental Neuropsychiatry Branch at the National Institute of Mental Health. Swedo and her team first identified PANDAS in 1998.

“Parents tell us PANDAS changes their child so dramatically it’s almost like their child is gone, and somebody else took her place,” Swedo says.

That’s exactly how Dalsin felt in 2011 when Ella all of a sudden couldn’t get herself to walk through a doorway.

“We were going from the garage into the house, and she kept going up and down the steps. She couldn’t make herself go in. She grabbed her hair with both hands and was screaming and crying. She was panicking because she didn’t know what was happening to her,” Dalsin said.

Ella’s symptoms got progressively worse. Her mind reeled with obsessive-compulsive thoughts, such as needing to touch the wall 10 times, otherwise something bad would happen. Ella was wrought with anxiety and could barely function. She missed weeks of school and had to quit hockey — a sport she loved to play. A visit to the pediatrician provided no answers. It wasn’t until the Dalsins did their own extensive Internet research that they discovered a probable cause.

“We read the PANDAS description, and it sounded exactly like her. We were convinced,”  Tammy Dalsin said.

Unfortunately, PANDAS isn’t easily diagnosed.

“It’s harder to recognize,” says Kiki Chang, director of PANS Psychiatry Research at Stanford University Medical Center, “because mild cases get missed and some of the major cases, too, because they get misdiagnosed as primary psychiatric illness.”

Many doctors are still unfamiliar with PANDAS, a relatively new disorder. Others refuse to believe it even exists, not accepting that an infection could be the cause of a behavioral disorder.

That explains the Dalsins’ hellish few months of unproductive doctor visits, including to a neurologist, psychologist and psychiatrist, before a different child psychiatrist confirmed their suspicion of PANDAS. Finally, Ella could start her long road to recovery.

Nine-year-old Abigail’s PANDAS also went undiagnosed by the first physician she saw — a psychiatrist. After the initial visit, he was ready to refer Abigail to a special school for children with severe mental disorders. Abigail’s parents sought a second opinion. This time a registered nurse ran blood tests and found strep in Abigail’s body, recognizing PANDAS was probably the cause of her abrupt onset of crying outbursts and refusal to go to school.

Abigail did return to school more than a month later, but she often ran out of the classroom to hide — one time hiding in a school kitchen cupboard where no one could find her for hours. Abigail’s handwriting skills decreased dramatically, and she started refusing to eat — two common PANDAS symptoms.

Experts say PANDAS affects 1 in 200 children and is “definitely present in every elementary school in the country,” Swedo said. She says it may go unnoticed, though, because children often try to hide their symptoms.

While not every child who gets strep develops PANDAS, family history of autoimmune illnesses and anxiety increase the risk.

PANDAS treatment consists of antibiotics to fight the infection along with cognitive behavioral therapy and/or antidepressants. The longer the child goes with untreated PANDAS, however, the more serious the symptoms and more intense treatment is needed.

“We’re working with Departments of Health in several states to increase awareness by both parents and clinicians. If we can help pediatricians recognize and treat PANDAS in its early stages, it can make a huge difference in that child’s life,” Swedo says.

Take it from me. My son was in the pediatrician’s office no more than 10 minutes when the term PANDAS was mentioned. The immediate antibiotics and simple behavioral therapy were just a blip in the road for my son — who now at age 13 barely remembers the experience.

It’s a very different story for Ella and Abigail, whose PANDAS was not caught until much later. After months of intense therapy, Ella was put on long-term antibiotics and continues to take antidepressants six years later. Diagnosed in October 2016, Abigail still suffers relapses and continues working with health professionals to completely eradicate her symptoms. Her outbursts have decreased, and she’s beginning to eat normally.

Every little bit of progress brings hope to her family that there is life after PANDAS.

Deanne Haines is a freelance writer and mother of three from Wisconsin.

Follow On Parenting on Facebook for more essays, news and updates. You can sign up here for our weekly newsletter. Join our discussion group here to talk about parenting and balancing a career.

____________

**Comment**

A highly respected LLMD here in Wisconsin has found that 80% of his PANS kids also have Lyme/MSIDS (borrelia and other coinfections).  There’s much that is still unknown about this life-changing illness but tick borne illness (TBI’s) can definitely cause or exacerbate PANDAS/PANS.

The take home: do your own research, ask questions, and don’t allow egotistical medical professionals to patronize you by telling you that you or your child are making it all up. Call them to the carpet. If they refuse to help, go elsewhere, to someone who will listen to you and believe you.

For more:  https://madisonarealymesupportgroup.com/2017/06/30/child-with-lymemsidspans-told-by-doctors-she-made-it-all-up/

https://madisonarealymesupportgroup.com/2017/10/01/panspandas-steroids-autoimmune-disease-lymemsids-the-need-for-medical-collaboration/

https://madisonarealymesupportgroup.com/2017/12/01/guidelines-for-treating-pans-its-real/

https://madisonarealymesupportgroup.com/2017/10/08/misdiagnosed-how-children-with-treatable-medical-issues-are-mistakenly-labeled-as-mentally-ill/

https://madisonarealymesupportgroup.com/2017/10/09/today-is-panspandas-awareness-day/

Diagnosis and Management of Lyme Neuroborreliosis

https://www.ncbi.nlm.nih.gov/m/pubmed/29278020/

Diagnosis and management of Lyme neuroborreliosis.

Halperin JJ. Expert Rev Anti Infect Ther. 2018.

Abstract

The nervous system is involved in 10-15% of patients infected with B. burgdorferi, B. afzelii and B. garinii. This review will address widespread misconceptions about the clinical phenomenology, diagnostic approach and response to treatment of neuroborreliosis. Areas covered: Improvements in diagnostic testing have allowed better definition of the clinical spectrum of neuroborreliosis, with lymphocytic meningitis and uni- or multifocal inflammation of peripheral/cranial nerves predominating. Despite widespread concern that post-treatment cognitive/behavioral symptoms might be attributable to persisting infection or aberrant inflammation within the central nervous system a large body of evidence indicates this is extremely improbable. Importantly, recent studies show most neuroborreliosis can be treated with fairly brief courses of oral antibiotics. All high-level evidence confirms that prolonged courses of antibiotics carry harm with no commensurate benefit. Expert commentary: Lyme disease in the US, and corresponding disorders in Europe, are well defined neuro-infectious diseases that are highly responsive to antibiotic therapy. Although the nervous system is slow to recover after insults (e.g. persistent facial weakness after appropriately treated facial nerve palsy) there is no evidence that prolonged post-treatment neurocognitive symptoms are related to nervous system infection – either as a triggering event or as a cause of ongoing symptoms.

 _____________

**Comment**

While I would love to read this in its entirety for amusement, I refuse to pay $1 let alone $90 for 24 hour access.

Just from the abstract it is evident that it is another great example of why a medical condition never makes forward progress.  “Experts” like Halperin refuse to rethink the paradigm.

  • This article focuses only on borrelia, a formidable foe alone, an absolute shape-shifting beast on steroids when coupled with Babesia, Bartonella, Anaplasma, and other critters.  The one disease, one drug paradigm needs to go straight into the garbage can, and until this happens we are doomed.
  • The 10-15% patient statistic with nervous system involvement also needs to go straight into the can.  Nobody has a clue on numbers on any of this.  If the CDC goes from 30,000 new cases to over 300,000 new cases a year, I think we need to wave the white flag and admit our ignorance.
  • Without reading the entire faulty article, I have a deep rooted suspicion that this “review” is based on other deeply flawed articles and studies from the past made by the Cabal.  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/ and https://madisonarealymesupportgroup.com/2017/12/06/ahern-flawed-lyme-policies-diagnostics-and-treatment/
  • Diagnostic testing has not improved with the CDC even stating numerous tests might be needed:  https://madisonarealymesupportgroup.com/2017/07/01/good-morning-america-cdc-advises-multiple-lyme-tests-due-to-false-negative-results/
  • A recent study states that treating prophylactically if TBI’s are suspected is warranted: https://madisonarealymesupportgroup.com/2017/07/12/start-treatment-if-tbis-are-suspected/.  Also see:  https://www.lymedisease.org/lyme-basics/lyme-disease/diagnosis/, and https://madisonarealymesupportgroup.com/2017/09/02/microbiologist-holly-ahern-on-lyme-disease-how-did-we-get-here/.
  • The definition of the clinical spectrum of neuroborreliosis is not better.  While it is true that more is being reported on, there is absolutely no consensus on any sort of definition.
  • The persisting infection/aberrant inflammation issue is not over just because Halperin reviews old Cabal manuscripts and claims there is a “wide body of evidence.”  As they say, Garbage in, garbage out.
  • Brief courses of antibiotics do work for some people, typically acute cases; however, there is much to indicate that many relapse and continue to have symptoms.  To say otherwise indicates bias of the highest sort.
  • His usage of “high-level evidence” also indicates an extreme personal bias indicating that the rest of us poor fools have low-level evidence.  Please, I know a slam when I hear one.  Nobody in Lyme-land is arguing that antibiotics do not have risks.  Many if not most treatments have risks, including drinking water; however, as with any disease state, the doctor and patient must discuss and weigh the risk/benefit ratio for sure.  An IDSA Founder, Dr. Waisbren, successfully used high powered IV antibiotics and wrote a book on 51 tough cases.  All improved.  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/  Again, there are so few studies looking at long-term antibiotic benefit on Lyme/MSIDS that this statement is premature and misleading.  I work with people on a daily basis who state they wouldn’t be alive today without the very treatment he is slamming, and trust me, we would all love an effective treatment with fewer risks!  
  • The “expert commentary” is only expert in my opinion if it takes into account numerous physicians who have actually treated complicated Lyme/MSIDS cases over decades of time, who are open-minded, are willing to change, and are continually studying, listening and learning from others.  Halperin fails on many accounts.  Keep reading below to see why.
  • This review is nothing more than a regurgitation of ancient, unscientific, and biased opinion.

In this interview  Halperin repeats the common myth that Lyme takes 24-49 hours or more to be transmitted  https://madisonarealymesupportgroup.com/2017/04/14/transmission-time-for-lymemsids-infection/, that it is primarily an Eastern problem  http://steveclarknd.com/wp-content/uploads/2013/11/The-Confounding-Debate-Over-Lyme-Disease-in-the-South-DiscoverMagazine.com_.pdf (go to page 6 and read about Speilman’s maps which were faulty but have ruled like the Iron Curtain), and that you typically have flu-like symptoms https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/ (My initial symptoms were gynecological).  He treats everyone with 2-4 weeks of antibiotics.

A quick search reveals Halperin commonly serves as an “expert” witness in medical malpractice cases defending physicians accused of failing to diagnose Lyme.  

Here’s a lengthy article Article Kicking and LLMDs Personal View coauthored by Halperin which states,

“Advocacy for LD has become an increasingly important part of an anti science movement that denies both the viral cause of AIDS and the benefits of vaccines and that supports unproven (sometimes dangerous) alternative medical treatments.”  

Oh, and somehow patients, advocates, and their doctors pose a threat to public health.

 Here’s a few telling Halperin quotes:
QUOTE-  “When physicians who diagnose chronic Lyme disease obtain laboratory tests to provide support for their diagnoses, they often rely heavily on “Lyme specialty laboratories.” Such laboratories may perform unvalidated in-house tests that are not regulated by the Food and Drug Administration, or they may perform standard serologic tests interpreted with the use of criteria that are not evidence-based.1” Source
 
QUOTE-  “Antibiotic therapy can cause considerable harm to patients treated for chronic Lyme disease or post–Lyme disease symptoms.” Source
 
QUOTE-  “Although anecdotal evidence and findings from uncontrolled studies have been used to provide support for long-term treatment of chronic Lyme disease,18-20 a response to treatment alone is neither a reliable indicator that the diagnosis is accurate nor proof of an antimicrobial effect of treatment.” Source
 
QUOTE-  “It is highly unlikely that post–Lyme disease syndrome is a consequence of occult infection of the central nervous system.” Source

Lyme Disease Laid Bare

https://www.nature.com/articles/d41586-017-08442-8 Dec. 2017

Lyme disease laid bare

James G. Logan hails a study of the controversial tick-borne condition.
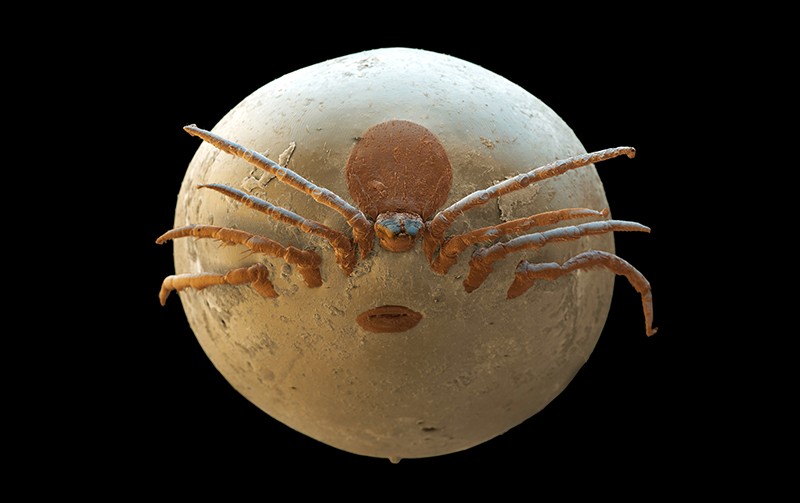
Blood filled sheep tick, SEM.

Ixodes ticks spread Lyme disease.Credit: Eye of Science/SPL.

Conquering Lyme Disease: Science Bridges the Great Divide Brian A. Fallon & Jennifer Sotsky Columbia University Press: 2017.

It occurs in more than 80 countries and is the most commonly reported vector-borne disease in the Northern Hemisphere. In the United States alone, it spawns 300,000 new cases each year. Yet Lyme disease — caused by species of Borrelia bacteria carried by ticks of the Ixodesgenus — remains one of the most poorly understood infections. It has divided researchers, clinicians and patients, and triggered intense public suspicion and confusion.

So what is science’s role in turning the corner on what some have labelled a “public health failure”? Physicians Brian Fallon and Jennifer Sotsky tackle this question in their insightful study Conquering Lyme Disease, in which they journey beyond the history, biology and symptoms of the illness. Their greatest accomplishment, by far, is delivering multiple viewpoints with minimal bias and great sensitivity: the clinician’s, the researcher’s and, particularly, the patient’s.

Although recent headlines make Lyme disease seem new, probably the first recorded case was in 1909: the Swedish dermatologist Arvid Afzelius associated a patient’s expanding rash (later named erythema migrans) with a tick bite. In the 1970s, a link was made to bacteria by rheumatologist Allen Steere; in 1981, the biologist Willy Burgdorfer discovered that the disease was caused by a type of bacterium called a spirochaete. The species complex was named Borrelia burgdorferi in his honour. But it was not until the 1990s that US cases were properly reported, through a surveillance system set up by the Centers for Disease Control and Prevention in Atlanta, Georgia.

Since that decade, the global incidence has increased and reporting has improved, as Fallon and Sotsky describe; in the United States alone, known cases have tripled since 1992. There is currently no human vaccine, and research on the disease has struggled to keep up.

The many presentations of an illness known as the “great imitator”, and its inherent complexities, are why medical communities have often failed to find common ground on diagnosis and treatment, as the authors explore. The manifestations range from no symptoms, or mild influenza-like ones, to severe complications such as inflammation in joints or the brain and persistent neurological problems.

One of the reasons Lyme is difficult to diagnose is that some non-infectious conditions, including fibromyalgia and Alzheimer’s disease, present with similar symptoms. The situation is further complicated because Ixodes ticks transmit a host of other pathogens, such as Rickettsia, other bacteria, viruses and protozoa, leading to diseases including typhus, relapsing fever, babesiosis and meningoencephalitis. Misdiagnosis is thus all too common.

Treatment is also far from straightforward. Although antibiotics can clear infection in some cases, Fallon and Sotsky describe how genetic differences in Borrelia bacteria found on different continents make treatment difficult. There are, for instance, three different species in the complex in Europe. The authors note that each can cause different symptoms in people with Lyme disease who develop neurological complications. So a treatment that works for one species of the bacterium may not work for another.

And spirochaetes can remain in the body even after courses of antibiotics (E. Hodzic et alAntimicrob. Agents Chemother. 52, 1728–1736; 2008). Fallon and Sotsky hypothesize that they may “hide” inside human cells, for instance. A big question is whether the spirochaetes that hang on in this way can replicate and cause disease.

Whatever the mechanism, proof of the existence of persistent symptoms will pave the way for better diagnostics, treatment and care. Some patients have spent years trying to convince medical doctors that their symptoms remain after treatment. Fallon and Sotsky strikingly convey these people’s difficulties and frustrations. Clinicians, for instance, might fail to ask the right questions. People with chronic Lyme disease can feel abandoned, and even suicidal. That has led to protests and court hearings, notably in the United States. But these people, the authors argue, have played a significant part in moving understanding beyond conventional thinking, and ultimately driving research forward. Clinicians are now beginning to acknowledge both the complexity of Lyme disease and patients’ needs. Fallon and Sotsky end on a firmly positive note, reviewing avenues for new research across many disciplines, from diagnostics to vaccines and treatments. What’s particularly pressing is the need for a definitive test to detect the spirochaetes that cause this devastating disease.

 ______________

Duke Studying Alternatives to Antibiotics for Lyme

https://corporate.dukehealth.org/news-listing/lyme-study-uses-drug-discovery-methods-have-fueled-cancer-breakthroughs

Lyme Study Uses Drug Discovery Methods That Have Fueled Cancer Breakthroughs

Labs at Duke and other academic centers collaborate to identify alternatives to antibiotics

Published December 13, 2017 

Ticks can spread the bacterium that causes Lyme disease

DURHAM, N.C. – Antibiotics are currently the only treatments available for Lyme disease and other tick-borne illnesses, but researchers at Duke Health are working to expand the medical toolkit by identifying vulnerable areas of disease-causing bacteria that could lead to innovative therapies.

The research project, which recently received a $3.8 million grant from the Steven & Alexandra Cohen Foundation, relies on drug discovery methods that have proven successful in identifying treatments for cancer and viral diseases.

“Our goal is to find alternatives to antibiotics to treat Lyme disease, which is caused by the Borrelia burgdorferi bacterium, and illnesses that arise from the Bartonella pathogen,” said Neil Spector, M.D., the Sandra Coates Associate Professor Breast Cancer Research at Duke Cancer Institute and the study’s co-principal investigator.

“We’re hoping to move from isolating targets to identifying potential drugs to testing in animal models within three years – so a very aggressive timeline,” said Spector, who was a Lyme patient himself and nearly died from complications of disease. “Our goal is to identify drugs that will target the Achilles’ heel of these pathogens while sparing the normal gut microbiome.”

Spector and co-principal investigator Timothy Haystead, Ph.D., professor in the department of Pharmacology and Cancer Biology at Duke, are collaborating with scientists at Johns Hopkins School of Medicine and Tulane Medical Center to perform distinct functions of the study.

The Duke team will use technology Haystead’s lab has pioneered for cancer drug discovery, which will identify protein targets for the development of a completely new class of molecularly targeted therapies for Borrelia burgdorferi and Bartonella.

The team at Duke will then screen thousands of new compounds to identify those that target the desired proteins. The new compounds identified at Duke will then be tested at Johns Hopkins in a high-throughput assay to evaluate their effects on the viability of Borrelia burgdorferi and Bartonella.

The most promising drug candidates will then be sent to Tulane, where researchers will determine their efficacy in animal models of Bartonella illnesses and Lyme diseases, including in primates.

The Spector and Haystead labs have already identified more than 20 bacterial proteins that represent attractive targets for drug development. The protein targets are selected in part for their specificity to Borrelia burgdorferi, which would reduce the risk of adverse side effects such as the destruction of normal, healthy gut flora.

Duke researchers have begun screening a library of thousands of compounds looking for potential drugs that target a specific Borrelia burgdorferi protein that plays a key role in promoting the survival of the bacteria.

The research project represents a new exploration for Spector, a leading cancer researcher who was instrumental in the development of lapatinib, the first oral inhibitor of the HER2/neu cancer promoting protein approved by the FDA for the treatment of a subset of breast cancers. Spector’s interest in Lyme disease research stems from his personal experience with the infection, which he battled for years without a clear diagnosis. After suffering near-fatal heart failure, he underwent a heart transplant in 2009.

Spector said many features of cancer are also true of Lyme. For example, how and where tumors spread is not random. Similarly, Lyme affects different people in different ways, and Spector asserts that there are likely biological factors at play.

“I think there’s a way to capitalize on the lessons we’ve learned in cancer biology and basic research over the past 20 years and apply them to Lyme research,” Spector said. “We don’t have to reinvent the wheel.”

Contact

______________