Archive for the ‘research’ Category

National Committee Creates New Acronym for Lyme: IACI

Lyme IACI, pronounced “Lyme eye-ACK-ee” is the latest fantasy dreamt up by the National Academies of Sciences, Engineering, and Medicine – the congressionally chartered organization that serves as the ‘collective’ scientific national academy of the U.S., which proudly deploys the climate, health, and equity propaganda pushed by globalists.  The sponsors of the organization are none other than:

AstraZeneca
Burroughs Wellcome Fund
Grantham Foundation
JPB Foundation​
McCall MacBain Foundation
Rockefeller Foundation

Are you getting this yet?

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/

Inquiry to the Deputy Director of the Vector-Borne Diseases Division at the CDC

Carl Tuttle
Hudson, NH, United States
Jul 31, 2024

Notice to everyone who has signed this petition:

The following so-called “National Committee” has been established turning persistent Lyme symptoms into a new acronym: Lyme Infection-Associated Chronic Illness (Lyme IACI)

Medscape

‘Doesn’t Fit Anything I Trained for’: National Committee Examines Treatment for Chronic Illness Following Lyme Disease

https://www.medscape.com/viewarticle/doesnt-fit-anything-i-trained-national-committee-examines-2024a1000dru

So now, Chronic Lyme will be swept under the rug for more decades to come despite the mountain of evidence that we have been dealing with an antibiotic resistant/tolerant superbug!

I don’t think this committee is looking to solve (expose) the chronic Lyme epidemic …. it seems more likely this is an opportunity to exploit the chronically infected with money making pharmaceuticals to treat the symptoms of an antibiotic resistant/tolerant superbug.

“Lyme IACI” conveniently sweeps chronic Lyme under the rug.

Please see the email below addressed to Dr. Ben Beard of the CDC with carbon copy to all members of this committee. I ask that everyone demand a response from Beard. You can copy all email addresses below and send a private email or post a comment to the NASEM Committee’s website: https://www8.nationalacademies.org/pa/feedback.aspx?type=project&key=HMD-HSP-23-07

Inquiry to Ben Beard:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “cbb0@cdc.gov” <cbb0@cdc.gov>
Cc: “jjohnson@genevausa.org” <jjohnson@genevausa.org>, “theerhisamariee@gmail.com” <theerhisamariee@gmail.com>, “jaucott@jhmi.edu” <jaucott@jhmi.edu>, “cbb0@cdc.gov” <cbb0@cdc.gov>, “jraitt1@stanford.edu” <jraitt1@stanford.edu>, “dclauw@med.umich.edu” <dclauw@med.umich.edu>, “john.leong@tufts.edu” <john.leong@tufts.edu>, “avindra.nath@nih.gov” <avindra.nath@nih.gov>, “charles.chiu@ucsf.edu” <charles.chiu@ucsf.edu>, “elliot.cowan@partnersindiagnostics.com” <elliot.cowan@partnersindiagnostics.com>, “beth.jaworski@nih.hhs.gov” <beth.jaworski@nih.hhs.gov>, “roger@lundquist.org” <roger@lundquist.org>, “rachele.hendricks.sturrup@duke.edu” <rachele.hendricks.sturrup@duke.edu>, “info@lymebiobank.org” <info@lymebiobank.org>, “lorrainejohnson@outlook.com” <lorrainejohnson@outlook.com>, “wendyadams1@gmail.com” <wendyadams1@gmail.com>, “Leith.States@hhs.gov” <Leith.States@hhs.gov>, “tindall.matt@gmail.com” <tindall.matt@gmail.com>, “stacie.hudgens@clinoutsolutions.com” <stacie.hudgens@clinoutsolutions.com>, “raymond_dattwyler@nymc.edu” <raymond_dattwyler@nymc.edu>, “timothy.sellati@globallymealliance.org” <timothy.sellati@globallymealliance.org>, “nklimas@nova.edu” <nklimas@nova.edu>, “kester@genevausa.org” <kester@genevausa.org>, “nicole@nicolemalachowski.com” <nicole@nicolemalachowski.com>, “marcom@genevausa.org” <marcom@genevausa.org>, “stephen.gluckman@pennmedicine.upenn.edu” <stephen.gluckman@pennmedicine.upenn.edu>, “epocratesMedia@athenahealth.com” <epocratesMedia@athenahealth.com>, “epocrates@athenahealth.com” <epocrates@athenahealth.com>
Date: 07/31/2024 7:40 AM EDT
Subject: Inquiry to the Deputy Director of the Vector-Borne Diseases Division at the CDC

Charles B Beard
Deputy Division Director, Division of Vector-Borne Diseases
Centers for Disease Control and Prevention

Dear Dr. Beard,

In 1991 the Lyme disease organism, Borrelia burgdorferi, was grown from the cerebrospinal fluid of patient Vicki Logan at the Centers for Disease Control in Fort Collins, Colorado despite prior treatment with intravenous antibiotics. The patient died when the insurer refused additional IV antibiotics. I have attached a copy of Logan’s positive culture report for your review:

Logan CDC Fort Collins Positive CSF Culture Report (Personal Dropbox storage area)
https://www.dropbox.com/scl/fi/agca4ynn9ok2ykgw6484q/Logan-CDC-Fort-Collins-Positive-CSF-Culture-Report.JPG?rlkey=krhiecm1xdmqs6ubhvjxuzzeo&dl=0

In 1995 the following publication identified treatment-resistant neuroborreliosis:
 
European Neurology 1995
Seronegative Chronic Relapsing Neuroborreliosis
https://www.karger.com/Article/Abstract/117104

In 2018 all patients were culture positive even after multiple years on antibiotics so there was no relief from current antimicrobials. Some of these patients had taken as many as eleven different types of antibiotics. Barbour-Stoener-Kelly (BSK) medium was used and is the same complex medium used in the NIH funded Klempner antibiotic trials.

Persistent Borrelia Infection in Patients with Ongoing Symptoms of Lyme Disease
https://www.mdpi.com/2227-9032/6/2/33

A recently published autopsy study for a young Lyme patient who committed suicide identifies chronic Lyme disease in the patient’s brain which was responsible for his neurological symptoms.

Concurrent Infection of the Human Brain with Multiple Borrelia Species
Published in MDPI Nov. 29, 2023
https://www.mdpi.com/1422-0067/24/23/16906

Excerpt:

The diverse strategies used by spirochetes to avoid the host immune system and persist in the host include active immune suppression, induction of immune tolerance, phase and antigenic variation, intracellular seclusion, changing of morphological and physiological state in varying environments, formation of biofilms and persistent forms, and, importantly, incursion into immune-privileged sites such as the brain. Invasion of immune-privileged sites allows the spirochetes to not only escape from the host immune system but can also reduce the efficacy of antibiotic therapy. 

In addition, there are 700 peer reviewed publications identifying persistent infection and more evidence of seronegative disease.

Question:

As Deputy Director of the Vector-Borne Diseases Division at the CDC, why has all the evidence indicating Borrelia as an antibiotic resistant/tolerant superbug been ignored for decades?

A response to this inquiry is requested.

Please hit reply all when responding.

Carl Tuttle
Hudson, NH

_______________

**Comment**

When reading the Medscape article, please notice the following:

The committee will not make recommendations on specific approaches to diagnosis and treatment when it issues a report in early 2025 but will instead present “consensus findings” on treatment for chronic illness associated with Lyme disease, including recommendations for advancing treatment.

There have been only a few randomized controlled trials (RCTs) conducted on what the committee is calling Lyme Infection-Associated Chronic Illness (Lyme IACI) for now, and no National Institutes of Health (NIH)-funded RCTs in the past 20 years or so. It’s an area void of the US Food and Drug Administration-approved therapies, void of any consensus on the off-label use of medications, and without any current standard of care or proven mechanisms and pathophysiology, said John Aucott, MD, director of the Johns Hopkins Medicine Lyme Disease Clinical Research Center, Baltimore, one of the invited speakers at a public meeting held by the NASEM in Washington, DC, in July.”

The best way to look at this illness is not from the silos of infectious disease or the silos of rheumatology; you have to look across disciplines,” Aucott, also associate professor of medicine in the Division of Rheumatology, told the committee. “The story doesn’t fit anything I trained for in my infectious disease fellowship. Even today, I’d posit that PTLD is like an island — it’s still not connected to a lot of the mainstream of medicine.”

COVID showed the world the devastating impact of ‘consensus-based medicine,’ which a report has deemed ‘shocking and immortal.’ In this Communist-type paradigm doctors are told by bureaucrats how to treat, what they can use to treat, and what they can’t use to treat.  Anything outside the lines of this monolith simply aren’t allowed.  Doctors who dare to think for themselves are persecuted and ostracized – with the full weight of the government pressing down upon them –  often times losing their medical license.

This is the world Lyme literate doctors (LLMDs) have lived in for forty years.

The article also regurgitates that only 10-20% go on to suffer with persistent symptoms after treatment, when the actual percentages are approximately 60% as many are not diagnosed or treated until much later – often years later.

Lyme/MSIDS will never fit into RCTs because there are too many variables to fit into a nice four-cornered research box.  Many never test positive on the CDC-2-tiered testing, many never get an EM rash, numerous coinfections are involved, not to mention the fact there are multiple strains of borrelia that testing will not pick up, and symptoms are wildly variable.  No two patients look alike.

The Important Connection Between COVID Infection, Injection, and Bacteria

http://  Approx. 24 Min

Connection Between COVID & Bacteria

July 21, 2024

By Dr. McMillan

Discover the mind-blowing connection between COVID-19 and bacteria in this shocking video.

Learn about the surprising ways in which the virus can infect bacteria and gain valuable insights into this fascinating phenomenon. Petrillo, Mauro, et al. “Increase of SARS-CoV-2 RNA load in faecal samples prompts for rethinking of SARS-CoV-2 biology and COVID-19 epidemiology.” F1000Research 10 (2021). https://www.ncbi.nlm.nih.gov/pmc/arti…  From study:

Discussion

Our observations are compatible with a ‘bacteriophage-like’ behaviour of SARS-CoV-2, which, to our knowledge has not been observed or described before. These results are unexpected and hint towards a novel hypothesis on the biology of SARS-CoV-2 and on the COVID-19 epidemiology. The discovery of possible new modes of action of SARS-CoV-2 has far-reaching implications for the prevention and the treatment of the disease.

This 2021 study shows how COVID was being found in stool and that the microbiome could be involved.

Researchers then designed a test to cultivate the microbiome from infected people and looked at the viral load.  Since it is known that the virus first infects the mucosa in the upper airways, the first priority should be protecting the airways from infection.  Once it infects and breaks through the mucosal barrier and either gets into the bloodstream or the lymphatic system, it will then circulate through the whole body causing sickness.  It then heads to the intestines because there’s a lot of Ace2 receptors it can bind to and then infect cells in the small and large intestines to then replicate.

This paper highlights how COVID is being driven from the gut.

Previously, the researchers were finding abnormal bacterial toxins in the stool, blood, and urine from both infection and the gene therapy injection.

Research has shown that gut symptoms are associated with severe COVID.  Scientists and physicians have even formed a consensus for a list of non-prescription agents for COVID prophylaxis and symptom de-escalation of which the top four consist of vitamins C & D, zinc, and quercetin.

Dr. Sabine Hazan has shown that some of the good bacteria (bifido) get completely wiped out after infection and injection.  This bacteria is imperative to break down vegetable matter in the gut.  This decimation could then allow the overgrowth of the toxins that cause C. Diff and strep infections. She has since developed and patented treatment protocols combining vitamins and drugs that increase bifidobacteria including vitamin C, vitamin D, HCQ, and ivermectin.


Chronic Lyme Patient Treated Successfully With Low Dose Flagyl

https://danielcameronmd.com/chronic-lyme-treated-low-dose-flagyl/

CHRONIC LYME PATIENT TREATED SUCCESSFULLY WITH LOW DOSE FLAGYL

chronic-lyme-treatment

In their article “Patient with Chronic Lyme Disease and Recurrent Relapses, Maintained in Complete Remission by Low Doses of Metronidazole,” Lacout and colleagues describe a unique case of a Lyme disease patient, residing in France, whose chronic symptoms and relapses resolved with long-term, low dose Flagyl. [1]

A 55-year-old man developed numbness and burning in his legs, numbness in his hands, tinnitus, extreme weakness, intense pain, cramps at night and at rest, palpitations, paresthesias (pins and needles sensation), headaches, shortness of breath and orthostatic hypotension.

In addition, “Fatigue was intense and incapacitating, accompanied by anxiety, difficulty concentrating, mental fogginess and sleep disturbances,” the authors state.

He reported having been bitten by a tick years earlier but did not recall having a rash.

The man had been prescribed antibiotics for biliary pancreatitis but realized that his Lyme symptoms improved dramatically with the antibiotics.

Various tests including MRI, CT scan, x-rays and blood work were all normal.

A neurologist finally diagnosed the patient with diabetic neuropathy and prescribed analgesics and duloxetine. However, after several months of treatment, the pain intensified. Increased doses of duloxetine did not alleviate his symptoms.

An ENT doctor concluded that there was a link between tinnitus and the neuropathy.

He then developed urinary and erectile dysfunction, for which a urologist concluded that neurological damage was the cause of the symptoms, the authors state.

The man was eventually diagnosed by clinicians in France with polymorphic persistent syndrome after a possible tick bite (SPPT), a condition similar to post-treatment Lyme disease.

He was subsequently treated with multiple medications including: pyrantel, doxycycline, hydroxychloroquine (Plaquenil), ceftriaxone and metronidazole.

“At the end of this treatment, all signs had disappeared except for some residual intermittent leg pain.”

Unfortunately, the patient developed lung cancer and was treated with chemotherapy.

After he completed his cancer treatments, the man’s Lyme-related symptoms re-emerged and he developed relapses every 2 to 3 months.

Each relapse was treated successfully with antibiotics, typically doxycycline or azithromycin, sometimes combined with low doses of hydroxychloroquine.

“In view of these recurrent and seemingly inescapable recurrences, long-term treatment was initiated in the hope of maintaining a prolonged remission with the minimum antibiotic as possible: metronidazole 500 mg once a week,” the authors state.

In the present case, prolonged clinical remission was achieved with very low doses of Flagyl (metronidazole) 500 mg once a week.

For the past year, the patient has been in complete remission with no symptoms.

Authors Highlights:

  • “In our case, long-term, inexpensive treatment with minimal doses of antibiotics (500 mg metronidazole per week) was successfully introduced: the patient has not relapsed since then, leads a normal life and has even returned to work.”
  • “This case perfectly illustrates the existence of a chronic form of Lyme disease, as the patient relapsed numerous times (every two to three months for several years), and always went into remission after reintroducing antibiotics.”
References:
  1. Alexis Lacout, Pierre Yves Marcy, Christian Perronne. Patient with Chronic Lyme Disease and Recurrent Relapses, Maintained in Complete Remission by Low Doses of Metronidazole. Archives of Microbiology and Immunology. 8 (2024): 261-264.

_________________

**Comment**

Please note that one of the study authors, Christian Perronne, has been a long-standing advocate for chronic Lyme.  He’s one of the good guys, and it’s not shocking at all that he would be behind using treatment that saves a life rather than toe the party line, be lazy, and tell the patient they are crazy.

I had good results with metronidazole too but my LLMD switched me to tinidazole due to it typically causing less side effects.  It is one of the few antibiotics to address the cystic form of borrelia.  I always felt like a truck ran over me after pulsing it a few times a week throughout treatment (5 years).

Please see Dr. Eva Sapi’s work: https://www.dovepress.com/evaluation-of-in-vitro-antibiotic-susceptibility-of-different-morpholo-peer-reviewed-article-IDR  Metronidazole led to reduction of spirochetal structures by ~90% and round body forms by ~80%. Tigecycline and tinidazole treatment reduced both spirochetal and round body forms by ~80%–90%.

In terms of qualitative effects, only tinidazole reduced viable organisms by ~90%. Following treatment with the other antibiotics, viable organisms were detected in 70%–85% of the biofilm-like colonies.

I must also add that for those with significant neuro issues, antibiotics that cross the blood/brain barrier are imperative.  One that worked for me was minocycline:  https://madisonarealymesupportgroup.com/2017/06/04/minocycline-for-ms-and-much-more/

Go here for more:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

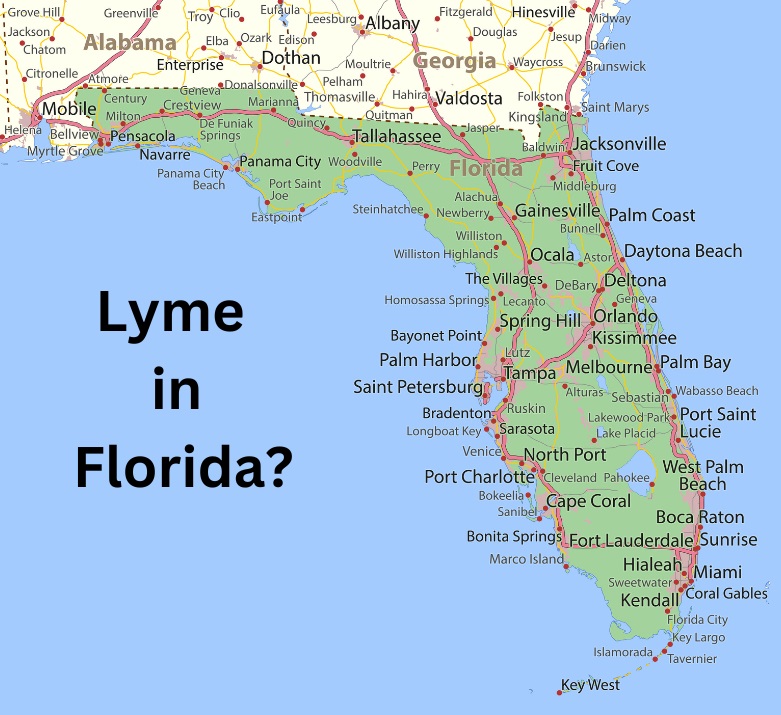
Florida Undercounts Lyme Disease & Downplays its Risk

https://www.lymedisease.org/florida-undercounts-lyme-disease/

Florida undercounts Lyme disease and downplays its risk

7/8/24

Melissa Bell, President of the Florida Lyme Disease Association, recently met with Florida Surgeon General Joseph A. Ladapo, MD, PhD, to discuss Lyme disease in their state. Their zoom call also included others from the Department of Health as well as Professor Kerry Clark from the University of North Florida.

Here is a follow-up email Melissa sent to the Dr. Ladapo, summarizing the call. This is a highly informative resource for anyone seeking to contact their local and state health officials. We thank Melissa for making this available to our readers.

The evidence is clear that Lyme disease is undercounted in Florida based on various data sources. The CDC surveillance counts place a heavy emphasis on “high incidence” states—which are primarily confined to the Northeast coast and upper Midwest United States. Doctors and patients are falsely told that there is “no Lyme in Florida” or that it is extremely rare.

Melissa Bell, President of Florida Lyme Disease Association.

As a result of this downplaying of the risk of Lyme and other tick-borne infections, people, especially parents, are less likely to take steps to prevent tick bites. Additionally, those infected are less likely to receive an early diagnosis. According to the CDC, “if left untreated, infection can spread to joints, the heart, and the nervous system.”

Due to poor awareness and training, doctors refuse to timely prescribe antibiotics for known tick bites even with symptoms and refuse to test for Lyme because they have been taught there is no Lyme in Florida. There is even less awareness regarding other tick-borne infections that are prevalent in the state, including Babesia, Ehrlichia, Anaplasma, and Bartonella.

Lyme and Bartonella infection can persist for years, despite antibiotic treatment (see studies linked above) and following:

New genetic group/species of Bartonella may be responsible for a portion of Lyme-like illness in Florida and other southern states. Standard lab tests for Bartonella will not likely identify these strains.

  • The CDC shows a 29.44% increase in reported cases in Florida comparing 2017-2019 data to 2022.
  • A 2021 CDC Study analyzing insurance data, revealed that in states the CDC considers to be “low incidence,” only 1 in 50 cases is counted, while in high incidence states 1 in 7 is counted. See also How much does the CDC undercount Lyme cases? It depends on where you live.
  • Standard lab tests for Lyme disease were developed to detect a single Borrelia strain present in the Northeast. Such lab tests fail to detect approximately half of actual cases pursuant to numerous peer reviewed studies. See Current Guidelines, Common Clinical Pitfalls, and Future Directions for Laboratory Diagnosis of Lyme Disease, United States; see also, Project Lyme. For unknown reasons, it appears as though the Florida Department of Health is not counting most CDC-positive Lyme cases. For example, in a July 2018 report (page 7), Quest Diagnostics showed an increase in Florida Lyme cases from 283 in 2015 to 501 in 2017, representing a 77% increase. In contrast, the CDC only reported 166 Florida Lyme cases in 2015 and 210 in 2017. Why are the CDC’s numbers for Florida so much lower than Quest, a single lab? In recent email correspondence, IGeneX has indicated a 48% positivity rate in Florida for 2023, which they consider high. There were 526 CDC-positive cases through IGeneX in 2023. Note that the IGeneX immunoblot has been validated by New York and other states and is covered by Medicare Part B. We do not have data for labs such as Mayo Clinic, Consolidated, ARUP, Medical Diagnostics Laboratory, Stony Brook University Medical Center, Cleveland Clinic, university and other labs which also test for Lyme disease in Florida, but we trust that the Florida Department of Health has this data available. We would appreciate transparency on these numbers.
  • Canine maps show a significant increase in incidence of Lyme disease, Ehrlichia, and Anaplasma in the state. Notably, dogs are less likely to travel out of state meaning the infections are more often locally acquired. 
    • According to the Companion Animal Parasite Council (CAPC), from 2019 – 2023, canine tick-borne infections have increased by 89.53% for Lyme disease; 100.49% for Ehrlichiosis; and 334.23% for Anaplasmosis in Florida.
    • In 2022, CAPC reported 4,284 canine cases compared to only 233 human cases reported by the CDC.
    • In 2023, CAPC reported 4,888 Lyme disease, 12,601 Ehrlichiosis, and 8,424 Anaplasmosis canine cases.
    • According to 2024 data YTD, Florida is considered moderate risk for Lyme and high risk for both Ehrlichia and Anaplasma. Notably, the Lyme incidence changed from 1/200 in 2023 to 1/100 for 2024 YTD.
    • The CAPC estimates its data represents “less than 30% of the activity in the geographic regions.” Applying this factor to the 4,284 cases in 2022, CAPC would estimate 14,280 canine cases which is >61x the human reported cases for the same year (4,284/.3 = 14,280).
  • MyLymeData statistics for “low incidence” states like Florida likewise show a large disparity between reported and actual cases. See Why Doesn’t the CDC Count Lyme Disease Cases in the South and the West? Everybody Else Does. | LymeDisease.org

The one-size-fits-all IDSA treatment guidelines fail countless patients, particularly those who are not timely diagnosed/treated or present with co-infections such as Babesia, Bartonella, or rickettsial infections.

  • A significant percentage of patients suffer persistent symptoms after antibiotic treatment. The CDC previously estimated 10-20% of patients, but now they claim “following antibiotic treatment, about 5-10% of people with Lyme disease have prolonged symptoms of fatigue, body aches, or difficulty thinking as a result of their infection.” We are unaware of any rationale or scientific basis for this change. To the contrary, research demonstrates a higher percentage. See e.g. Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here? (at six months, 36% of patients reported new-onset fatigue, 20% widespread pain, and 45% neurocognitive difficulties). It is widely accepted that patients who are not timely diagnosed and treated are more likely to suffer from persistent symptoms after IDSA-recommended treatment.
  • Lyme persists due to biofilms, round bodies, inability of antibiotics to penetrate tissues/organs. See Lyme Persists
  • Studies at Johns Hopkins showed doxycycline failed to eradicate the Lyme bacteria Borrelia burgdorferi in vitro. However, triple antibiotic combinations were effective in a mouse model. See also Superior efficacy of combination antibiotic therapy versus monotherapy in a mouse model of Lyme disease
  • Studies showing “long term antibiotics are not effective” used a single antibiotic, did not have a true placebo (i.e. giving IV rocephin to the control group), and/or ignored improvement of symptoms such as fatigue. Studies were designed to fail and then were widely reported without mention of study limitations/flaws.

The failure to timely diagnose and adequately treat Lyme disease comes at a tremendous economic burden. Lyme patients had 87% more visits to the doctor and 71% more visits to the emergency room within the year following diagnosis. This does not take into account additional economic costs due to missed work and long term disability. See Johns Hopkins study Lyme Disease Costs Up to $1.3 Billion Per Year to Treat, Study Finds and Health Care Costs, Utilization and Patterns of Care following Lyme Disease | PLOS ONE; see also The Financial Implications of a Well-Hidden and Ignored Chronic Lyme Disease Pandemic – PMC

Requested Action Items:

  1. Transparency on CDC positive cases. What are the reported case counts for each of the labs who test for Lyme disease in Florida and what percent are being reported to the CDC? Why are such a large percentage of cases not being counted? Why are canine cases an estimated 61x higher than human cases?
  2. Mandated education of clinicians in the state and alerts to medical care providers advising of increase in cases of Lyme, Ehrlichia, and Anaplasma in the state. Babesia and Bartonella can also cause overlapping symptoms. There are free CME webinars available on Invisible International.
  3. Educate residents about the risk of tick bites, including education of children in schools. See e.g. A School-Based Intervention to Increase Lyme Disease Preventive Measures Among Elementary School-Aged Children
  4. Since 2017, Babesia has been reportable in Florida. Please share the reports.
  5. Similar to the federal Tick-Borne Disease Working Group, we request that a Florida task force be formed, composed of members who have a diversity of backgrounds and perspectives (i.e. patients, researchers, health practitioners, public health).
  6. Explore potential legislation in the state promoting tick-borne disease awareness, mandating insurance coverage outside of IDSA guidelines when deemed medically necessary, and protecting doctors who prescribe medications in accordance with the ILADS standard of care. See Reviewing Current Lyme Legislation
  7. Fund research within the state, including widespread tick testing and patient-centered studies (i.e. efficacy of emerging combination therapies, screening of at-risk pregnant women, etc.).
  8. Update Florida Department of Health website on Lyme disease. In particular (but not limited to):
    • The FL DOH page discussing Lyme rashes under the symptoms and treatment tab is outdated and inconsistent with the CDC website. It is critical to communicate that there are many forms of erythema migrans rashes, not just the classic bull’s-eye. The current page states “between 60 and 80% of people will develop a red, “bull’s-eye rash” which is not accurate. In this study, researchers discovered most rashes were uniform in color (51%), pink (74%), oval (63%), and with clear borders (92%). Only 6% had the classic bull’s-eye pattern.
    • Under the symptoms and treatment tab, it states “a few patients, especially those diagnosed in the later stages of disease, may have persistent or recurrent symptoms.” (emphasis added). For many years, the  CDC had recognized that 10-20% of patients continue to suffer symptoms after antibiotic treatment. Without explanation, the CDC recently changed this estimate to 5-10% without any clear rationale for the change. Research from Johns Hopkins demonstrates a higher percentage than the CDC. See e.g. Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here? (at six months, 36% of patients reported new-onset fatigue, 20% widespread pain, and 45% neurocognitive difficulties); see also Health Care Costs, Utilization and Patterns of Care following Lyme Disease | PLOS ONE (“over 63% of the Lyme disease cases had at least one diagnosis associated with PTLDS, which is 36 percentage points higher a rate than the prevalence of the same symptoms in our control population”). Whatever estimate is used, it is certainly more than “a few.”
    • Under the transmission tab of the FL DOH website, it states “studies have shown that both nymph and adult ticks need to be attached for more than 24 hours to effectively transmit the infection.” However, a literature review has determined that in animal models, transmission can occur in less than 16 hours, and the minimum attachment time for transmission of infection has never been established. See Lyme borreliosis: a review of data on transmission time after tick attachment – PMC. In particular, if a tick is only partially fed and then attaches to a human, spirochetes can be found in the salivary glands increasing the risk of disease transmission after shorter attachment periods. Additionally, if a tick is not removed properly (i.e. if the body is squeezed or if heat or oils are used), then this increases the risk of disease transmission.
    • There is a growing body of research showing that ticks can also spread Bartonella infections to humans. See Can Ticks Transmit Bartonella? – Project Lyme.
    • Include acknowledgement that Lyme can spread from mother to baby during pregnancy. See e.g., CDC “Untreated Lyme disease during pregnancy can lead to infection of the placenta; spread from mother to fetus is possible but extremely rare.” While we disagree with the term “extremely rare” absent scientific studies proving this point, at least the CDC is now publicly acknowledging maternal-fetal transmission. See also Congenital Lyme disease is under-recognized by medical professionals (50% of Lymelight grant recipients were born with Lyme disease); Ongoing study Pregnancy and Early Neurodevelopmental Outcomes Following In Utero Lyme Disease Exposure funded by the Clinical Trials Network for Lyme and other Tick-borne Diseases (CTN); Lyme Disease and Pregnancy – LYMEHOPE
    • Provide an acknowledgement that existing laboratory tests for Lyme disease often result in false negative results such as: “if you are tested for Lyme disease and the results are negative, this does not necessarily mean you do not have Lyme disease. If you continue to experience unexplained symptoms, you should contact your health care provider and inquire about the appropriateness of retesting or initial or additional treatment.” See e.g., Maryland legislation.
    • Provide links to both the ILADS and IDSA standards of care for treating Lyme disease and related infections. See Schools of Thought about Lyme Disease

Melissa Bell, Esq. founded the Florida Lyme Disease Association in 2013, after several members of her family were severely impacted by Lyme disease. She also serves on the Executive Board of Project Lyme.

_______________

Great article!  

For more:

The take home: Clark is finding borrelia (Lyme) strains in the South that the current CDC two-tier testing will never pick up in a thousand years.

https://www.researchgate.net/publication/285584725_Isolation_of_live_Borrelia_burgdorferi_sensu_lato_spirochetes_from_patients_with_undefined_disorders_and_symptoms_not_typical_for_Lyme_diseases

The take home: Clark found live Bbsl (bissettii-like strain) in people from the Southeast who had undefined disorders not typical of LD, and were treated for LD even though they were seronegative, proving that B. bissetti is responsible for worldwide human infection.

He also showed DNA of Bbsl in Lone Star ticks which might be a bridge vector of transmission to humans.

Dr. Clark was the first to report finding LD spirochetes in animals and ticks in South Carolina, as well as in wild lizards in South Carolina and Florida. He has documented the presence of LD Borrelia  species, Babesia microti, Anaplasma phagocytophilum, Rickettsia species, and other tick-borne pathogens in wild animals, ticks, dogs, and humans in Florida and other southern states.

Plum Island History

http://  Approx. 12 Min

Why New York’s Plum Island is Totally Forbidden

3/24

Plum Island, located off the coast of Long Island, has a rich history spanning centuries. Originally known as “Isle des Plumes” by early French settlers due to its abundant bird population, it later became a haven for pirates and smugglers during the colonial era. In the 19th century, it was used as a quarantine station for diseased livestock, helping prevent the spread of diseases to mainland farms. During World War II, the island was taken over by the U.S. government and used for military purposes. In 1954, the Plum Island Animal Disease Center was established by the U.S. Department of Agriculture, where research on infectious animal diseases, including foot-and-mouth disease, was conducted. Today, the island remains a site of scientific research, though its future is uncertain amidst discussions of potential closure and redevelopment.

The video explains that as of 2023 the island was slated for closure and to be sold at private auction, while the facility itself would move to Kansas City University. As a part of the Consolidated Appropriations Act of 2021, and the response to the most recent ‘pandemic’ outbreak, the island was offered to federal agencies first. As of Feb. 2024, the facility still operates at Plum Island.

While the author of the video emphasizes the safety of the lab, the book Lab 257 paints quite a different picture with virus outbreaks, infected workers, flushing of contaminated raw sewage into area waters and the insidious connections between the island and Lyme disease and West Nile Virus.

For more: