Archive for the ‘research’ Category

Spanish Study Shows Vaxxed Spread COVID at Same Rate as Unvaccinated

https://thevaccinereaction.org/2022/02/spains-first-study-on-omicron-finds-vaccinated-people-spread-covid-at-same-rate-as-unvaccinated/

Spain’s First Study on Omicron Finds Vaccinated People Spread COVID at Same Rate as Unvaccinated

Spain’s First Study on Omicron Finds Vaccinated People Spread COVID at Same Rate as Unvaccinated

Several governments in Spain scrapped COVID passports following the study’s release.

The first Spanish study on how the Omicron variant of COVID-19 infects, incubates, and transmits was recently concluded by the Public Health Observatory of Cantabria.

The findings, which have not yet been peer reviewed, show that the highly infectious variant accounted for nearly half of the infections recorded during the whole pandemic. One reason Omicron has proven so transmissible, researchers discovered, is that the window for transmission is earlier than previous variants.

“Half of the infections occurred before the onset of symptoms,” researchers said.

The early stage transmission, scientists noted, complicates some mitigation efforts.

“This would imply that the effectiveness of measures such as screening, rapid testing or isolation would decrease significantly in the absence of preventive measures such as distance, limiting mass gatherings or social gatherings,” researchers said.

Perhaps the most consequential finding in the research, however, is that vaccines did not appear to reduce the spread of the virus.

“Vaccinated cases seem to have the same transmission capacity as unvaccinated people,” researchers concluded, according to EITB Radio Televisión Pública Vasca (the Basque Autonomous Community’s public broadcast service).

This is a departure from the Delta variant, researchers said, where transmission differences were found in vaccinated households and workplaces.

The study was based on 622 Omicron cases (and their 1,420 contacts) detected in Cantabria, a region on Spain’s north coast, in December 2021.

Scrapping Vaccine Passports

The findings out of Spain are just the latest example of why COVID-19 continues to spread despite human ingenuity and the widespread efforts of central planners to tame the virus.

Unlike previous pandemics, governments around the world took sweeping actions to restrict basic freedoms out of fear of the deadly pathogen. Businesses were closed, speech restricted, free assembly denied, and bodily autonomy was violated.

Despite these efforts the virus, now in its third year, continues to rage, and in many parts of the world governments have been slow to rescind harmful policies despite their ineffectiveness.

To its credit, parts of Spain have proven much more responsive than other parts of the world.

Two week ago, public health officials in Catalonia, an autonomous province in northeast Spain, and several other provinces, announced they were scrapping vaccine passports in light of this new evidence.

A committee of scientists told Catalonia’s regional government that because of the nature of Omicron, “a large part of the population is once again susceptible to getting infected whether or not they are vaccinated or have already had the illness.”

“The effectiveness of the compulsory use of the Covid certificate is reduced as an extra level of security,” scientists added.

The requirement to show a COVID passport had been in place since November in Catalonia, the second most-populous community in Spain, with some 7.7 million people. Smaller regions in Spain, such as Cantabria and Asturias, also have reportedly announced they will no longer require COVID passports for people to enter bars, restaurants, and other public spaces.

European media point out that Spain has suffered from widespread Omicron outbreaks even though the country boasts one of the higher vaccination rates in the world.

“Despite high levels of vaccination in Spain where 90.7 percent of people over the age of 12 are fully immunised,” The Local reports, “coronavirus cases exploded in Spain over the Christmas holidays, giving it one of Europe’s highest incidence rates.

The decision to scrap the vaccine passport follows widespread protests in Spain against vaccine passports and mask mandates.

The Pre-Eminence of His Own Plan

While the effectiveness of vaccines in slowing the spread is questionable, there is still an abundance of evidence suggesting that vaccines can significantly reduce the likelihood of falling seriously ill from COVID-19.

Dr. Jay Bhattacharya, a professor of medicine who studies epidemiology at Stanford University, credits his own speedy recovery from COVID to the vaccines and has praised them as “a wonderful achievement.”

But Bhattacharya has said vaccines are primarily a matter of personal health, not public health, since the benefits of vaccination lay primarily with the individual, and has argued that efforts to mandate vaccination erode confidence in public health.

“Opposition to discriminatory vaccine mandates is not the same as opposition to vaccines,” Bhattacharya said last year. “On the contrary, support for vaccine mandates is an anti-vax position because it breeds distrust and resentment toward public health.”

The new research out of Spain, combined with recent data from the CDC that show natural immunity confers more protection from some COVID variants than vaccines, reveals the folly of these coercive policies.

Vaccine passports are inherently unjust because free people require free movement, but they become both unjust and ridiculous when they fail to reduce the transmission of the virus or account for natural immunity.

Provinces in Spain that are rescinding their vaccine passport policies in light of this new evidence deserve some credit, because this does not come naturally to state planners.

In his work Socialism: An Economic and Sociological Analysis, the economist Ludwig von Mises noted how difficult it is for bureaucrats to relinquish control over their own plans.

“What those calling themselves planners advocate is not the substitution of planned action for letting things go. It is the substitution of the planner’s own plan for the plans of his fellow-men,” Mises wrote. “The planner is a potential dictator who wants to deprive all other people of the power to plan and act according to their own plans. He aims at one thing only: the exclusive absolute pre-eminence of his own plan.”

For those wondering why many countries continue to use coercive policies even in light of this new evidence, the words of Mises offer a beam of understanding.

Fortunately, many countries around the world—including the United KingdomDenmark, and the Czech Republic—are beginning to see the error and injustice of these coercive measures.


This article was reprinted with the author’s permission. It was originally published by the Foundation for Economic Education. Jonathan Miltimore is the Managing Editor of FEE.org. His writing/reporting has been the subject of articles in TIME magazine, The Wall Street Journal, CNN, Forbes, Fox News, and the Star Tribune.

Note: This commentary provides referenced information and perspective on a topic related to vaccine science, policy, law or ethics being discussed in public forums and by U.S. lawmakers.  The websites of the U.S. Department of Health and Human Services (DHHS) provide information and perspective of federal agencies responsible for vaccine research, development, regulation and policymaking.

Do Remnants of Lyme Bacteria Cause Ongoing Brain Inflammation?

https://www.lymedisease.org/tulane-kyme-brain-inflammation/

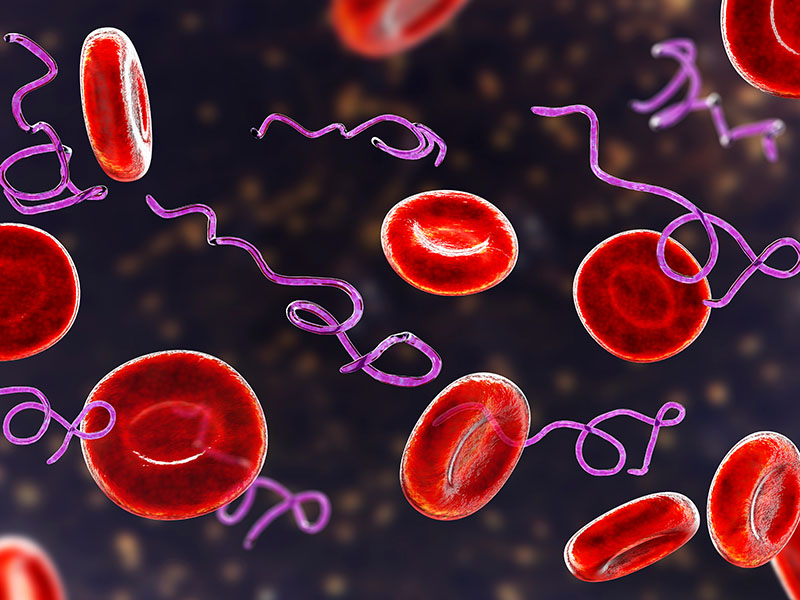
Do remnants of Lyme bacteria cause ongoing brain inflammation?

By Leslie Tate, Tulane University

Jan. 30. 2022

Even after antibiotic treatment, some Lyme disease patients suffer from an array of symptoms including neurological issues that greatly diminish their quality of life.

Brain scans of these patients show persistent neuroinflammation, but the cause has been unclear.

Tulane University researchers have discovered that remnants of B. burgdorferi, the bacteria that causes Lyme disease, may contribute to inflammation in both the central and peripheral nervous systems.

These remnants are significantly more inflammatory than live, intact bacteria. Their results were published in Scientific Reports.

Lead researcher Geetha Parthasarathy, PhD, assistant professor of immunology at the Tulane National Primate Research Center, explored the effects of B. burgdorferi remnants on nervous system tissue using a nonhuman primate model, investigating the effects on both the frontal cortex and dorsal root ganglion.

Inflammatory markers

Inflammatory markers in these areas were several times higher in samples exposed to remnants of B. burgdorferi than in samples exposed to live bacteria, and several times higher in the frontal cortex than the dorsal root ganglion. The bacterial remnants also caused cell death in brain neurons.

“As neuroinflammation is the basis of many neurological disorders, lingering inflammation in the brain due to these unresolved fragments could cause long term health consequences,” Parthasarathy said.

Scientists still don’t know how B. burgdorferi spirochetes find their way into brain tissue.

In longstanding or persistent Lyme disease infections, bacterial spirochetes may harbor inside major organs, including the heart and brain, where they could continue to wreak havoc over time. Antibiotics may kill the bacteria in these organs, but remnants could remain if the body cannot adequately eliminate them.

Parthasarathy said the findings may explain some of the neurological symptoms and conditions that patients with persistent Lyme infections can experience.

She plans future studies to investigate new anti-inflammatory therapies for antibiotic-resistant neuroinflammation and to explore why the body may not be clearing these bacterial remnants.

This study was funded by the Bay Area Lyme Foundation

SOURCE OF PRESS RELEASE: Tulane University

Cannabidiol Inhibits SARS-CoV-2 Replication Through Induction of the Host ER Stress and Innate Immune Responses

https://www.science.org/doi/10.1126/sciadv.abi6110

Cannabidiol inhibits SARS-CoV-2 replication through induction of the host ER stress and innate immune responses

Science Advances • 20 Jan 2022 • First ReleaseDOI: 10.1126/sciadv.abi6110
Abstract

The spread of SARS-CoV-2 and ongoing COVID-19 pandemic underscores the need for new treatments. Here we report that cannabidiol (CBD) inhibits infection of SARS-CoV-2 in cells and mice. CBD and its metabolite 7-OH-CBD, but not THC or other congeneric cannabinoids tested, potently block SARS-CoV-2 replication in lung epithelial cells. CBD acts after viral entry, inhibiting viral gene expression and reversing many effects of SARS-CoV-2 on host gene transcription. CBD inhibits SARS-CoV-2 replication in part by up-regulating the host IRE1α RNase endoplasmic reticulum (ER) stress response and interferon signaling pathways.
In matched groups of human patients from the National COVID Cohort Collaborative, CBD (100 mg/ml oral solution per medical records) had a significant negative association with positive SARS-CoV-2 tests. This study highlights CBD as a potential preventative agent for early-stage SARS-CoV-2 infection and merits future clinical trials. We caution against use of non-medical formulations including edibles, inhalants or topicals as a preventative or treatment therapy at the present time.
__________________
For more:

Ticks Bite Leads to GBS

https://danielcameronmd.com/tick-bite-leads-to-guillain-barre-syndrome/

Tick bite leads to Guillain-Barré Syndrome

tick-bite-Guillain-Barre

Welcome to another Inside Lyme Podcast with your host Dr. Daniel Cameron. In this episode, Dr. Cameron will be discussing the case of a 71-year-old woman who was initially diagnosed with Ehrlichia, a tick-borne illness but later developed Guillain-Barré Syndrome.

The study, entitled “Case of ehrlichiosis induced Guillain-Barre Syndrome in a 71-year-old female,” was published by Malhis and colleagues in the journal IDcases

The woman’s initial symptoms occurred over a 3-week period and included: generalized weakness, dizziness, visual changes, chills, a fever, neck and abdominal pain.

After presenting to the hospital, she was diagnosed with Ehrlichia, a tick-borne illness, based on a low platelet count, elevated liver function tests, an insect bite, a positive Ehrlichia test by PCR, and absence of another illness.

The woman was treated with doxycycline and her symptoms improved.

Click top link to watch a video discussing Ehrlichia-induced Guillain-Barre Syndrome 

However, approximately one week later, she returned to the hospital with worsening symptoms and “numbness and areflexia in her lower extremities which progressed since her first encounter,” the authors write.

She developed an unsteady gait, which required a walker and had tingling in her feet and difficulty urinating. She required a straight foley catheterization.

“Although ehrlichiosis is not a common cause for GBS, the pathogenesis is like Lyme disease or Campylobacter jejuni,” the authors write.

“This patient had clinical symptoms that were like tick-borne illness yet as her disease progressed, it illustrated the need for an expanded differential diagnosis.”

The woman was diagnosed with an acute inflammatory demyelinating polyneuropathy, often referred to as Guillain-Barré Syndrome.

There was no evidence of another tick-borne illness including Lyme disease, Babesia, Heartland or Bourbon Virus.

The patient improved significantly with IVIG and was discharged to a rehabilitation center.

“Although ehrlichiosis is not pathognomonic for Guillain-Barre, it is important to not rule out as a cause,” the authors point out. “With the COVID-19 outbreak, there have been reported cases of GBS induced by COVID. It too can cause an immune response to the nervous system.”

Bourbon virus

“There have been reported cases of tick-borne illness that have not recovered despite tetracycline treatment,” reports Kosoy et al.2

They cite the case of a 50-year-old male from Eastern Kentucky who was found to have several tick bites, enlarged Lymph nodes, a macular papular rash, low platelets, low white count, and complaints of nausea, vomiting and diarrhea, followed by fever, myalgias, headaches and arthralgias.

The patient’s labs were negative for known tick-borne pathogens and he failed tetracycline treatment.

“Multiorgan failure developed, and he died 11 days after illness onset from cardiopulmonary arrest,” the authors write.

The man was later diagnosed with the Bourbon virus, a newly recognized tick-borne illness.3

Guillain-Barré Syndrome

 Guillain-Barré Syndrome (GBS) is an acute autoimmune demyelinating polyradiculoneuropathy that induces rapid and progressive flaccid weakness, according to Malhis.1 GBS can be life threatening if it progresses to involving the diaphragm.

 There are a number of causes of GBS. Respiratory and gastrointestinal infections can lead to GBS.  Lyme disease, tick-paralysis, HIV, and West Nile Virus can also lead to GBS.  There is also a very slim chance (1 in a million) that a flu vaccine can lead to GBS.

Treatment for GBS includes intravenous immunoglobulin (IVIG) therapy or plasma exchange. Steroids have not been helpful in treating the condition. An estimated 85% of patients recover their independent ambulation.

The authors conclude: “It is important to keep a broad differential as sometimes common syndromes do not always come from common pathogens and with the COVID-19 pandemic having similar results, we are learning new things that may potentially be new standards in medical education.”

The following questions are addressed in this Podcast episode:

  1. What is the Guillain-Barré Syndrome?
  2. What is the treatment for Guillain-Barré Syndrome?
  3. What is the Bourbon and Heartland virus?
  4. Why are there concerns for individuals with COVID-19?

Thanks for listening to another Inside Lyme Podcast. Please remember that the advice given is general and not intended as specific advice to any particular patient. If you require specific advice, please seek that advice from an experienced professional.

Inside Lyme Podcast Series

This Inside Lyme case series will be discussed on my Facebook page and made available on podcast and YouTube.  As always, it is your likes, comments, and shares that help spread the word about this series and our work. If you can, please leave a review on iTunes or wherever else you get your podcasts.

References:
  1. Malhis JR, Mahmoud A, Belote A, Ebers A. Case of ehrlichiosis induced Guillain-Barre Syndrome in a 71 year-old female. IDCases. 2021;26:e01301. doi:10.1016/j.idcr.2021.e01301
  2. Kosoy OI, Lambert AJ, Hawkinson DJ, et al. Novel thogotovirus associated with febrile illness and death, United States, 2014. Emerg Infect Dis. May 2015;21(5):760-4. doi:10.3201/eid2105.150150
  3. Hearland and Bourbon Virus Disease. CDC. https://www.cdc.gov/ticks/tickbornediseases/heartland-virus.html Last accessed 12/12/21.

___________________

**Comment**

This article states that COVID can also induce GBS, which begs the question – why would Dr. Cameron believe and encourage Lyme/MSIDS patients to get the COVID injections?  The article admits that COVID can cause an immune response to the nervous system, which Lyme/MSIDS patients are already struggling with.  Illogical.

Please read and understand the risks of the COVID injections – and there are many:

A Literature Review & Meta-Analysis of the Effects of Lockdowns on COVID-19 Mortality. CDC Finally Admits Natural Immunity Trumps “Vaccines.” It’s Time to Rehire Unvaxxed Workers

A_Literature_Review_and_Meta_Analysis_of_the_Effects_of_Lockdowns

January 2022

By Jonas Herby, Lars Jonung, and Steve H. Hanke

John Hopkins Institute for Applied Economics, Global Health, and the Study of Business Enterprise

Abstract
This systematic review and metaanalysis are designed to determine whether there is empirical evidence to support the belief that “lockdowns” reduce COVID19 mortality. Lockdowns are defined as the imposition of at least one compulsory, nonpharmaceutical intervention (NPI). NPIs are any government mandate that directly restrict peoples’ possibilities, such as policies that
limit internal movement, close schools and businesses, and ban international travel. This study employed a systematic search and screening procedure in which 18,590 studies are identified that could potentially address the belief posed. After three levels of screening, 34 studies ultimately qualified. Of those 34 eligible studies, 24 qualified for inclusion in the metaanalysis.
They were separated into three groups: lockdown stringency index studies, shelterinplaceorder (SIPO) studies, and specific NPI studies.

An analysis of each of these three groups support the conclusion that lockdowns have had little to no effect on COVID19 mortality.

More specifically, stringency index studies find that lockdowns in Europe and the United States only reduced COVID19 mortality by 0.2% on average. SIPOs were also ineffective, only reducing COVID19 mortality by 2.9% on average. Specific NPI studies also find no broadbased evidence of noticeable effects on COVID19 mortality.

While this metaanalysis concludes that lockdowns have had little to no public health effects, they have imposed enormous economic and social costs where they have been adopted.

In consequence, lockdown policies are illfounded and should be rejected as a pandemic policy instrument.

________________

Go here for an excellent article and news video titled: “The CDC is Finally Recognizing ‘Natural Immunity’ – Legislators Should Follow Suit”

Not exempting those with prior infection was always unfair; now it is unscientific as well.

https://childrenshealthdefense.org/defender/cdc-natural-immunity-trumps-vaccine-immunity/

CDC Admits Natural Immunity Trumps Vaccine Immunity — 5 Months After Touting Vaccines as Superior

Five months after issuing a statement that vaccine immunity protects against COVID better than natural immunity, the Centers for Disease Control and Prevention sent a report showing the opposite is true, at least when it comes to the Delta variant.

A Jan. 19 report from the Centers for Disease Control and Prevention (CDC) showed natural immunity against COVID was at least three times as effective as vaccination alone at preventing people from becoming infected with the Delta variant.  (See link for article)

Important quote regarding higher hazard rates for hospitalization in the vaxxed:

“This is potentially a concerning finding in that it suggests the vaccine could be interfering with natural immunity,” Setty said.

___________________

https://www.clarkcountytoday.com/news/natural-immunity-gets-another-boost-from-two-new-u-s-studies/

Natural immunity gets another boost from two new U.S. studies

CDC and Johns Hopkins studies show strength and duration of natural immunity protection

Two newly released studies show the power of natural immunity following recovery from COVID-19 sickness. The Centers for Disease Control and Prevention (CDC) says:

“previous SARS-CoV-2 infection also confers protection against severe outcomes in the event of reinfection.”

Johns Hopkins found that natural immunity developed from prior variants reduced the risk of infection with the Omicron variant.  (See link for article)

Summary:

  • natural immunity was six times stronger during the Delta wave than vaccination 
  • Dr. Makary states that “hybrid immunity” (“vaccinated” & infected) increases immunity by 3.8%, while Dr. Urso, on the other hand, states there’s no such thing as “super immunity.”  Natural immunity is robust, long-lasting, and sufficient. 
  • Makary believes we aren’t seeing new “vaccinations” because people are hardened by excessive government policies and are choosing to forgo the shots. He also states “no healthy child has ever died of COVID that we know of.”
  • The Omicron wave in Africa subsided quickly with modest hospitalizations because close to 80% had been previously infected by variants.
  • The CATO institute weighed in and stated that “universal vaccine mandates are irrational in ignoring naturally acquired immunity from infection and recovery…..If OSHA had reviewed the medical and scientific literature regarding the relative protection efficacy of natural immunity compared to “vaccination”, it is unlikely the agency would be successful in establishing a factual basis for forced “vaccination” of COVID-recovered individuals.  Given the trivial – if any – benefit to either the individual or the public from compelled “vaccination” of Covid-recovered individuals, that evidence of elevated adverse effects requires an especially high standard of proof by regulators to overcome.”
  • Dr. Makary states, “By firing staff with natural immunity, employers got rid of those least likely to infect others.” “It’s time to reinstate those employees with an apology.”
  • Makary states it’s time to rehire the fired for three reasons: it was unfair to begin with, we have therapeutics, and many have natural immunity. “The risk of somebody who has natural immunity getting hospitalized is 3 per 10,000,” which is identical to the risk of someone with hybrid immunity – so getting a booster did NOTHING to change hospitalization numbers.
  • Makary noted that public health officials are falsely reporting higher numbers of COVID deaths than reality shows, and cases have declined steeply.
  • It’s normal to have a massive influx of patients every winter from a number of respiratory pathogens, the problem this time is a massive staffing shortage.  One in five health care workers have left. 

Washington State was so short-staffed they told workers who had COVID to come back into work – even with symptoms.

  • There’s only been ONE death in 52,000 Omicron cases in the Kaiser CA study, which is LOWER than influenza.
  • The article then reported on a North Carolina man who said a hospital refused to carry out a kidney transplant because he’s unvaccinated against COVID-19. He is willing to “die free” rather than comply with their vaccine requirement. He’s had the coronavirus twice before and believes getting the vaccine should be a personal choice, not a requirement.  The hospital doesn’t care about science and is holding its ground. Sadly, this has been happening globally.  A three year old from Cyprus was also refused lifesaving surgery in three countries because his parents weren’t vaxxed.  Go here to send an email to your members of Congress to stop this violation of medical ethics.
  • Noah Carl noted in his review of the Danish study, that there’s no obvious need for people who have recovered from COVID to get vaccinated.

“The tricky part may be getting this message through to politicians.”

Illogical COVID madness continues…..

For more:
