Archive for the ‘Activism’ Category

Autism-Aluminum Adjuvant Link Corroborated

https://medium.com/@jbhandley/new-canadian-study-autism-aluminum-adjuvant-link-corroborated-330e947f5f62

New Canadian study: Autism-Aluminum adjuvant link corroborated

BY J.B. HANDLEY September 18, 2017

In the December 2017 issue of the Journal of Inorganic Biochemistry and released online today, Dr. Christopher Shaw and colleagues at the University of British Columbia have established convincing biological evidence linking aluminum adjuvant used in vaccines to autism.

“This is the paper I have been waiting for. This paper reports measurements of cytokines in the brains of animals injected with aluminum adjuvant as neonates. The same cytokines are elevated as in human autism. IL-6 and CCL2/MCP-1 are elevated for example. Male animals are more strongly affected. It’s a perfect match to human autism.”
VANCOUVER, British Columbia — Just two weeks ago, I wrote about a study from France that raised major concerns about aluminum adjuvant used in vaccines. The French study authors wrote: “Concerns about its [aluminum adjuvant’s] safety emerged following recognition of its unexpectedly long-lasting biopersistence within immune cells in some individuals, and reports of chronic fatigue syndrome, cognitive dysfunction, myalgia, dysautonomia and autoimmune/inflammatory features temporally linked to multiple Al [aluminum]-containing vaccine administrations.”

In a nutshell, the French study found that when smaller doses of aluminum adjuvant were consistently injected over a short period of time — like during childhood vaccinations —the aluminum was more likely to end up in the brain, and the French scientists issued a stern warning about the use of aluminum adjuvant in vaccines:

In the context of massive development of vaccine-based strategies worldwide, the present study may suggest that aluminium adjuvant toxicokinetics and safety require reevaluation.


Canadian researchers establish direct link

In the December 2017 issue of the Journal of Inorganic Biochemistry and released online today, Dr. Christopher Shaw and colleagues have established convincing biological evidence linking aluminum adjuvant to autism. The study’s title alone should cause concern for parents everywhere:

Subcutaneous injections of aluminum at vaccine adjuvant levels activate innate immune genes in mouse brain that are homologous with biomarkers of autism

As the study authors state:

“It thus appears that Al [aluminum adjuvant] triggered innate immune system activation and altered cholinergic activity in male mice, observations which are consistent with those in autism. Female mice were less susceptible to Al exposure as only the expression levels of NF-κB inhibitor and TNFA were altered. Regional patterns of gene expression alterations also exhibited gender differences, as frontal cortex was the most affected area in males and cerebellum in females. Thus, Al adjuvant promotes brain inflammation and males appear to be more susceptible to Al′s toxic effects.”

It’s critical to note that the researchers found gender differences in how the mice responded, with male mice showing higher susceptibility, which is consistent with what we are seeing in autism: roughly 80% of the cases are boys.


The Canadian researchers included a diagram in their study that showed how aluminum adjuvant can contribute to an inflammatory cascade in the brain that leads to autism.
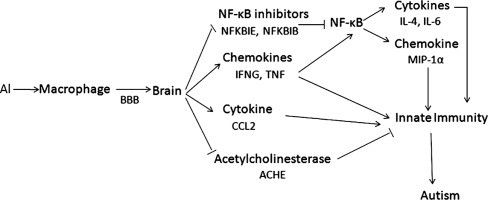

What does this mean in plain English?

Six months ago, I wrote an article about how close it appeared international scientists were to establishing a clear biological basis for how aluminum adjuvant can create autism. My article has been read more than 250,000 times, and I have heard from scientists from all over the world (most unwilling to let me quote them in public, which is its own great tragedy), including a scientist who has created a great website called Vaccine Papers. I asked “VP” about the importance of this study, and words were not minced:

This is the paper I have been waiting for.

This paper reports measurements of cytokines in the brains of animals injected with aluminum adjuvant as neonates. The same cytokines are elevated as in human autism. IL-6 and CCL2/MCP-1 are elevated for example. Male animals are more strongly affected. It’s a perfect match to human autism.

The paper includes a number of strong statements about vaccine causality.

This paper is hugely important because it shows IL-6 elevation in the brain, which of course provides a firm link to the immune activation literature. It is strong evidence supporting the al adjuvant IL-6 autism hypothesis.
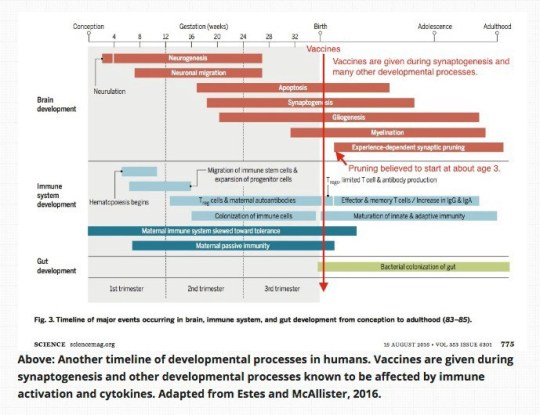
Vaccines are given to babies during key phases of brain development

A Clear Hypothesis

If you would like to understand this complex issue in greater detail, I hope you will consider reading my widely read article from six months ago:

For the sake of brevity, here are the four key scientific discoveries I discussed in this lengthy article, most of which has happened in the last thirty-six months, appearing to show a clear link between aluminum adjuvant from vaccines and autism.

Discovery #1: “Maternal Immune Activation” can cause autism

Studies that support Discovery #1:

  1. Pregnancy, Immunity, Schizophrenia, and Autism.

2. Neuroglial activation and neuroinflammation in the brain of patients with autism

3. Microglial Activation in Young Adults With Autism Spectrum Disorder

4. Maternal Immune Activation Alters Fetal Brain Development through Interleukin-6

5. Activation of the Maternal Immune System During Pregnancy Alters Behavioral Development of Rhesus Monkey Offspring

6. Brain IL-6 elevation causes neuronal circuitry imbalances and mediates autism-like behaviors

Some helpful quotes from the above research to help contextualize Discovery #1:

“As we learn more about the connections between the brain and the immune system, we find that these seemingly independent networks of cells are, in fact, continually talking to each other. As an adult, the activation of your immune system causes many striking changes in your behavior — increased sleep, loss of appetite, less social interaction — and, of course, headaches. Conversely, stress in your life (as perceived by your brain) can influence immune function — the brain regulates immune organs, such as the spleen, via the autonomic nervous system.

Recent evidence shows that this brain-immune conversation actually starts during the development of the embryo, where the state of the mother’s immune system can alter the growth of cells in the fetal brain. As we shall see, such alterations can lead to an increased risk of schizophrenia or autism in the offspring.” — Dr. Paul Patterson, CalTech

Dr. Paul Patterson, CalTech

“There is also very striking evidence of immune dysregulation in the brain itself. Just last year, a group led by Carlos Pardo at Johns Hopkins found what they’re calling a “neural inflammation” in postmortem examination of brains of patients with autism who died between the ages of eight and 44 years. But these people weren’t infected — they died of such things as drowning or heart attacks. The study found that the microglial cells, which act as the brain’s own immune system, were activated. The study also found amazing increases of certain cytokines in the brain, and of others in the cerebro- spinal fluid. This is is a landmark paper, in my opinion. It presents the first evidence that there’s an ongoing, permanent immune-system activation in the brains of autistic people. It’s a subclinical state, because there’s no overt infection. But it’s there.” — Dr. Paul Patterson, CalTech

“In conclusion, the present PET measurements revealed marked activation of microglia in multiple brain regions of young adults with ASD. The results strongly support the contention that immune abnormalities contribute to the etiology of ASD.” — Dr. Carlos Pardo, Johns Hopkins

“Cytokines are produced by the white blood cells, and their levels in the blood increase when we get an infection…We think that maternal immune activation alters brain circuits…there’s that permanent, subclinical, altered immune state in the autistic brain — those increased cytokine levels…are they [cytokines] actually interacting with the brain in an ongoing fashion, with consequences visible in the patients’ behavior? I favor [the cytokine] hypothesis.” — Dr. Paul Patterson, CalTech

“Here we show that the cytokine interleukin-6 (IL-6) is critical for mediating the behavioral and transcriptional changes in the offspring. A single maternal injection of IL-6 on day 12.5 of mouse pregnancy causes prepulse inhibition (PPI) and latent inhibition (LI) deficits in the adult offspring.” — Dr. Paul Patterson, CalTech

“In this rhesus monkey model, MIA yields offspring with abnormal repetitive behaviors, communication, and social interactions. These results extended the findings in rodent MIA models to more human-like behaviors resembling those in both autism and schizophrenia.” — UC Davis MIND Institute

“In summary, our study supports a critical role of IL-6 elevation in modulating autism-like behaviors through impairments on synapse formation, dendritic spine development, as well as on neuronal circuit balance. These findings suggest that manipulation of IL-6 may be a promising avenue for therapeutic interventions.” —Dr. Xiaohong Li, Shanghai Jiao Tong University School of Medicine


Discovery #2: Aluminum Adjuvant causes immune activation and is far more neurotoxic than previously thought

Studies that support Discovery #2:

  1. Aluminum Adjuvant Linked to Gulf War Illness Induces Motor Neuron Death in Mice
  2. Aluminum hydroxide injections lead to motor deficits and motor neuron degeneration
  3. Mechanisms of aluminum adjuvant toxicity and autoimmunity in pediatric populations
  4. Slow CCL2-dependent translocation of biopersistent particles from muscle to brain

5. Biopersistence and brain translocation of aluminum adjuvants of vaccines

6. Non-linear dose-response of aluminium hydroxide adjuvant particles: Selective low dose neurotoxicity

Some helpful quotes from the above research to help contextualize Discovery #2:

“In addition, the continued use of aluminum adjuvants in various vaccines (i.e., Hepatitis A and B, DPT, and so on) for the general public may have even more widespread health implications. Until vaccine safety can be comprehensively demonstrated by controlled long-term studies that examine the impact on the nervous system in detail, many of those already vaccinated as well as those currently receiving injections may be at risk in the future. Whether the risk of protection from a dreaded disease outweighs the risk of toxicity is a question that demands urgent attention.” — Dr. Christoper Shaw, University of British Columbia

“Overall, the results reported here mirror previous work that has clearly demonstrated that aluminum, in both oral and injected forms, can be neurotoxic. Potential toxic mechanisms of action for aluminum may include enhancement of inflammation (i.e., microgliosis)…” — Dr. Christoper Shaw, University of British Columbia

“…it is somewhat surprising to find that in spite of over 80 years of use, the safety of Al adjuvants continues to rest on assumptions rather than scientific evidence.For example, nothing is known about the toxicology and pharmacokinetics of Al adjuvants in infants and children…Yet, in spite of these observations children continue regularly to be exposed to much higher levels of Al adjuvants than adults, via routine childhood vaccination programmes.” — Dr. Lucija Tomljenovic, University of British Columbia

“However, continuously escalating doses of this poorly biodegradable adjuvant in the population may become insidiously unsafe, especially in the case of overimmunization or immature/altered blood brain barrier…” —Dr. Josette Cadusseau, Université Paris

“Thus alum and other poorly biodegradable materials taken up at the periphery by phagocytes circulate in the lymphatic and blood circulation and can enter the brain using a Trojan horse mechanism similar to that used by infectious particles. Previous experiments have shown that alum administration can cause CNS dysfunction and damage, casting doubts on the exact level of alum safety.” — Dr. Josette Cadusseau, Université Paris

“We conclude that Alhydrogel [aluminum adjuvant] injected at low dose in mouse muscle may selectively induce long-term Al cerebral accumulation and neurotoxic effects. To explain this unexpected result, an avenue that could be explored in the future relates to the adjuvant size since the injected suspensions corresponding to the lowest dose, but not to the highest doses, exclusively contained small agglomerates in the bacteria-size range known to favour capture and, presumably, transportation by monocyte-lineage cells. In any event, the view that Alhydrogel neurotoxicity obeys ‘the dose makes the poison’ rule of classical chemical toxicity appears overly simplistic.” —Dr. Romain K. Gherardi, Université Paris Est Créteil (UPEC)

“In the context of massive development of vaccine-based strategies worldwide, the present study may suggest that aluminium adjuvant toxicokinetics and safety require reevaluation.” — Dr. Romain K. Gherardi, Université Paris Est Créteil (UPEC)


Discovery #3: Aluminum can increase IL-6 in the brain

Studies that support Discovery #3:

  1. Neuroprotective Effect of Nanodiamond in Alzheimer’s Disease Rat Model: a Pivotal Role for Modulating NF-κB and STAT3 Signaling

2. Brain IL-6 elevation causes neuronal circuitry imbalances and mediates autism-like behaviors

Some helpful quotes from the above research to help contextualize Discovery #3:

“The results also showed that aluminum administration increased the hippocampus pro-inflammatory cytokines TNF-α by 3.8-fold, IL-6 by 4-fold, and iNOS by 3.8-fold compared to the normal control group.” —Dr. Mosaad A. Abdel-Wahhab, Cairo University

Most vaccines contain aluminum, and aluminum is a proven neurotoxin, in amounts received from vaccines. Vaccines in combination can result in toxic aluminum overload. Even the aluminum in a single vaccine can be harmful because the aluminum is in a form that is more dangerous than ingested aluminum. Specifically, vaccine aluminum is in nanoparticulate form, which is harder for the body to eliminate, and because it is transported around the body differently than ingested aluminum.

It is natural and normal to ingest small doses of aluminum from food and water. Its not good for you, but the body has adequate defenses. Absorption of ingested Al is low, about 0.3%, so about 99.7% is eliminated in feces. Ingested aluminum is in ionic form (individual charged atoms), which is readily removed by the kidneys. Also, ionic aluminum is blocked from entering the brain by the blood brain barrier. The low absorption, rapid elimination by the kidneys and barrier to brain entry adequately protects the brain from aluminum.

However, nanoparticulate aluminum from vaccines cannot be removed by the kidneys. The particles are far too large to be filtered out by the kidneys. The Al nanoparticles do dissolve slowly (converting to ionic aluminum). But long before they can dissolve completely, the Al nanoparticles are “eaten” by immune system cells called macrophages. In other words, the particles wind up inside the macrophages. Once loaded with the Al nanoparticles, the macrophages spread aluminum as they travel through the body. This is dangerous, because the Al-loaded macrophages carry Al nanoparticles to tissues (e.g. the brain) that are damaged by very small amounts of aluminum. — Vaccine Papers

“Here we show that mice with elevated IL-6 in the brain dis- play many autistic features, including impaired cognitive abilities, deficits in learning, abnormal anxiety traits and habituations, as well as decreased social interactions. IL-6 elevation caused alterations in excitatory and inhibitory synaptic formations and disrupted the balance of excitatory/inhibitory synaptic transmissions. IL-6 elevation also resulted in an abnormal change in the shape, length and distributing pattern of dendritic spines. These findings suggest that IL-6 elevation in the brain could mediate autistic-like behaviors, possibly through the imbalances of neural circuitry and impairments of synaptic plasticity.” —Dr. Xiaohong Li, Shanghai Jiao Tong University School of Medicine


Discovery #4: Hepatitis B vaccine induces IL-6 in postnatal rats

Studies that support Discovery #4:

[Author’s note: This fourth discovery was really the subject of my extensive article, because it discussed a new paper that seemed to tie everything together. The Canadian paper above ties everything together even more tightly.]

  1. Neonatal vaccination with bacillus Calmette–Guérin and hepatitis B vaccines modulates hippocampal synaptic plasticity in rats

Some helpful quotes from the above research to help contextualize Discovery #4:

“An important new study by Li et al. reports the effects of bacillus calmette-guerin (BCG) vaccine (for tuberculosis) and hepatitis B vaccine on brain development in infant rats. The study relates the observed brain changes to the type of immune activation (Th1 or Th2, explained below) stimulated by the vaccines. The BCG and hep B vaccines had opposite effects on the brain (BCG being beneficial, and hep B being detrimental), and a combination of both vaccines resulted in cancellation of the effects.

This is the first study to test the effects of immune activation by vaccination on brain development. All other studies of immune activation have used essentially pathological conditions that mimic infection and induce a strong fever. A criticism I have heard often from vaccine advocates is that the immune activation experiments are not relevant to vaccines because vaccines cause a milder immune activation than injections of poly-IC or lipopolysaccharide (two types of immune system activators).

This new study demonstrates that vaccines can affect brain development via immune activation. Hence, the immune activation experiments are relevant to vaccines…The hep B vaccine increased IL-6 in the hippocampus (the only brain region analyzed for cytokines).” — Vaccine Papers


Four discoveries, a clear path to autism

Here’s a simple graphic that I think spells out the process of triggering autism very clearly, as demonstrated by the published science I have shared with you above through the four discoveries.

The new Canadian study, just published, makes these findings even more clear, and more robust, and provides even greater detail into HOW aluminum adjuvant leads to autism.

Image created by Vaccine Papers.org

Now what?

When I published my article back in February, I heard from scientists from all over the world. I heard from pediatricians. I heard from board members at Autism Speaks. Many agreed with me: this was disturbing and important work, and it may well describe where all this autism is coming from. What’s happened since that time? Nothing.

There’s no mechanism for reviewing or putting all this published science together. The scientists doing this great work are perpetually nervous that they will lose their funding source or get “Wakefielded.” There’s no group responsible for putting all these published scientists in a room and figuring out what we do about this giant mess, and what all this information means. Every minute, a new child is diagnosed with autism, and every minute, it strikes me that autism may be completely AVOIDABLE. If you’re reading this, all I can ask is that you share the information widely, and that if you happen to be in a position of influence, please help save our kids.

In my opinion, we are much, much closer to understanding how autism has been triggered in so many children, and I hope this article is another step on the path to the truth. And, for so many of you out there doing everything you can to help you son or daughter with autism live the best possible life, perhaps a clearer understanding of how their autism was triggered will improve their chances for recovery.


Addendum

For those of you interested in hearing from Dr. Shaw directly, here’s a video excerpt (just under 2 minutes) from the movie The Greater Good where Dr. Shaw discusses an earlier study he and his colleagues conducted looking at aluminum adjuvant (Aluminum hydroxide injections lead to motor deficits and motor neuron degeneration):


J.B. Handley is the father of a child with Autism. He and his wife co-founded Generation Rescue, a national autism charity. He spent his career in the private equity industry and received his undergraduate degree with honors from Stanford University. He is also the author of “The Only Vaccine Guide a New Parent Will Ever Need” , “An Angry Father’s Guide to Vaccine-Autism Science”, and “7 reasons CDC employees should be “crying in the hallways” Mr. Handley has started a podcast called “How to End the Autism Epidemic” — you might enjoy his first six interviews:


**Comment**

I’m posting this because it should be important to everyone; however, whenever you talk about the immune system and cytokines, Lyme/MSIDS patients should sit up and take notice.  Due to a pathogen storm, we have a cytokine storm, confusing our immune systems and giving us boatloads of pain among other horrific symptoms.  This is also a sound warning about receiving any vaccinations while infected as they are designed to introduce many foreign substances into the body so the body mounts a response.  Our immune systems are already confused by a pathogen invasion.  In fact, the question truly begs to be asked, are vaccines ever safe for infected patients?  Also, it is important to point out that it is believed that children can get infected congenitally, which means they come out of the shoot compromised.  What does vaccination do to them?

So much is unknown and unproven.  Our children are too important not to search out the answers as inconvenient as they may be.

Every Lyme/MSIDS patient I know has regressed after a vaccination.  Food for thought.

For more on vaccines:  https://madisonarealymesupportgroup.com/2017/03/30/ty-bollinger-the-truth-about-vaccines-series/

https://wordpress.com/post/madisonarealymesupportgroup.com/17421  Dark Ages of Immunization Medicine Are NOW

https://madisonarealymesupportgroup.com/2017/07/21/class-and-race-profiling-in-the-vaccine-culture-war/

Info on the Lyme Vaccine:  https://madisonarealymesupportgroup.com/2017/07/01/pbs-lyme-vaccine/

https://madisonarealymesupportgroup.com/2017/09/07/20268/  (This link has many more listed at the end of the article)

 

TBI’s in Australia

https://www.mja.com.au/journal/2017/206/7/tick-borne-infectious-diseases-australia

Tick-borne infectious diseases in Australia

Stephen R Graves and John Stenos
Med J Aust 2017; 206 (7): 320-324. || doi: 10.5694/mja17.00090

Summary

  • Tick bites in Australia can lead to a variety of illnesses in patients. These include infection, allergies, paralysis, autoimmune disease, post-infection fatigue and Australian multisystem disorder.
  • Rickettsial (Rickettsia spp.) infections (Queensland tick typhus, Flinders Island spotted fever and Australian spotted fever) and Q fever (Coxiella burnetii) are the only systemic bacterial infections that are known to be transmitted by tick bites in Australia.
  • Three species of local ticks transmit bacterial infection following a tick bite:
    • the paralysis tick (Ixodes holocyclus) is endemic on the east coast of Australia and causes Queensland tick typhus due to R. australis and Q fever due to C. burnetii;
    • the ornate kangaroo tick (Amblyomma triguttatum) occurs throughout much of northern, central and western Australia and causes Q fever; and
    • the southern reptile tick (Bothriocroton hydrosauri) is found mainly in south-eastern Australia and causes Flinders Island spotted fever due to R. honei.
  • Much about Australian ticks and the medical outcomes following tick bites remains unknown. Further research is required to increase understanding of these areas.

**Comment**

The key phrase:  Much remains unknown.  Truer words were never spoken.

For more:  https://madisonarealymesupportgroup.com/2016/11/03/ld-not-in-australia-here-we-go-again/

https://madisonarealymesupportgroup.com/2017/07/25/brave-new-worlds-the-expanding-universe-of-lyme-disease/

https://madisonarealymesupportgroup.com/2017/08/14/canadian-tick-expert-climate-change-is-not-behind-lyme-disease/

https://madisonarealymesupportgroup.com/2017/08/05/cdc-maps-for-lyme-disease-not-accurate/

https://madisonarealymesupportgroup.com/2017/08/24/canine-maps-better-than-the-cdcs-in-predicting-lyme-disease/

https://madisonarealymesupportgroup.com/2016/09/24/arkansas-kids-denied-lyme-treatment/

https://madisonarealymesupportgroup.com/2017/03/02/hold-the-press-arkansas-has-lyme/

Three Things for Parents to Watch For Regarding TBI’s

https://www.lymedisease.org/3-things-watch-frid/  Sept. 18, 2017

3 Things to Watch For: Summer Flu, School Phobia, Abdominal Migraines
By Dr. Elena Frid

Frid-headshot-preferred-300x233

The summer is officially behind us and the school year is back in full swing. As we put the long summer days and warm summer nights behind us and get back in the academic saddle, I want to address some symptoms that you might not realize can be related to Lyme disease and associated co-infections.

Summer Flu
I often hear parents talk about the summer flu. This usually occurs in the middle of summer when young kids who are in camp or just spending the summer with their families develop a flu-like illness for a few days. Often the symptoms are vague, such as fevers, joint aches, muscle pain and weakness. The child may spend days in bed with recurrent spikes of fevers, headaches and decreased level of energy. This is often thought of as a viral infection.

It is important to know that half of people with Lyme will never notice a tick bite and more than half will not have a rash. Ruling out Lyme disease due to absence of a bull’s-eye rash is inaccurate and misleading. Especially if you live in an endemic area or have seen ticks on your property or on your pets, “summer flu” must be assessed for Lyme disease and associated co-infections.

I also urge families to educate themselves on the accuracy of the blood test given for Lyme disease. The test can be over 50% inaccurate, especially if blood is drawn immediately after exposure or months after the tick bite. I recommend either rechecking the blood work a number of times with your doctor (using the Western Blot technique not just ELISA), or using a specialty lab to assess for vector-borne illnesses. If misdiagnosed, the summer flu may resolve spontaneously, but can later develop into a persistent/tertiary Lyme illness that is difficult to treat.

Therefore, we need to be more vigilant about methods of prevention in both children and adults, as repeat insult to one’s immune system can lead to chronic and life-altering symptoms. For more information on various methods of prevention please visit my website www.drfrid.com.

School Phobia
Many children are diagnosed with school phobia, when they develop anxiety, depression, or OCD behavior which peaks at the onset of a school year. Starting a new school year is stressful for a child, which in turn can bring on various neuropsychiatric symptoms. Often, these symptoms are misdiagnosed as purely psychiatric disorders such as “school phobia.”

I am deeply concerned when I hear that diagnosis in a child who has multiple other complaints including pain syndrome, severe fatigue, headaches, cognitive impairment and much more. When these children see a physician, their testing many times comes back normal or vaguely abnormal and so they fall through the medical cracks and receive a psychiatric diagnosis.

If your child is complaining of multiple physical and neuropsychiatric symptoms – believe him/her. Have the child assessed by a neuropsychologist if he/she had a drop in IQ, impaired memory and concentration, decline in visual special skills or executive functioning.

Please note, if your child is also complaining of physical symptoms, he/she must be evaluated for systemic illnesses. Lyme disease and associated co-infections can certainly bring on many of the symptoms mentioned here and much more. Since Lyme disease is the fastest growing vector-borne illness in the United States and has been reported in all 50 states – we as parents should be vigilant and think of it even if the doctor doesn’t.

Abdominal Migraines
In my practice, at least 50% of children present with gastrointestinal complaints as one of the main symptoms of Lyme disease. They often have months of unexplained abdominal pain, with normal gastrointestinal workup. Symptoms of nausea, vomiting, diarrhea/constipation, food intolerances and weight loss or gain are quite common.

Children develop a very restricted diet, only able to eat a handful of food groups. Going out to dinner or preparing proper meals becomes extremely difficult, impacting the entire family. If your child has had a thorough gastrointestinal work up without any explanation as to what is causing these pronounced symptoms, I urge you to look into the possibility of Lyme disease. The bacteria can be very disruptive to the gut lining through direct invasion as well as inflammation of the GI tract.

These are only some of the symptoms that can be caused by Lyme and associated infections. Addressing them accurately and promptly will help change your child’s life tremendously for years to come.

Dr. Elena Frid, a board-certified neurologist and clinical neurophysiologist who practices in New York City, is a member of the International Lyme and Associated Diseases Society. Her website is elenafridmd.com. Follow her on Instagram, Facebook, and YouTube.

**Comment**

Once again Dr. Frid speaks candidly about serisously considering TBI’s (tick borne illness) in children with vague complaints.

Here a child’s main complaint was severe headaches:  https://madisonarealymesupportgroup.com/2017/08/12/lyme-disease-case-started-with-headaches/

Here a young lady was misdiagnosed with HIV:  https://madisonarealymesupportgroup.com/2017/08/13/diagnosed-with-hiv-14-year-old-really-had-lyme/

Another had severe leg pain, staph and ear infections, migraines, and anemia:  https://madisonarealymesupportgroup.com/2017/09/08/another-lyme-patient-benefits-from-iv-treatment/

Here a young girl has tick paralysis:  https://madisonarealymesupportgroup.com/2017/05/20/child-paralyzed-after-tick-bite/

It’s also important to note that Lyme (borrelia) is the rock star we all know by name; however, there are often other pathogens involved each with their own symptomology and treatment requirements.  This is why using doxycycline like napalm doesn’t work.  If doctors are not versed in this (and they aren’t), they will misdiagnose a child (or adult) for sure:  https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/  (BTW:  there’s way more than 6)  

Excellent warning – When Lyme isn’t caught early:  https://madisonarealymesupportgroup.com/2017/09/05/when-lyme-isnt-caught-early/

I could literally go on and on and on with similar but different stories.  What’s important to note here is that small children often do not have the verbal skills to express what they feel and where.  It’s up to parents to keep a watchful eye, and be educated.  Fight for your child.  Unfortunately, even though 40 years in, Lyme/MSIDS is still a politically incorrect disease with mainstream doctors more likely to disregard your child and state they are being lazy, or even accuse the parent of Munchausen syndrome by proxy, a psychiatric disorder wherein parents draw attention to themselves by faking illness in their child.  Some are accused of child abuse:  https://madisonarealymesupportgroup.com/2017/09/14/dutch-parents-accused-of-child-abuse-due-to-children-with-lyme-disease/

Also, Lyme/MSIDS can cause suicides and all sorts of psychiatric manifestations:  https://www.lymedisease.org/lyme-sci-teen-suicide/, https://madisonarealymesupportgroup.com/2017/06/20/suicide-lyme-and-associated-diseases/, https://madisonarealymesupportgroup.com/2017/04/11/hidden-invaders-infections-can-trigger-immune-attacks-on-kids-brains-provoking-devastating-psychiatric-disorders/   (A highly respected Wisconsin LLMD states 80% of his PANS patients have Lyme/MSIDS.)

Thankfully, more and more information and stories are being shared such as the ones in the links.  Please share these with family, friends, and other health professionals.  If this mountain is going to move, we have to do it.

For support for parents with children with Lyme/MSIDS:  https://groups.yahoo.com/neo/groups/lymeparents/info

Illinois 9th Lyme Disease Awareness Walk

https://lyme-support-network.ticketleap.com/9th-annual-lyme-disease-awareness-walk/

large

9th Annual Lyme Disease Awareness Walk

By Lyme Support Network
CITIZEN’S PARK
511 Lake Zurich Road, Barrington, IL 60010
SUNDAY, SEPTEMBER 24 2017
10:00 AM — 3:00 PM
GET TICKETS:  https://lyme-support-network.ticketleap.com/9th-annual-lyme-disease-awareness-walk/dates/Sep-24-2017_at_1000AM

A gathering of people, their friends & family effected by Lyme Disease.

More than a walk! Prizes, music, food, kid’s fun & info on Lyme & Tick-borne illness.

Online registration for the 2017 walk is now open!

Sign up before September 12th to be guaranteed an event bag.

Lyme Disease is epidemic in Lake County and surrounding areas! Join us for our 9th annual Lyme Disease Awareness Walk on Sunday, September 24th in Barrington, IL.

Help us continue to raise funds to support research, education, awareness and innovative treatments for Lyme disease and other tick-borne diseases.

This incredible event brings together folks from Illinois, Wisconsin and beyond.

The event begins with registration at 10:00am with the program and kick-off to the 2.5 mile walk starting at 11 AM.

We are very pleased to have the entire beautiful Citizens Park available to us, including the Jewel Tea Pavilion, so the event will be held rain or shine!

The Lyme Support Network is a non-profit service organization dedicated to making a difference by building awareness of Lyme Disease and other tick-borne illnesses within our community. Because our organization is run entirely by volunteers, individual and corporate donations are essential in supporting our efforts.

We hope that you can either walk with us or donate so we can raise funds to fight these debilitating and complicated diseases. Your support and/or donation of any size will help out tremendously.

The Lyme Support Network operates as a 501(c)(3) non-profit service organization, tax ID # 80-0547829.

Interested in being a sponsor? Please contact us for sponsorship opportunities.


The Future of Lyme Disease – Final Contagion Live Segment

 Contagion Live  Sept. 7, 2017  Approx. 10:30

Peter L. Salgo, MD: What are we looking for going forward 10 years from now? What is the future of Lyme disease management, whether or not it be testing improvements?

Robert C. Bransfield, MD, DLFAPA: I would think, eventually, you see a trend towards more DNA-based testing platforms that may evolve. I think, eventually, there would be better testing that would help. The question of vaccines, that has been something that people have been struggling with for a long time. One interesting thing is vaccines against ticks themselves, because there have been a lot of problems with the vaccines so far. I think that of those different things that are being considered, that’s probably the best option. So, it has been very hard to develop a vaccine. Just like a vaccine against the common cold. It may not be possible. I would love to see it happen.

Samuel Shor, MD, FACP: One of the major problems is, even if you have a good vaccine for Borrelia, what do you do about the co-infections? And more and more ticks are co-infected.

Leonard Sigal, MD: That’s why, going back to your anti-tick idea, there’s a wisdom commonly shared: the more erythema, the more redness and inflammation you develop at a tick bite site, the less likely you are to actually get infection.

Samuel Shor, MD, FACP: More robust immune response.

Leonard Sigal, MD: And so, that goes back to your comment. If you could come up with a tick saliva vaccine, not only would you cover Borrelia burgdorferi, but you’d also cover coinfections as well.

Robert C. Bransfield, MD, DLFAPA: And I also think there’s a trend towards looking in the microbiome— the tick microbiome, the human microbiome—and that’s part of disease. It’s not like you can ever just get rid of all infection in the body. It’s the microbiome that’s within us, and that’s, I think, becoming a broader area in psychiatry and general medicine with chronic illness: to look at chronic infections and the microbiome, and some of these infections are good for us.

Peter L. Salgo, MD: We’re going to get guideline changes going forward?

Patricia V. Smith: Yes. I think we need to get guideline changes, and the reason that we need to is because, even though I know the IDSA is coming out with their guidelines in early 2018, my understanding is they didn’t last time—and I’m guessing that they won’t this time—include anything for patients with chronic disease or post-treatment Lyme, whatever you want to call it. And so, that is very problematic, the same way with the CDC MMWR article. The way they have, in a little box in the side of the article, put in that they do not recommend any antibiotic treatment or IVIG treatment for chronic Lyme because, of course, we know chronic Lyme doesn’t exist. So, now you leave a whole plethora of patients out there without any kinds of options. They’re not allowed to have alternative medicine and they’re not allowed to have extended antibiotics, which are not alternative medicine. Tuberculosis patients get treated for 2 years with IV antibiotics.

Leonard Sigal, MD: And there’s a reason for that, Pat. There’s a reason for that, and that is the lack of really rigorous science in support of those approaches.

Patricia V. Smith: I agree with you.

Leonard Sigal, MD: What I’d like to see is cooperation between the 2 ends of the spectrum, proper studies.

Patricia V. Smith: I’m totally in favor of that.

Peter L. Salgo, MD: I need to stop right here. I’m going to go around and everybody is going to get a last word. You’re going to get it, too. Dr. Bransfield, start. This is your shot.

Robert C. Bransfield, MD, DLFAPA: So, William Osler, the father of medicine, once said, “To know syphilis is to know medicine.” But I think we could look at that in terms of Lyme disease, and to know Lyme disease, you really have to know not just medicine, but also psychiatry, entomology, epidemiology, immunology, psychoimmunology, rheumatology, and politics.

Leonard Sigal, MD: Throw cardiology in as well.

Robert C. Bransfield, MD, DLFAPA: And cardiology. You need a broad capability that’s beyond the training of most people. So, the big thing we have to add is some humility. We can’t have arrogance. We have to know that a lot of the answers to this are outside our field of specialty, so we have to have open dialogue, open communication like we’re having here, and that’s what will help resolve this.

Peter L. Salgo, MD: Dr. Shor?

Samuel Shor, MD, FACP: Well, it’s important, I think, to recognize that chronic active Borrelia infection exists. What is most contentious is this post-treatment component, which I’ll get to in a second. But what is often disregarded are those who never get diagnosed and are untreated. We have an expanding tick population, and the percentage of ticks are increasing that are actually infected. The majority of patients never recognize they’ve been bitten by a tick. There’s a large percentage of them who don’t have the hallmark feature EM rash, and if they do, it’s often in a hidden place, or it may be atypical. They present with common symptoms—summer flu. Then, throw in the post-treatment group that can potentially present in similar manners with chronic disease. We’ve already alluded to that there’s good evidence of persistence after requisite antibiotics. Not everybody who’s chronically ill after treatment has active infection, but I would argue that a modest percentage do. And so, we need to be empathetic in dealing with this chronic fatigue, chronic pain, and cognitive impairment, this complex group of individuals who, unfortunately, because of poor lab testing and the politicization of this condition, are often peripheralized.

Peter L. Salgo, MD: Dr. Sigal?

Leonard Sigal, MD: In clinical medicine, have an open mind and an open heart. To rephrase what you were saying, we have to have humility, absolutely. We don’t know everything. We have to be open to the possibilities of it being Lyme disease, being another infection, being something else entirely, being immune meditated or inflammatory mediated. You have to be aware of all the potential mechanisms, and you have to be humble in the sight of all these competing potentials. You have to have an open mind and ultimately, even if I can’t make a diagnosis, the person who’s sitting in front of me is suffering. And to show that person the door without any sense of what we’re going to do next is cruel and should not be the practice of any physician. So, an open mind, open heart, clinical practice, and better science. We need to stop arguing with each other, and we need to stop pointing fingers, and we need to be able to move on and say, ultimately, that the only important thing is the patients are suffering. Ergo, I agree: power, I agree; money, I agree. We have to throw out those things and get beyond ourselves and sit down and come up with the studies, mutually agreeable studies, that will allow us to come up with biomarkers; better sero-confirmatory tests, they’re not diagnostic tests; and better approaches to therapy. Anything short of that is an abdication of our primary responsibility, which is to practice scientific and empathic medicine.

Peter L. Salgo, MD: And I promised you the last word.

Patricia V. Smith: You did.

Peter L. Salgo, MD: And I’m keeping my promise. Go ahead.

Patricia V. Smith: I want to speak to the fact that, for many decades now, patients and advocates have been left out of this process of Lyme disease. And by that I meant they’ve been excluded. Other diseases have had committees for years that have sat in Washington, and they’ve sat with these working groups, and they’ve been able to have input on their diseases. Patients have been totally excluded. It’s very frustrating for them. It has caused, in my opinion, some of this bad science, because the educated patients know what kind of studies they need to help them with their disease. They just want to get better. They don’t care about these arguments, they want to get better. They’ve never been able to sit down like this.

So, finally, I’m pleased to say that last year we were successful for the first time, after a lot of opposition from the IDSA and others over the years, in getting legislation passed and included in the 21st Century Cures Act. That provides a working group that—there’s a working group now in Washington—only includes federal officials at the table. They have been making all the decisions for patients. That is really outrageous. And so now, patients, because of the way we set this up, will have a seat at the table, perhaps an advocate, or a member of a Lyme organization will have a seat. Our treating physicians who have never had any input into this process—guess what they’re going to be doing. They’re going to be working with all the different agencies to find out what the resources are that are available for research, what kinds of studies need to be done, and it’s also going to be done in a transparent fashion, whereas now it’s behind closed doors. No one knows what research is selected until after it’s done, and then you have no say in the matter. I just say for Lyme patients, the time has come when they will get a seat at the table, to be able to have input about their disease.

Peter L. Salgo, MD: Alright. Well, thank you all for being here. You can all take off your flak jackets and your helmets. This has been a tremendous discussion, one of the best in my career, and I’m glad we all got at the same place at the same time to discuss what has been one of the most contentious issues in modern American medicine. On behalf of our panel, I want to thank you for joining us, and I hope you found this Peer Exchange® discussion to be useful and informative. I’m Dr. Peter Salgo, and I’ll see you next time.

The entire Contagion Live Series:
3rd Segment:  
7th Segment:  
8th Segment: