Archive for the ‘Activism’ Category

Cataract Resident Advocates For Individuals Struggling With Lyme Disease

https://www.monroecountyherald.com/news/cataract-resident-advocates-individuals-struggling-lyme-disease

Cataract resident advocates for individuals struggling with Lyme disease

Alicia Cashman

Cataract resident Alicia Cashman, a Lyme disease patient, advocate and leader with Madison Lyme Support Group, is passionate about the cause as she herself has been fighting the battle for over a decade after a tiny tick changed her and her husband’s lives.

Most people don’t know that a tick can contain many pathogens. Cashman prefers the term MSIDS, or Multi Systemic Infectious Disease Syndrome, over Lyme Disease as it is almost always far more than just borrelia, the causative agent of Lyme disease.

“Due to the synergistic effects of these pathogens, treatment is often far more complex and longer than the CDC’s treatment guidelines of 21 days of doxycycline and that particular mono therapy rarely works unless you catch it early,” she said. “We saw neither tick nor rash and less than 30 percent do, but we tested positively on the Extended Western Blot from Igenex Labs in California, which is one of the few labs that uses a far more sensitive testing.”

As stated earlier, Lyme disease is caused by bacteria called Borrelia. There are 100 different strains of Borrelia in the United States and 300 worldwide. Current CDC testing only tests for one strain, according to Cashman. (See link for article)

____________________

**Comment**

I’m thankful the staff writer didn’t shy away from the polarization in the medical community, research bias, conflicts of interest, or the fact this is probably sexually transmitted.

We need the truth if we ever expect to move forward.

I never know what the outcome of these interviews will be, but I’m happy with this one.  Good, honest information with very practical advice.

For more:

Time Sensitive: Hearing on Vaccine Freedom Bills Wed. June 2, 2021, 10 a.m. WI State Capital

URGENT: The Assembly Committee on Constitution and Ethics has scheduled a hearing on vaccine freedom bills AB 299, AB 303, AB 309, AB 316, and AB 347. The hearing is scheduled for Wednesday, June 2, at 10 am and will be held in the Wisconsin State Capitol at 417 North (GAR Hall). The John Birch Society encourages members to attend tomorrow’s hearing and testify in support of the bills listed above.

Members of the Wisconsin Legislature are seeking to pass legislation protecting citizens from forced vaccinations.

Several bills have been introduced and would robustly protect individual freedom with regard to vaccinations. One of these is SB 4, which prevents both local officials and the Department of Health Services (DHS) from requiring people to receive COVID-19 vaccines. Although Governor Tony Evers vetoed the Assembly companion, AB 23, the Senate bill can still pass.

Additionally, SB 5 and AB 25, prohibits employers from forcing their employees to receive any of the COVID-19 vaccines. Meanwhile, AB 299 would prohibit government and private entities from requiring a COVID vaccine in order to receive services, while AB 303 would prohibit businesses from discriminating against customers based on whether or not they have been vaccinated.

Similarly, AB 309 would prohibit multiple forms of discrimination based on one’s vaccination status, while AB 316 prevents government discrimination against those who refuse to take the coronavirus vaccine. Last, but not least, AB 347 ensures that students attending the University of Wisconsin System are not required to take the coronavirus vaccine in order to attend.

In addition to the general, and real, risk of the government mandating coronavirus vaccinations to increase the inoculation rate, some Wisconsin employers are already laying off staff for refusing to take the vaccine.

Multiple reasons exist for why it is important to oppose forced vaccinations. For one, individuals might have religious, conscientious, or other personal reasons for wishing not to be vaccinated, making forced vaccination a direct infringement on the U.S. Constitution’s First Amendment. Additionally, potential health risks of vaccines in general – and of a COVID-19 vaccine specifically, considering its rapid development – make it even more important to keep them voluntary. Mandatory vaccinations would be yet another step in the steady encroachment of government over every aspect of our daily lives.

Since the COVID-19 pandemic began, the federal, state, and local governments have exceeded their constitutional limitations in a variety of areas. It is imperative that citizens push back, rein in these government entities, and ensure they cease to violate our constitutional liberties.

Enacting SB 4, SB 5, AB 25, AB 299, AB 303, AB 309, AB 316, and AB 347 would be a positive start in Wisconsin.

Urge your state representative and senator to pass these vaccine freedom bills!

If you can’t attend in person, let your representatives here:

Uncensored Truth Tour Coming to Milwaukee June 26, 2021

https://www.aflds.org/agenda  Register Here (Other dates and locations listed)

The Uncensored Truth Tour

Physicians and Patients Standing Up for Science, Freedom, and Common Sense

Attendance is FREE when you Register in Advance!

About the Event

America’s Frontline Doctors takes the truth directly to the people, with a cross-country road tour headlined by AFLDS.org founder Dr. Gold delivering “The Religion of Public Health”, a profound diagnosis of 2020’s viral propaganda, and also featuring additional AFLDS physicians and attorneys at select venues.

The Uncensored Truth Tour is a relentless force of scientific and legal facts fighting back against censorship, chaos, and the undeniable slide towards communism that lurks beneath the tyrannical lockdowns of governmental “public health” policy.

Milwaukee, WI

DR. SIMONE GOLD

Doors at 5:30pm
SATURDAY, JUNE 26, 2021

CDC Lying Again. Tuttle Drops the Mic

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/29105701?

The US Centers for Disease Control is lying to the public about Lyme disease!

MAY 24, 2021 — 

As promised from the previous petition update, the following is a critique of Dr. Grace Marx’s, PowerPoint presentation which clearly shows that our public health officials are lying to us. You can voice your opinion and send her an email:  lwx1@cdc.gov

Dr. Marx contact info: (photo is from this link)

https://www.eventscribe.com/2019/IDWeek/ajaxcalls/AccountInfo.asp?efp=Q0NRVktHSkw2ODg2&userShareID=36678593&rnd=0.8305856

———- Original Message ———-

From: CARL TUTTLE <runagain@comcast.net>
To: “lwx1@cdc.gov” <lwx1@cdc.gov>, “coca@cdc.gov” <coca@cdc.gov>
Cc: All members of the NH Lyme Disease Study Commission,”governorsununu@nh.gov” governorsununu@nh.gov
Date: 05/22/2021 2:16 PM
Subject: Re: Lyme Disease Updates and New Educational Tools for Clinicians

Dr. Marx,

As anticipated, the Clinician Outreach and Communication Activity (COCA) Webinar failed to mention the ten important facts I pointed out in my email dated May 15th five days prior to your presentation.

After reviewing the slides of your presentation at the following link, I found additional areas of concern:

Lyme Disease Updates and New Educational Tools for Clinicians
https://emergency.cdc.gov/coca/ppt/2021/052021_Lyme_Disease_Slides.pdf?fbclid=IwAR05dtD4eswvd_8WLpBQkp_1j-A2iME1WRdWJmcGTaxehWdIZN5FC2KcpAA

_____________________________________________________________________________________________________________________
Page# 11

Transmission occurs:

  • After an infected tick has been attached for at least 24hrs
  • Most transmission occurs after 36 hours
Carl Tuttle’s comments:  Rapid transmission has been reported in under 4hrs  [1, 2, 3, 4]

Page# 15

95% of reported Lyme disease cases are from 15 states and D.C.

Carl Tuttle’s comments:  Quest diagnostics is reporting positive Lyme tests in all fifty states. [5]

Page# 21

  • A single dose of doxycycline can lower the risk of Lyme disease
Carl Tuttle’s comments:  Single dose Doxycycline after tick bite as prophylaxis against Lyme disease failed 80% of the time in the mouse model so why would this be recommended in humans? [6]

Page# 25

  • Most tick bites do NOT transmit disease, so antimicrobial PEP is not routinely recommended.
Carl Tuttle’s comments:   77% of the ticks tested in the town of Litchfield, NH were carrying tick-borne disease as reported by a 2009 UMass Tick Study [7] so assuming that disease will not be transmitted is like playing Russian roulette with the public’s health. Front line clinicians in this Lyme endemic region who are witnessing the devastation first hand will offer the patient thirty days of minocycline after a tick bite.

Page# 32

  • The LYMERix vaccine was available between 1998 and 2002
  • Safe and effective
  • Pulled from the market in 2002
Carl Tuttle’s comments:  The LYMErix vaccine was pulled due to adverse reactions [8]and class action lawsuit:

VACCINES AN-D RELATED BIOLOGICAL PRODUSTS ADVISORY COMMITTEE
Advisory Committee Meeting: l/31/01
https://www.dropbox.com/s/sodqs3pdeeesktf/Sheller%20Lymerix.pdf?dl=0

Below is communication with the attorney who handled the LYMErix lawsuit.

“The people who have contacted us were, prior to vaccination with LYMErix, healthy, active and energetic. Indeed, the very reason they sought the LYMErix vaccine was their desire to preserve their healthy, active lifestyle. However, what they experienced was a dramatic degradation of their health and quality of life. As will be described below, these previously healthy individuals are now afflicted with painful, at times debilitating arthritic symptoms, including joint pain and swelling, as well as extremely severe Lyme-disease-like symptoms which have persisted to this day.”  -Stephen A. Sheller, Esq

Page# 37

Typical Lyme Disease Manifestations

  • Three months or more; Arthritis [Late stage]
Carl Tuttle’s comments:  What stage of Lyme disease results in disability; patients in wheelchairs?  You can become horribly disabled or die [9] from Lyme disease and routinely denied Social Security Disability Compensation and yet the public knows nothing about this stage of disease.

Page# 38

  • Erythema migrans (bulls-eye rash) 70%
Carl Tuttle’s comments:  The State of Maine DOH reported incidence of rash less than 50% as mentioned in my previous email.

Page# 45

  • Blacklegged ticks may also transmit pathogens that cause:
    Anaplasmosis
    Babesiosis
    Ehrlichiosis
    Borrelia miyamotoi disease
    Borrelia mayonii (Lyme disease)
    Powassan virus disease
Carl Tuttle’s comments:  Why isn’t the CDC recommending a “tick panel” to check for all of these pathogens?

Page# 48

  • CDC recommends diagnostic tests for Lyme disease that have been evaluated and cleared by the FDA. Two-step serologic tests are the only FDA-cleared test for Lyme disease.
Carl Tuttle’s comments:  Why after nearly forty years since the discovery of Lyme do we not have an accurate test to detect Lyme in all stages of disease???

Page# 49

  • Two-Step Lyme Disease Serologic Testing
  • A NEGATIVE Elisa means NEGATIVE
Carl Tuttle’s comments:  The more sensitive Western blot is only ordered after a positive Elisa lab result and it is used to rule out a FALSE POSITIVE Elisa.

When a NEGATIVE Elisa is found the Western blot is never ordered to rule out a FALSE NEGATIVE. So basically a NEGATIVE Elisa is 100% reliable whereas a POSITIVE Elisa is never reliable. How can this test be reliable in one instance and not another? Physicians are not allowed to order the Western Blot after a NEGATIVE Elisa and this practice is criminal. The system of using the Elisa as first line testing is completely flawed.

“If false results are to be feared, it is the false negative result which holds the greatest peril for the patient.” – Dr. Allan MacDonald

Page# 51

Western blot for Lyme Disease

  • Positive test requires at least 2 out of 3 [IgM] bands
  • Positive test requires at least 5 out of 10 [IgG] bands
Carl Tuttle’s comments:  Interpretation of the Western immunoblot is an area of significant confusion. Strict criteria were created in 1994 for surveillance of Lyme disease and only those patients who met this strict case definition were reported to the CDC. So if you did not meet those criteria your Western blot stated NEGATIVE.

Under the Infectious Conditions for Public Health Surveillance page, the Centers for Disease Control updated its Lyme Case Definition  in 2011 stating the following:

“This surveillance case definition was developed for national reporting of Lyme disease; it is not intended to be used in clinical diagnosis”

Physicians who treat Lyme disease exclusively recognize that it is not necessary to have five positive Western blot IgG bands or two IgM bands in order to diagnose Lyme disease. Those guidelines were strictly developed for surveillance purposes only.

Page# 59

Test Sensitivity by Manifestation of Lyme Disease

  • Early Localized (bulls-eye rash) -POOR
  • Early Disseminated -VERY GOOD
  • Late Disseminated -EXCELLENT
Carl Tuttle’s comments: Serology for Lyme disease is no better than a coin toss [10, 11] and is responsible for unimaginable pain and suffering.

2010 Complaint Letter to Jose T. Montero, MD, Director NH DHHS
https://www.dropbox.com/s/3pfjav6mtj50hkd/2010%20Letter%20Jose%20T.%20Montero%2C%20MD%2C%20Director.pdf?dl=0

Page# 63

Each stage of disease can be treated effectively with antibiotics.

Carl Tuttle’s comments:  There are hundreds of references to failed treatment of the one-size-fits-all IDSA Lyme treatment guideline [12,13] so why does the CDC continue to refuse to recognize this problem leaving hundreds of thousands (if not millions worldwide) in a debilitated state?

Treatment Delays Increase Risk of Persistent Illness in Lyme Disease (Johns Hopkins)
https://www.hopkinslyme.org/news/treatment-delays-increase-risk-of-persistent-illness-in-lyme-disease/

Page# 66

Treatment for Neurologic Lyme Disease

  • 2-3 weeks duration in all cases
Carl Tuttle’s comments:  I have never met any Lyme patient horribly disabled from neurologic Lyme disease who returned to baseline health with 2-3 weeks of antibiotics.

One high profile case comes to mind:

NEWS: Former patient who testified as a child about Lyme disease recalls encounter with Sen. Ted Kennedy
https://www.lymedisease.org/186/

Evan White testified from his wheelchair in 1993 at Senator Ted Kennedy’s Hearing, Washington DC

Excerpt:

“No one could hear or feel the moment of that child and not be moved,” Kennedy explained to the [Boston] Globe at the time. Anyone who wasn’t moved, he said, “hasn’t got a heart.”

Based on the summary below it appears that it took years of antibiotics, not weeks to treat Evan’s disability. Had he not met Dr. Joseph Burrascano, Evan would have been a burden on the Social Security program today through “therapeutic nihilism.”
 
Late Neurologic Lyme Is Reversible: Evan White

Post by CaliforniaLyme » Wed 31 Oct 2007 16:46

https://www.lymeneteurope.org/forum/viewtopic.php?t=147

Page# 72

Lyme Disease Treatment Considerations

  • Pregnant or breastfeeding patients:
    • doxycycline in pregnant or breastfeeding woman has not been thoroughly studied
Carl Tuttle’s comments:  Where is the section on congenital transmission of Lyme disease which has been identified dating back to 1985? [14]

Page# 74

Post Treatment Consideration

  • Most patients with Lyme disease recover completely within WEEKS to MONTHS after a course of antibiotic treatment.
Carl Tuttle’s comments: This statement has been propagated by the CDC for over thirty years while the horribly disabled continue to go unrecognized .

Page# 74

Post Treatment Considerations

  • About 1 in 20 treated patients may experience symptoms more than six months after treatment.
Carl Tuttle’s comments:  Once again that number was pulled out of a hat and propagated by the CDC for over thirty years while researchers at Johns Hopkins found 35% of acute Lyme disease patients who were treated with the IDSA’s short course of antibiotics were found to meet the case definition of “Post Lyme Disease Syndrome” at six months:
 

Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here?
http://www.lymemd.org/pdf/aucott_et_al_qol_research.pdf

Page# 75

Post Treatment Considerations

  • Additional prolonged antibiotics have not been shown to improve long-term outcomes
  • long-term antibiotic therapy has the potential to cause serious side-effects…
  • More than two courses of antibiotics have NOT been recommended for the treatment of Lyme disease.
Carl Tuttle’s comments:  The Klempner NIH antibiotic trials were cut short at three months. Evan White would still be in a wheelchair today or deceased if his treatment ended after only three months.

Two Controlled Trials of Antibiotic Treatment in Patients with Persistent Symptoms and a History of Lyme Disease
http://www.nejm.org/doi/full/10.1056/NEJM200107123450202#article_references#t=references

Second comment: Doxycycline for Acne has been prescribed long term for decades but when Lyme is involved, suddenly we have a double standard.

____________________________

Dr. Marx,

It would appear that you are not a front-line treating physician for Lyme disease. The majority of our public health officials have never treated the late-stage Lyme patient and therefor have no practical experience whatsoever while propagating the disinformation as I have pointed out.

It is blatantly obvious that the CDC is now grooming its younger generation of Medical Epidemiologists in the practice of suppressing the truth, facts and scientific references in order to maintain the illusion that our public health officials have everything under control.

Carl Tuttle
Hudson, NH

Cc: All members of the NH Lyme Study Commission
Governor Chris Sununu

REFERENCES (Please read them!)

1. Clinical evidence for rapid transmission of Lyme disease following a tick bite

https://www.sciencedirect.com/science/article/abs/pii/S0732889311004159?via%3Dihub

2. B. Patmas, MA, Remora, C. Disseminated Lyme Disease After Short-Duration Tick Bite. JSTD 1994; 1:77-78

https://www.lymedisease.org/hard-science-on-lyme-ticks-can-transmit-infection-the-first-day/

3. Lyme borreliosis: a review of data on transmission time after tick attachment

Michael J Cook
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4278789/

The claims that removal of ticks within 24 hours or 48 hours of attachment will effectively prevent LB are not supported by the published data, and the minimum tick attachment time for transmission of LB in humans has never been established.

4. Regarding Tick Attachment Times –

https://history.nih.gov/display/history/Burgdorfer%2C+Willy+1986

there are about 5 to 10 percent of infected ticks that have a generalized infection, including salivary glands and saliva at the time of attachment. In such cases, transmission of spirochetes would and does occur immediately at time of attachment.” —Willy Burgdorfer

5. LYME SCI: Lyme has been found in all 50 states and is on the rise

https://www.lymedisease.org/lymesci-lyme-all-states/#:~:text=Quest%20Diagnostics%20has%20released%20its,cases%20continues%20to%20rise%20nationwide

6. A sustained-release formulation of doxycycline hyclate (Atridox) prevents simultaneous infection of Anaplasma phagocytophilum and Borrelia burgdorferi transmitted by tick bite
 
https://www.dropbox.com/s/jc0h9g9arjhc8l1/Zeidner%202008.pdf?dl=0

7. Correlation between Tick Density and Pathogen Endemicity, New Hampshire
https://wwwnc.cdc.gov/eid/article/15/4/08-0940_article

8. LymeRix Vaccine Victim’s Stories
https://www.dropbox.com/s/5ikfgocui4hk7h9/LymeRix%20Victims.pdf?dl=0

9.  Deaths From Lyme Disease Compiled by: John D. Scott, Research Scientist 17 April 2018
 
https://www.dropbox.com/s/eo794dx7zspc1ln/Ld%20deaths.doc?dl=0

10. Two-Year Evaluation of Borrelia burgdorferi Culture and Supplemental Tests for Definitive Diagnosis of Lyme Disease
 
Peggy Coulter , 1   Clara Lema , 1   Diane Flayhart , 1   Amy S. Linhardt , 1   John N. Aucott , 2   Paul G. Auwaerter , 2 and   J. Stephen Dumler  1, *

Published 2005

Comparisons with qualitative clinical assessments

“Overall, initial serologic tests agreed with possible or probable clinical Lyme disease diagnosis in only 50% (40/80) of cases.” [COIN TOSS]

11. Commercial test kits for detection of Lyme borreliosis: a meta-analysis of test accuracy
 
Michael J Cook   1 ,   Basant K Puri   2

Sensitivity for each test technology varied from 62.4% for Western blot kits, and 62.3% for enzyme-linked immunosorbent assay tests, to 53.9% for synthetic C6 peptide ELISA tests and 53.7% when the two-tier methodology was used.  [COIN TOSS]

12. 700 articles LYME EvidenceofPersistence-V2
 
https://www.dropbox.com/s/n09sk90eo6xz7ua/700%20articles%20LYME%20EvidenceofPersistence-V2.pdf?dl=0

13. Lyme borreliosis: diagnosis and management

https://www.bmj.com/content/369/bmj.m1041/rr-1

14. Congenital Transmission of Lyme
 
https://www.dropbox.com/s/xlju8w25phkypy0/Congenital%20Transmission%20of%20Lyme.pdf?dl=0

_______________________

**Comment**

A picture is worth 1,000 words:
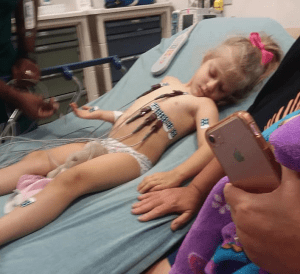
child-300x274

This is what an “insignificant” tick bite looks like and why all of this matters.

If You’ve Had COVID, Please Don’t Get Vaccinated

https://articles.mercola.com/sites/articles/archive/2021/05/24/delay-vaccination-for-people-with-covid-19-infections.aspx?  Interview with Dr. Noorchashm in Link

If You’ve Had COVID, Please Don’t Get Vaccinated

Analysis by Dr. Joseph MercolaFact Checked  May 24, 2021
STORY AT-A-GLANCE
  • An international survey of 2,002 people found that people who had previously had COVID-19 experienced “significantly increased incidence and severity” of side effects after the COVID-19 vaccine
  • Dr. Hooman Noorchashm has repeatedly warned the FDA that “clear and present danger” exists for those who have had COVID-19 and subsequently get vaccinated
  • At issue are viral antigens that remain in the body after a person is naturally infected; the immune response reactivated by the COVID-19 vaccine may trigger inflammation in tissues where the viral antigens exist
  • The inner lining of blood vessels, the lungs and the brain may be particularly at risk of such inflammation and damage, which could lead to major thromboembolic complications
  • Noorchashm believes that people should be screened for SARS-CoV-2 viral proteins prior to COVID-19 vaccination, while vaccination should be delayed for people with symptomatic or asymptomatic COVID-19 infections, as well as those who have recently recovered from the virus

In their race to vaccinate the entire U.S. adult population, health officials are urging everyone to get a COVID shot, regardless of whether or not they’ve already been infected with SARS-CoV-2, the virus that causes COVID-19, and spending billions of dollars in taxpayer funded propaganda to convince people to get the vaccine.

This is an important distinction, however, with at least one scientist warning the U.S. Food and Drug Administration that “clear and present danger” exists for those who have had COVID-19 and subsequently get vaccinated.

That scientist — Dr. Hooman Noorchashm, a cardiac surgeon and patient advocate — warned the FDA that prescreening for SARS-CoV-2 viral proteins may reduce the risk of injuries and deaths following vaccination, as the vaccine may trigger an adverse immune response in those who have already been infected with the virus.1

Unfortunately, health agencies continue to assert that everyone should get vaccinated, even if they’ve already acquired natural immunity via previous infection.

CDC: Get Vaccinated Even if You’ve Had COVID

The U.S. Centers for Disease Control and Prevention admits that it’s rare to get sick again if you’ve already had COVID-19. Despite this, they say those who have recovered from COVID-19 should still get vaccinated:2

“You should be vaccinated regardless of whether you already had COVID-19. That’s because experts do not yet know how long you are protected from getting sick again after recovering from COVID-19. Even if you have already recovered from COVID-19, it is possible — although rare — that you could be infected with the virus that causes COVID-19 again.”

Your immune system is designed to work in response to exposure to an infectious agent. Upon recovery, you’re typically immune to that infectious agent. This is why, for instance, proof of prior diagnosis with chickenpox, measles and mumps is allowed instead of vaccination to enter most U.S. public schools3 — once you’ve had the disease and recovered, you’re immune.

If you’ve had COVID-19, you have some level of immunity against the virus. It’s unknown how long it lasts, just as it’s unknown how long protection from the vaccine lasts. According to the Public Health Agency of Sweden:4

“If you have had COVID-19, you have some protection against reinfection. This means that you are less likely to become infected and seriously ill, and less likely to infect others if you are exposed to the virus again.

Over time, the protection that you get after an infection wanes and there is an increased risk of getting infected again. At present, we estimate that the protection after having had COVID-19 lasts at least six months from the time of infection.”

People With Prior COVID Have More Vaccination Side Effects

An international survey of 2,002 people who had received a first dose of COVID-19 vaccine found that people who had previously had COVID-19 experienced “significantly increased incidence and severity” of side effects after the COVID-19 vaccine.5 Those who had previously had COVID-19 had a greater risk of experiencing any side effect, along with the following, specifically:

Fever

Breathlessness

Flu-like illness

Fatigue

Local reactions

Severe side effects leading to hospital care

The mRNA COVID-19 vaccines were linked to a higher incidence of side effects compared to the viral vector-based COVID-19 vaccines, but the mRNA side effects tended to be milder, local reactions. Systemic reactions, such as anaphylaxis, flu-like illness and breathlessness, were more likely to occur with the viral vector COVID-19 vaccines.

According to the researchers, the findings should prompt health officials to reevaluate their vaccination recommendations for people who’ve had COVID-19:6

“People with prior COVID-19 exposure were largely excluded from the vaccine trials and, as a result, the safety and reactogenicity of the vaccines in this population have not been previously fully evaluated. For the first time, this study demonstrates a significant association between prior COVID19 infection and a significantly higher incidence and severity of self-reported side effects after vaccination for COVID-19.

Consistently, compared to the first dose of the vaccine, we found an increased incidence and severity of self-reported side effects after the second dose, when recipients had been previously exposed to viral antigen.

In view of the rapidly accumulating data demonstrating that COVID-19 survivors generally have adequate natural immunity for at least 6 months, it may be appropriate to re-evaluate the recommendation for immediate vaccination of this group.”

Surgeon Warns of Immunological Dangers, Blood Clots

Noorchashm has written multiple letters to the FDA, warning them that people should be screened for SARS-CoV-2 viral proteins prior to COVID-19 vaccination. Without such screening, he wrote in one letter to the FDA, “this indiscriminate vaccination is a clear and present danger to a subset of the already infected.”7

He describes the case of 32-year-old Benjamin Goodman of New York, who died within one day of receiving the Johnson & Johnson COVID-19 vaccine.

“There will be many more in the coming months as we carelessly and indiscriminately vaccinate the already infected, millions a day … It is a near certainty,” he continued.8 At issue are viral antigens that remain in the body after a person is naturally infected.

The immune response reactivated by the COVID-19 vaccine may trigger inflammation in tissues where the viral antigens are present. The inner lining of blood vessels, the lungs and the brain may be particularly at risk of such inflammation and damage.9 According to Noorchashm:10

“Most pertinently, when viral antigens are present in the vascular endothelium, and especially in elderly and frail with cardiovascular disease, the antigen specific immune response incited by the vaccine is almost certain to do damage to the vascular endothelium.

Such vaccine directed endothelial inflammation is certain to cause blood clot formation with the potential for major thromboembolic complications, at least in a subset of such patients. If a majority of younger more robust patients might tolerate such vascular injury from a vaccine immune response, many elderly and frail patients with cardiovascular disease will not.”

What’s more, Noorchashm quotes one of his previous medical school professors, who said, “the eyes do not see what the mind does not know.” In the case of a vaccine-induced antigen specific immune response, which may trigger thromboembolic complications 10 to 20 days after vaccination, including in those who may already be elderly and frail, the reaction isn’t likely to be registered as a vaccine-related adverse event.

Immediately Delay Vaccination for These Key Groups

In his repeated letters to the FDA, Noorchashm suggests that the FDA “immediately and at the very minimum” delay COVID-19 vaccination for people with symptomatic or asymptomatic COVID-19 infections, as well as those who have recently recovered from the virus.

Because so many cases are asymptomatic, he recommends clinicians “actively screen as many patients with high cardiovascular risk as is reasonably possible, in order to detect the presence of SARS-CoV-2, prior to vaccinating them.”11 As it stands, Noorchashm points out that by ignoring what he believes to be an imminent risk for a sizable minority of people, the FDA’s credibility, and that of the mass vaccination campaign in general, is at grave risk:12

“Can you imagine if the public, without having received any real warning from FDA, becomes aware of an increasing number of such vascular/thromboembolic complications? What do you suppose will happen to the level of ‘vaccine hesitancy’ then?

And, what kind of accountability do you think the public will demand from our experts and federal regulators — especially if they knew, or should have known, that this immunological danger might exist?

The aim of benefiting the majority of our public and saving the nation from this pandemic by quick and aggressive vaccination is an ethically sound one — but where we know of real or likely risks of harm and mortality, we ought to mitigate the risks to those in potential harm’s way.

So doing is the only reasonable, ethical, and likely legal option you can pursue as public health regulators — for in America, we no longer sacrifice the lives of minority subsets of people for the benefit of the majority.”

At least 62 cases of myocarditis, or heart inflammation, in people who received the Pfizer COVID-19 vaccine are being investigated by the Israel Health Ministry. Most of the cases occurred in men under the age of 30 who were in good health, and two deaths have been reported as a result.13,14

No Proof of Efficacy in People Who’ve Had COVID-19

In a high-profile report issued by the CDC’s Advisory Committee on Immunization Practices, 15 scientists stated that the Pfizer-BioNTech COVID-19 vaccine had “consistent high efficacy” of 92% or more among people with evidence of previous SARS-CoV-2 infection.15

But according to Rep. Thomas Massie, R-Ky, “That sentence is wrong.”

There is no efficacy demonstrated in the Pfizer trial among participants with evidence of previous SARS-CoV-2 infections and actually there’s no proof in the Moderna trial either.”16 In France, the health body la Haute Autorité de Santé (HAS) does not recommend routinely vaccinating those who have already recovered from COVID-19, stating:17

“At this stage, there is no need to systematically vaccinate people who have already developed a symptomatic form of Covid-19 unless they wish to do so following a decision shared with the doctor and within a minimum period of time. 3 months from the onset of symptoms.”

When Massie realized that vaccination didn’t change the risk of infection among people who’ve had COVID-19, he was alarmed and contacted the CDC directly, recording his calls.

“It [the CDC report] says the exact opposite of what the data says. They’re giving people the impression that this vaccine will save your life, or save you from suffering, even if you’ve already had the virus and recovered, which has not been demonstrated in either the Pfizer or the Moderna trial,” Massey says in a “Full Measure” report.18

CDC Allows Misinformation to Continue

Massie spoke with multiple officials on numerous occasions, who acknowledged the misinformation and implied that it would be fixed.19,20 It wasn’t until Massie’s final call with the CDC, to deputy director Dr. Anne Schuchat, that it was acknowledged that a correction was necessary.

“As you note correctly, there is not sufficient analysis to show that in the subset of only the people with prior infection, there’s efficacy. So, you’re correct that that sentence is wrong and that we need to make a correction of it. I apologize for the delay,” Schuchat said. January 29, 2021, the CDC did finally issue a correction, which reads:21

“Consistent high efficacy (≥92%) was observed across age, sex, race, and ethnicity categories and among persons with underlying medical conditions. Efficacy was similarly high in a secondary analysis including participants both with or without evidence of previous SARS-CoV-2 infection.”

Instead of fixing the error, Massie believes the wording just phrases the mistake in a different way and still misleadingly suggests vaccination is effective for those previously infected.22 Meanwhile, increasing numbers of breakthrough COVID-19 cases among the fully vaccinated are being reported, which the CDC has been reporting.

As of April 26, 2021, there have been 9,245 reported cases of COVID-19 in fully vaccinated individuals, including 132 deaths.23 Note this is not total deaths from the vaccine, which is rapidly approaching 4,000.

However, May 14, 2021, the CDC announced it will no longer report breakthrough cases unless they involve hospitalization or death,24 which will obscure the actual number of breakthrough cases occurring, artificially driving down rates and making the vaccines appear to be more effective.

The CDC also changed recommendations on PCR tests for the fully vaccinated, which will further drive down the appearance of breakthrough cases by making them less likely to “test positive.”

PCR tests recommended by the WHO used to be set to 45 cycle thresholds (CTs),25 yet the scientific consensus has long been that anything over 35 CTs renders the test useless,26as the accuracy will be extremely low, with false positives artificially driving up case numbers.

In April 2021, the CDC recommended the CT be lowered to 28, but only for people who are fully vaccinated.27 Under this guidance, someone with a CT of 30 would not be considered to have COVID-19 if they were fully vaccinated, but if they were not, then their test would be “positive.” 

This is beyond obvious that they are rigging the system to create data that fit their fake narrative, which is pushing the entire population to get a vaccine they don’t need, will harm or kill them and which will generate tens of billions of dollars in annual recurring revenue for the drug companies.

In return, the drug companies have no legal risk for any complications, adverse effects or deaths and are given billions of dollars in free advertising from the U.S. taxpayers to get this dangerous gene therapy.

The Big Lie — Natural Infection Isn’t Adequate

Why is it that the media continue to promote the fake narrative that natural immunity — the type acquired by getting infected by and recovering from a virus — isn’t as powerful or long-lasting as vaccine-acquired immunity?28,29 Do you think it might be to support vaccine sales?

Did they forget that COVID-19 vaccines aren’t intended to be a long-term solution, and have NEVER been shown to provide immunity benefits? The original warp speed test only showed reduced symptoms.

Pfizer’s CEO Albert Bourla exacerbated this charade by stating that not only will people need a third booster dose of COVID-19 vaccine within 12 months of being fully vaccinated, but annual vaccination will probably be necessary.30

Robust natural immunity has been demonstrated, however, for at least eight months after infection in more than 95% of people who have recovered from COVID-19.31,32 A Nature study also demonstrated robust natural immunity in people who recovered from SARS and SARS-CoV-2.33

There continue to be many unanswered questions surrounding COVID-19 vaccines, many of which most of the public has never heard of, such as imprinting and Th2 immunopathology. If you choose to get a COVID-19 vaccine, you’re participating in a giant experiment, acting as a guinea pig to see what will ultimately bear out.

That being said, if you or someone you love have received a COVID-19 vaccine and are experiencing side effects, be sure to report it. Children’s Health Defense (CHD) is calling on all who have suffered a side effect from a COVID-19 vaccine to do three things:34

  1. If you live in the U.S., file a report on VAERS
  2. Report the injury on VaxxTracker.com, which is a nongovernmental adverse event tracker (you can file anonymously if you like)
  3. Report the injury on the CHD website

________________________

For more:

“You see it in each country, it’s the same: the curve of vaccination is followed by the curve of deaths.  I’m following this closely and I a doing experiments at the Institute with patients who became sick with Corona after being vaccinated. Luc Montagnier, French virologist

  • The group Doctors For COVID Ethics also recently wrote a paper where they state COVID injections are “needless, ineffective and dangerous.” They delivered notices of liability for COVID-19 “vaccine” harms and deaths to every member of the European parliament.
Please educate yourself on the backstory of COVID.