Information Doctors Have Died For with Dr. Carrie Madej
October 11th, 2021
Dr. Madej is a highly credentialed doctor who has been literally had to flee the country for her life. She is back now with a vengeance and shows us what is in the vaccines. She takes us under her microscope to show us what is really go on from hydrogel to computer chips.
When I published my study on pathogenic priming in April, 2020, it was meant as a warning. The evidence was in from past COVID vaccine development attempts: vaccination against coronaviruses had led to DISEASE ENHANCEMENT.
I had hoped vaccine makers would have paid heed and would have excluded the unsafe epitopes from their vaccines. I gave them a roadmap.
Now, in Belgium, 100% of ICU admissions are among the vaccinated. Only 40% of the Belgium population are vaccinated*
I’m ready to call it: The COVID-19 vaccination program causes Disease Enhancement, likely via numerous possible means: from molecular mimicry leading to autoimmunity, or antibody-dependent enhancement, Pathogenic Priming has Antwerp, Belgium in its grip
Hospital Saint Vincent in Antwerp, Belgium — 100% of the patients in the ICU unit are inoculated
Transcript (Google Translated):
Dr. Kristiaan Deckers, GZA Hospitals
“even more radical about for those who would faithfully think that the intensive care now follows with not vaccinated that is no longer correct us right now we see a large majority are so-called breakthrough infections and that is different from to me a few weeks ago indeed not a majority vaccinated patients in intensive had at the moment that is no longer the case have the patients we have now put on intensive. I checked it yesterday are actually all vaccinated.”
Lyons-Weiler J. Pathogenic priming likely contributes to serious and critical illness and mortality in COVID-19 via autoimmunity. J Transl Autoimmun. 2020 Apr 9;3:100051. doi: 10.1016/j.jtauto.2020.100051. PMID: 32292901; PMCID: PMC7142689. https://pubmed.ncbi.nlm.nih.gov/32292901/
Recent data from the U.K. Office of National Statistics reveals people who have been double jabbed against COVID-19 are dying from all causes at a rate six times higher than the unvaccinated
In the U.S., meanwhile, the Centers for Disease Control and Prevention is propping up the official narrative with two manipulated studies — one suggesting the jab reduces all-cause mortality, and another claiming the shot is five times more protective than natural immunity
Both studies are of questionable quality and have several problems, including selection of time and date ranges that allow them to pretend that the COVID shots are safer and more effective than they really are
According to all-cause mortality statistics, the number of Americans who died between January 2021 and August 2021 is 16% higher than 2018 (the pre-COVID year with the highest all-cause mortality) and 18% higher than the average death rate between 2015 and 2019. Did COVID-19 raise the death toll despite mass vaccination, or are people dying at increased rates because of the COVID jabs?
CDC data reveal that while the number of hospitalized patients with natural immunity fell sharply over the summer, when the delta variant took over, the number of vaccinated people being hospitalized soared, from three per month on average during the spring to more than 100 a month in late summer. Since these vaccinated patients were less than six months from their second dose, they should have been at or near maximum immunity
While recent data from the U.K. Office of National Statistics (ONS) reveal people who have been double jabbed against COVID-19 are dying from all causes at a rate six times higher than the unvaccinated,1 the U.S. Centers for Disease Control and Prevention is propping up the official narrative with a “study”2 that came to the remarkable conclusion that the COVID shot unbelievably reduces your risk of dying from all causes, which includes accidents (but excluding COVID-19-related deaths). As reported by CNN Health, October 22, 2021:3
“The research team was trying to demonstrate that the three authorized Covid-19 vaccines are safe and they say their findings clearly demonstrate that. ‘Recipients of the Pfizer-BioNTech, Moderna, or Janssen vaccines had lower non-COVID-19 mortality risk than did the unvaccinated comparison groups,’ the researchers wrote in the weekly report4of the U.S. Centers for Disease Control and Prevention.
The team studied 6.4 million people who had been vaccinated against Covid-19 and compared them to 4.6 million people who had received flu shots in recent years but who had not been vaccinated against coronavirus.
They filtered out anyone who had died from Covid-19 or after a recent positive coronavirus test … People who got two doses of Pfizer vaccines were 34% as likely to die of non-coronavirus causes in the following months as unvaccinated people, the study found.
People who got two doses of Moderna vaccine were 31% as likely to die as unvaccinated people, and those who got Johnson & Johnson’s Janssen vaccine were 54% as likely to die …”
Two key takeaways from those paragraphs are:
the researchers admit they intended to demonstrate that the shots are safe and effective, and stats can be manipulated to find what you want to find
people who got the Janssen shot did in fact have a higher death rate than the unvaccinated (54% likelihood, compared to the unvaxxed).
Are the Shots Reducing All-Cause Mortality?
The researchers hypothesize that people who get the COVID jab may be healthier overall than those who abstain, and have healthier lifestyles. In my view, this is classic Orwellian doublespeak, as most of the brainwashed don’t understand the fundamentals of healthy behavior.
I suspect their new propaganda has more to do with the fact that they only looked at data through May 31, 2021. By mid-April, an estimated 31% of American adults had received one or more shots.5 As of June 15, 48.7% were fully “vaccinated.”6 So, we can assume that by the end of May, somewhere in the neighborhood of 45% of eligible Americans were double jabbed, give or take a couple of percentage points.
The reason I suspect statistical tomfoolery is because this is precisely how the CDC invented the “pandemic of the unvaccinated” myth, where they claimed 99% of COVID-19 deaths and 95% of COVID-related hospitalizations were occurring among the unvaccinated.7
To achieve those statistics, the CDC included hospitalization and mortality data from January through June 2021, a timeframe during which the vaccinated were still in a minority.
Here, we again see them use a seven-month span of time when vaccination rates were low. More importantly, however, is that the chosen cutoff date also obscures a rapid rise in vaccine-related deaths reported to the U.S. Vaccine Adverse Events Reporting System (VAERS).
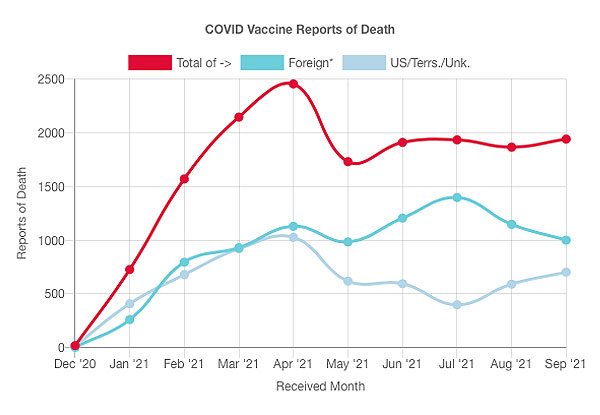
Look at the graph below, obtained from OpenVAERS mortality reports page.8 As you can see, reports of deaths following the COVID jab peaked right at the beginning of April 2021, then dropped down again during the month of April. Interestingly enough, the study notes that the daily vaccination rate has declined by 78% since April 13, 2021.
However, while the daily vaccination rate has plummeted since April, reported deaths have remained high and relatively steady. Could this be a hint that people are dying from shots they received earlier in the year?
As of January 1, 2021, only 0.5% of the U.S. population had received a COVID shot, so comparing death rates of the vaxxed and unvaxxed in December 2020 and January 2021 may not be all that fruitful. Why not include July, August and September in the analysis instead?
As you can see, reported deaths were significantly elevated during these months, compared to December and January. And, while not shown in that graph, between September 3, 2021, and October 22, 2021, the total cumulative reported death toll shot up from 7,6629,10 to 17,619.11 In other words, it more than doubled in about seven weeks — a timeframe that was not included in the CDC’s analysis.
What’s more, while the study was large and sociodemographically diverse, the authors admit that “the findings might not be applicable to the general population.”
Also, recall they changed the definition of “vaccinated” to include someone who is two weeks past their second dose (for two dose regimens). This would obfuscate the truth as there were tens of millions that received one jab or more but were not considered “vaccinated.”
Why Is All-Cause Mortality Higher in 2021?
According to all-cause mortality statistics,12 the number of Americans who died between January 2021 and August 2021 is 16% higher than 2018, the pre-COVID year with the highest all-cause mortality, and 18% higher than the average death rate between 2015 and 2019. Adjusted for population growth of about 0.6% annually, the mortality rate in 2021 is 16% above the average and 14% above the 2018 rate.
The obvious question is, why did more people die in 2021 (January through August) despite the rollout of COVID shots in December 2020? Did COVID-19 raise the death toll despite mass vaccination, or are people dying at increased rates because of the COVID jabs?
In a two-part series,13 Matthew Crawford of the Rounding the Earth Newsletter examined mortality statistics before and after the rollout of the COVID shots. In Part 1,14 he revealed the shots killed an estimated 1,018 people per million doses administered (note, this is doses, not the number of individuals vaccinated) during the first 30 days of the European vaccination campaign.
After adjusting for deaths categorized as COVID-19 deaths, he came up with an estimate of 200 to 500 deaths per million doses administered. With 4 billion doses having been administered around the world, that means 800,000 to 2 million so-called “COVID-19 deaths” may in fact be vaccine-induced deaths. As explained by Crawford:15
“This does not even include vaccine-induced deaths that have not been recorded as COVID cases, though I suspect that latter number is smaller since the only good way to hide the vaccine mortality signal is to smuggle deaths through the already-established COVID death toll.”
Corroborating Crawford’s calculations are data from Norway, where 23 deaths were reported following the COVID jab at a time when only 40,000 Norwegians had received the shot. That gives us a mortality rate of 575 deaths per million doses administered. What’s more, after conducting autopsies on 13 of those deaths, all 13 were determined to be linked to the COVID jab.16
Is the COVID Jab Responsible for Excess Deaths?
Crawford goes on to look at data from countries that have substantial vaccine uptake while simultaneously having very low rates of COVID-19. This way, you can get a better idea as to whether the COVID jabs might be responsible for the excess deaths, as opposed to the infection itself.
He identified 23 countries that fit these criteria, accounting for 1.88 billion individuals, roughly one-quarter of the global population. Before the COVID jabs rolled out, these nations reported a total of 103.2 COVID-related deaths per million residents. Five nations had more than 200 COVID deaths per million while seven had fewer than 10 deaths per million.
As of August 1, 2021, 25.35% of inhabitants in these 23 nations had received a COVID jab and 10.36% were considered fully vaccinated. In all, 673 million doses had been administered. Based on these data, Crawford estimates the excess death rate per million vaccine doses is 411, well within the window of the 200 to 500 range he calculated in Part 1.
Another interesting data dive was performed by Steve Kirsch, executive director of the COVID-19 Early Treatment Fund. In the video “Vaccine Secrets: COVID Crisis,”17 he argues that VAERS can be used to determine causality, and shows how the VAERS data indicate more than 300,000 Americans have likely been killed by the COVID shots.18Anywhere from 2 million to 5 million have also been injured by them in some way.
What Do the VAERS Data Tell Us?
In a September 18, 2021, interview with The Covexit podcast, Jessica Rose, Ph.D., who holds degrees in applied mathematics, immunology, computational biology, molecular biology and biochemistry, also discussed what the VAERS data tell us about the safety of the COVID shots.
Rose covers issues such as the magnitude of the side effects compared to other vaccination programs, the problem of under-reporting, and how causality can be assessed using the Bradford Hill Criteria. You can find a PDF of the slide show that Rose presents here.19 Here’s a summary of some of the key points made in this interview:
Between 2011 and 2020, the number of VAERS reports ranged between 25,408 and 49,412 for all vaccines. In 2021, with the rollout of the COVID shots, the number of VAERS reports shot up to 521,667, as of September 3, 2021, for the COVID shots alone. (Fast-forward to October 22, 2021, and the report tally for COVID-related adverse events has ballooned to 837,593.20)
Between 2011 and 2020, the total number of deaths reported to VAERS ranged between 120 and 183. In 2021, as of September 3, the reported death toll had shot up to 7,662. As of October 22, 2021, the death toll was 17,619.21
Cardiovascular, neurological and immunological adverse events are all being reported at rates never even remotely seen before.
The estimated under-reporting factor (URF) is 31. Using this URF, the death toll from COVID shots is calculated to be 205,809 as of August 27, 2021; Bell’s palsy 81,747; herpes zoster infection 149,017; paresthesia 305,660; breakthrough COVID 365,955; myalgia 528,457; life threatening events 230,113; permanent disabilities 212,691; birth defects 7,998.
The Bradford Hill Criteria for causation are all satisfied. This includes but is not limited to strength of effect size, reproducibility, specificity, temporality, dose-response relationship, plausibility, coherence and reversibility.
CDC Claims COVID Jab Beats Natural Immunity
If you think the CDC’s claim that the COVID jab lowers all-cause mortality is a low point in its irrational vaccine push, prepare to let your expectations sink even lower, with even more egregious Orwellian doublespeak implementation. October 29, 2021, the CDC released yet another study, this one claiming the COVID jab actually offers five times better protection against COVID-19 than natural immunity. As reported by Alex Berenson in an October 30, 2021, Substack article:22
“Yesterday the Centers for Disease Control, America’s not-at-all-politicized public health agency, released a new study purporting to show that vaccination protects against COVID infection better than natural immunity. Of course, a wave of stories about the benefits of mRNA vaccination followed.
To do this, the CDC used some magic statistical analysis to turn inside raw data that actually showed almost four times as many fully vaccinated people being hospitalized with Covid as those with natural immunity — and FIFTEEN TIMES as many over the summer. I kid you not.
Further, the study runs contrary to a much larger paper from Israeli researchers in August. As my 2-year-old likes to say, How dey do dat? Well, the Israeli study drew on a meaningful data set in a meaningful way to reach meaningful conclusions.
It counted infections (and hospitalizations) in a large group of previously infected people against an equally large and balanced group of vaccinated people, then made moderate adjustments for clearly defined risk factors.
It found that vaccinated people were 13 times as likely to be infected — and 7 times as likely to be hospitalized — as unvaccinated people with natural immunity. In contrast — how do I put this politely? — the CDC study is meaningless gibberish that would never have been published if the agency did not face huge political pressure to get people vaccinated.”
Data Manipulation Is Apparently a CDC Specialty
Berenson goes on to dissect the study in question, starting with its design, which he calls “bizarre.” The CDC analysts looked at data from 200,000 Americans hospitalized with “COVID-like” illness between January and August 2021 in nine states. Two groups were then compared:
Those who had confirmed COVID at least 90 days before and received another COVID test at the time of their hospitalization
Those who had been fully vaccinated for at least 90 days, but not more than 180 days, before their admittance and received another COVID test at the time of their hospitalization
Berenson points out what I stressed earlier, which is that choosing certain time or date ranges will allow you to make the shots appear a whole lot better than they actually are. Here, by choosing a 90- to 180-day inclusion range, they’re looking at a best-case scenario, as we now know the shots quit working after a handful of months. So, they’re only looking at that short window during which the COVID shots are at maximum effectiveness.
The 90-day criterion also ends up excluding the vast majority of patients hospitalized with COVID-like illness, both vaccinated and unvaccinated. While Berenson doesn’t address the vaccinated, few if any could have been fully vaccinated for at least 90 days prior to March, so why include January and February? Just about everyone was by definition unvaccinated at that time.
As for those with natural immunity, only 1,020 of the 200,000 patients hospitalized between January and August had a previously documented COVID infection. As noted by Berenson:23
“Given the fact that at least 20% of Americans, and probably more like 40%, had had COVID by the spring of 2021, this is a strikingly small percentage — and certainly doesn’t suggest long COVID is much of a threat.“
Of the 1,020 with natural immunity, only 89 tested positive for COVID, while 324 of the 6,328 vaccinated patients who met the study criteria tested positive. Of note here is two things:
There were more vaccinated patients hospitalized for COVID-like illness than those with natural immunity; this despite including months when vaccination rates were in the fractional and single digits
A greater number of vaccinated patients tested positive for breakthrough infection than patients with natural immunity
Hospitalization Rate Among Vaccinated Is Soaring
Berenson continues:24
“And the CDC didn’t have, or didn’t publish, figures on how many people were actually in the two groups … Instead it compared the PERCENTAGE OF POSITIVE TESTS in the two groups. But why would the percentage of positive tests matter, when we don’t know how many people were actually at risk? …
[A]mazingly, the statistical manipulation then got even worse. The natural immunity group had an 8.7% positive test rate. The fully vaccinated group had a 5.1% positive test rate. So the natural immunity group was about 1.7 times as likely to test positive. (1.7x 5.1 = about 8.7.)
With such a small number of people in the natural immunity group, that raw ‘rate ratio’ may well have failed to reach statistical significance. (We don’t know, because the CDC didn’t provide an unadjusted odds ratio with 95% boundaries — something I have never seen before in any paper.)
Instead, the CDC provided only a risk ratio that it had adjusted with a variety of factors, including ‘facility characteristics [and] sociodemographic characteristics.’
And finally, the CDC’s researchers got a number that they could publish — hospitalized people who had previously been infected were five times as likely to have a positive COVID test as people who were fully vaccinated. Never mind that there were actually four times as many people in the second group. Science!
By the way, buried at the bottom of report is some actual data. And it’s bad. The CDC divided the hospitalizations into pre- and post-Delta — January through June and June through August.
Interestingly, the number of hospitalized people with natural immunity actually fell sharply over the summer, as Delta took off. About 14 people per month were hospitalized in the winter and spring, compared to six per month from June through August. (Remember, this is a large sample, with hospitals in nine states.)
But the number of VACCINATED people being hospitalized soared — from about three a month during the spring to more than 100 a month during the Delta period. These vaccinated people still were less than 180 days from their second dose, so they should have been at or near maximum immunity — suggesting that Delta, and not the time effect, played an important role in the loss of protection the vaccine offered.”
Perhaps Rep. Thomas Massie said it best when he tweeted:25
“What do ‘road kill’ and a CDC sponsored COVID paper have in common? By the third day, they’re so picked apart they’re unrecognizable. This CDC Director is shameless for fabricating junk science with findings that stand in stark contrast to every credible academic study.”
Massie goes on to point out some obvious flaws and questions raised by the study, including the following:
The authors failed to verify recovery among those with previous infection, so any number of these “reinfections” may actually have been long-COVID.
The fact that more than 6,000 hospitalized for COVID symptoms were vaccinated, compared to just 1,000 with previous infection, counters the claim that 99% of COVID hospitalizations are unvaccinated.
The number of vaccinated people hospitalized for COVID symptoms correlate negatively with the time since vaccination; 3,625 were hospitalized within 90 to 119 days of vaccination, 2,101 within 120 to 149 days, and 902 within 150 to 179 days of vaccination. “Could initial hospitalizations be due to vaccine adverse effects or due to a temporarily weakened immune system from the vaccine?” Massey asks.26
The study only considered those with natural immunity who ended up in the hospital, and not the ones who didn’t get sick. “Natural immunity helps prevent hospitalization!” Massey says.27
Massie also notes that this paper, which is only six pages long, has an astounding 50 authors, and at least half a dozen of them disclose Big Pharma conflicts of interest. What’s more, seeing how Congress gave the CDC a cool $1 billion to promote the COVID jab, isn’t working for the CDC a conflict of interest as well?
Martin Kulldorff, Ph.D., professor of medicine at Harvard Medical School and a biostatistician and epidemiologist in the Division of Pharmacoepidemiology and Pharmacoeconomics at Brigham and Women’s Hospital, also critiqued the study in a tweet, saying:28
“This CDC study has a major statistical flaw, and the 5x conclusion is wrong, it implicitly assumes that hospitalized respiratory patients are representative of the population, which they are not. Trying to connect with authors.”
Natural Immunity Is the Best Answer
Try as the CDC might to twist the data, there’s really no question that natural immunity is superior and longer lasting than vaccine-induced immunity. This is also a long-held medical fact that has been tossed aside as too inconvenient to matter in COVID-19.
For some undisclosed reason, the government wants everyone to get the COVID injection, whether medically warranted or not. The sheer lunacy of that is cause enough to be leery and hold off on getting the risky jab. I can tell you one thing, this policy has nothing to do with safeguarding public health, because it’s driving public health in the wrong direction.
It’s quite clear that the way out of this pandemic is through natural herd immunity, and at this point, we know there’s no reason to fear COVID-19. Overall, its lethality is on par with the common flu.29,30,31,32,33 Provided you’re not in a nursing home or have multiple comorbidities, your chances of surviving a bout of COVID-19 is 99.74%, on average.34
Additionally, we also know there are several early treatment protocols that are very effective, such as the Frontline COVID-19 Critical Care Alliance I-MASK+35 protocol, the Zelenko protocol,36 and nebulized peroxide, detailed in Dr. David Brownstein’s case paper37 and Dr. Thomas Levy’s free e-book, “Rapid Virus Recovery.” Whichever treatment protocol you use, make sure you begin treatment as soon as possible, ideally at first onset of symptoms.
The reported rate of death from COVID-19 shots in VAERS, on the other hand, exceeds the reported death rate of more than 70 vaccines combined over the past 30 years, and if you are injured by a COVID shot and live in the U.S., your only recourse is to apply for compensation from the Countermeasures Injury Compensation Act (CICP).38
Compensation from CICP is very limited and hard to get. You only qualify if your injury requires hospitalization and results in significant disability and/or death, and even if you meet the eligibility criteria, it requires you to use up your private health insurance before it kicks in to pay the difference.
There’s no reimbursement for pain and suffering, only lost wages and unpaid medical bills. Salary compensation is of limited duration, and capped at $50,000 a year, and the CICP’s decision cannot be appealed.
REMINDER: Please mark your calendars for the upcoming November Madison Lyme Support Group Meeting.
**Note the new location**
For future reference, anytime you want to know upcoming meeting times, go to the upper right hand corner on the website and click on the “meetings” tab.
TOUCHED BY LYME: Helping families with Lyme re-capture their joy
Nov. 4, 2021
Gloria Kim, a mother of three from New Jersey, fell into the Lyme world when her son was bitten by a tick at a young age.
As a result, her family has been dealing with chronic Lyme and co-infections for the last 14 years. And as she learned early on, Lyme disease affects the whole family—not just the ones who are sick.
“As a caretaker, I worked tirelessly to keep my son alive and was constantly in a state of despair, isolation and survival,” she recalls.
“As much as I wanted to be there for my other two healthy children and husband, the struggle of saving my son overwhelmed me and I lost myself.”
She understands the “difficulty, frustration, sadness and anger” of being a Lyme caregiver, she says.
To help others, she has created a weekly online support group to help bring connection and community to people in this situation–and to help them rediscover joy.
One of the things that Gloria said really helped her and her family was to find ways to laugh together. Here’s something she recently posted on her Facebook page.
Add this to your toolbox to help you heal from Lyme.
Melissa Wright is the Director of Patient Engagement & Outreach for LymeDisease.org and Project Manager of MyLymeData.
She spoke at the recent Tick-borne Disease Diagnostics online event spons
Lyme is not recognized as a possibility in their area
Many patients do not present with a classic erythema migrans rash
The diagnostic testing for Lyme is flawed
View her presentation here:
Here’s the text of her remarks:
Hello everyone, my name is Melissa Wright and I am the Director of Patient Engagement & Outreach for LymeDisease.org and Project Manager of MyLymeData. I am happy to be with you today for the Tick-borne Disease Diagnostics Innovation Incubator, and have the opportunity to talk with you about the impact of diagnostic delays in the Lyme community.
Founded over 30 years ago, LymeDisease.org, is one of the oldest Lyme disease organizations in the nation. It is the largest and most trusted communications network for Lyme patients. Our mission is to harness the power of tens of thousands of patients to improve patient care and accelerate the pace of Lyme disease research. We do this through providing tools like our symptom checker, physician directory, and the MyLymeData patient registry and research platform with over 15,000 patients enrolled.
Today I’ll briefly discuss diagnostic issues with data from MyLymeData, the current testing and what we’re doing to push the needle
Using a diagram first developed by the Institute of Medicine (now the National Academy of Medicine) in its report “Improving Diagnosis in Health Care,” which identified different points along the path to diagnosis where things can go wrong and diagnosis can be delayed or missed. It has been modified to reflect the diagnostic issues we encounter in Lyme disease. For example:
Lyme is not identified as a possibility in (name your state)
Many patients do not present with a classic EM rash
And the diagnostic testing is flawed
Which leads to a large majority of patients being misdiagnosed.
In MyLymeData we found that 70% of those with late or chronic Lyme disease experienced years of diagnostic delays even though 45% had presented with early symptoms. It had taken the majority, 3 or more years to be diagnosed after seeing 5 or more doctors with 72% being misdiagnosed and likely unnecessarily treated for another disease.
So why the delay? In Lyme disease we know early diagnosis can be a ticket to recovery. 70-80% do become well. Unfortunately, a diagnosis of early Lyme disease is not so straight forward. A lot of the symptoms are not specific for Lyme disease and do occur in other illnesses. So, there’s a big emphasis on whether the patient has distinguishing factors.
– Was the patient exposed to an area where there are ticks that carry the disease? (Remember, no Lyme in name your state)
– Did the patient have a distinctive round rash that could have been caused by the bite of a tick. (only 34% of patients report having a rash)
– And were any blood tests positive? (flawed testing, with 37% receiving a false negative)
In regard to testing, we know during the first four to six weeks of Lyme infection, standard Lyme disease tests are unreliable because most people have not yet developed the antibody response that the test measures, and even later in Lyme the two-tiered testing is highly insensitive.
The chart (Stricker, Johnson 2010) illustrates the studies examining the testing. As you can see, the mean sensitivity for Lyme testing is 46%. This means 108 of every 200 cases is missed in Lyme compared to that of the highly sensitive testing for HIV/AIDS, which has a mean sensitivity of 99.5%, where only 1 in every 200 cases is missed.
Simply put, the likelihood of Lyme disease being diagnosed from a positive lab test is the equivalent of getting a heads or tails in a coin toss. This ultimately means many patients go undiagnosed.
Now everyone knows the saying there is power in numbers, but despite Lyme disease having 475,000 cases annually little has been done to advance Lyme testing or research.
According to research by Goswami, the number of clinical studies for Lyme disease trails behind leprosy–which has an incidence of less than 200 cases per year. So, Lyme disease should be thought of as a research disadvantaged disease that faces the same challenges that rare diseases face.
Patients are the most underutilized resource in medical research, and we are striving to bridge that gap.
The research cycle illustrated is derived from Groft’s work with rare diseases. His model suggests forming a patient registry that links with a biorepository—we are collaborating with the Lyme Disease Biobank here.
The registry helps to develop a research hypothesis—here we have published three peer-reviewed publications to better characterize the disease, assess patient reported outcomes, and analyze treatment effects among patient subgroups. The registry can then be used to help recruit patients. We have worked on recruiting for two clinical studies.
A team research approach will allow rapid knowledge generation to accelerate the pace of research–-leading to improved diagnostics, treatment and care.
Thank you for your time, I appreciate the opportunity to speak with you all today and I want to close by encouraging anyone not yet participating in MyLymeData to enroll.
We’re Not in a ‘Pandemic of the Unvaccinated,’ Peter Doshi Explains During COVID Panel
Peter Doshi, a senior editor at The BMJ, and Retsef Levi, a professor at the Massachusetts Institute of Technology, told a panel of experts the COVID vaccines’ trial data doesn’t support the narrative that the vaccines are safe and effective.
Peter Doshi, a senior editor at The BMJ and associate professor of pharmaceutical health services research at the University of Maryland School of Pharmacy, and Retsef Levi, a health system and analytics professor at MIT, expressed doubts about COVID vaccine efficacy and the failures of the scientific community.
Doshi said we’re not in a “pandemic of the unvaccinated.” If hospitalizations and deaths are almost exclusively occurring in the unvaccinated “why would booster shots be necessary?” Doshi asked. “And why would the statistics be so different in the UK, where most COVID hospitalizations and deaths are among the fully vaccinated?”
He also criticized the fact that society is vaccinating and mandating the vaccine for large portions of the public despite the raw data on the safety and efficacy of the vaccines not being available yet.
Levi claimed the government attempted to censor the research by calling its credibility into question. “They called the research fake,” Levi said.
Watch here (Doshi starts at 1:18:40 and Levi starts at 1:49:07):
WATCH: Sen. Johnson Holds Expert Panel on COVID Vaccine Injuries, Federal Vaccine Mandates
On Tuesday, Nov. 2, U.S. Sen. Ron Johnson held a panel discussion with doctors and medical researchers who have treated COVID-19 vaccine injuries and are researching the safety and efficacy of COVID-19 vaccines.
U.S. Sen. Ron Johnson (R-Wis.) held a panel discussion Tuesday, Nov. 2 with doctors and medical researchers who have treated COVID-19 vaccine injuries and are researching the safety and efficacy of COVID-19 vaccines. Johnson also talked with patients who have experienced adverse events due to the COVID-19 vaccine and discuss vaccine mandates.
The senator discussed the importance of early treatment for COVID, Americans’ health care freedom and natural immunity. Johnson covered the impacts of mandates on the American workforce and the economy, and the lack of transparency from federal health agencies in response to his COVID-19 oversight requests. (See link for article and who spoke in the video)
Lieutenant Colonel Theresa Long, a senior U.S. Army aerospace medicine specialist who has treated soldiers injured by COVID vaccines, said that those shots pose a greater danger to the health of American servicemen and military readiness than COVID itself and condemned the Biden administration for treating men and women in uniform as “lab rats.”
Dr. Long points out in the video that only 12 active duty soldiers have died from COVID. This study on the U.S. military already shows that heart inflammation is linked to the COVID injections. Keep in mind all military members were previously healthy with a high level of fitness. They were physically fit by military standards and lacked any known history of cardiac disease, significant cardiac risk factors or exposure to cardiotoxic agents.
Vaccine-Injured Speak Out, Feel Abandoned by Government Who Told Them COVID Shot Was Safe
During an event hosted Tuesday by U.S. Sen. Ron Johnson (R-Wis.), people whose lives were ruined by COVID vaccines said they feel abandoned by a government that told them it was their patriotic duty to get the shot.
U.S. Sen. Ron Johnson (R-Wis.) on Tuesday held a discussion with a panel of experts, including clinicians, scientists, lawyers and patient advocates, and with people injured by COVID vaccines, who gave powerful testimonies about their experiences.
Johnson and the expert panel discussed the importance of early treatment for COVID, healthcare freedom and natural immunity, the impacts of mandates on the American workforce and the economy, COVID vaccine safety concerns and the lack of transparency from federal health agencies in response to his COVID oversight requests.
None of the major mainstream media outlets picked up the event, but Children’s Health Defense hosted Johnson’s live panel discussion on CHD.TV. (See link for article and video)