https://www.lymedisease.org/life-lessons-chronic-lyme/

Career and life lessons from survivors of chronic Lyme disease

By Fred Diamond, Nov. 9, 2021

We all know that Lyme disease can cause major career disruption. But what if overcoming the disease can help you find your life’s purpose and mission?

I host The Sales Game Changers Podcast for sales professionals around the globe. I interview sales leaders about tactics, strategies, and ideas. Because someone in my life has chronic Lyme disease, I became interested in learning more about how survivors could transform their lives.

I recently hosted an episode called, “How These Leaders Discovered Their ‘Why’ After Conquering Chronic Illness and How It Applies to Sales.”

I sought out people to interview who had overcome their disease, or at least contained it, and found a more purposeful way to focus their careers and lives.

Great sales professionals are always looking for ways to find their purpose and mission so they can better serve their customers. I knew these lessons would resonate with my audience.

I’ve met some amazing leaders who have battled chronic Lyme and have shifted their career paths and life efforts to helping others suffering from chronic illness. I am inspired by them all.
You can listen to the episode or read the complete transcript. This episode was one of our most listened to ever.

Guests

The guests included:

  • Gregg Kirk, a digital sales support marketing director who switched career paths after his decade-long struggle with Lyme disease. After reaching remission, he wrote the book “The Gratitude Curve” and founded a nonprofit Lyme patient fund called Ticked Off Foundation.
  • Tanya Hoebel, vice-president of The Lyme Center in Chico, California, as well as the co-host of the Integrated Lyme Solution podcast.
  • And JP Davitt, founder of Lymefriends and the author of “LYME BOOK: A Journey to Becoming One Day Better.” After overcoming chronic illness, he’s been focused on helping others make one day better.

All three have found their life’s purpose in helping others who are struggling with Lyme disease.

The shift to recovery

I asked when the shift to recovery took place and then how did this define their mission.

Gregg Kirk said, “The shift started when I was at my worst, I was at the point where I wanted to die. It was one of these weird situations where I wanted to die but I kept hanging around. Then I started looking inward. Why am I still here and why have I gone through this? Is this some kind of weird karma thing? Did I deserve this? Did I kill someone in a past life? Why am I going through all this mental and physical punishment? Then after I had that night, I let everything go. I just felt like my life had burnt to the ground and I started looking at my life in a different way.”

“I started thinking, maybe this disease is pointing me in a direction. Maybe I was going in the wrong direction in my life, as much as I liked my life at the time. I just started to let it happen. And the less I resisted, the more things started changing in very unexpected ways,” he said.

Tanya Hoebel said, “When I was nearing the end of my treatment, that was about 9 years into my illness, I could for the first time see the light at the end of the tunnel. I really had some faith that I was going to get better. I didn’t let it physically or emotionally ruin me because I continued to fight back. I thought, how can I possibly allow another human being go through even one day of what I’ve gone through over the last 9 years? My life changed at that moment.”

JP Davitt said, “When I was sick, I dreamt of a platform that would allow sick people to connect more easily with one another. I imagined a social platform that was more like online dating for wellness. I created an interactive health and wealth advisory practice, and my passion became my niche.”

Mission and meaning

I then asked them specifically what they created to further their mission and how it’s put more meaning into their life.

Tanya said, “I’m so thankful that I found another resource to end my suffering. It proved to me also, that someone on top of the world emotionally, financially, and at the top of their career like I was prior to Lyme can in one moment lose it all. I could have been one of those people homeless on the streets that you see roaming around and you often wonder why they’re there. That is what Lyme disease does physically, emotionally, and financially.”

“Because this positive person, me, contemplated suicide at one point, I thought I’ve got to do something, I’ve got to make a difference. That is when I became so involved in advocating for Lyme. I run a nonprofit organization, it’s called The Lyme Center, it’s based out of Chico, California and our mission is to educate and advocate for Lyme.”

“I’m also the co-founder of an incredible mentoring group on Facebook. This group has proved to be more than I ever dreamt it to be in such a short amount of time. We offer lots of treatment options and help educate them on so many different levels of Lyme because there are so many facets of it. I even managed to find time to cohost a weekly podcast, Integrative Lyme Solutions.”

JP said, “Lymefriends is a platform that acts like a dashboard for people with Lyme disease to go to, a one-stop-shop for all of the resources. I collect resources without worrying about any competition bringing everything together to help them finance sooner.”

“Whenever I was sick and having to streamline my efficiency with my body, it really taught me a lot about processes. Learning a lot about this process as I carried that over to healthcare and I was able to them form a goal to not just help with Lyme disease, but my goal really in the grand picture is to change the literacy and vocabulary of healthcare using technology.”

Gregg said, “There is a patient care problem. People have no money and they’re not getting diagnosed properly. When they finally are, they’re not getting the proper care.”

“I thought, if I had a billion dollars, what would I do? I thought I would create a healthcare system, like an insurance system that funded treatment because most of the treatments that worked for me were not covered by insurance, the herbal treatments and so forth. I thought, I don’t need to wait until I’m a billionaire, I can start a foundation, a nonprofit that people come to us, they get qualified through some documentation, and we give them monthly stipends. We’ve been able to help many people get the treatment they need.”

It was very inspiring to hear from some people who have overcome Lyme disease and have been able to give back in a big way and to give their lives more purpose.

The same can happen for you.

Fred Diamond is based in Fairfax, VA and can be contacted via Facebook. For a living, he runs the Institute for Excellence in Sales and hosts the Sales Game Changers Podcast. Someone close to him is a chronic Lyme survivor, which led to his Lyme-related advocacy.

https://www.lymedisease.org/advocates-call-for-idsa-retraction/

Advocates call on IDSA to retract false information on congenital Lyme

Nov. 9, 2021

Mothers Against Lyme, a group of advocates concerned about the impact of Lyme disease and its co-infections on pregnant women, children and families, is calling for retraction of a statement in the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), American College of Rheumatology (ACR) 2020 Clinical Practice Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease that contributes to misdiagnosis and harm to pregnant women and children who are congenitally infected.

On October 20, Mothers Against Lyme sent a retraction request letter to the editors of the journals that published the guidelines and the leadership of the sponsoring organizations. Copies were sent to the clinical practice guidelines committees of the sponsoring organizations and the co-authors of the guidelines. The guidelines were published in Clinical Infectious Diseases, Neurology, Arthritis Care & Research, and Arthritis & Rheumatology.

Page e12 of the guidelines “Treatment of Lyme Disease” section states:

“To date, Lyme disease in pregnancy has not been found to result in congenital infection or a syndrome of congenital abnormalities, and no additional treatment or monitoring of the mother or infant is recommended beyond the standard of care.”

According to the letter, the statement “To date, Lyme disease in pregnancy has not been found to result in congenital infection” is not true.

40 peer-reviewed articles

The letter cites more than 40 peer-reviewed articles, including a systematic review co-authored by a CDC epidemiologist, that provide evidence of congenital infection with Lyme disease.

The letter also cites studies and review articles that show adverse birth outcomes are common for both treated and untreated pregnant women with Lyme disease.

Adverse outcomes include fetal death, newborn death, and newborns with an abnormal outcome (e.g. birth defects, hyperbilirubinemia, respiratory distress).

According to Mothers Against Lyme Chair Isabel Rose:

“Correction of this error is vital and warrants an expedited review and notice of correction. The potential harm to mothers, children, and families from the inaccurate information in the IDSA, AAN, ACR Guidelines is significant. Providers who rely on the guidelines will fail to diagnose and treat Lyme disease in pregnancy and fail to recognize the offspring of women with Lyme disease as infants and children at risk. Countless tragic births and fetal losses will result, with a lifetime of harm to the children and their families.”

Authors contradict their own work

The letter also cites eight articles co-authored by IDSA, AAN, ACR Guidelines authors that “clearly contradict what they’ve written in the guidelines, and which address the issue of intrauterine transmission and fetal abnormalities head-on.”

Following are examples.

“It is clear that B. burgdorferi can be transmitted in the blood of infected pregnant women across the placenta into the fetus. This has now been documented with resultant congenital infections and fetal demise.”

“The precise risk to the developing fetus of maternal Lyme disease during pregnancy is unknown, although it is well documented that fetal infection can occur and may have deleterious outcomes, including malformations and death.”

“The aim of treatment of early Lyme disease during pregnancy is not only to treat the infection and prevent long-term sequelae but to eliminate the infection as quickly as possible so as to prevent congenital transmission to the fetus.”

Ignoring their own research

According to Rose:

“It is disheartening and alarming that the authors of medical guidelines that direct the care of pregnant women with Lyme disease are ignoring their own research to put forward guidelines based on ‘expert opinion’ rather than their own discoveries. Their own work conclusively proves that perinatal transmission of B. burgdorferi during pregnancy does occur and may have dire consequences for the pregnant mother and her fetus.”

The IDSA, AAN, ACR Guidelines say that “no additional treatment or monitoring of the mother or infant is recommended beyond the standard of care.”

Instead of denying the existence of congenital Lyme, the letter says “the Guidelines should acknowledge that Lyme bacteria can cross the placenta, both infecting and causing harm to unborn children, and describe the manifestations of Lyme in pregnancy that the research has uncovered and advise screening and treatment according to the knowledge we have to date.”

Research funding

Rose points out that researchers who depend on the IDSA, AAN, ACR Guidelines for information will be less likely to submit grant applications for much needed research if they rely on the statement that congenital Lyme disease does not exist.

She notes that this is especially important since more than $29 million in new annual funding for NIH has been appropriated that could support this type of research. NIH has also issued several notices of special interest to encourage research on Lyme and other tick-borne diseases. A recent notice includes a section that calls for research on “gestational Lyme disease” and the impact on pregnancy on immune response.

Rose says, “Correcting this error does not undo the harm. In addition to making this correction in a timely manner, the sponsoring organizations should encourage their members to conduct research on congenital Lyme that will improve health outcomes for pregnant women with Lyme disease and children who are congenitally infected.”

About Mothers Against Lyme

We’re a group of mothers and mother-advocates who are concerned about the impact of Lyme disease and its co-infections on pregnant women, children and families. Our focus includes awareness, education, advocacy and community building, as we promote research that advances diagnosis, treatment and prevention.

SOURCE OF PRESS RELEASE: Mothers Against Lyme

**UPDATE**

The 2025 update to the following report is this: A study has shown that nearly half of COVID deaths were not due to COVID.

The study revealed a massive overcounting of ‘COVID deaths,’ massive death certificate inaccuracy, and massive misclassification of hospital-acquired infections.

On top of these issues the study found that patients who died “with” COVID-19:

  • were younger
  • more likely to be immunosuppressed
  • have end-stage liver disease, or be admitted for other causes

Patients who died “due to” COVID-19 were more likely to:

  • Exhibit classic symptoms: hypoxia (44.1%), shortness of breath, fever, and cough
  • Require oxygen support (93.4% vs. 66.9%) and receive COVID-specific therapies:
Truth always outs in the end.

http://  Approx. 10 Min

Counting COVID

Full Measure with Sharyl Attkisson

Sept. 20, 2021

https://articles.mercola.com/sites/articles/archive/2021/11/15/died-from-or-died-with-covid

Investigation: Died ‘From’ or Died ‘With’ COVID?

Nov. 15, 2021

Analysis by Dr. Joseph Mercola

Story at-a-glance –

  • A recent investigative piece by Full Measure revealed a serious death rate miscount in Colorado, including two people out of five who were not dead
  • Analysis of the number of people who died in Santa Clara and Alameda counties in California found there was a 22% and roughly 25% overcount in the death rate
  • Former CDC director Dr. Robert Redfield admitted financial policies may have artificially inflated hospitalization rates and death toll statistics
  • The CDC is now counting people who die within 14 days of their shot as an unvaccinated death, further skewing the death toll results and hiding deaths that result from the COVID jab
  • New guidelines from the AMA are teaching doctors how to participate in misinformation campaigns using “language swaps” and approved social media posts to ensure the public doesn’t look closely at vaccine injuries

In this short news report from Full Measure, Sharyl Attkisson interviews the coroner from Grand County, Colorado, where a murder-suicide during Thanksgiving 2020 were recorded as two COVID-19 deaths. While outlandish, it has appeared from other reports around the country1 and statements from the Colorado governor, this practice is not uncommon.2

In the early months of 2020, many in the mainstream news media laughingly called concerns that there were more deaths reported from COVID-19 than could be attributed to the disease a “death toll conspiracy.”3 Rolling Stone reported this was led by conservative Republicans and “anti-vaxxers” who believe the numbers were inflated.4

Yet, it was only several short months later that data confirmed what many already knew: The number of people who died “from” COVID-19 we’re not the same as those who died “with” COVID-19. The differentiation is not subtle. In the first case, individuals died from the disease.

However, in the second case, an individual may have tested positive for COVID-19 within the last 28 days but died from other health conditions, such as heart disease, diabetes or end stage cancer.

Inaccurate and high false positive rates from PCR tests likely contributed to the number of individuals who died “with” COVID-19. PCR tests use something called “cycle thresholds” to look for positive cases. The higher the threshold, the greater the risk a healthy person is labeled as a COVID-19 “case.”5 In reality, PCR testing is not a proper diagnostic tool.6 Yet, it has supported the promoted narrative that the U.S. is suffering from a rising number of deaths.

Inflated COVID Death Numbers Recorded in Multiple Counties

In July 2021, Santa Clara and Alameda counties in California did an analysis of the number of people who died from COVID-19. Santa Clara found a significant discrepancy.7 The data did not change. The number of actual deaths did not change. But the authorities found 22% of the deaths recorded from COVID-19 could not be attributed to the virus.

The new numbers were generated by counting only those people whose cause of death was ‘from’ the virus. They left off the people who had tested positive at the time of death, but whose cause of death was not the result of an infection from SARS-CoV-2. In the month before, Alameda County recounted their deaths and registered a drop of roughly 25%.8

Dr. Monica Gandy is an infectious disease expert at the University of California San Francisco. She believes that it’s important to have an accurate accounting of the cause of death. She spoke with a reporter from CBS KPIX San Francisco and rather optimistically believed the CDC “may soon ask all counties to do the same as Alameda and Santa Clara Counties and that the nation could also see a drop in its COVID-19 death toll.”9

In the Full Measure video above, Attkisson recounts the story from 2020 of the two deaths from gunshot wounds in Grand County, Colorado, that were recorded as COVID-19 deaths.

The video also reveals that what was happening in Grand County was happening across the state. Dr. James Caruso, chief medical examiner and coroner for Denver, recounted hearing similar stories from coroners in rural counties where it was easier to quickly assess whether a death was from COVID. He told Attkisson:10

“I was told by some of my fellow coroners in the more rural counties in Colorado that it was happening to them, that they knew of issues where they had signed out a death certificate with perhaps trauma involved. And they were being advised that it was being counted as a COVID-related death.”

Caruso believes that early in the process at the local level, death certificates are probably completed accurately. But then, potentially at the state or federal level, there is a possibility that agencies are cross-referencing COVID tests against death certificates. Anyone who had tested positive is listed as a COVID-related death, regardless of how they died.

When Attkisson checked the tally of deaths in Grand County in July 2021, she found The New York Times had over reported the deaths, including the two gunshot wounds, one who had died outside of the county and two people who were recorded as dead but were alive.11

Merrit Linke is the chair of the Grand County Board of Commissioners. He and the other commissioners drafted and signed a letter that was sent to the governor of Colorado. Essentially, the letter said, “Hey, these numbers are not correct. It’s not right. We should report these correctly, and please fix this.”12

The response was appalling. Brenda Bock is the corner for Grand County, and she also signed the letter with the commissioners. She recounted her conversation with the governor of Colorado to Attkisson, saying, “He told me he didn’t believe it was right, but he wasn’t going to have them remove it from the count because all the other states were doing it that way so we were going to also.”13

Financial Incentives Likely Contributed to Inflated Numbers

The reason other states were over reporting COVID deaths, and maybe the reason the governor of Colorado wanted to continue, were the financial incentives offered to hospitals. As early as April 2020, some health authorities were suspicious that the COVID-19 death counts were padded.

However, Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases (NIAID) and the chief medical adviser to the president, brushed off those questions, even after the CDC numbers were called into question later in the year.14 A host of mainstream media also reported these suspicions were a conspiracy theory.15,16

Yet, in June 2020, nurse Erin Olszewski gave first-hand testimony, sharing how financial incentives were at the heart of diagnosis and mistreatment at a public hospital in Queens, New York.17 Olszewski was interviewed by The Press and the Public Project as part of the series “Perspectives on the Pandemic.” Olszewski has a long history of honorable service in the army.

She was deployed during Operation Iraqi Freedom in 2003. “Part of her duties involved overseeing aid disbursement and improvements to hospital facilities. While in the country she received the Army Commendation Medal for meritorious service and was wounded in combat.”18 She retired in 2012 to work as a civilian nurse and continued work as a medical freedom and informed consent advocate.

According to Olszewski, patients who tested negative were routinely listed as positive and quickly placed on ventilators, a largely inappropriate treatment that ended up killing nearly all of them. By August 2020,19 then-CDC director Dr. Robert Redfield admitted financial policies may have artificially inflated hospitalization rates and death toll statistics.

In response to a question before a House panel committee asked by Rep. Blaine Luetkemeyer, R-Mo., about potential “perverse incentives” that hospitals might have to alter death certificates, Redfield said:20

“I think you’re correct in that we’ve seen this in other disease processes, too. Really, in the HIV epidemic, somebody may have a heart attack but also have HIV — the hospital would prefer the [classification] for HIV because there’s greater reimbursement.”

The Washington Examiner21 also reported that in August 2020 more than 3,000 people were removed from the death count in Texas after it was revealed they did not test positive but were only considered a probable case.

CDC Now Counting Vaccination Deaths as Unvaccinated Illness

The issue of inaccurately counting COVID-related deaths is continuing. Based on statements made by Dr. Rochelle Walensky, director of the Centers for Disease Control and Prevention, it appears the CDC is manipulating statistics to create a false and inaccurate impression.

In a July 16, 2021, White House Press briefing, she claimed “over 97% of people who are entering the hospital right now are unvaccinated.”22 Just a few weeks later, she inadvertently revealed how the CDC came by that statistic.23

The CDC took hospitalization and mortality data from January through June 2021 to come to this conclusion. However, during this time frame, most of the people in the U.S. were not vaccinated,24 so the majority of people in the hospital or who had died would not have received the vaccine.

The newest way that the CDC is playing with statistics is to count anyone who has died within the first 14 days post-injection as unvaccinated.25 This not only artificially inflates the unvaccinated death toll, but also artificially deflates the number of people who die as a result of the genetic therapy shot.

The vast majority of deaths from the COVID jabs are happening within the first 2 weeks.26 These deaths are now being recorded as an unvaccinated death from COVID, rather than being counted as a death related to a breakthrough infection or vaccine injury.

This may be related to the fact that public health agencies were fully aware of the expected side effects from the shot and that they may have determined these were acceptable losses. According to Slide 16 in an October 22, 2020, presentation to the FDA by the director of Biostatistics and Epidemiology on some of the expected effects included:27

Death Convulsions Stroke
Acute myocardial infarction (heart attack) Multisystem Inflammatory Syndrome in children Vaccine enhanced disease
Myocarditis/pericarditis Autoimmune disease Thrombocytopenia
Kawasaki disease Anaphylaxis Guillain-Barre syndrome

As you’ll note, many of these effects from the shot are reported in growing numbers to the Vaccine Adverse Event Reporting System (VAERS).28 Additionally, the FDA added a warning to the Pfizer and Moderna shots about the risk of heart inflammation and myocarditis.29

Just days before, the CDC announced the benefits of the shot outweigh the risk of a “likely association” between the shots and myocarditis in otherwise healthy young people.30 In June 2021, CNN31 reported the CDC had received 1,226 preliminary reports of children with myocarditis or pericarditis through VAERS.

Interestingly, the CDC found these numbers enough to issue a warning but have completely ignored the number who have died from the shots. By October 22, 2021, VAERS had recorded 10,956 cases of “rare”32 myocarditis and 17,619 deaths from the shot.33

AMA Teaches Doctors the Power of Misinformation

Before turning to your health care professional for accurate information, it’s important to note that the American Medical Association is strongly advising doctors to follow the company line. And the company line is full of “language swaps,” samples of acceptable social media posts and information on how to deflect or redirect questions to push AMA acceptable content.34

Deception has been the name of the game since long before the vaccine was released. As the push toward the “Great Reset” continues on multiple fronts, it is imperative that the medical establishment remain on board with the same rhetoric and unsubstantiated messages to drive fear and impair American’s critical decision making.

The language swaps and sample social media posts take advantage of a powerful tool – words. Language is a powerful way to shape reality,35,36,37 because it shapes how we think about what we’re experiencing. As noted by storyteller and filmmaker Jason Silva:38

“The use of language, the words you use to describe reality, can in fact engender reality, can disclose reality. Words are generative… We create and perceive our reality through language. We think reality into existence through linguistic construction in real-time.”

For example, “lockdown” sounds like involuntary imprisonment imposed by a totalitarian regime, which is what it is, whereas “stay-at-home order” sounds far less draconian. After all, “home” is typically associated with comfort and safety. The AMA goes on to provide instructions on how to block, deflect and stall in the face of tough questions where an honest answer might break the official narrative.

I encourage you to read through Page 8 of the guide and pay attention to how these psychological tricks are used when listening to interviews or reading the news.

The AMA’s guidance isn’t all bad. Some of its advice makes perfect sense. But the inclusion of language swaps that result in false statements being made, and tools for steering, blocking, deflecting, redirecting and stalling to avoid direct answers do nothing but erode credibility and thus trust in the medical community.

After having gathered data during the pandemic for roughly 19 months (March 2020 to October 2021) it is imperative that the American people begin to question the number of reported “cases” and deaths in a country where medical care is reportedly better and more advanced than many other countries.

In other words, why does the U.S. lead the world in number of deaths from an infection?39 Might it be for the same reason that Australia is in a tyrannical lockdown when their infection rate is .6% and just 1% of those infected have died? Could there be a different agenda than what you’ve been led to believe?

– Sources and References

___________________

Go here to see numerous articles on COVID All-cause mortality.

For more:

https://popularrationalism.substack.com/p/fifth-circuit-court-of-appeals-affirms

Fifth Circuit Court of Appeals Affirms: “We Said Hold On There, OSHA”

Citing Natural Immunity and Separation of Powers, a 3-Judge Panel Affirms the TRO after the Biden Administration Complains. And more on “Grave Dangers”.
Warning: Authors at the non-peer-reviewed opinion blog website “HealthFeedback dot org” may wish to take a pharmaceutical to chill their jets before reading.

The Biden administration’s use of OSHA to enforce the COVID-19 vaccine mandate has many problems, and the 5th Circuit Court sees some of the important ones, such as the constitutional issue of separation of powers as well as natural immunity.

The Biden Administration asked the court to lift its stay on the mandate, saying stopping its implementation “would likely cost dozens or even hundreds of lives per day”, to back their false claim of “Grave Danger” to the “unvaccinated”.

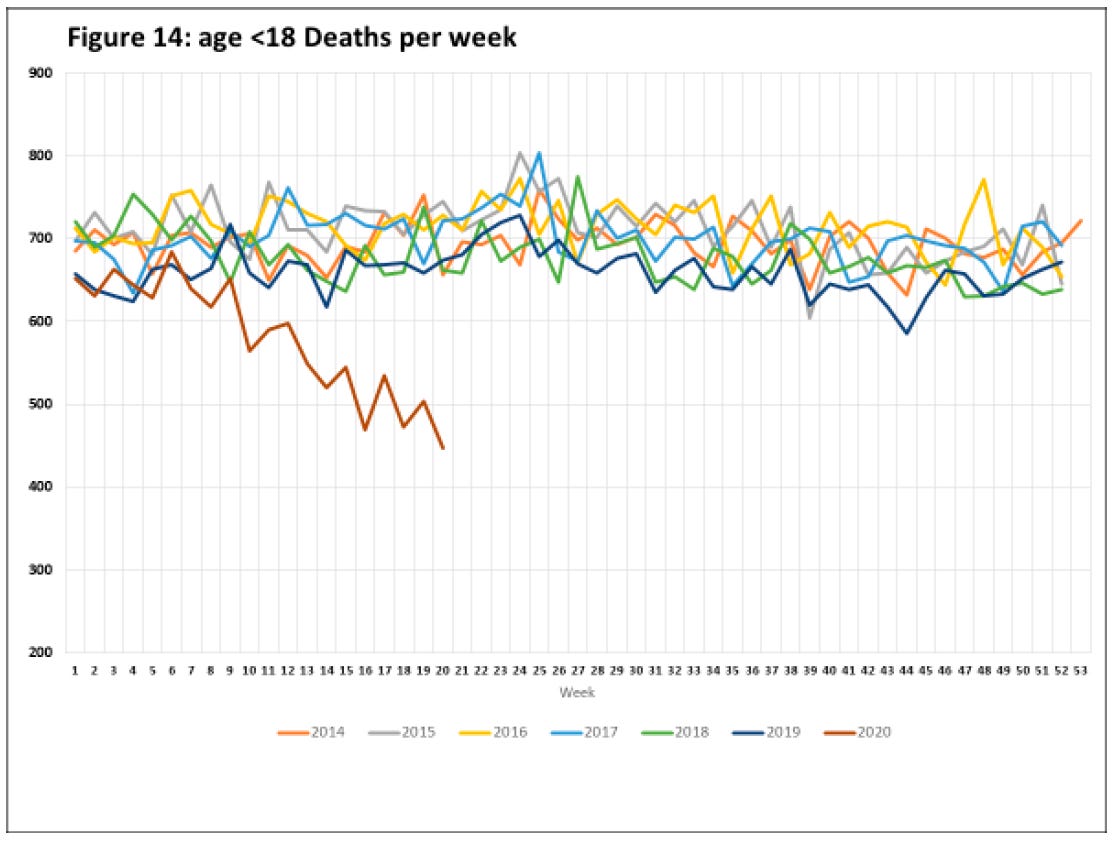
Hundreds Per Day? What About the Kids? And No, Fewer Motor Vehicle Accidents Do Not Explain the Massive Drop in Pediatric Deaths During Lockdown

The term “Grave Danger” brings to mind an interesting pair of facts that were originally brought forward by Mark Blaxill and April Becker.

Fact 1. The CDC has reported significant declines in childhood vaccination rates during the pandemic, ranging from 7% decrease to 20% decrease in childhood vaccination uptake.

Fact 2. Becker and Blaxill published a compelling analysis pointing to a reduction in mortality rates in young people (especially infants) during the pandemic. Their analysis, based on NCHS data, points to hundreds of lives in infants not lost per day during the same period of time when vaccination uptake dropped significantly.

The Omniscient “Fact-Checkers” Weigh In [Sarcasm Alert! for those who need that]

Not surprisingly, self-nominated, non-peer-reviewed “Fact-Checking” opinion blog websites (like this one at “Health Feedback Dot Org” have concluded for themselves that the drop in infant deaths is NOT related to the drop in vaccination, well, because they have special magical powers to discern causality and truth, when no one else can. Their monopoly on truth is self-evident, because their opinion articles are published on their very own blogs on the internet and you can read their words with your own eyes, which must make them true. Their virtue is unparalleled in this regard, and we are ever so grateful for their generosity in sharing their opinions. Plus, they even cite other people’s opinions. Man, that’s amazing.

Ok, back to reality. “Health Feedback Dot Org” cited things like lags in reporting, but “Health Feedback Dot Org” fails to emphasize that Blaxill and Becker did adjust for that. The opinion blog site instead claims that Blaxill and Becker must not have adjusted sufficiently for underreporting… well, because, you know, they just know that.

“Health Feedback Dot Org” also fails to mention the size of CDC’s budget or question why CDC has such deplorable and biased lag times in reporting, such as was found by IPAK Joshua Kuntz Research Scholar Dr. Jessica Rose, who found (in a peer-reviewed research article, not an opinion blog) that CDC held onto serious adverse event data longer than mild adverse events data in the months leading up to key committee meetings to determine policy on COVID-19 vaccination. But I digress.

They jump from guessing that there must be underreporting to 100% fact-holding. Their certainty is remarkable (ahem, their title: “Infant deaths did not decrease during the pandemic due to a reduced use of vaccines” is a causality determination).

They accuse Blaxill and Becker of coming to a definite claim:

“Overall, Blaxill and Becker’s claims are premature because they are based on incomplete data due to underreporting.”

“HealthCheck DOT org” also says that Blaxill and Becker did not consider factors that they consider to be important. Remember that word “important”.

They wrote:

“The article compares… pediatric vaccine uptake during the pandemic to child deaths and does not consider the many other factors which may have contributed to the recent decline in child deaths, such as lockdowns leading to reduced travel and social contact, culminating in fewer traffic accidents and infectious diseases, respectively.”

Blaxill and Becker’s interpretation of their own results is more far tempered than the opinion blog article “Health Feedback Dot Org” would have you believe. They write:

“What has changed during this period that might have such an effect? Are infant deaths not being recorded? Are parents taking better care of their families while working remotely and their children are not going to school? There are many possible hypotheses about the infant death decline.”

Compared to “Health Feedback Dot Org”’s chronically inaccurate assessment and misrepresentation, Becker and Blaxill appear studious, reserved, academic and focused. They estimated 154,029 life-years saved by whatever was causing the drop in deaths in people under 25.

Remember that word “Important?”

According to CDC, 608 child passengers aged 12 and younger died in motor vehicle crashes in 2018. That’s a maximum of 1.66 deaths per day that could possibly have been prevented by less driving during the lockdown, not hundreds.

According to Healthy People.org, 300 children die each year in the US from “vaccine preventable diseases”. 300. So, fewer infectious disease cases due to social isolation, but no vaccination that would allegedly prevented those that would occur in spite of the lockdown, ok, I think I follow, but still, it’s 300 people. Less than one per day.

Vaccine cessation was followed by hundreds of fewer deaths per day and “Health Fact Check Dot Org’s” summoned other causes account for… at most… two.

These are the kinds of distortions that “Fact Check” websites feed the public. They are dangerous sources of misinformation. It is quite possible that pediatric vaccines are killing hundreds of kids per day, and reducing symptoms from infectious diseases. Think of Peter Aaby’s team finding of ten times more mortality from deaths from other causes, including infections following DTP vaccination:

“all currently available evidence suggests that DTP vaccine may kill more children from other causes than it saves from diphtheria, tetanus or pertussis. Though a vaccine protects children against the target disease it may simultaneously increase susceptibility to unrelated infections.”

Grave danger, indeed. Becker and Blaxill have done a service to humanity for pointing out the possible link between pediatric vaccinations and pediatric mortality.

Back to the OSHA case, the FACT is that the Fifth Circuit Court of Appeals has called bullshit on OSHA’s administrative rule on some very important fundamental points – including the importance of recognizing natural immunity and the separation of powers mandated by the US Constitution – and when the Biden administration complained, they repeated their assessment more firmly.

The panel wrote:

“The mandate is a one-size-fits-all sledgehammer that makes hardly any attempt to account for differences in workplaces (and workers).”

And,

“We next consider the necessity of the Mandate. The Mandate is staggeringly overbroad. Applying to 2 out of 3 private-sector employees in America, in workplaces as diverse as the country itself, the Mandate fails to consider what is perhaps the most salient fact of all: the ongoing threat of COVID-19 is more dangerous to some employees than to other employees. All else equal, a 28 year-old trucker spending the bulk of his workday in the solitude of his cab is simply less vulnerable to COVID-19 than a 62 year-old prison janitor. Likewise, a naturally immune unvaccinated worker is presumably at less risk than an unvaccinated worker who has never had the virus. The list goes on, but one constant remains-the Mandate fails almost completely to address, or even respond to, much of this reality and common sense.”

Fact check that.

Credit to John Gilmore, Autism Action Network for the quips from the 5th Circuit Court of Appeals.

Reference

  1. Becker, A and M Blaxill. Why are so many fewer children dying? July, 2020 https://healthchoice.org/lessons-from-the-lockdown/
  2. Some Bullshit Opinion Article on the Internet.
  3. Mogensen, Søren Wengel et al. The Introduction of Diphtheria-Tetanus-Pertussis and Oral Polio Vaccine Among Young Infants in an Urban African Community: A Natural Experiment. EBioMedicine vol. 17 (2017): 192-198. doi:10.1016/j.ebiom.2017.01.041
  4. Jessica Rose, 2021. Critical appraisal of VAERS Pharmacovigilance: Is the U.S. Vaccine Adverse Events Reporting System (VAERS) a functioning pharmacovigilance system? Sci, Publ Health Pol & Law 3:100-129. https://www.publichealthpolicyjournal.com/general-5  Related: https://www.forbes.com/sites/kimberleespeakman/2021/11/12/federal-appeals-court-reaffirms-decision-to-temporarily-halt-biden-administration-covid-19-vaccine-mandate/

__________________

https://popularrationalism.substack.com/p/the-argument-over-natural-immunity

The Argument Over Natural Immunity is Over. It’s Time to Update Policy.

Science shows robust and durable T-cell immunity to variants. Now, CDC admits no record of unvaccinated person who had COVID-19 spreading.

At one time, there was a great amount of concern of people who had COVID-19 being re-infected and getting sick again.

Public health policies, including the rationalization of universal vaccination with endless boosters, and OSHA’s recent and highly challenged universal administrative rule, have been based on the theoretical possibility that those with past COVID-19 infections may still spread the SARS-CoV-2 virus, but evidence on viral escape from natural immunity has been scarce.

By contrast, a study in Genomics published in July, 2021 found Vaccine Escape and Vaccine-Weakening mutations in the receptor binding domain of the SARS-CoV-2 virus (See “Vaccine-escape and fast-growing mutations in the…”).

The theoretical concern over escape from infection is comparatively weak. A study in PNAS predicted that SARS-CoV-2 would evolve to escape polyclonal antibodies produced against the viral proteins during infection (See SARS-CoV-2 escape from a highly neutralizing COVID-19 convalescent plasma). This theoretical analysis reported that “only three mutations were necessary” for the virus to escape infection-acquired immunity to existing immunity to the spike protein. The study did not provide any probability of such escape happening and failed to distinguish between polyclonal immunity to multiple proteins, as happens in SARS-CoV-2 infection, and immunity to the single spike protein, which may occur in persons who have had mRNA vaccines.

Public health policies have been based on the premise that natural immunity does not play an important role in protecting individuals. OSHA’s recent administrative rule requires that those who have survived COVID-19 still need to vaccinate, or test & mask due to OSHA’s concern over accuracy of tests for immunity. (Ironically, OSHA shows no concern over accuracy of the use of PCR tests for case discernment, a problem that has long been recognized by scientists around the globe).

All of that changed this week when The Gateway Pundit shared the contents of a letter, obtained via FOIA from the US CDC admitting that they have no record of anyone who has recovered from SARS-CoV-2 infection spreading the virus post-recovery.

From Pundit:

“The CDC admitted it has no record of an unvaccinated person spreading Covid after recovering from Covid in response to an attorney’s FOIA request.

A New York attorney filed a FOIA request in September asking for “documents reflecting any documented case of an individual who (1) never received a Covid-19 vaccine; (2) was infected with Covid-19 once, recovered, and then later became infected again; and (3) transmitted SARS CoV-2 to another person when reinfected.”

The CDC responded: ‘A search of our records failed to reveal any documents pertaining to your request. The CDC Emergency Operation Center (EOC) conveyed that this information is not collected.’”

The Pundit article includes a Tweet linking to the CDC’s response letter, as well as a Tweet from Senator Rand Paul that mentions this peer-reviewed study published in the journal Open Forum Infectious Diseases.

CD8+ T cell responses in COVID-19 convalescent individuals target conserved epitopes from multiple prominent SARS-CoV-2 circulating variants

Oddly, the Pubmed database labels this study as a “Preprint”, while clearly (from the publisher’s website) it has now survived peer review.

Long-term immunity to the SARS-CoV-2 virus is expected following COVID-19 infection given the large number of immunogenic epitopes present in the proteome of the virus. In April 2020, I published an analysis (validated by Harvard University) in which I identified over 50 epitopes in the SARS-CoV-2 proteome (See: Pathogenic priming likely contributes to serious and critical illness and mortality in COVID-19 via autoimmunity).

The SARS-CoV-2 vaccines from Moderna and Pfizer target one protein. This has led to grave concern over “vaccine escape”. One article in The Lancet predicted vaccine escape within six months if the number of cases remains too high (See SARS-CoV-2 incidence and vaccine escape). The madness of mass vaccination during an epidemic was known; if the vaccine is imperfect (i.e,, “leaky”), vaccine escape is all but assured. Vaccine efficacy has plummeted, and is now likely below 50% for all three vaccines in use in the US (See Do COVID-19 Vaccines Still Qualify for Emergency Use Authorization?)

Broad and Durable beats Narrow and Temporary

A longitudinal study in Cell Reports Medicine followed 254 patients with mostly mild to moderate symptoms of SARS-CoV-2 infection over a period for more than eight months (250 days). The study authors reported that the patients’ immune responses to the virus remained durable and strong. (See Longitudinal analysis shows durable and broad immune memory after SARS-CoV-2 infection with persisting antibody responses and memory B and T cells).

Studies reporting durable immunity from vaccines are less reassuring, as the vaccination program does not provide redundant immunity due to polyclonal antibodies to the myriad immunogenic epitopes provided by SARS-CoV-2 infection.

If public health policy in the US were at all science-based, those who have B- and T-cells would be exempt from vaccination, masking, social distancing and should not have their livelihoods threatened by administrative rules agnostic to the on-the-ground, real-world and peer-review data.

_________________

**Comment**

But alas, U.S. public Health policy is NOT science-based and has been completely and utterly corrupted by Big Pharma.

https://www.greenmedinfo.com/blog/osteoporosis-myth-dangers-high-bone-mineral-density

The Manufacturing of Bone Diseases: The Story of Osteoporosis and Osteopenia

The present-day definitions of osteopenia and osteoporosis were arbitrarily conceived by the World Health Organization (WHO) in the early ’90s and then projected upon millions of women’s bodies seemingly in order to convince them they had a drug-treatable, though symptomless, disease

Osteopenia (1992)[i] and osteoporosis (1994)[ii] were formally identified as skeletal diseases by the World Health Organization (WHO) as bone mineral densities (BMD) 1 and 2.5 standard deviations, respectively, below the peak bone mass of an average young adult Caucasian female, as measured by an X-ray device known as dual energy X-ray absorptiometry (DXA, or DEXA). This technical definition, now used widely around the world as the gold standard, is disturbingly inept, and as you shall see, likely conceals an agenda that has nothing to do with the promotion of health.

Deviant Standards: Aging Transformed Into a Disease

A “standard deviation” is simply a quantity calculated to indicate the extent of deviation for a group as a whole, i.e., within any natural population there will be folks with higher and lower biological values, e.g., height, weight, bone mineral density, cholesterol levels. The choice of an average young adult female (approximately 30 years old) at peak bone mass in the human lifecycle as the new standard of normality for all women 30 or older, was, of course, not only completely arbitrary but also highly illogical. After all, why should an 80-year-old’s bones be defined as “abnormal” if they are less dense than a 30-year-old’s?

Within the WHO’s new BMD definitions the aging process is redefined as a disease, and these definitions targeted women, much in the same way that menopause was once redefined as a “disease” that needed to be treated with synthetic hormone replacement therapies (HRT); that is, before the whole house of cards collapsed with the realization that by “treating” menopause as a disease the medical establishment was causing far more harm than good, e.g., heart disease, stroke and cancer.

As if to fill the void left by the HRT debacle and the disillusionment of millions of women, the WHO’s new definitions resulted in the diagnosis, and subsequent labeling, of millions of healthy middle-aged and older women with what they were now being made to believe was another “health condition,” serious enough to justify the use of expensive and extremely dangerous bone drugs (and equally dangerous mega-doses of elemental calcium) in the pursuit of increasing bone density by any means necessary. 

One thing that cannot be debated, as it is now a matter of history, is that this sudden transformation of healthy women, who suffered no symptoms of “low bone mineral density,” into an at-risk, treatment-appropriate group, served to generate billions of dollars of revenue for DXA device manufacturers, doctor visits and drug prescriptions around the world.The Manufacture of a Disease

WHO Are They Kidding?

Osteopenia is, in fact, a medical and diagnostic non-entity. The term itself describes nothing more than a statistical deviation from an arbitrarily determined numerical value or norm. According to the osteoporosis epidemiologist Dr. L. Joseph Melton at the Mayo Clinic who participated in setting the original WHO criteria in 1992, “[osteopenia] was just meant to indicate the emergence of a problem,” and he noted, “It didn’t have any particular diagnostic or therapeutic significance. It was just meant to show a huge group who looked like they might be at risk.“[iii] Another expert, Dr. Michael McClung, director of the Oregon Osteoporosis Center, criticized the newly adopted disease category osteopenia by saying, ”We have medicalized a nonproblem.”[iv]

In reality, the WHO definitions violate both commonsense and fundamental facts of biological science — sadly, an increasingly prevalent phenomenon within drug-company-funded science. After all, anyone over 30 years of age should have lower bone density than a 30-year-old, as this is consistent with the normal and natural healthy aging process. And yet, according to the WHO definition of osteopenia, the eons-old programming of your body to gradually shed bone density as you age, is to be considered a faulty design and/or pathology in need of medical intervention.

How the WHO, or any other organization that purports to be a science-based “medical authority,” can make an ostensibly educated public believe that the natural thinning of bones is not normal, or more absurdly, a disease, is astounding. In defense of the public, the cryptic manner in which these definitions and diagnoses have been cloaked in obscure mathematical and clinical language makes it rather difficult for the layperson to discern just how outright insane the logic they are employing really is.

So, let’s look closer at the definitions now, which are brilliantly elucidated by Washington.edu’s published online course on Bone Densitometry, which can be viewed in its entirety here.

The Manufacture of a Disease Through Categorical Sleight-of-Hand

bone mineral density loss

The image above shows the natural decrease in hip bone density occurring with age, with variations in race and gender depicted. Observe that loss of bone mineral density with age is a normal process.

Bell Curve Bones

Next is the classical bell-shaped curve, from which T- and Z-scores are based. T-sores are based on the young adult standard (30-year-old) bone density as being normal for everyone, regardless of age, whereas the much more logical Z-score compares your bone mineral density to that of your age group, as well as sex and ethnic background. Now here’s where it gets disturbingly clear how ridiculous the T-score really system is:

WHO definitions osteoporosis

Above is an image showing how within the population of women used to determine “normal” bone mineral density, e.g., 30-year-olds, 16% of them already “have” osteopenia, according to the WHO definitions, and 3% already “have” osteoporosis! According to Washington.edu’s online course, “One standard deviation is at the 16th percentile, so by definition, 16% of young women have osteopenia! As shown below, by the time women reach age 80, very few are considered normal.”

Osteopenia and Osteoporosis Rates with Age

Above you will see what happens when the WHO definitions of “normal bone density” are applied to aging populations. Whereas at age 25, 15% of the population will “have” osteopenia, by age 50 the number grows to 33%. And by age 65, 60% will be told they have either osteopenia (40%) or osteoporosis (20%).

On the other hand, if one uses the Z-score, which compares your bones to that of your age group, something remarkable happens: a huge burden of “disease” disappears! In a review on the topic published in 2009 in the Journal of Clinical Densitometry, 30% to 39% of the subjects who had been diagnosed with osteoporosis with two different DXA machine models were reclassified as either normal or “osteopenic” when the Z- score was used instead of the T-score. The table, therefore, can be turned on the magician-like sleight-of-hand used to convert healthy people into diseased ones, as long as an age-appropriate standard of measurement is applied, which presently it is not.

Bone Scans or Scams? How Dense Bones Can Harm Your Health

Bone Mineral Density Is NOT Equivalent to Bone Strength

As you can see there are a number of insurmountable problems with the WHO’s definitions, but perhaps the most fatal flaw is the fact that the DXA is only capable of revealing the mineral density of the bone, and this is not the same thing as bone quality/strength.

While there is a correlation between bone mineral density and bone quality/strength — that is to say, they overlap in places — they are not equivalent. In other words, density, while an excellent indicator of compressive strength (resisting breaking when being crushed by a static weight), is not an accurate indicator of tensile strength (resisting breaking when being pulled or stretched).

Indeed, in some cases having higher bone density indicates that the bone is actually weaker. Glass, for instance, has high density and compressive strength, but it is extremely brittle and lacks the tensile strength required to withstand easily shattering in a fall. Wood, on the other hand, which is closer in nature to human bone than glass or stone, is less dense relative to these materials, but also extremely strong relative to them, capable of bending and stretching to withstand the very same forces that the bone is faced with during a fall. Or, take spider web. It has infinitely greater strength and virtually no density. Given these facts, having “high” bone density (and thereby not having osteoporosis) may actually increase the risk of fracture in a real-life scenario like a fall.

Essentially, the WHO definitions distract from key issues surrounding bone quality and real world bone fracture risks, such as gait and vision disorders.[v] In other words, if you are able to see and move correctly in your body, you are less likely to fall, which means you are less prone to fracture. Keep in mind also that the quality of human bone depends entirely on dietary and lifestyle patterns and choices, and unlike X-ray based measurements, bone quality is not decomposable to strictly numerical values, e.g., mineral density scores.

Vitamin K2 and soy isoflavones, for instance, significantly reduce bone fracture rates without increasing bone density. Scoring high on bone density tests may save a woman from being intimidated into taking dangerous drugs or swallowing massive doses of elemetal calcium, but it may not translate into preventing “osteoporosis,” which to the layperson means the risk of breaking a bone. But high bone mineral density may result in far worse problems.

High Bone Mineral Density & Breast Cancer

High Bone Mineral Density & Breast Cancer

One of the most important facts about bone mineral density, conspicuously absent from discussion, is that having higher-than-normal bone density in middle-aged and older women actually INCREASES their risk of breast cancer by 200% to 300%, and this is according to research published in some of the world’s most well-respected and authoritative journals, e.g., Lancet, JAMA, NCI. (see citations below).

While it has been known for at least 15 years that high bone density profoundly increases the risk of breast cancer — and particularly malignant breast cancer — the issue has been given little to no attention, likely because it contradicts the propaganda expounded by mainstream women’s health advocacy organizations. Breast cancer awareness programs focus on X-ray based breast screenings as a form of “early detection,” and the National Osteoporosis Foundation’s entire platform is based on expounding the belief that increasing bone mineral density for osteoporosis prevention translates into improved quality and length of life for women.

The research, however, is not going away, and eventually these organizations will have to acknowledge it or risk losing credibility.

High Bone Density: More Harm Than Good

The present-day fixation within the global medical community on “osteoporosis prevention” as a top women’s health concern is simply not supported by the facts. The No. 1 cause of death in women today is heart disease, and the No. 2 cause of death is cancer, particularly breast cancer, and not death from complications associated with a bone fracture or break. In fact, in the grand scheme of things osteoporosis or low bone mineral density does not even make the CDC’s top 10 list of causes of female mortality. So, why is it given such a high place within the hierarchy of women’s health concerns? Is it a business decision or a medical one?

Regardless of the reason or motive, the obsessive fixation on bone mineral density is severely undermining the overall health of women. For example, the mega-dose calcium supplements being taken by millions of women to “increase bone mineral density” are known to increase the risk of heart attack by 24% to 27%, according to two 2011 meta-analyses published in Lancet, and 86% according to a more recent meta-analysis published in the journal Heart. Given the overwhelming evidence, the 1,200+ milligrams of elemental calcium the National Osteoporosis Foundation (NOF) recommends women 50 and older take to “protect their bones” may very well be inducing coronary artery spasms, heart attacks and calcified arterial plaque in millions of women. Considering that the NOF named calcium supplement manufacturers Citrical and Oscal as corporate sponsors, it is unlikely their message will change anytime soon.

Now, when you consider the case of increased breast cancer risk linked to high bone mineral density, being diagnosed with osteopenia or osteoporosis would actually indicate a significantly reduced risk of developing the disease. What is more concerning to women: breaking a bone (from which you can heal) or developing breast cancer? If it is the latter, a low BMD reading could be considered cause for celebration and not depression, fear and the continued ingestion of inappropriate medications or supplements, which is usually the case following a diagnosis of osteopenia or osteoporosis.

I hope this article will put to rest any doubts that the WHO’s fixation on high bone density was designed not to protect or improve the health of women, but rather to convert the natural aging process into a blockbuster disease, capable of generating billions of dollars of revenue.

Learn more on the GreenMedInfo.com database:


References

[i] WHO Scientific Group on the Prevention and Management of Osteoporosis (2000 : Geneva, Switzerland) (2003). “Prevention and management of osteoporosis : report of a WHO scientific group” (PDF). Retrieved 2007-05-31.

[ii] WHO (1994). “Assessment of fracture risk and its application to screening for postmenopausal osteoporosis. Report of a WHO Study Group”. World Health Organization technical report series 843: 1-129. PMID 7941614.

[iii] Kolata, Gina (September 28, 2003). “Bone Diagnosis Gives New Data But No Answers”. New York Times.

[iv] Ibid

[v] P Dargent-Molina, F Favier, H Grandjean, C Baudoin, A M Schott, E Hausherr, P J Meunier, G Bréart Fall-related factors and risk of hip fracture: the EPIDOS prospective study. Lancet. 1996 Jul 20;348(9021):145-9. PMID: 8684153