https://odysee.com/@neverlosetruth:0/What-MSM-Will-NOT-Report—Pandemic-Of-The-Vaccinated,-Numbers-Of–Deaths—Horrific-Injuries-Keep-Increasing  Video Here  (Approx. 24 Min)  **Warning** It gets pretty graphic at about 11:15

What MSM Will NOT Report – It’s A Pandemic Of The ‘Vaccinated’, Numbers Of Deaths & Horrific Injuries Keep Increasing

November 7th, 2021

In this video doctors, nurses and other health care providers talk about the untold number of patients who are experiencing serious side effects and even death from the COVID-19 jabs, and they ask why the media aren’t reporting it.

The ‘vaccinated’ are succumbing to numerous adverse reactions that are sending them to the hospital, they say. One hospital worker says he’s seen “32 elderly people pass away my facility immediately after the Moderna vaccine. None of that is being talked about on the news.”

“I don’t know why the lies continue,” another health care provider says as she questions why this isn’t being told. “I see it every single day. I have seen nothing but ‘vaccinated’ individuals.”

____________________

https://www.brighteon.com/4d09fc49-5baa-4811-97c0-5285d6f6fe51  Video Here  (Approx. 24 min)

3 BOMBS DROPPED at Health and Freedom: Dr. Judy Mikovits & Mikki Willis

NOVEMBER 13, 2021

In a rare dual interview, Dr. Judy Mikovits, author of Plague, One Scientist’s Intrepid Search for the Truth About Human Retroviruses and Chronic Fatigue Syndrome, Autism, and Other Diseases and Ending Plague: A Scholar’s Obligation in an Age of Corruption, and Mikki Willis, producer of the Plandemic Series and Author of the book, Plandemic: Fear Is the Virus. Truth Is the Cure drop some truth bombs  at the Health and Freedom Conference.

For more:

https://www.lymedisease.org/post-infectious-fatigue-vagus-nerve/

LYME SCI: Post-infectious fatigue and your vagus nerve

By Lonnie Marcum

Nov. 3, 2021

In 2013, the pain management clinic at a large teaching hospital diagnosed my then-15-year-old daughter with Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS). This was after 10 months of being referred to many pediatric specialists, none of whom could find an answer to her mysterious illness.

One of the hallmarks of ME/CFS is post-exertional malaise—profound fatigue following activity that is not restored by rest. Fatigue is also the most common symptom reported in patients with Lyme disease. (Aucott 2013, Johnson 2014)

At the time of my daughter’s diagnosis, she was mostly bedbound. An hour of homework would require a week of recovery. She had many symptoms of Lyme disease (fatigue, headache, light sensitivity, memory loss, heart block, POTS, swollen knee, muscle pain, nausea…the list goes on) but three separate standard tests for Lyme were negative.

In the absence of a definitive diagnosis, patients are often lumped into the category of ME/CFS—a complex and disabling syndrome. First defined by the CDC in 1988, the symptoms of ME/CFS have been recorded for centuries. (Holmes, 1988)

The million-dollar question?

There is no question that many infectious agents can trigger chronic illness. Past pandemics with infection-triggered chronic fatigue include: Russian influenza 1889, polio 1916, SARS-CoV-1 2003, Zika 2015, Ebola 2016, and more recently, COVID 2019.

But not everyone who contracts these diseases becomes chronically ill. As PolyBio researcher Amy Proal, PhD, said at the 2021 LymeMind conference, “The million-dollar question is why? Why do some patients go on to develop long-term, chronic symptoms and others do not?”

Even more puzzling is why do patients infected with completely different pathogens (viruses, bacteria, parasites) have so many of the same flu-like symptoms?

For example, the pathogens that cause COVID-19 (SARS-CoV-2, a virus) and Lyme disease (Borrelia burgdorferi, a bacterium) are vastly different. However, the chronic symptoms they leave behind are nearly identical: fatigue, brain fog, headaches, sensory issues, cognitive impairment, memory loss, sleep impairment, heart issues, muscle and joint aches/pain. The primary difference here being the respiratory symptoms among those with COVID-19. (Proal & VanElzakker 2021)

During the LDA/Columbia Lyme Conference, Dr. John Aucott, of Johns Hopkins University, reviewed several potential causes of “long-haul” symptoms for infectious diseases such as Lyme disease and COVID-19. These include: 1) persistent antigens and/or persistent infection; 2) immune inflammation and dysregulation; 3) neural network alterations.

One pathway that links all three of these elements (infection, inflammation, nervous system) together is called the vagus nerve. And one theory gaining recognition is the vagus nerve infection hypothesis, first proposed by Harvard neuroscientist Michael VanElzakker in 2013. (VanElzakker, 2013)

Because we know that Borrelia can infect the brain and the cranial nerves, this theory may explain why some patients remain ill following treatment for Lyme disease. (Gadila, 2021)

What is the vagus nerve?

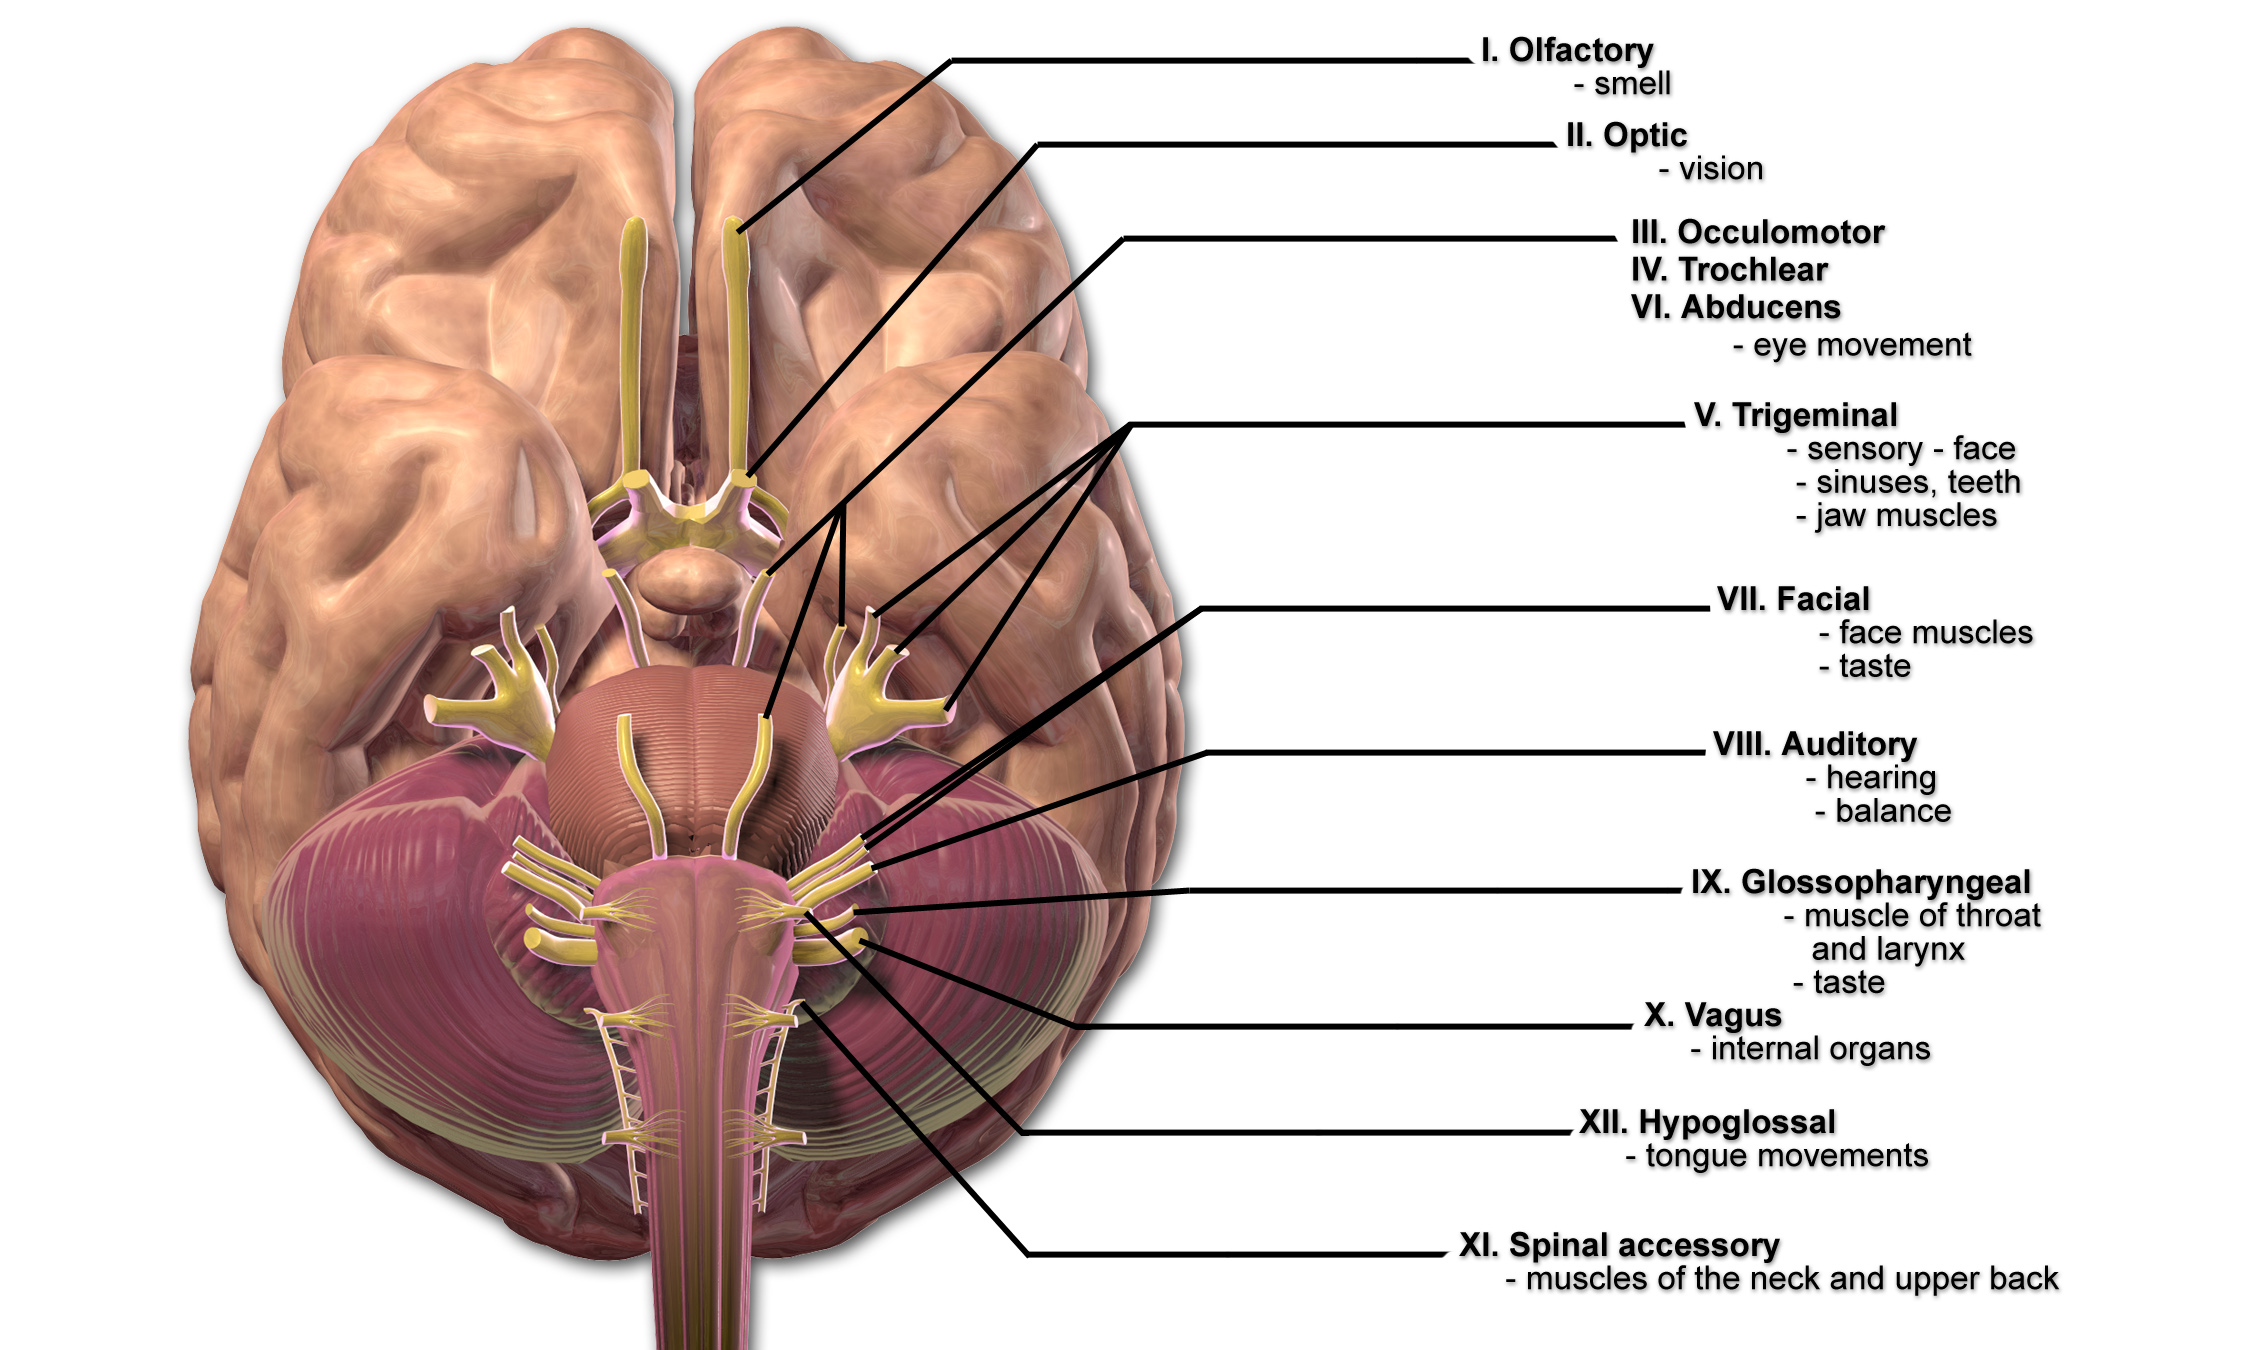
The vagus nerve is the tenth (X) of 12 cranial nerves originating in the brain, denoted as CN-X. It originates from a portion of the brain responsible for autonomic function.
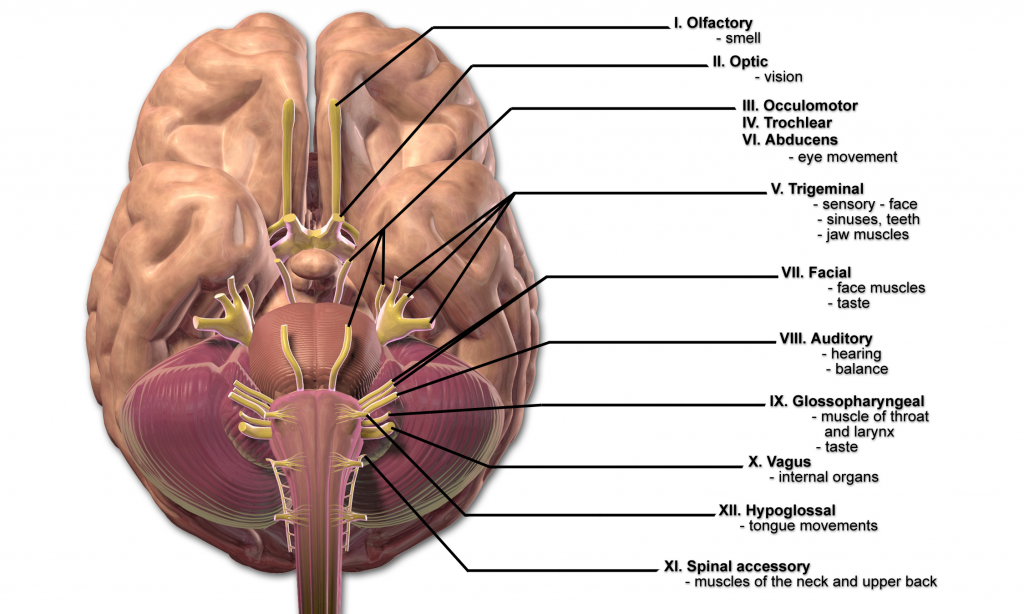
Blausen.com staff (2014). “Medical gallery of Blausen Medical 2014”. WikiJournal of Medicine 1

The autonomic nervous system (ANS) is the part of the nervous system that functions without you having to think about it. It regulates bodily functions such as breathing, heart rate, digestion, and blood pressure.

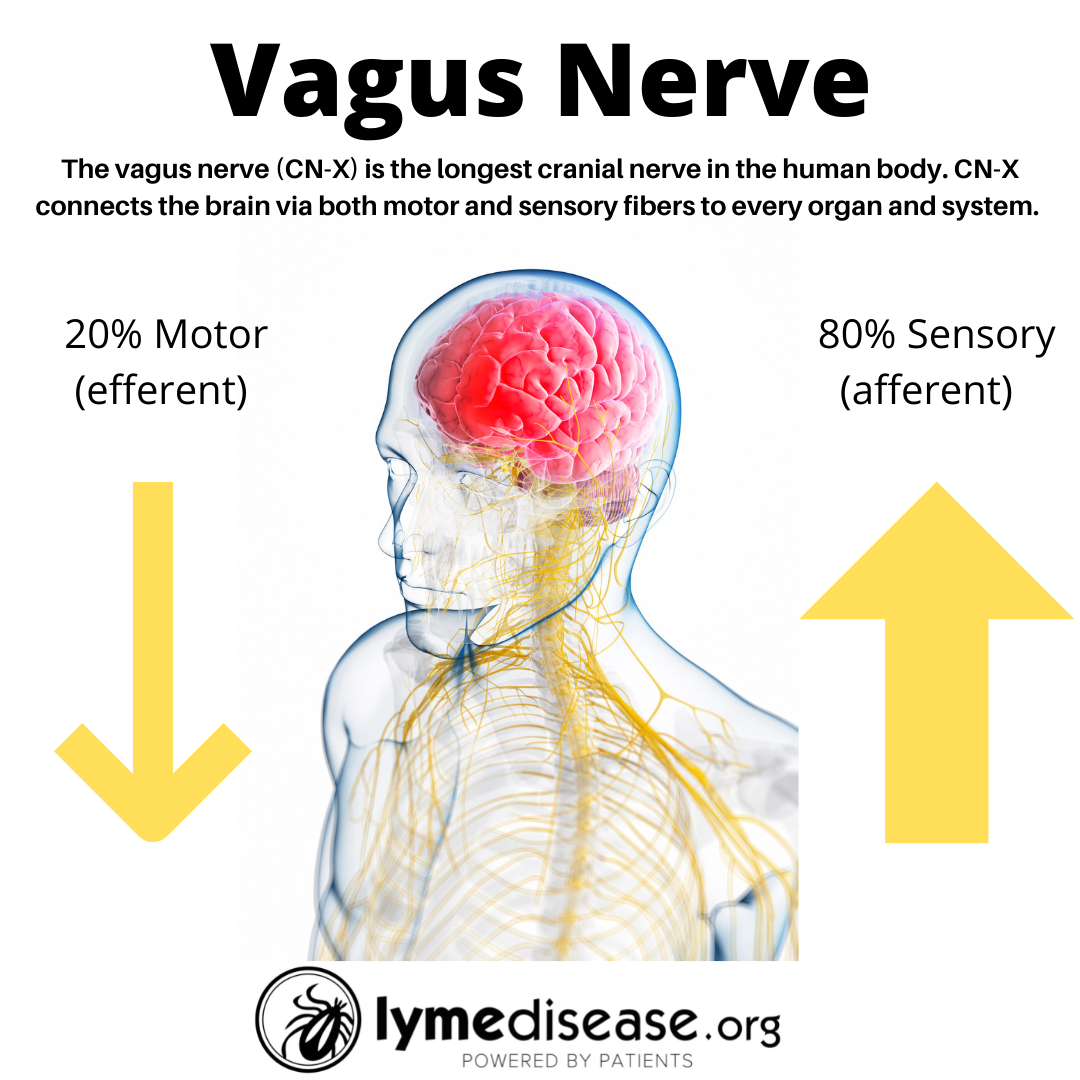
The vagus is the longest cranial nerve in the body. It innervates (supplies nerves to) every major trunk organ including the pancreas, liver, spleen, heart and bladder, along with the gastrointestinal lining and lymph nodes (Kenny and Bordoni, 2019). The Latin word vagus means “wandering.”

Twenty percent of the vagus nerve fibers lead away from the brain into the body (efferent), while 80 percent of the nerve fibers send signals from various points in the body back to the brain (afferent).
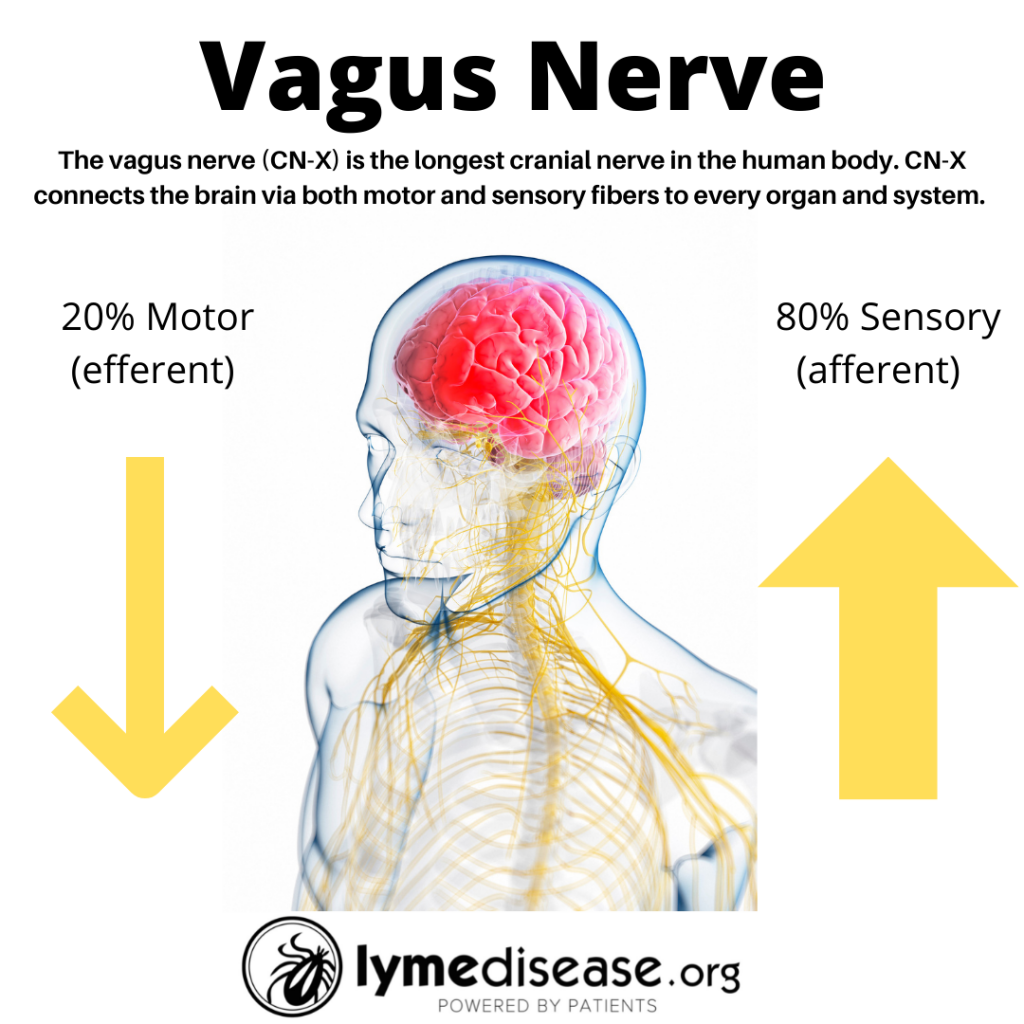
The most important function of the vagus nerve is afferent signaling. This is information brought from the inner organs—such as gut, liver, heart, and lungs—to the brain. Thus, our inner organs are a major source of sensory information to the brain.

The limbic system, amygdala and insular cortex are important central regions that are affected by vagus nerve signals. These areas of the brain are involved in regulating emotions, behavior, memory, and energy.

How does the vagus nerve affect autonomic function?

The ANS is divided into the sympathetic nervous system and the parasympathetic nervous system.

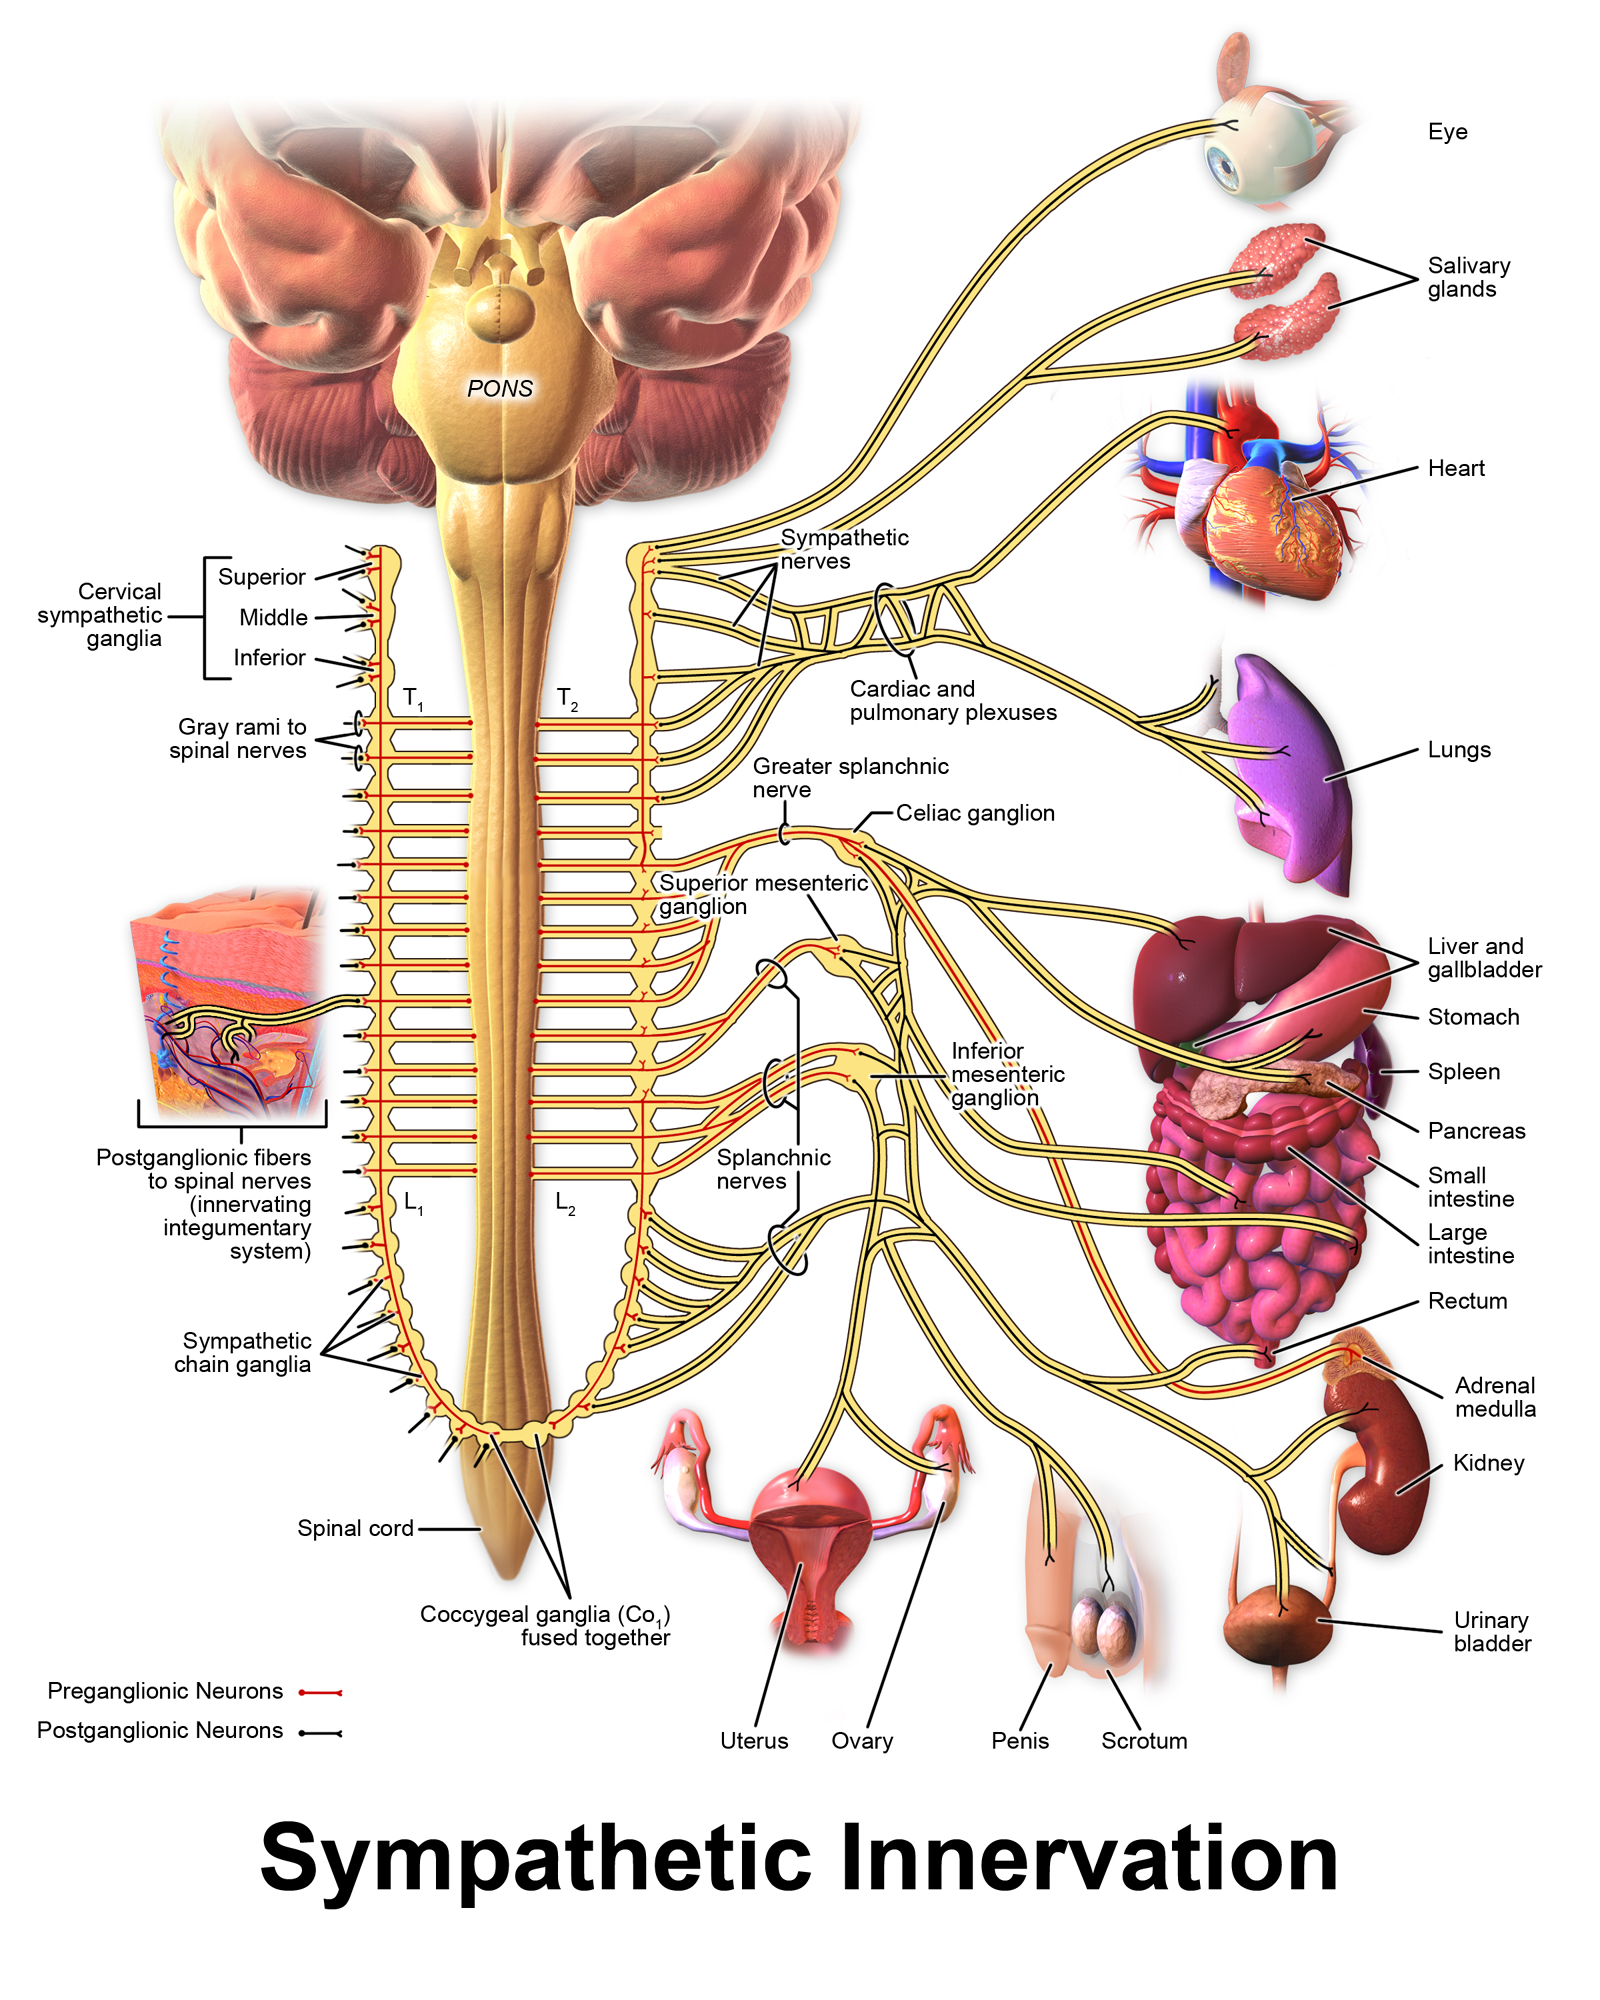
The sympathetic nervous system (SNS) is often referred to as the “fight or flight” or “excitatory” system. It is a primitive system designed to respond and help you get out of danger.
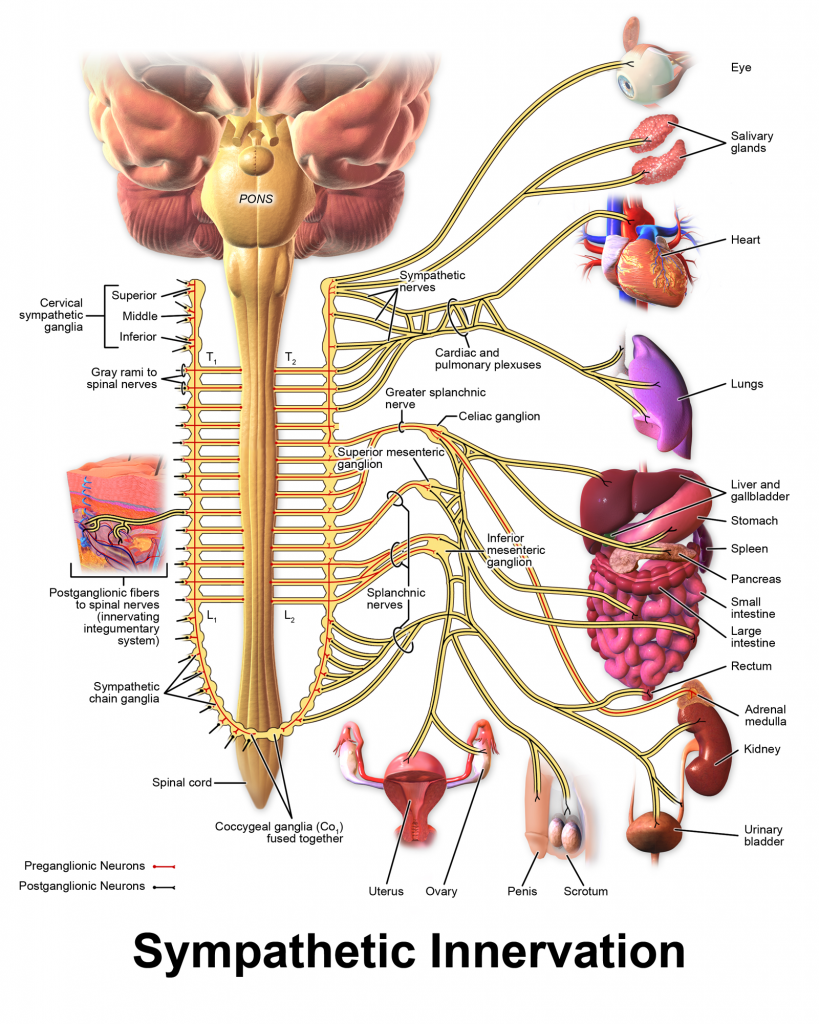
Blausen.com staff (2014). “Medical gallery of Blausen Medical 2014”. WikiJournal of Medicine 1

The parasympathetic nervous system (PNS), commonly known as the “rest and digest” or “inhibitory” system, promotes the opposite response of the SNS.
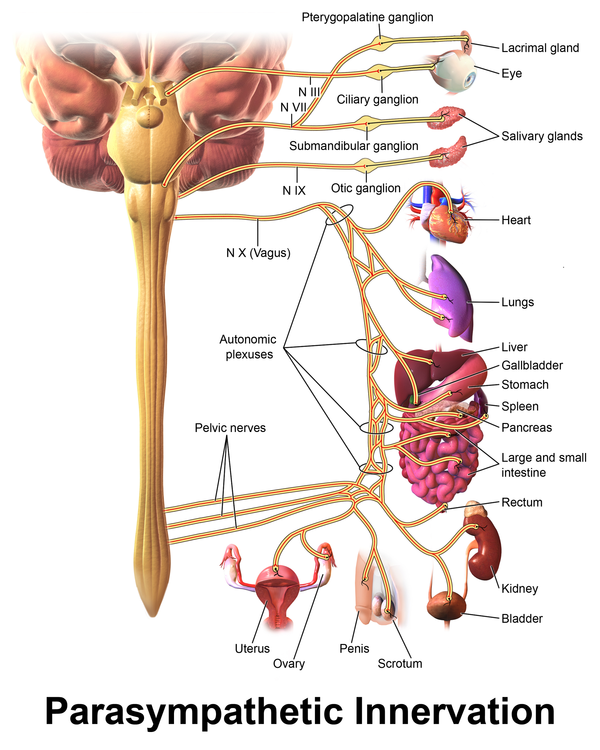
Blausen.com staff (2014). “Medical gallery of Blausen Medical 2014”. WikiJournal of Medicine 1

Both the SNS and PNS are involved when you become sick. Because we cannot feel, smell or see pathogens, the body uses the vagus nerve to sense when we are ill and send a message to the brain. This message triggers an adaptive response to the infection called “sickness behavior” or the “sickness response.”

However, if the infection or inflammation persists, this sickness response can become chronic, resulting in ME/CFS type symptoms.

How the vagus nerve causes flu-like symptoms

When a pathogen is detected, mast cells and glial cells release inflammatory markers and cytokines that trigger an immune response. The vagus nerve senses these markers and sends a message to the brain.  This causes flu-like symptoms: fever, fatigue, headache, sleep problems, loss of appetite, muscle/joint pain, nausea, autonomic dysfunction, cognitive dysfunction, and others.

This constellation of symptoms causes a sickness response that is designed to make us rest. Ideally, during this rest period our body can use all its energy to fight the infection and recover from the illness. Farmers and pet owners may recognize such sickness behavior in their sick animals, as well.

For years, it has been thought that Borrelia spread to the nervous system via the blood stream. A recent publication indicates that central nervous system involvement in Lyme neuroborreliosis may be a result of Borrelia moving from the skin to the spinal cord via peripheral nerves. (Ogrinc, 2021)

The vagus nerve may be a pathway for this type of infection.

Vagus nerve infection hypothesis

The vagus nerve infection hypothesis theorizes that the chronic flu-like symptoms of ME/CFS are an exaggerated version of normal sickness behavior triggered by infection of the vagus nerve.

In theory, any infectious agent with a preference for nervous tissues (neurotropic) can cause a vagus nerve infection, including Borrelia.

The gut-brain axis

The gut is the largest organ innervated by the vagus nerve, making it a particularly important sensory organ. (Breit, 2018) Gut bacteria (both good and bad) communicate through the microbiota-gut-brain axis in a bidirectional way that directly involves the vagus nerve. (Bonaz, 2018)

A huge amount of data has highlighted a potential role of microbial dysbiosis (an imbalance of bacteria in the gut) in various chronic disorders (Lynch and Pedersen, 2016).

The standard treatment for Lyme disease involves the use of antibiotics, which can adversely affect gut bacteria. Researchers at Northeastern University are currently looking at how the microbiome may contribute to the chronic symptoms of Lyme.

Not only can imbalance of the microflora or microbiome in the gut cause inflammation that triggers the vagus nerve, but it can also contribute to a leaky blood-brain barrier contributing further to neurological and psychological symptoms in Lyme.

Treatment

Obviously, if there is an infection present it should be treated appropriately. Lyme disease is often accompanied with co-infections carried by the same tick, a separate tick bite, or possibly even a prior latent viral infection. Thus, treatment may involve antibiotics, anti-parasitics and antivirals.

As a benefit, some of the standard medications for Lyme disease have anti-inflammatory effects on the nervous system. However, not all of them are able to cross the blood-brain barrier.

For example, minocycline crosses the blood-brain barrier and in addition to anti-microbial activity, it has been shown to have anti-inflammatory, anti-apoptotic activities, inhibition of proteolysis, angiogenesis and tumor metastasis-inflammatory as well as neuro-protective properties. (Garrido-Mesa, 2013)

Self-Help

Following treatment, or even during treatment, if you are exhibiting symptoms of dysautonomia (dysfunction of the ANS), you may want to  try some of the non-prescription practices that worked for my daughter.

Another technique is the use of external (transdermal) vagus nerve stimulation, similar to a home TENS unit. (Diedrich 2021)

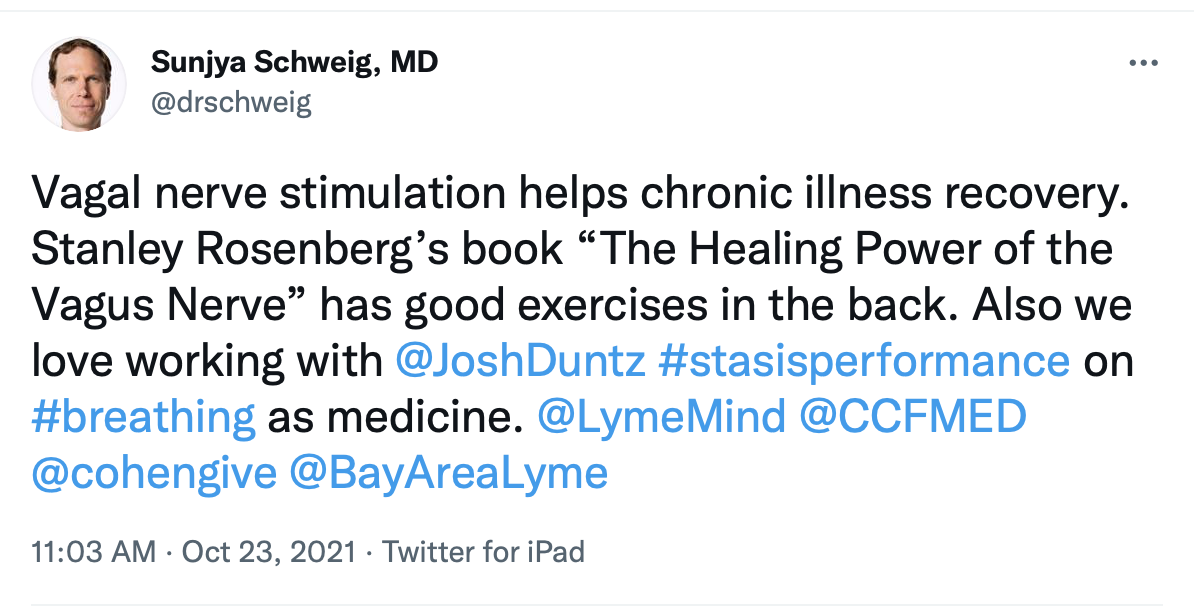
During the LymeMind conference, Dr. Sunjya Schweig, an integrative medicine specialist, tweeted this:
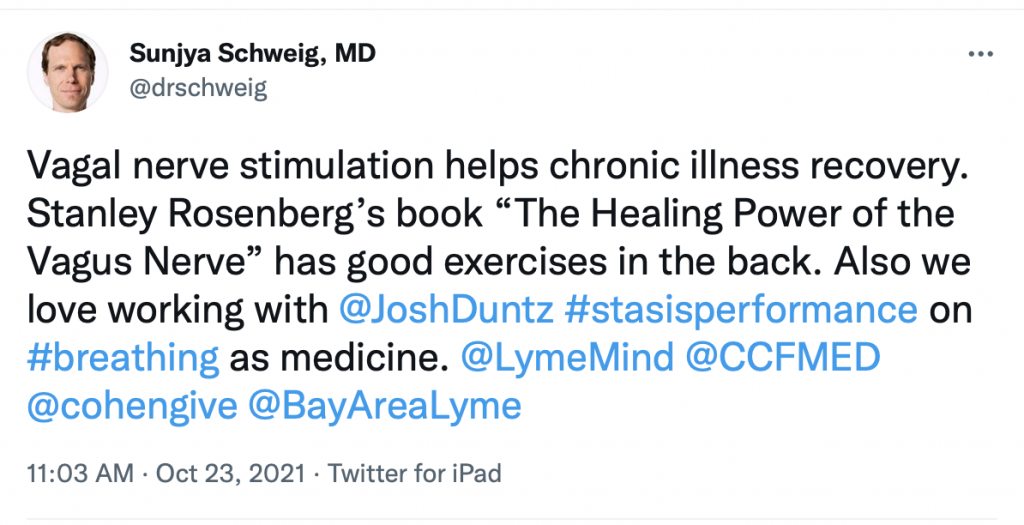
Stanley Rosenberg’s 2017 book “Accessing the Healing Power of the Vagus Nerve: Self-Help Exercises for Anxiety, Depression, Trauma, and Autism” offers a simple explanation of Stephen Porges’s polyvagal theory.

Rosenberg’s book draws on more than 30 years of his experience as a hands-on craniosacral therapist and Rolfer. He offers immediate self-diagnostic and treatment techniques that can be done from the comfort of your home.

Main takeaway

Whether you have an active infection or the remnants of a previous infection, the vagus nerve may be contributing to your ongoing symptoms. Learning to recognize those symptoms and adding a few simple self-help techniques may help in your healing journey.

LymeSci is written by Lonnie Marcum, a Licensed Physical Therapist and mother of a daughter with Lyme. She serves on a subcommittee of the federal Tick-Borne Disease Working Group. Follow her on Twitter: @LonnieRhea  Email her at: lmarcum@lymedisease.org.

References

Aucott JN, Rebman AW, Crowder LA, Kortte KB. Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here? Qual Life Res. 2013 Feb;22(1):75-84. doi: 10.1007/s11136-012-0126-6. PMID: 22294245; PMCID: PMC3548099.

Azcona Sáenz J, Herrán de la Gala D, Arnáiz García AM, Salas Venero CA, Marco de Lucas E. (2021) Atypical bacterial infections of the central nervous system transmitted by ticks: An unknown threat. Radiologia (Engl Ed). Sep-Oct;63(5):425-435. doi: 10.1016/j.rxeng.2021.07.002. PMID: 34625198

Bonaz, B., Bazin, T., & Pellissier, S. (2018). The Vagus Nerve at the Interface of the Microbiota-Gut-Brain Axis. Frontiers in neuroscience, 12, 49. https://doi.org/10.3389/fnins.2018.00049

Breit S, Kupferberg A, Rogler G and Hasler G (2018) Vagus Nerve as Modulator of the Brain–Gut Axis in Psychiatric and Inflammatory Disorders. Front. Psychiatry 9:44. doi: 10.3389/fpsyt.2018.00044

Coughlin et al. Imaging glial activation in patients with post-treatment Lyme disease symptoms: a pilot study using [11C]DPA-713 PET

Diedrich A, Urechie V, Shiffer D, Rigo S, Minonzio M, Cairo B, Smith EC, Okamoto LE, Barbic F, Bisoglio A, Porta A, Biaggioni I, Furlan R. (2021) Transdermal auricular vagus stimulation for the treatment of postural tachycardia syndrome. Auton Neurosci. Sept29;236:102886. doi: 10.1016/j.autneu.2021.102886. Epub ahead of print. PMID: 34634682.

Ford, L., & Tufts, D. M. (2021). Lyme Neuroborreliosis: Mechanisms of B. burgdorferi Infection of the Nervous System. Brain sciences, 11(6), 789. https://doi.org/10.3390/brainsci11060789

Gadila SKG, Rosoklija G, Dwork AJ, Fallon BA and Embers ME (2021) Detecting Borrelia Spirochetes: A Case Study With Validation Among Autopsy Specimens. Front. Neurol. 12:628045. doi: 10.3389/fneur.2021.628045

Garrido-Mesa, N., Zarzuelo, A., & Gálvez, J. (2013). Minocycline: far beyond an antibiotic. British journal of pharmacology, 169(2), 337–352. https://doi.org/10.1111/bph.12139

Holmes GP, Kaplan JE, Gantz NM, Komaroff AL, Schonberger LB, Straus SE, Jones JF, Dubois RE, Cunningham-Rundles C, Pahwa S (1988). “Chronic fatigue syndrome: a working case definition”. Annals of Internal Medicine. 108 (3): 387–89. doi:10.7326/0003-4819-108-3-387. PMID 2829679.

Johnson L, Wilcox S, Mankoff J, Stricker RB. 2014. Severity of chronic Lyme disease compared to other chronic conditions: a quality of life survey. PeerJ 2:e322 https://doi.org/10.7717/peerj.322

Kenny BJ, Bordoni B. (Updated 2021) Neuroanatomy, Cranial Nerve 10 (Vagus Nerve) In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2021 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK537171/

Lynch SV, Pedersen O. The Human Intestinal Microbiome in Health and Disease. N Engl J Med. 2016 Dec 15;375(24):2369-2379. doi: 10.1056/NEJMra1600266. PMID: 27974040.

McCusker, R. H., & Kelley, K. W. (2013). Immune-neural connections: how the immune system’s response to infectious agents influences behavior. The Journal of experimental biology, 216(Pt 1), 84–98. https://doi.org/10.1242/jeb.073411

Ogrinc, K., Kastrin, A., Lotrič-Furlan, S., Bogovič, P., Rojko, T., Maraspin, V., Ružić-Sabljić, E., Strle, K., Strle, F. (2021) Colocalization of radicular pain and erythema migrans in patients with Bannwarth’s syndrome suggests a direct spread of borrelia into the central nervous system, Clinical Infectious Diseases, ciab867, https://doi.org/10.1093/cid/ciab867

Proal AD and VanElzakker MB (2021) Long COVID or Post-acute Sequelae of COVID-19 (PASC): An Overview of Biological Factors That May Contribute to Persistent Symptoms. Front. Microbiol. 12:698169. doi: 10.3389/fmicb.2021.698169

VanElzakker MB. (2013) Chronic fatigue syndrome from vagus nerve infection: a psychoneuroimmunological hypothesis. Med Hypotheses. Sep;81(3):414-23. doi: 10.1016/j.mehy.2013.05.034. Epub 2013 Jun 19. PMID: 23790471.

VanElzakker MB, Brumfield SA and Lara Mejia PS (2019) Neuroinflammation and Cytokines in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS): A Critical Review of Research Methods. Front. Neurol. 9:1033. doi: 10.3389/fneur.2018.01033

https://www.medicalnewstoday.com/articles/can-lyme-disease-cause-leukemia#having-lyme-disease-and-leukemia

Can Lyme disease cause leukemia?

Medically reviewed by Faith Selchick, DNP, AOCNP, Nursing, Oncology
Written by Mathieu Rees
September 8, 2021

Leukemias are cancers that involve certain cells of the body’s blood, bone marrow, or immune system. Lyme disease is a bacterial infection that people can catch from tick bites. Although these conditions are very different, certain connections may exist between them.

As a 2021 reviewTrusted Source explains, leukemias are cancers that develop from certain cells called leukocytes. When someone has leukemia, some of their leukocytes grow and divide in an uncontrolled fashion. Doctors can classify such cancers according to whether they affect myeloid or lymphoid cells. These cells are kinds of leukocytes.

As the review notes, there are many possible genetic and environmental causes of leukemia.

Lyme disease is the resultTrusted Source of Borrelia burgdorferi bacteria. These bacteria can make their way into a person’s body via tick bites. Ticks are small arachnids that feed on blood, and that can carry B. burgdorferi bacteria.

This article will look into the possibility that Lyme disease is a risk factor of leukemia. It will also look into what it is like to have both conditions at the same time, and at whether Lyme disease could mask or be mistaken for leukemia.  (See link for article)

_____________

Summary:

  • some evidence showsTrusted Source that Lyme disease may increase a person’s risk for another type of blood cancer called lymphoma. This may be because of the inflammation that Lyme disease causes in the body.
  • evidenceTrusted Source that Lyme disease is a risk factor of lymphomas. But this risk is small, and the link is not clear.
  • American Cancer Society (ACS)Trusted Source notes that some people with a B. burgdorferi infection, which causes Lyme disease, developed skin lymphomas in Europe. But the ACS emphasizes that most individuals with Lyme disease will not develop skin lymphomas.
  • ScientistsTrusted Source believe that bacterial infections such as Lyme disease could increase a person’s cancer risk by causing inflammation in the body. Up to 25%Trusted Source of cancer causes may include infections and inflammation.
  • The article erroneously states that those with the EM rash are more likely to have a more “developed” form of Lyme.  In fact, I would state it’s probably just the opposite.
  • The article further erroneously states 10-14 days of doxycycline is the treatment, which case after case and study after study has proven this to be insufficient.
  • The article also erroneously states 70-80% get the EM rash when in fact the percentages are highly variable and many never get a rash at all.
  • Some with leukemia develop a skin rash that is different than the EM rash.  See top link for pictures of both.

https://www.statista.com/statistics/1191568/reported-deaths-from-covid-by-age-us/  Click on link to see graph

As is clear from the graph above, only 595 children under the age of 17 have died from COVID as of Nov. 10, 2021, and while any death is upsetting, it certainly doesn’t warrant a wide-scale “vaccination” program with an experimental, fast-tracked gene-therapy injection that has caused more harm than for all 70+ vaccines combined since they started tracking adverse events 30 years ago. COVID shots are associated with the following:

  • They are 800 times more deadly than the smallpox vaccine – the previous record holder
  • They have killed more than 150,000 Americans
  • They don’t make sense for anyone of any age
  • The Pfizer 6 month trial showed it can save 1 life for every 22,000 people jabbed, but killed more than it saved
  • A FOIA request showed lipid nanoparticles delivered a substantial dose of mRNA to female ovaries and testes which could cause sterility, the spike protein subsequently produced causes blood clots, inflammation, and scarring leading to cardiovascular and neurological symptoms
  • Fibrin D dimer (blood clots) increased by a factor of over 400x above baseline
  • Tropin (heart damage) increased by a factor of 205
  • death elevated by 96X
  • brain herniation elevated by a factor of 100X
  • Cardiac arrest elevated by 93X
  • Pulmonary embolism elevated by 954X
  • Intracranial hemorrhage 79X
  • Tinnitus elevated by 105X (people have committed suicide over this as it drives you nuts)
  • They are still clueless as to the amount, dose, and duration of the spike protein that is produced
  • Many, many more issues to be concerned with  Source
  • Best-case scenario cost-benefit analysis showed very conservatively that there are five times the number of deaths attributable to each inoculation vs those attributable to COVID-19 in the most vulnerable 65+ demographic. The risk of death from COVID-19 decreases drastically as age decreases, and the longer-term effects of the inoculations on lower age groups will increase their risk-benefit ratio, perhaps substantially.  Source
Further, this Reuters article goes through the research showing the Delta variant does not make children sicker and secondary immune response is stronger after infection than after the jab.

https://www.tmj4.com/news/coronavirus/uw-health-begins-testing-covid-19-vaccine-on-children-6-months-to-4-years-old

UW Health begins testing COVID-19 vaccine on children 6 months to 4-years-old

The trial will last 18 months.
Posted Nov 09, 2021

MILWAUKEE — A new wave of kids 5 to 11 years old are rolling up their sleeves for covid shots in Milwaukee.

“I am very, very pleased that already were seeing a very solid positive response from parents,” said Milwaukee Mayor Tom Barrett.

“Every day that we have more people vaccinated, our community is safer,” said Dr. Smriti Khare of Children’s Wisconsin

City officials say since they began offering the vaccine last week, nearly 400 children in that age group have gotten their first dose of the Pfizer vaccine. Including the son of Milwaukee County’s top doctor. (See link for article)

______________

https://healthimpactnews.com/2021/pfizer-secretly-adds-dangerous-ingredient-to-injections-for-5-to-11-year-olds-as-taiwan-stops-pfizer-shots-for-12-to-17-year-olds/

Pfizer Secretly Adds Dangerous Ingredient to Injections for 5 to 11 Year Olds as Taiwan Stops Pfizer Shots for 12 to 17 Year Olds

by Brian Shilhavy
Editor, Health Impact News

Excerpts:

Greg Reese of Infowars.com has just published an explosive report about a secret ingredient that Pfizer has added to the shots being given to children under the age of 12 that is not present in their other COVID-19 shots.

It is a drug called “tromethamine” that is used in patients with heart attacks, and like all pharmaceutical drugs, has multiple reported adverse side effects, which includes tissue damage.

It has never before been tested in use with a “vaccine.”

We have put Mr. Reese’s report on our Bitchute and Rumble channels, but please support his work at Infowars.com, as well as his own website, because he does excellent work. (See link for article)

**UPDATE Nov. 17, 2021**

https://www.bitchute.com/video/0CUV7SmJvH0h  Video Here (Approx. 5 Min)

New VAERS Data Reveals Over 300,000 Deaths After COVID Shots

In this alarming video Steve Kirsch, president & founder of the Vaccine Safety Research Foundation, discusses some of the data points presented in the paper below which he recently presented to the FDA.

https://stevekirsch.substack.com/p/new-vaers-analysis-reveals-hundreds

New VAERS analysis reveals hundreds of serious adverse events that the CDC and FDA never told us about

They missed hundreds of serious adverse events that are more elevated than myocarditis. A new VAERS analysis done by Albert Benavides blows the doors off the “safe and effective” narrative.
The CDC and FDA have said the vaccines are “safe and effective.” They haven’t found any serious issues with the COVID vaccines. Zero. Zip. Nada. It was the DoD that found myocarditis.
The evidence in plain sight shows that they are either lying or incompetent. Or both. But of course, the medical community is never going to call them on this.

So that’s where our team of vaccine safety experts comes in; to reveal the truth about what is really going on.

In a brand new VAERS data analysis performed by our friend Albert Benavides (aka WelcomeTheEagle88), we found hundreds of serious adverse events that were completely missed by the CDC that should have been mentioned in the informed consent document that are given to patients. And we found over 200 symptoms that occur at a higher relative rate than myocarditis (relative to all previous vaccines over the last 5 years). All together, there were over 4,000 VAERS adverse event codes that were elevated by these vaccines by a factor of 10 or more over baseline that the CDC should have warned people about.

As of November 1, 2021, there have been more adverse events reported for the COVID vaccines than for all 70+ vaccines combined since they started tracking adverse events 30 years ago. That’s a stunning statistic, nobody can deny it, but nobody in the mainstream medical community (or mainstream media) seems to care much. It’s not even worth noting in passing. Wow.

Here’s what the evidence shows:

  1. The COVID vaccines are the most dangerous vaccines in human history. They are 800 times more deadly than the smallpox vaccine which was the previous record holder. The vaccines have killed over 150,000 Americans and permanently disabled even more. They don’t make sense for anyone of any age. The younger you are, the worse it gets. For kids, it is estimated that we kill 117 kids for every COVID death we prevent.
  2. The Pfizer 6 month trial showed the drug can save 1 life for every 22,000 people vaccinated. It also appeared from the trial that the drug killed more people than it saved (there were 20 deaths in the treatment group vs. 14 in placebo after unblinding). So we are “saving” fewer than 10,000 lives at the expense of over 150,000 deaths. In short, we kill 15 people to save 1. That’s incredibly stupid. But nobody in the Biden administration wants to meet with our team. They basically don’t want to hear the truth. Instead, they focus on deplatforming and censoring us which are techniques that are effective when the data doesn’t work out for you.
  3. Both the FDA and CDC have proven inept in spotting safety signals. They can’t even compute the VAERS URF which is a number that is required for any serious risk-benefit analysis. So the FDA and CDC outside committee members are all flying blind in approving the vaccines. Even after this deficiency is pointed out in the public comments by yours truly (and direct emails to the committee members), it makes no difference. We are ignored. The CDC safety monitoring is so bad that they even admitted at the last ACIP meeting that it was the DoD that spotted the myocarditis signal. So the FDA and CDC have basically been batting .000 in terms of spotting safety signals that have been sitting in plain sight the entire time.
  4. They can’t admit that they missed the signals now because that would be an admission they missed them before. So they will try to discredit this article with ad hominem attacks (this is a technique used to win an argument when you cannot win on the evidence).
  5. The serious events we highlight below are all consistent with the mechanism of action that Robert Malone and I first described in the Darkhorse podcast. Namely, that the spike protein that is produced in response to the delivery of the mRNA is cytotoxic and results in blood clots, inflammation and scarring throughout your body which then creates a wider range of severe adverse events than any vaccine in human history.
  6. The medical community is trained by the CDC to believe the vaccines are safe, so they interpret all the adverse events as not vaccine related. But if it wasn’t the vaccine that caused all these events, what was it? What’s worse is they tell their patients, “this is all in your head” or that “your baby died because you had a genetic defect.”
  7. In general, patients believe their doctors and never figure out where to get a cytokine panel to discover that they are vaccine injured (go to www.covidlonghaulers.com to get the cytokine panel and IncellDx to get the spike protein assay). So people never learn how to rid their body of the spike protein either (see my article on vaccine treatment for the drugs they use to do this) which is the first step in the road to recovery.
  8. The high adverse event rates aren’t “excess reporting.” It is due to excess events. For example, one neurologist had 0 cases of vaccine adverse events in her entire career, but this year, she has 2,000. Another physician I know has had 0 events in 29 years in his 700 patients. This year he needs to report 25 events. Physicians themselves have experienced stunningly higher incidence rates of reproductive, neurological, and cardiac events since the vaccines rolled in 2021. We couldn’t find a single cardiologist who actually had fewer cases of myocarditis after the vaccines rolled out as the members of the FDA and CDC claim.
  9. The serious events are primarily centered around menstruation, blood clots, inflammation and scarring, cardiovascular damage, and neurological damage, just as we predicted in the podcast in June of 2021.
  10. There are hundreds of serious adverse events that are caused by these vaccines. This of course is shocking to people since the CDC has repeatedly said you can’t ascribe causality to data in VAERS. Not true. The VAERS data analysis (temporal data, the dose dependency, and the elevated reporting rates compared to baseline) provide ample signal to enable us to show causality on all of these events using the five Bradford-Hill criteria applicable to vaccines.
  11. Nicki Minaj was right to complain about elevated rates of testicular swelling, impotence (erectile dysfunction), and orchitis. Every world authority who opined on the matter belittled her and said she was wrong, but all the symptoms she talked about are strongly elevated as you’ll see from the data below. None of these so-called experts of course ever looks at the data; it’s all based on arguing from their belief system rather than the scientific evidence. And even if those authorities disagreed with the VAERS data, it was irresponsible not to have pointed out the raw data to people and then explain why they totally ignored the elevated signal in the VAERS data. Today, we do science based on our belief system rather than the old-fashioned way of looking at what the data actually says. Our team is old-fashioned.
  12. There is a pretty good chance that the vaccines don’t really work at all and never did. We know the Pfizer Phase 3 trials were gamed in many ways. There is no doubt that the vaccines elevate antibodies, but it seems that it is quite possible that the immunity they confer is actually the result of killing off (or excluding as in the case of the trials) people with weaker immune systems. The people who are left are thus more resistant to the virus. Mathew Crawford will be coming out shortly with an analysis that makes a compelling case for this novel hypothesis. Subscribe to his substack here.
  13. It is unlikely that anyone in the world will want to debate us publicly on any of the claims above (or on any of my articles or on any of Mathew’s articles), but if you are a prominent supporter of the false narrative and want a public debate, we are here for you. Our team would be thrilled to accept the challenge as we have no desire to spread misinformation. If we got it wrong, we are happy to correct our mistakes if you can explain to us clearly the mistake we made and the correction you suggest (e.g., the “right” answer). Yet even with multiple million dollar incentives (listed in this article), nobody seems to be interested in showing how we got it wrong. Everyone talks about how bad the vaccine misinformation problem is, but nobody is willing to do anything to show that we got it wrong. For example, I’ve asked any prominent scientist in America who disagrees with my analysis (showing eight different ways to validate that over 150,000 Americans have been killed by the vaccines) to let me see their “correct” analysis showing the “correct” number, but nobody will. They won’t even come on a recorded call to show us how we got it wrong. It’s baffling. They all want to do it in slow motion via documents because that way it’s easier to obfuscate the truth and they can avoid answering questions. The latter is key.
  14. It’s really easy to tell who is telling you the truth here. John Su is the CDC expert on VAERS. If he’s wrong, the entire narrative falls apart. I personally attacked Dr. Su in a widely read article accusing him of being corrupt. I offered to publish his response in the article. He said nothing. I offered to debate him. No dice. TrialSiteNews tried to interview him. He refused to reply. Seriously? If the CDC gave us 2 hours to ask John Su questions, we would destroy his credibility and the credibility of the CDC. That’s why he’s not talking and that’s why the CDC will never let him talk to anyone on our team. Because we don’t ask softball questions like what John gets at the ACIP meetings. We play hardball.

What we found in the VAERS analysis below can be verified by anyone because it is all publicly accessible. Albert spent only a few hours to produce the tables. So the CDC should have been able to do the same work Albert did.

You can easily verify any entry yourself via manual queries to any VAERS interface (my favorite is MedAlerts, but others such as openvaers and the HHS site give the same results).

Before we get to Albert’s analysis of the VAERS data, let’s do a little background.

The Darkhorse Podcast

On June 10, 2021, my friend Robert Malone and I appeared on Bret Weinstein’s Darkhorse Podcast to tell the world what we had learned about the COVID vaccines. You can watch the 3 hour version here or the condensed 1 hour version here if you haven’t already seen it. I highly recommend the whole thing; I know a lot of people who watched it multiple times and raved about it.

Basically, we said the COVID vaccines were super dangerous, they had killed a lot of people at the time, the Pfizer bio-distribution data that Dr. Byram Bridle obtained from the Japanese government using a FOIA request showed the lipid nanoparticles delivered a very substantial dose of mRNA to female ovaries, and that the spike protein that is subsequently produced causes blood clots, inflammation, and scarring leading to a large number of cardiovascular and neurological symptoms, a number of which would be irreversible. Robert in particular noted that we had no clue about the amount, dose, and duration of the spike protein that is produced (we still don’t) because this testing was never done in animals (they looked only at the distribution of the nanoparticles which is not the same thing). Bret referenced a very long article I had written on May 25, 2021 for TrialSiteNews entitled “Should you get vaccinated?”

For reference, here is the bio-distribution graph that Bret showed in that podcast:

See anything wrong? Note that we deliberately omitted areas of the body where the vaccine was expected to accumulate in order to highlight areas of the body where it wasn’t supposed to go. Naturally, those supporting the mainstream narrative that the vaccines are safe and effective went into overdrive to suppress the episode and discredit what we said. They said we were dishonest not to include everything in the chart. YouTube censored the video after nearly 1M views. Wikipedia accused both of us of spreading misinformation and then blocked me when I tried to point out that the scientific evidence supported what I said. Wikipedia relies on fact checks for science.

We were right about everything we said in the podcast, and now, thanks to the work Albert did, it’s now easier to see we were telling the truth: the top elevated events were neurological, cardiovascular, and related to the female reproductive system, just like we said. I was stunned at the sheer number of menstrual events that made it to the very top of the list. That was a surprise to me.

Openvaers has been highlighting the damaging effects on both male and female reproductive systems for months with a page dedicated to reproductive health, but the medical community, Congress, and mainstream press wasn’t paying any attention at all. These event counts are not normal, but nobody really seems to care. President Biden not only doesn’t care; he wants to force all our kids to be vaccinated with the most dangerous vaccine in human history.

With the new analysis, the counts are much easier to interpret because instead of being just raw counts, they are no numbers relative to a baseline rate so we can instantly see what symptoms are “abnormal” meaning 10X or more higher than “expected.” The answer: over 4,000 adverse events.

The X factor analysis (November 7, 2021)

Before I give you the link to the spreadsheet of VAERS symptoms sorted by X factor, you need to know a few things to properly interpret the data.

First, let’s address the myth that is promoted by the FDA that the VAERS database is “over reported.” As we said above, there are more events this year than any previous year, so that’s why the events are up. But there still could be a component of overreporting as well, i.e., that people this year are more likely to make a report on an event compared to last year since everyone is so “highly aware” of the vaccines. Nice theory. No data to back it up. Nobody making that argument has ever included any data to back up their assertion. We call that a hand-waving argument. Doctor surveys we’ve done show that, if anything, they are less likely to report an adverse event this year for a variety of reasons (hospital frowns on it, no time, still too frustrating, too many events to report). The other way we can tell is to look at the rates of events that are not comorbidities or causal. We find that events like Musculoskeletal pain, Screaming, Head banging, Local reaction, Diet refusal, Croup infectious, Hepatitis A, Eyelid oedema, and more occur at pretty much the same rate this year as in previous years.

Now let’s tackle the columns:

Symptom
This is the VAERS symptom name. These are coded by HHS upon receipt of the report based on the contents of the report. Some of these symptoms are tests that are ordered. An elevation of a test is a good signal something is amiss. Other symptoms are not causal, but are comorbidities. For example, it might be that diabetes is there more often not because it makes diabetes worse, but because diabetic people are more likely to report symptoms. So for these symptoms, we have to be careful about the analysis. But for many of these symptoms such as cancer, herpes zoster (shingles), diabetes and more, these are all exacerbated by the vaccine as we know from talking directly to doctors. Finally, some symptoms like “rib fracture” or “suicide” are elevated because they are caused by the vaccine. For example, the vaccine can make you lose consciousness and fall and fracture your hip. The vaccine can give you tinnitus which is so bad that you want to kill yourself. So we have to be extremely careful to examine each one of these symptoms carefully because in most cases, we’ll find that they are indeed caused by the vaccine. I’ve coded a bunch of symptoms red that I thought were serious/interesting. I’m not done yet, so the redness coding was only methodically done on the first 100 symptoms and sporadically after that. When I get more time, I’ll go through them and update the file. Note that myocarditis is located on row 274, i.e., way way down.

Also, when looking at deaths, we never look at a “symptom” of death since death is coded in a separate field. So the event count for the “death” symptom (6,487) is lower than the over 8,000 domestic deaths.

Guillain-Barre syndrome is only elevated by a factor of 6 from baseline, likely because other vaccines also elevate GBS; this vaccine elevates it even more.

C19 count
This is the raw number of VAERS events in 2020 and 2021 due to the COVID vaccines for that symptom. The key here is that this count should be multiplied by 41 (known as the underreporting factor or URF to estimate the absolute number of events that occurred). See this article for how that is computed.

Baseline count
The baseline rate is the # of incidents occurring in a 5 year period from 2015-2019 for all vaccines given in that time period.

X-factor
The X-factor is the (C19 count*5/Baseline count). This is because the baseline is 5 years so we compare the COVID counts in a year vs. the average count in a typical year. So an X-factor of 10 or more would mean that the symptom is very likely to be caused by the vaccine since it is highly elevated from the “normal” rate.

Now let’s tackle the tabs. There are two tabs:

match tab
On the match tab are symptoms where the baseline count !=0

no match tab
On the “no match” tab are symptoms where the baseline count=0. So these are quite extraordinary since these symptoms are not typically seen even once in 5 years. So here, even a small value in the “count” field is very significant, e.g., 2 or more would be comparable to a 10X or more on the “match tab.”

Now here are some screenshots of the first page of the two tabs:

And the no match tab:

What the data tells us

Here are a few quick observations from the complete data set (see next section for downloading):

  1. Female reproductive issues top the list. These are strongly elevated by these vaccines. Many of the top symptoms are all related to the menstrual process.
  2. There are an enormous number of cardiovascular and neurological events that are strongly elevated, many of them serious.
  3. Fibrin D dimer increased is #53 on the list, elevated by a factor of over 400x above baseline. Charles Hoffe discovered D-dimer was elevated in over 60% of the patients he measured. This is very serious as D-dimer is a lagging indicator of blood clots.
  4. Troponin increased was #130, elevated by a factor of 205. Troponin indicates heart damage and it is elevated to extreme levels (10X heart attack levels or more) and can stay elevated for months at a time (with a heart attack, the levels start returning back to normal immediately after the incident)
  5. Death as a symptom (which is pretty unusual coding since it isn’t a symptom), is #433 and elevated by 96X. Hardly a “safe” vaccine.
  6. Brain herniation at #405 is elevated by a factor of 100X over baseline. However, this is not considered a big deal at the CDC (perhaps because many people there don’t use their brain).
  7. Cardiac arrest at #450 is elevated by 93X. This is when your heart stops. This is a relatively serious condition since you don’t last for too long after that. It’s a bit surprising that the CDC missed that one. Perhaps because they don’t have a heart?
  8. Pulmonary embolism #24 is elevated by 954 times normal. How the CDC can miss that one is simply astonishing! This was the cause of death of 2 of the 14 kids that the CDC looked at in their death analysis. Mainstream press will never ask them that question as to why the CDC would not find causality here. They wrote: “CDC reviewed 14 reports of death after vaccination. Among the decedents, four were aged 12–15 years and 10 were aged 16–17 years. All death reports were reviewed by CDC physicians; impressions regarding cause of death were pulmonary embolism (two), …” 954 times normal is hard to explain, isn’t it? So no causality? That’s hard to explain, so they didn’t. They just moved on as if there is nothing to see.
  9. Intracranial haemorrhage (their spelling) is at #604 and is elevated by 79X. Two of the 14 kids from the CDC analysis died from that. How could that not be causal? They never explained that.
  10. Tinnitus at #362 is elevated by 105X. This can be so bad that people can kill themselves from this alone. One of the people who work at Vaccine Safety Research Foundation (VSRF) had to talk a friend out of suicide.
  11. There are many many more issues to be concerned with, but I wanted to get the list out quickly so there can be more eyes on this.
  12. For months, I’ve offered to discuss our data and analyses to both the FDA and CDC outside committees as well as the CDC and FDA themselves, but nobody wanted to see it. Most hit delete on my emails. A few told me to wait for the public comment period and submit it then (which I’ve done). Nobody followed up.

The Excel file with the full results

I’m trying to increase the number of paying subscribers I have as this supports the substack community. All proceeds will go to paying the salaries of people working for the Vaccine Safety Research Foundation (vacsafety.org) as well as buying ads so we can get the message out.

You can find the full Excel file and Albert’s analysis in this article.

______________

For more: