To explore and critically appraise the published data on the current and emerging treatment modalities for neuroretinitis.
RECENT FINDINGS:
The optimum treatment strategy for neuroretinitis due to Bartonella henselae in immunocompetent individuals is not clear and a matter of debate. The role of systemic corticosteroids in infectious neuroretinitis and the optimum immunosuppressive regimen for use in recurrent idiopathic neuroretinitis also remains ill defined. There is no class 1 evidence to support a specific treatment strategy for neuroretinitis. For uncomplicated B. henselae-associated neuroretinitis in immunocompetent patients, initiation of antibiotic and corticosteroid therapy remains controversial.
In patients with severe vision loss and/or moderate to severe systemic symptoms, a 4- to 6-week regimen of doxycycline or azithromycin with rifampin may provide some benefit.
The routine use of systemic corticosteroids in infectious neuroretinitis is not recommended.
Targeted antimicrobial agents should be instituted in cases of neuroretinitis due to specific infectious etiologies (e.g., syphilis, Lyme disease, tuberculosis).
Azathioprine may be beneficial in cases of recurrent idiopathic neuroretinitis.
There is a need for collaborative, multicenter prospective studies to provide definitive guidelines regarding the use of antibiotics and corticosteroids and to evaluate future therapies in infectious and recurrent idiopathic neuroretinitis.
Most Lyme literate doctors do not recommend systemic corticosteroids unless antimicrobials are used in tandem. If steroids are used alone they suppress the immune system allowing the infection(s) to worsen.
Fifty nymphal Ixodes ricinus ticks collected in Alsace, France, identified by morphological criteria and using MALDI-TOF MS, were tested by PCR to detect tick-associated bacteria and protozoan parasites. Seventy percent (35/50) of ticks contained at least one microorganism; 26% (9/35) contained two or more species. Several human pathogens were identified including Borrelia burgdorferi s.s. (4%), Borrelia afzelii (2%), Borrelia garinii (2%), Borrelia valaisiana (4%), Borrelia miyamotoi (2%), Rickettsia helvetica (6%) and “Babesia venatorum” (2%). Bartonella spp. (10%) and a Wolbachia spp. (8%) were also detected. The most common co-infections involved Anaplasmataceae with Borrelia spp. (4%), Anaplasmataceae with Bartonella spp. (6%) and Anaplasmataceae with Rickettsia spp. (6%). Co-infection involving three different groups of bacteria was seen between bacteria of the family Anaplasmataceae, Borrelia spp. and Bartonella spp. (2%). Results highlight the panel of infectious agents carried by Ixodes ricinus. Co-infection suggests the possibility of transmission of more than one pathogen to human and animals during tick blood feeding.
_________________
**Comment**
Ixodes ricinus, commonly known as the castor bean tick, sheep tick, or deer tick, transmits numerous pathogens of medical and veterinary importance including Borrelia burgdorferi s.l. causing Lyme borreliosis, tick-borne encephalitis virus, Anaplasma phagocytophilum causing human granulocytic ehrlichiosis, Francisella tularensis causing Tularaemia, Rickettsia helvetica and Rickettsia monacensis, Babesia divergens and Babesia microti responsible for Babesiosis,Louping ill virus and Tribec virus.https://ecdc.europa.eu/en/disease-vectors/facts/tick-factsheets/ixodes-ricinus
A rare and life-threatening tick-borne virus is worrying doctors. What is Powassan disease and how can you keep yourself safe?
A Maine resident has been infected with a rare but typically severe tick-borne illness that can cause brain infections and meningitis and, in some cases, lead to death.
The Maine Center for Disease Control and Prevention (CDC) announced in a Wednesday news release that the resident, who has not been identified, showed symptoms of human Powassan encephalitis disease — more commonly referred to as Powassan virus — in late June and was hospitalized. The state CDC did not say whether or not the resident recovered.
Powassan virus — which “belongs to a group of viruses that can cause infection of the brain (encephalitis) or the membranes around the brain and spinal cord (meningitis), per the Centers for Disease Control and Prevention— is typically spread to humans after they’re bitten by an infected woodchuck or deer tick. The federal agency says those who live or work near brushy or woody areas are more likely to be exposed to potentially infected ticks.
Most cases of Powassan virus — which was first discovered in Powassan, Ontario in 1958, according to the Maine CDC — have occurred in the northeast and Great Lakes areas of the U.S.
Those infected with the virus typically experience fever, headache, vomiting, weakness, confusion, seizures and memory loss, per the Maine CDC, which also noted: “long-term neurologic problems may occur.”
“Symptoms can begin anytime from one week to one month after the tick bite. There is no specific treatment, but people with severe Powassan virus illness often need to be hospitalized,” it added.
Patients typically need support breathing and to treat swelling around the brain, but there is no medicine to treat the virus, nor is there a vaccine to prevent it, and about 10 percent of cases result in death, according to the federal health agency.
Powassan virus is rare, with an average of seven cases reported cases each year in the U.S. In Maine, 11 cases of Powassan virus have occurred since 2000, state health officials said.
For the last two years, Coppe Laboratories has dedicated a significant amount of time and resources to dispelling the myth that infection with Powassan virus, a virus transmitted by tick bite, is rare. The Centers for Disease Prevention and Control (CDC) reports only 100 cases of Powassan virus infection in the United States in the last 10 years. Indeed, that statistic gives the illusion that Powassan infection is rare. However, did you know that the only infections reported to CDC are those that are life-threatening, particularly cases causing severe inflammation of the brain like the case reported in LiveScience? Coppe has published three new papers in the last year that clearly show Powassan virus infection is not rare are at all,and until testing for this virus is included as part of tick-borne disease screening panels infections will continue to be underreported. Coppe’s Powassan Guide, which can be downloaded from the website, summarizes the findings from both tick and human Powassan prevalence studies, as well as defining the patient populations that would benefit most from Powassan testing.
COPPE LABORATORIES OFFERS THE FIRST COMMERCIAL PANEL DESIGNED TO DETECT EXPOSURE TO POWASSAN VIRUS THROUGHOUT ALL STAGES OF INFECTION.
Powassan can be transmitted in 15 minutes, so all the comforting words by the CDC on the emphasis that transmission of Lyme takes anywhere from 24-72 hours falls flat regarding Powassan. Also, to my knowledge, no work has been done on transmission time when multiple pathogens are being transmitted concurrently, or what happens when a person perhaps gets bitten, obtains Powassan but doesn’t have symptoms, and then in the future gets another tick bite and perhaps gets Lyme with that one.
Does that second bite activate a latent virus infection with Powassan?
THESE QUESTIONS HAVE NEVER BEEN BROACHED BY THE CDC.
The virus can be worse in those with “other medical conditions.”
Nobody really has a clue what a concurrent infection with Powassan looks like, but I would label that another medical condition.What if someone has Powassan and Lyme? Or, in my case, what if you have Lyme, Bartonella, Babesia, and then Powassan on top of that?
THIS IS THE FLY IN THE OINTMENT THAT CURRENT RESEARCH IS NOT ADDRESSING.
In this article Coppe Lab, right here in Wisconsin has uncovered some interesting findings: https://madisonarealymesupportgroup.com/2016/08/31/wi-coppe-lab-in-the-news/ A study completed in May, 2016 of 106 patients with suspected acute tick borne disease showed 10.4 % had Powassan. Nearly 17% of the patients with positive Lyme results also tested positive for POWV exposure. The authors concluded,
“Infection with POWV may be underdiagnosed and may contribute to the persistent symptoms often associated with Lyme diseasediagnosis.”16
They postulate:
In both studies, the percentage of Lyme patients co-infected with POWV was about 17%, coinciding with the 10 – 20% of patients treated for Lyme that develop lingering symptoms attributed to post-treatment Lyme disease syndrome.
One thing’s for sure. The CDC is not getting the memo because every single article I read on Powassan calls it “rare.”
QUESTION TO PONDER: HOW MANY HAVE TO DIE BEFORE SOMETHING IS NO LONGER RARE?
Ticks spread plenty more for you to worry about beyond Lyme disease
Jerome GoddardExtension Professor of Biochemistry, Molecular Biology, Entomology and Plant Pathology, Mississippi State University
When it comes to problems caused by ticks, Lyme disease hogs a lot of the limelight. But various tick species carry and transmit a collection of other pathogens, some of which cause serious, even fatal, conditions.
In my career as apublic health entomologist, I’ve been amazed at the ability of ticks to bounce back from all the ways people try to control them, including with pesticides. Ticks excel at finding new ecological niches for survival. So people and ticks frequently cross paths, exposing us to their bites and the diseases they carry.
Here are some of the lesser-known, but growing, threats from ticks.
Ticks can spread bacterial diseases
Certain very small species of bacteria that can cause human diseases, such as rickettsia, ehrlichia and anaplasma, live in ticks. Ticks ingest these bacteria when they drink animals’ blood. Then when the ticks take a subsequent blood meal, they pass the bacteria along to the next animal or person they feed on.
Probably the most well known of these bacterial diseases is Rocky Mountain spotted fever, the most frequently reported rickettsial disease in the U.S., with about 6,000 cases each year. The number of diagnoses seems to be increasing nationwide, especially among Native Americans, probably due to exposure on reservations to free-roaming dogs that can carry ticks.
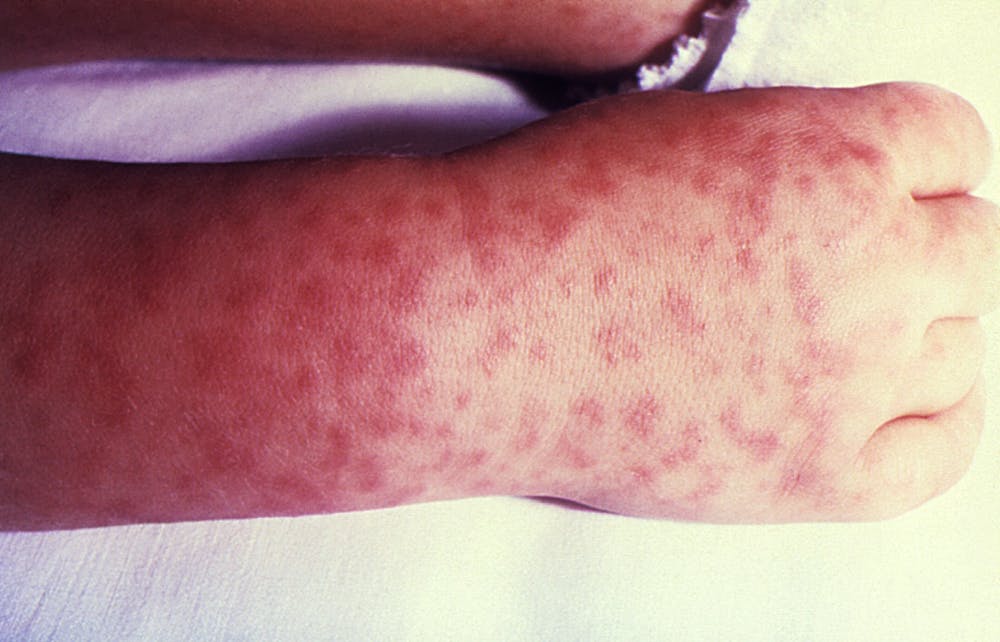
When people get sick with Rocky Mountain spotted fever, they usually come to a clinic with three things: fever, rash and history of tick bite. They may also report severe headache, chills and muscle pains, and gastrointestinal symptoms such as abdominal pain and diarrhea. A skin rash is usually present after a few days, but not always. Mental confusion, coma and death can occur in severe cases. Untreated, the mortality rate is about 20%; and even with treatment, 4% of those infected die.
Not all tick species are effective transmitters of the rickettsia bacteria. Even within the vector species, often only 1% to 5% of ticks in an area are infected. So getting bitten by a tick that passes rickettsia bacteria on to you is like getting stuck with a needle in a haystack. The primary carriers are the American dog tick in the eastern U.S. and Rocky Mountain wood tick in the West. The brown dog tick has also recently been shown to be a vector.
In most tick-borne diseases, the tick needs to feed for some amount of time before any pathogens it’s carrying are transmitted to the animal whose blood it’s eating. Rocky Mountain spotted fever organisms generally take between one and three hours for transmission to occur, so attached ticks need to be removed quickly. Doctors usually prescribe the antibiotic doxycycline to treat Rocky Mountain spotted fever, which works quite well if the disease is recognized early.
Ehrlichiosis is another bacterial disease transmitted from ticks to people. In the U.S. it’s most commonly caused by Ehrlichia chaffeensis bacteria, carried by lone star ticks which are common in the eastern U.S. Ehrlichia bacteria infect a type of blood cell called leukocytes. Human monocytic ehrlichiosis occurs mostly in the southern and south-central U.S.; 1,642 cases were reported to the CDC in 2017.
Ehrlichiosis patients usually have fever, headache, muscle aches and a progressive low white blood cell count. As opposed to Rocky Mountain spotted fever, people get a rash only about 20% to 40% of the time. Doctors usually treat ehrlichiosis with doxycycline.
Another tick-borne bacterial disease to worry about is human granulocytic anaplasmosis. In human granulocytic anaplasmosis, Anaplasma phagocytophilum bacteria infects a type of white blood cell called granulocytes. It mostly occurs in the upper midwestern and northeastern U.S., and the incidence is increasing, with 5,762 cases of human granulocytic anaplasmosis reported to the CDC in 2017.
A female Ixodes scapularis tick.Dr. Blake Layton, MSU, CC BY-ND
Symptoms include fever, headache, muscle aches and progressive low white blood cell count. It’s the deer tick Ixodes scapularis – famously also responsible for Lyme disease – that transmits the Anaplasma bacteria to humans. There’s the unlucky chance that a bite from a deer tick could infect you with both diseases. Again, recommended therapy is doxycycline.
Ticks can carry viruses, too
People usually think of mosquitoes when they think of insect-transmitted viruses – dengue, Zika or West Nile garner a lot of headlines. But ticks can transmit viruses, too.
Scientists have historically grouped tick-borne viral diseases into two categories. One is diseases similar to dengue fever. The main dengue-like viral disease transmitted by ticks in the U.S. is Colorado tick fever, which occurs in mountainous areas of the West.
The other group of tick-borne diseases resemble mosquito-borne encephalitis. Most of these illnesses, characterized by brain inflammation, are not found in the U.S. Powassan encephalitis is the one that is, occurring in the northeastern U.S. and adjacent regions of Canada.
Powassan is a relatively rare but serious human disease, characterized by sudden onset of fever with temperature up to 104 degrees Fahrenheit, along with convulsions. Brain inflammation is usually severe, with vomiting, respiratory distress and prolonged fever.
Fewer than 100 cases of Powassan have been reported in North America, with about half of them fatal. Its incidence seems to be increasing; there were 34 cases of Powassan reported during 2017. POW is maintained in a natural cycle when ticks – primarily Ixodes cookei – infect animals with the virus via their bites. Then these infected animals may serve as what scientists call disease reservoirs, infecting new ticks when they feed on their blood.
Tiny larval lone star ticks next to a penny.Jerome Goddard
In the last decade, researchers have found additional new tick-borne viruses in the U.S. About 30 cases of Heartland virus have thus far been identified. It’s associated with the lone star tick and has been recognized in Missouri, Oklahoma, Kentucky and Tennessee.
A few cases of a new Thogotovirus called Bourbon virus have been identified in the Midwest and southern U.S. The lone star tick may be the vector of Bourbon virus as well.
A food allergy triggered by a tick bite
Maybe the most bizarre threat from ticks is the “red meat allergy” scientists have recently traced back to tick bites. People can become allergic to eating meat when a tick’s saliva passes on the carbohydrate galactose-α-1.3-galactose it had previously picked up in a blood meal from an animal. If prone to allergies, the person can get sensitized to that alpha-gal molecule that’s found in animal blood and other tissues.
Then days or weeks later, he or she may develop hives, swollen skin and lips, or even life-threatening anaphylactic shock three to six hours after eating red meat. Meats containing alpha-gal include beef, pork, lamb, squirrel, rabbit, horse, goat, deer, kangaroo, seal and whale. People who become sensitized to alpha-gal may still eat chicken, turkey and fish.
Take precautions, like tucking pants into socks, when you’re in tick territory.rck_953/Shutterstock.com
Overall, people should be aware of what tick-borne diseases are present in their area and use personal protection techniques whenever outdoors in tick-infested areas. Remember that ticks often come into close contact with people via pet dogs or cats. It’s a good idea to inspect yourself for ticks after being outdoors in tick-infested areas. Reducing the number of tick bites and the amount of time ticks remain attached can go a long way to protecting you from tick-borne diseases.
Disclosure statement
Jerome Goddard does not work for, consult, own shares in or receive funding from any company or organization that would benefit from this article, and has disclosed no relevant affiliations beyond their academic appointment.
Republish this articleRepublish our articles for free, online or in print, under Creative Commons license._________________**Comment**
Why people continue to downplay this thing is beyond my understanding.
Compare this:
“So getting bitten by a tick that passes rickettsia bacteria on to you is like getting stuck with a needle in a haystack.” Gerome Goddard – 2019 – (Extension Professor of Biochemistry, Molecular Biology, Entomology and Plant Pathology)
With this:
“A lot of tick pathogens are rickettsia and rickettsial diseases. Every time I go to my local physician and I have some strange illness that they don’t know what it is, he says it is probably a rickettsia—an idiopathic condition.I’ve tested negatively for rickettsia, but the symptoms [suggest it] could be.” – James Oliver – 2016 (international expert in medical entomology and acarology,especially the biology and cytogenetics of pathogen-transmitting ticks and parasitic mites) https://academic.oup.com/ae/article/62/4/206/2712469
For the last two years, Coppe Laboratories has dedicated a significant amount of time and resources to dispelling the myth that infection with Powassan virus, a virus transmitted by tick bite, is rare. The Centers for Disease Prevention and Control (CDC) reports only 100 cases of Powassan virus infection in the United States in the last 10 years. Indeed, that statistic gives the illusion that Powassan infection is rare. However, did you know that the only infections reported to CDC are those that are life-threatening, particularly cases causing severe inflammation of the brain like the case reported in LiveScience? Coppe has published three new papers in the last year that clearly show Powassan virus infection is not rare are at all,and until testing for this virus is included as part of tick-borne disease screening panels infections will continue to be underreported. Coppe’s Powassan Guide, which can be downloaded from the website, summarizes the findings from both tick and human Powassan prevalence studies, as well as defining the patient populations that would benefit most from Powassan testing.