A federal judge on Monday ruled that some of Pennsylvania Gov. Tom Wolf’s restrictions implemented amid the ongoing coronavirus pandemic were unconstitutional — marking a win for businesses struggling to stay afloat amid the forced shutdown.
The ruling found that Wolf’s restrictions that required people to stay at home, placed size limits on gatherings and ordered “non-life-sustaining” businesses to shut down were unconstitutional.(See link for article and news video)
_____________________
Key Quote:
The Wolf administration’s pandemic policies have been overreaching, arbitrary and violated citizens’ constitutional rights, Stickman wrote in his ruling.
Were you ever infected with Powassan? These researchers want to know.
Powassan virus, a tick-borne illness, can cause serious neurological problems that are sometimes fatal. It’s transmitted to humans by Ixodes ticks—the same ones that can carry Lyme disease. But much is unknown about Powassan, something that researchers want to change.
Dr. Margaret MacDonald is a physician and researcher at Rockefeller University in New York City. She’s Principal Investigator of a study of neutralizing antibodies and Powassan virus infections. One of her collaborators is Dr. Brian Fallon, director of the Lyme and Tick-Borne Diseases Research Center at Columbia University.
In the following blog, Dr. Fallon interviews Dr. MacDonald about neutralizing antibodies, Powassan virus, and COVID-19.
If you have had Powassan virus infection, you may be able to help with this important study. See links at the end of the article for more information about how you can do that.
Dr. Fallon: Can you describe the similarities between COVID-19 and Powassan infection?
Dr. MacDonald: While the viruses that cause COVID-19 and Powassan infection are in completely different families, they do have some similarities, one of which is that they both use a molecule called ribonucleic acid (RNA) to encode their genetic material.
One property that both viruses share is that they don’t always cause obvious disease and some infected people may never know they were even infected. The Centers for Disease Control and Prevention (CDC) estimates that about 40% of SARS-CoV-2 infected individuals have no symptoms. SARS-CoV-2 was only recently identified while POWV was first discovered in North America in 1958.
Despite the fact that POWV has been around much longer than COVID-19, there is actually less information about how many people are infected each year and what percentage of them have symptoms, because unless someone has serious symptoms, they are never tested.
But we do know that in some regions of the United States about 2-3% of ticks that carry POWV infection are infected and that transmission after a tick bite can occur within 15 minutes. Although nationally cases of Powassan encephalitis have been increasing in recent years, there are still only about 20-30 reported cases each year, suggesting that there are quite a few people who have been infected but who do not develop symptoms.
SARS-CoV-2 usually presents as a respiratory illness, but we know it can affect multiple systems of the body. POWV typically starts as a nonspecific flu-like illness that progresses to an infection of the central nervous system with inflammation of the brain (encephalitis) or the fluid surrounding the brain (meningitis). SARS-CoV-2 can also cause encephalitis and meningitis, but this is not typical.
Both viruses may share similar initial symptoms including fever and chills, sore throat, headache, nausea and vomiting, diarrhea, tiredness, and muscle ache. There also can be neurological symptoms in both diseases; shared symptoms include gait disturbances, decreased level of consciousness, hallucinations and seizures. Respiratory failure can occur in either disease, although for different underlying reasons.
Can you describe the differences between COVID-19 and POWV infection?
There are a number of differences between SARS-CoV-2 and POWV. The RNA genetic material of SARS-CoV-2 is longer than POWV (~30,000 bases long compared to ~11,000) and encodes more proteins (29 compared to 10) and while still really tiny, the SARS-CoV-2 virion is about twice the size of POWV.
To start the infection, the SARS-CoV-2 spike protein binds a protein (the receptor) on the surface of your cells called angiotensin converting enzyme 2, or ACE2. Another of your proteins, abbreviated TMPRSS2, helps the spike protein, allowing the virus to gain entry to the cell. The receptor for POWV is unknown, but presumably it is not ACE2. Once inside the cell, the two viruses use very different strategies to make viral proteins and new copies of their RNA.
How these two viruses infect us is completely different! As you know, COVID-19 is spread from person to person when an infected person breathes or coughs, expelling SARS-CoV-2 that makes its way into another person through inhalation, or exposure to the mouth, nose or eyes. It is believed that virus can also survive for some time on surfaces, which if you touch the surface and then touch your mouth, nose or eyes can result in infection.
On the other hand, POWV does not spread from person to person, except in rare circumstances such as transfusion of blood originating from an infected person. Instead, POWV is spread through the bite of an infected Ixodes species tick, very much like in Lyme disease. In fact, the same tick may carry both Borreliaburgdorferi and POWV.
SARS-CoV-2 and POWV also can cause different symptoms. SARS-CoV-2 infection starts in the respiratory tract. Symptoms from SARS-CoV-2 are the result of both direct infection of cells in the body as well as the inflammation that occurs in response to the infection and effects on the coagulation system.
This later effect can result in blood clots in the smaller arteries that can affect the blood flow to and thus function of organs such as the lungs, heart and kidneys and can also cause skin rashes, strokes and heart attacks. The infection of cells in the lung combined with the inflammatory process results in respiratory distress with poor oxygenation of the blood and difficulty breathing, and mechanical ventilation can be required to support the patient.
A prominent symptom in COVID-19 is the loss of taste and/or smell, as well as congestion or runny nose. The long-term effect on the function of the affected organs is not yet known, but patients have reported continued symptoms of weakness, muscle aches, headaches, rash, shortness of breath and abnormal heart rate even weeks after recovery.
POWV infection presumably starts in the skin at the site of the tick bite. Based on what is known about other virus family members, it may replicate in lymph nodes, gain access to the blood and subsequently the brain. Powassan disease in the brain occurs after a 1-2 day flu-like illness and can present with a wide variety of neurological symptoms including paralysis or weakness of one or more limbs, or of the muscles controlling the eyes or parts of the face, tremors and twitching, inability to talk, and abnormal jerking eye movements. Confusion and varying degrees of a depressed level of consciousness including coma are common.
While these symptoms can be seen in SARS-CoV-2 infection, they are not as common. POWV doesn’t cause pneumonia, but respiratory failure due to infection of the region of the brain that controls breathing can result in the need for mechanical ventilation. Long term residual symptoms are common after Powassan encephalitis, and include memory difficulties, headache, difficulty speaking, imbalance, and weakness or paralysis of limbs or muscles of the eyes.
Most people had never heard of “neutralizing antibodies” before COVID-19. Can you explain to us what “neutralizing antibodies” are? How do they differ from the regular antibodies that the body generates to fight infection? Why are some antibodies more effective as virus killers than other antibodies?
Antibodies are proteins secreted by special immune cells called B cells. Each B cell makes its own unique antibody, which can work in different ways to fight infection. One way is for the antibody to bind the invader which then allows the early immune response cells (phagocytes) to gobble up the invader. Another way is for the antibody to bind and activate a defense program called complement, which can destroy cells containing the invading microbe. A third way antibodies work is to bind to the invader and block it from infecting your cells. This is called neutralization.
Neutralizing antibodies therefore are especially potent in fighting infection because they target and neutralize the invading microbe directly. To block infection requires that the antibody be specific for a part of the invader that is required for entry into the cell, which in the case of SARS-CoV-2, would be the spike protein. Antibodies that bind the spike protein and prevent it from interacting with the ACE2 receptor can block infection of your cells before it even gets started.
One of the big questions with vaccine research is always how long will the antibodies last in the blood that can protect us against the virus or bacterial infection? If a vaccine is developed against POWV that creates neutralizing antibodies, would these antibodies last months or years? What about with COVID-19? Will we need frequent booster shots?
This is one of those million-dollar questions and likely ultimately depends on the type of vaccine that ends up being developed. The good news is that many different approaches are being used for the SARS-CoV-2 vaccines that are in the development pipeline. It is not clear to me what makes antibodies last longer for some infections or vaccines than others. Antibody responses to the live-attenuated yellow fever virus vaccine can persist for years and that vaccine can protect you for 10 years or even longer.
Yellow fever is in the same family as POWV, so there is a chance that if a similar vaccine were developed for POWV, that the antibodies could last a long time and boosters would not be necessary. But natural infection with viruses in this family tends to result in good protection against that specific virus.
This is not necessarily true for viruses in the same family as SARS-CoV-2. We know that people can be infected with a SARS-CoV-2 relative that causes the common cold and get infected multiple times with the same virus. Antibodies in the blood after the SARS outbreak, caused by the related SARS-CoV-1, lasted 2-3 years. Early indications are that SARS-CoV-2 vaccination can induce responses that are robust, but how well and how long they protect is anyone’s guess and this will just need to be studied.
Powassan Virus can cause very serious neurologic consequences in those individuals that get encephalitis. It now seems that the coronavirus may also be causing a wide range of neurologic problems. Do you know whether they attack the nerve cells in the same way?
POWV likes to infect nerve cells so once it gains access to cells of the brain or spinal cord it can directly cause damage that results in the symptoms the patient is suffering. This damage to the nerve cells likely explains the long-term symptoms that these patients can have.
Since SARS-CoV-2 has been detected in brain tissue, it is quite possible that direct infection of the nerve cells may underlie some of the neurological symptoms of COVID-19. However, there are other mechanisms of neurologic disease currently under investigation that likely contribute to the neurological symptoms, including abnormal clotting in small vessels, reduced oxygen flow to the brain, and the damaging effects of the inflammatory process.
You are doing a Powassan virus study now and you need to find people with prior Powassan virus infection. Please tell us about this and how these individuals can help you. What do they need to do to participate?
Yes, we are looking for people who have had POWV infection. Some of these recovered individuals will still have POWV-specific B cells and neutralizing antibodies in their blood. We study the antibodies to the POWV envelope protein, which is the target of most neutralizing antibodies against viruses in this family. We will identify the antibodies that have the strongest binding and neutralizing capacity. We will then identify where the binding occurs on the virus – ie, which protein on the virus surface is the most important in triggering the production of these potent antibodies.
This information can help us design a vaccine. These antibodies also would be good candidates as a treatment to administer to someone with Powassan virus encephalitis, much like the use of SARS-CoV-2 convalescent serum that has been used for COVID-19 patients that you may have read about in the news.
Our study may lead to a critical public health breakthrough. However, we can’t study antibody responses to POWV unless we have volunteers who have been infected with POWV. If the reader of this blog has had POWV infection or knows someone who has had POWV infection, please take note of how to participate.
After the initial contact, we will ask for documentation of the prior POWV infection. We will explain the study in detail and the participant will be asked to sign a consent form that they agree to participate in our study. Then, they would fill out a medical questionnaire and would donate a volume of blood that is similar to the amount given in a blood donation, such as for the Red Cross.
The consent process and blood donation typically would occur at the Rockefeller University Hospital in New York City, but we are also open to working with volunteers from outside our area to arrange for the blood to be drawn elsewhere and shipped to us for our study.
While the COVID-19 pandemic has been a tragedy for so many throughout the world, one result of this experience is to highlight the importance of public health preparedness. While POWV infection is currently rare in the United States, the reports of human disease have been increasing over the last decade. One study documented that in 1980 less than 10% of deer in the Northeast had been infected, while in 2009 this had risen to ~90%. The rising infection rate in deer may be an early signal that POWV infection in humans may be more of a problem in the future. Our study aims to enhance POWV public health preparedness through early development of a vaccine and treatment.
As part of our mission to accelerate research of tick-borne illnesses, LymeDisease.org periodically highlights studies that seek patient participation.
“It’s Like Using A Hammer To Kill A Fly” – Architect Of Sweden’s COVID-19 Anti-Lockdown Strategy Finally Vindicated
When the history books are written about 2020 and the great coronavirus pandemic, Anders Tegnell, the humble Swedish state epidemiologist and architect of the global-consensus-defying ‘Sweden strategy’, will inevitably loom large throughout the text. But whether he is portrayed as a hero or villain may – like so many things in this highly polarized era – ultimately depend on who’s writing the piece.
As the FT explained in its latest in a series of interviews with Tegnell, the American press – thanks in large part to its newfound fanatical devotion to the cause of “science” – including the NYT, has been particularly hard on Tegnell. The Gray Ladyhas called Sweden a “pariah state” and “the world’s cautionary tale.”
European papers have been somewhat more forgiving. That’s perhaps because the lockdowns imposed across Europe were far more restrictive than what most, outside NYC, experienced in the US. And despite all that work, new daily cases are back to seeing record highs in France, and post-lockdown highs in Spain, while cases climb in Italy, the UK, Germany and across Central Europe into Ukraine. (See link for article)
**Comment**
The article admits that preventable deaths in nursing homes and long-term facilities occurred in Sweden when little was known about the virus, but despite this, Sweden is the singular European nation without a “second wave,” and cases have continued to fall into September.
Hydrogen peroxide sits inside and outside cells of your cells in low levels, ready and waiting to be generated in greater amounts as soon as a pathogen is detected by your immune system
Nebulizing hydrogen peroxide into your sinuses, throat and lungs is a simple, straightforward way to augment your body’s natural expression of hydrogen peroxide to combat infections
In addition to having direct viricidal effects, iodine improves white blood cell function and thyroid hormone production. This provides a metabolic boost to white blood cells to increase hydrogen peroxide antimicrobial properties which is one way your immune system works to kill pathogens
Vitamin C also increases hydrogen peroxide production when used at high doses, while vitamin A helps modulate your immune system
Buy a desktop nebulizer and stock food-grade hydrogen peroxide, Lugol’s iodine and some saline. That way, you have everything you need and can begin treatment at home at the first signs of a respiratory infection
Dr. Mercola Interviews the Experts
This article is part of a weekly series in which Dr. Mercola interviews various experts on a variety of health issues. To see more expert interviews, click here.
Dr. David Brownstein, who has a clinic just outside of Detroit, has successfully treated over a hundred patients with what has become my favorite intervention for COVID-19 and other upper respiratory infections, namely nebulized hydrogen peroxide. He has published the results of his work in a study that you can download here.
Since I first wrote about it at the beginning of April 2020, I’ve received impressive testimonials of its effectiveness from friends and acquaintances who got severely ill and used it.
Brownstein is probably best known for his promotion of iodine and its supplementation. He was also an early adopter of vitamin D optimization and nebulized peroxide. He explains the background that led him to his current regimen:
“The history goes back about 28 years when I began practicing holistic medicine. Of course, we would see people with influenza and influenza-like illnesses every fall and winter, so I started searching for things that would help people’s immune systems …
We initially started using vitamin C and vitamin D. I started to check vitamin D levels in 1992. What I found was the vast majority of my patients, well over 90%, were deficient in vitamin D, and those who had more chronic issues and were sicker in general, they usually had lower levels of vitamin D …
Then I came across vitamin A. I originally read the research on how vitamin A helped third world countries when they had measles infections and helped … [patients] recover uneventfully if they had enough vitamin A, so I quickly added vitamin A to the regimen.
A few years later, I learned about iodine. Iodine has direct viricidal effects. It has immune system effects. It helps the white blood cells produce hydrogen peroxide to fight viral and bacterial infections, as well as thyroid effects. Iodine got added to the regimen, and so the original treatment of our patients was vitamins A, C, D and iodine at high doses for about four days.
What we found was our patients did not develop pneumonia, did not get hospitalized, did not die from flu and other influenza-like illnesses at anywhere near the rates that they should have when you looked at the published rates of problems with these illnesses.”
Hydrogen Peroxide and Ozone
While attending an oxidative medicine course, Brownstein learned about hydrogen peroxide. At that point, he and his staff started using nebulized hydrogen peroxide and intravenous (IV) hydrogen peroxide. That was back in the mid-1990s. So, he has been using nebulized peroxide clinically for 25 years now, which is longer than anyone I know of.
With each revision of his original protocol, patients seemed to fare better. Fast-forward another couple of years, at another medical course, he learned about the benefits of ozone.
“That was the latest addition to it. What we found over 28 years of using this therapy is that our patients did well. I never made a claim that this cured any influenza or influenza-like illness. What it does is it supports the immune system in multiple ways, and people get over it just like they’ve gotten over it for eons of time,” Brownstein says.
“If we didn’t get over these viral illnesses, we wouldn’t survive as a human species, so it certainly makes sense we’d want a strong immune system in place when we get exposed to these pathogenic organisms.
When COVID-19 came around … we were warned that we’re going to have millions of deaths, and this is going to be the biggest medical catastrophe in our lifetimes …
Everyone was on edge, and I had a meeting with my staff at the end of a work week. It was the last Thursday in February. And I told the staff that the first 28 years of our holistic practice was truly practice for this pandemic … And I said, ‘I think we’ve got this covered.’
I said, ‘I can’t guarantee anyone anything, but we’ve treated coronavirus in past years’ … Coronavirus is known to be part of the influenza-like illnesses … I don’t see any reason why this wouldn’t work for this illness as it has worked for the other viral/coronavirus illnesses that we’ve been treating.'”
107 Patients — One Hospitalization, Zero Deaths
Brownstein and the other physicians in his practice first started treating COVID patients in the middle of a Detroit winter under full social distancing and lockdown restrictions. As a result, he had to treat patients who were ill in a drive-through manner in his clinic parking lot. They’d stick their arm out their car window, and Brownstein and his colleagues would do an IV of hydrogen peroxide and vitamin C and intramuscular shots of ozone.
“I vividly remember the snow coming down on my face mask as I’m shaking my head like a dog in order to clear my face shield, trying to put the IV in,” he says. “At the end of the treatment, we would do ozone. We didn’t want to do IV ozone outside because the elements weren’t good, so we decided to do intramuscular ozone.
People who were sick, who couldn’t breathe, we’d meet them in the parking lot. At the end of the IVs, we’d open their car door and have them stick their rear end out the car door. We’d put ozone in each [butt] cheek and send them on their way.
We got them hooked up on a nebulizer too, nebulizing hydrogen peroxide and iodine. After they started the therapies, usually after the first nebulized treatment, their airways would open up, and they could breathe again.We ended up treating 107 patients that I wrote about in the published, peer-reviewed [paper]. We had one hospitalization, no ventilators, no deaths.”
The case report,1 “A Novel Approach to Treating COVID-19 Using Nutritional and Oxidative Therapies,” was published in Science, Public Health Policy, and The Law in July 2020. For a couple of months, Brownstein would post video interviews with his patients, in which they told their story.
He removed all of them after receiving a warning letter from the Federal Trade Commission, saying that because there’s no established prevention, treatment or cure for COVID-19, any mention thereof falls in violation of FTC law.
“In their first letter to me, they said, ‘Because there’s no human clinical studies documenting what you say works, you need to remove it.’ So, after we published the [case review], my lawyer wife sent the FTC a letter saying, ‘Here’s a published study. We’d like to put my study on my website without comment.’ And they said, ‘No, it’s not a randomized. We want a randomized controlled study.’
So, we felt like we had punched the ball into the end zone, and then they moved the goal post back 30 yards, but that’s where we stand right now with it. And we’re still treating patients with it. The study was on 107 patients. We’ve probably treated 10 more patients since then, still with good success.
I wrote in the article that the reason I didn’t do a randomized study was it’s unethical for me to withhold that treatment from people when I’m as certain as I can be that the therapy was going to work. There’s no way I could sleep at night if I was randomizing people to get the therapy, and others to not get the therapy.
COVID was a new illness. We had never seen it. Nobody had ever seen it. There were no randomized studies. There’s no reason to. Too many people were dying. We’ve already had over 100,000 deaths. It’s just tragic, and it’s really going to be a stain on medicine when the final autopsy is written on this.”
Boosting Your Immune Function Is Imperative
Interestingly, as explained by Brownstein, in addition to having direct viricidal effects, iodine also stimulates and supports the immune system. It increases the killing effect of hydrogen peroxide production in your white blood cells by improving white blood cell and thyroid function, which is one way our immune system works to kill pathogens. Vitamin C directly increases hydrogen peroxide production when used at high doses, he says, while vitamin A helps modulate your immune system.
“Perhaps instead of just relying on masks and social isolation, we should be talking about the immune system,”Brownstein says. “How do we support it? And I’d like to throw out the question: Since when did talking about supporting the immune system become illegal? Since when do you have to be quiet about it?
Unfortunately, in this time and age, this is where we’re at right now, and it’s a sad time … I’ve been writing a book on a holistic approach to viruses. And in this book … I say that this illness is an example of what’s wrong with our country.
The health of our country is in such decline, we finish last or nearly last in every single health indicator when compared to other Western countries, and this is why we’ve got hit so hard with this. And nobody talks about our health. All they’re talking about is masks, social isolation and wait for a vaccine.
What about the next virus that comes around? What are they going to do about that one? And my comments on this warp speed vaccine to the world is, I hope it’s safe and effective, but I don’t think I’ll be first in line getting this thing, not when it’s bypassing all the safety studies …
What I’d be first in line with is trying to figure out how I’m going to support my immune system, so when I’m confronted with these different viruses — because after this one, there’s going to be the next one — you’re not going to depend on another warp speed project. You’re going to depend on yourself to get over these things. We can do it.”
How to Do Nebulized Hydrogen Peroxide — The Basics
Nebulized hydrogen peroxide is extremely safe. Brownstein has used it for 25 years with no ill effects being found. It’s also incredibly inexpensive, and you can administer it at home, without a prescription. In my view, it is one of the absolute best therapies for viral infections like SARS-CoV-2 or even worse respiratory viruses that will likely be unleashed in the future.
You need to buy a desktop nebulizer (it needs to produce a very fine mist and desktop versions are stronger than handheld battery operated models). The one I use is the Pari Trek S Compressor Aerosol System, which is available on Amazon or less expensively on eBay. The large battery option is unnecessary as you can simply plug in the device to run it when you need it.
Please understand, though, that the Pari Trek S is designed to treat asthmatics and as such only comes with a mouthpiece. While this would get the peroxide in the lungs where it is needed, it does nothing to reach the sinuses, which are also likely infected. This is why it would be worth pick up some face masks on Amazon to use instead of the mouthpiece as they are only about $10.
It is important to acquire this BEFORE you need it, as the sooner you treat the infection the better your results will be, although the testimonials are unbelievably impressive even in late stage illness. It is not necessary to treat yourself preventively, but only if you are sick or exposed to someone who is.
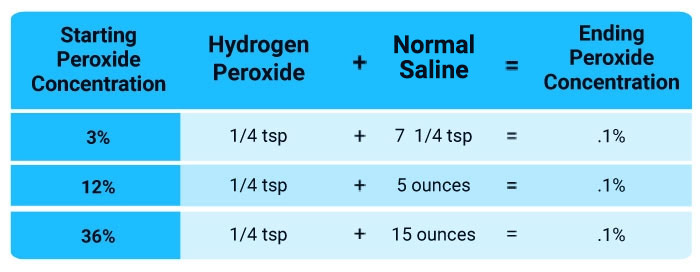
While I’ve been using a 0.1% dilution, Brownstein uses an even lower concentration of just 0.04%. Neither Brownstein nor I recommend using commercial 3% hydrogen peroxide found in most grocery stores, however, as it has potentially toxic chemical stabilizers in it. Then take 3-5 ml and put that into the nebulizer and inhale the entire amount. You can do this every hour when you are sick until you start to notice improvement and then back down to every 4-6 hours and continue until you are over the illness.
Since you are not using full strength 3% peroxide and diluting it by 30 to 50 times, it is unlikely the stabilizers will present a problem, but to be safe it is best to use FOOD-GRADE peroxide. Also remember not to dilute it with plain water as the lack of electrolytes in the water can damage your lungs if you nebulize that. You will need to use saline or add a small amount of salt to the water to eliminate this risk.
Brownstein also dilutes the peroxide with sterile water and saline rather than distilled water. Using saline prevents the osmotic differential that can cause damage to lung cells. Brownstein dilutes the 35% food-grade peroxide as follows. When nebulizing, Brownstein also adds one drop of 5% Lugol’s solution to the nebulizer as well.
Dilute 35% food-grade peroxide down to 3% by mixing 1 part peroxide with 10 parts sterile water
Take 3 cubic centimeters (CCs) of that 3% dilution and add it to a 250CC bag of normal saline. This brings it down to a .04% hydrogen peroxide concentration
Sample Case History
Brownstein relates the case of a 67-year-old male patient. The man developed COVID-19 symptoms, and after seven or eight days could not breathe and went to the hospital where he was diagnosed with bilateral pneumonia. After two days of treatment, which included oxygen, he felt only slightly better, but was released from the hospital due to a shortage of beds.
“They sent him home on oxygen and told him, ‘Only come back if you can’t breathe.’ So he goes home, and he calls me on the phone, crying, ‘I’m going to die. They sent me home to die.’
I said to him, ‘You’re not going to die. Do you have a nebulizer?’ And he said, ‘No.’ And I’m like, ‘We need to start nebulizing right away … Send your wife over. We’ll put a nebulizer in the car and tell you how to do it.’ So, we mixed up the solution for him, and she brought the nebulizer home.
I called him up at the end of the day. He had done three nebulizer treatments, and he said that after the second nebulizer treatment his lungs started to open up. He felt about 70% better and didn’t feel like he was going to die at that point.
He was still coughing and short of breath, but not like he was. After the third treatment, he said he was even better … So, this nebulizer thing really does work.
The one thing I’d like your readers to know, the handheld nebulizers don’t work as well. I had a handful of patients who were using a handheld nebulizer and trying it with the same solution.
They were calling me back saying, ‘It’s not working.’ When they got a desktop model, a little stronger model, it worked. So, I encourage people not to use a handheld nebulizer. Use a desktop model. It’s a little bit stronger.”
Nebulized Peroxide Typically Improves Symptoms Within Hours
This story echoes the experiences of personal acquaintances who have tried the treatment. After two treatments, they felt significantly better. After the third treatment, their breathing was restored and they were well on their way to a full recovery.
You’d be hard-pressed to find another treatment that works within hours. Brownstein agrees that this scenario is consistent with what he has encountered among his own patients.
“Usually, everything feels better within a couple of hours of starting nebulizing,” he says. When asked about how others in the medical community have responded to his blog posts about the treatment, he replies:
“In the middle of the crisis as I was posting … I started hearing from doctors all over the country, especially in New York and New Jersey. They were hospital physicians … They didn’t know what to do. The therapies weren’t working.
No. 1, they want the therapy for their family, and No. 2, they want to help their patients. So, I was hearing from doctors. They were interested. I heard from a couple of local doctors who sent patients to us whom they couldn’t help.
They had nothing to offer them … and [those patients] got better … It was really the first time I got a bunch of emails, messages and phone calls from doctors saying, ‘Hey, tell me how it works. Tell me what you’re doing.'”
Hydrogen Peroxide Facts
In my April 2020 article, “Could Hydrogen Peroxide Treat Coronavirus?” I reviewed some of the basic science of how hydrogen peroxide works, as well as some of the studies assessing its therapeutic potential.
The most relevant study2 was published in March 2020 in the Journal of Hospital Infection. They studied 0.5% hydrogen peroxide, and found it killed human coronaviruses, including the coronaviruses responsible for SARS and MERS. Here are a few additional facts that explain how and why hydrogen peroxide works so well for respiratory infections:
1. Hydrogen peroxide freely crosses cell membranes and does not readily oxidize biological molecules, including lipids and proteins.3 It does however react with iron. The presence of free, unbound iron in high concentrations in pathogens is what allows them to be selectively targeted by hydrogen peroxide.
High concentrations of iron result in a rapid breakdown of hydrogen peroxide into hydroxyl radicals and water. The hydroxyl radical, a potent oxidizing agent, kills any pathogens present. (Under normal, healthy circumstances, hydrogen peroxide merely breaks down into oxygen and water.)
2. Peroxide is generated by activated phagocytes (pathogen-killing immune cells) at sites of inflammation.4 Phagocytes also contain high amounts of ascorbate (vitamin C), which directly donate electrons to peroxide to generate the pathogen-killing hydroxyl radical inside the infected cells. Vitamin C also helps generate increased amounts of extracellular hydrogen peroxide, which further boosts the elimination of pathogens.5
3. Hydrogen peroxide is continually generated inside all cells in your body, including the epithelial lining of your lungs. (Hydrogen peroxide is present in the air exhaled by healthy human subjects, and when inflammation is present, more peroxide is found in the exhaled breath.6) The presence of excreted peroxide on these surface cells in the airways is part of a healthy, at-the-ready immune response.7
4. Aside from its anti-pathogen properties, hydrogen peroxide is also recognized as an important signaling molecule, both intracellular and extracellular, influencing and modulating multiple metabolic processes.8
In summary, hydrogen peroxide sits inside and outside your cells in low levels, ready and waiting to be generated in greater amounts as soon as a pathogen is detected by the immune system by NADPH Oxidase (NOX).
Its presence in your human body (at varying amounts depending on whether infection is present), and the lack of toxic metabolites, are indicative of its safety and nontoxic nature.
Similarly, as noted by Brownstein, hydrogen peroxide is extremely safe to use and nebulize at the diluted levels suggested. It’s also effective. All pathogens studied to date have been found to succumb to hydrogen peroxide, albeit at varying concentrations and for different amounts of exposure.
So, nebulizing hydrogen peroxide into the sinuses, throat and lungs is a simple, straightforward way to augment your body’s natural expression of hydrogen peroxide to combat infection.
While individual sensitivities to inhaled peroxide vary, even very low concentrations (below 3%) have been shown to reliably kill most pathogens.9,10,11,12Through trial and error, Brownstein found 0.04% was the lowest concentration at which patients report significant improvement, which is why he recommends that level of dilution.
Summary of Treatment
To summarize, here’s how I would treat myself or a family member:
At the very first signs of a respiratory infection, dilute food-grade hydrogen peroxide down to a 0.1% (my recommendation) or 0.04% solution (Dr. Brownstein’s recommendation). If you want, you can add one drop of 5% Lugol’s iodine solution, and nebulize using a desktop nebulizer.
Start taking quercetin and zinc, as an adjunctive therapy as soon as you know you have an infection, as the earlier you start the better. This treatment is likely ineffective late in the course of the illness as it works to inhibit viral replication. If the virus has already reproduced, it is too late and the horse is out of the barn.
The key is to have everything you need readily available. Have it in your possession before you need it. An ounce of prevention is worth a pound of cure, so procure the nebulizer, peroxide and iodine before you get ill.
If you’re exposed to someone who is sick, you can use the nebulized peroxide as a prophylactic, but if you’re healthy, it’s not recommended to nebulize daily. For prevention, also make sure your vitamin D level is above 40 ng/mL.
In the later stages of disease, NAC may be really useful. The MATH+ protocol developed by Dr. Paul Marik uses methylprednisolone, vitamin C, thiamine (vitamin B1) and heparin. Heparin is administered because COVID-19 is a blood disorder too. There are clotting complications, and the heparin seems to improve that.
NAC also prevents platelet aggregation and abnormal blood clotting. It also reduces oxidative stress and increases glutathione levels, both of which play important roles in this disease. In my view, quercetin, zinc, glutathione, vitamin D and nebulized peroxide is a home run.
“There are cheap and effective ways to treat [COVID-19], and we should be studying this,” Brownstein says. “We should be allowed to report on it, and we should be allowed to study it. [If we were], we wouldn’t have the travesty that’s happened to our country.”
BTW: this is yet another example of how “Big Science” is often a hindrance to effective treatments. In the case of COVID, somewhat of an unknown and emerging illness that can kill people quickly,there isn’t time for these randomized, controlled trials (RCT’s). There’s also the issue of ethics, mentioned by Dr. Brownstein, as well as by Dr. Raoult regarding the reason he didn’t do RCT’s with HCQ on COVID patients. For a great read on the HCQ issue and “Big Science”: https://madisonarealymesupportgroup.com/2020/08/26/hydroxychloroquine-a-morality-tale/
Lyme/MSIDS fits into this camp as well. For over 40 years CDC and IDSA ‘authorities’ haven’t batted an eye to the plethora of case studies done by independent researchers. They flat-out just ignore their work. They continue to stand by RCT’s as their guidepost when Lyme/MSIDS will probably never fit into that paradigm due to not only ethics (choosing to NOT treat very ill people) but due to other confounding factors such as coinfection presence and the fact every patient has differing symptoms. As best stated by Garg et al.:
“Our findings recognize that microbial infections in patients suffering from TBDs do not follow the one microbe, one disease Germ Theory as 65% of the TBD patients produce immune responses to various microbes.”
But there is another important point.
According to this review, 83% of all commercial tests focus only on Lyme (borrelia), despite the fact we are infected with more than one microbe.
Pascal Soriot, the chief executive officer of AstraZeneca. WIN MCNAMEE/GETTY IMAGES
The participant who triggered a global shutdown of AstraZeneca’s Phase 3 Covid-19 vaccine trials was a woman in the United Kingdom who experienced neurological symptoms consistent with a rare but serious spinal inflammatory disorder called transverse myelitis, the drug maker’s chief executive, Pascal Soriot, said during a private conference call with investors on Wednesday morning.
The woman’s diagnosis has not been confirmed yet, but she is improving and will likely be discharged from the hospital as early as Wednesday, Soriot said. (See link for article)
___________________
**Comment**
The clinical trail was also stopped in July as well due to a participant developing neurological symptoms. They state she was diagnosed with MS and it was an unrelated event.
BTW, TM is no small hiccup:
Transverse myelitis is a serious condition involving inflammation of the spinal cord that can cause muscle weakness, paralysis, pain and bladder problems. In rare instances, vaccines have triggered cases of transverse myelitis; although it can also be caused by viral infections.
They state the vaccine known as AZD1222 — uses an adenovirus that carries a gene for one of the proteins in SARS-CoV-2, the virus that causes Covid-19. The adenovirus is designed to induce the immune system to generate a protective response against SARS-2. The platform has not been used in an approved vaccine, but has been tested in experimental vaccines.
However, this protocol exists in all human DNA and exactly corresponds to C8. Therefore, what the PCR test is doing is equating C8 (which is present in ALL human DNA) as a foreign hostile material and indeed the coronavirus – Covid19 – itself.
IT FOLLOWS THAT ANY EFFICIENT COVID19 VACCINE MUST SERVE TO EITHER DELETE C8 (AS THE CORONAVIRUS), OR SUBSTANTIALLY SUPPRESS IT. HOWEVER, DOING BOTH, OR EITHER, WILL CERTAINLY RESULT IN THE DEATH, OR SEVERE MENTAL AND PHYSICAL IMPAIRMENT OF THOSE WHO TAKE IT.