Archive for the ‘research’ Category

Research Challenges in Lyme Disease – Contagion Live

 Approx 9 min

Published on Aug 29, 2017

Panelists Peter L. Salgo, MD; Patricia V. Smith; and Leonard Sigal, MD, discuss research challenges in Lyme disease and allegations on both sides of the debate over the existence of chronic forms of the disease.

**Please see comment at end of article**

Peter L. Salgo, MD: First of all, people with good will are attacking this all the time; we’re looking at this. Second, there are outliers on both sides. People who say, “This isn’t Lyme disease, it can’t be, you’re not sick,” and that you’re crazy, or others will say—and I’m not pointing to you, I’m just saying it’s the other side—“Look at this, Lyme disease can do anything. Therefore, since you’re in an endemic area, you have this, and Lyme can do this—wow—you’ve got Lyme disease.” There has got to be a middle course, right? And because there is no real consensus—I’m going to give you that there is no good testing, that we would rather have a better test—what is the impact on patients who hear this? This is medical noise. What do patients think when they hear all of this?

Patricia V. Smith: I can tell you that patients are very frustrated, and many of them have had Lyme disease for decades—and despite what some people’s opinions may be, it started out as Lyme disease. The patients see the research out there that there are things now called persisters, which just don’t appear in Lyme, but also appear in other diseases. But does the establishment want to recognize these studies that are being done at places like John Hopkins and Northeastern University by great researchers? They are doing it in laboratory settings, and the plan is to go on with animal and human studies. They are looking at other types of antibiotics, combinations of antibiotics, and whether or not pulsing doses might help. And yet, no one wants to acknowledge that perhaps these people really do have Lyme disease and they say to themselves, “Well, I’m looking at this. Maybe I’m one of these people.”

Leonard Sigal, MD: What do you mean by no one?

Peter L. Salgo, MD: I was just going to address it, which is that you said 2 things that are very provocative.One is the establishment—whatever that “them” might be—and that nobody wants to hear it. Who’s nobody?

Patricia V. Smith: Well, I’ll be honest. After 33 years, I can say if it wasn’t for the International Lyme and Associated Diseases Society, most of the patients that I have seen across the country—children who have Lyme disease, and their parents—they would not have anyone to turn to, to try to help them figure out just exactly what they do have. And contrary to some opinions, these doctors do not always diagnose Lyme. It’s just that people go to them because they have signs and symptoms. Lyme disease appears to certainly be in the mix, and they may have a history of that. Now, just because they get 3 weeks of doxycycline, I certainly think that the literature has shown that that is not necessarily a situation where that will be clear.

Leonard Sigal, MD: You’ll forgive me, but define no one: you haven’t defined the establishment.

Peter L. Salgo, MD: I’m trying to understand, because the implication in your statement is that there was some vast conspiracy to ignore Lyme disease. Is that what you really think?

Patricia V. Smith: Yes, I absolutely do, and I am not a conspiracy theorist. I have lived with it. I had 2 daughters diagnosed with it in the ´90s. One of my daughters was out of school 4 full years and 2 partial years. I would not have believed what my daughter went through, or what other patients went through, perhaps if I did not live with it.

Leonard Sigal, MD: What is the conspiracy? I want to preface my question by saying that there have been many, many accusations against many, many academic clinicians and others, that there is some sort of a conspiracy. So, you’re the perfect person. I’m not being facetious. You’re the perfect person to explain to us and to the people over there what this conspiracy is, and who’s behind it.

Peter L. Salgo, MD: And why?

Patricia V. Smith: Well, I certainly don’t know who’s behind it. I wish I did know. I do know that the government and certain medical societies take a very strong opinion. When I saw this happen, it was in the late ´80s approaching into the ´90s, and Lyme disease at that time was basically considered to be an arthritic disease. And there were a lot of rheumatologists involved. Quite frankly, there was a lot of money for that research, and so, there’s thinking out there—and a lot of patients feel this way, and some researchers, clinicians, and others—that perhaps what happened was, because that occurred, that changed the course of the disease: not just changed it physically, but into a disease that now we see there are a lot of neurologic implications. The fact that then these people, quite frankly, wanted their money. And so, perhaps it was a case of vested interest.

Peter L. Salgo, MD: But isn’t that money spent on Lyme research?

Patricia V. Smith: Not necessarily.

Leonard Sigal, MD: I beg to differ with you. NIH funds that are designated for research in sarcoidosis have to be used in research on sarcoidosis. If they’re not, then the investigator, first of all, will never get another grant and, second of all, is in deep trouble, because there’s malfeasance. Monies that were given by the NIH and other organizations to do research on Lyme disease were, first of all, never enough, I can assure you, and, second of all, never went into the pocket of any researcher, because those allegations have been made. Those monies went to pay technicians, they went to buy test tubes, and they went to pay for animal husbandry. That money was always properly spent. First, there’s an undercurrent to many of these conversations that, somehow, there’s this nefarious self-interest amongst people who are getting funds for research. That’s really not true. These are scientists who are trying to do their best. Now, there are other people who believe in a very different approach to Lyme disease or believe many different things about Lyme disease. They are welcome to approach the NIH to get funds for their research as well. They are certainly welcome to submit those papers to the top tier journals. If all these are done properly—the paper is written properly, if the grant is written properly—they’ll be taken into consideration. You can’t assume that the NIH is in on this vast conspiracy.

Patricia V. Smith: In 2012, there were hearings in Congress in the House Foreign Affairs Committee. I testified there, and some researchers testified. And a researcher who testified, a prominent researcher in the field of Lyme disease and animal work, said that in the NIH with the grant process, there were serious issues with how that process was carried out. Because, at any time, if someone wanted to do a study and said they were looking at chronic Lyme, those grants were just not considered. Apparently, those who sat in peer review didn’t really want to look at chronic Lyme because they had another bias. So, what happened was that the same kinds of studies were funded year after year after year instead of the kinds of research that really needed to be done. For example, research on new cutting-edge testing. We’re driving the horse and buggy in the testing area when we should be flying out to Saturn with the testing area. We have none of that, and none of that was done.

Peter L. Salgo, MD: I’m sure Saturn was a random choice.

Patricia V. Smith: Just one more thing.

Peter L. Salgo, MD: You’ve got about 30 more seconds, because we have to move on.

Patricia V. Smith: There were 4 treatment trials that were funded by the NIH. The conclusions on those trials were vastly broad-brushed, and I believe the doctors will probably address that issue. That was so detrimental to patients, because it said that antibiotics do not help, long-term, with Lyme disease patients. They could not make that conclusion based on that study.

 
**Comment**
This discussion is truly a crux of the matter.  What is hilarious, if not maddening, is Sigal’s incredulous disbelief in a “conspiracy.”  This is the same man that appears in journalist, Pam Weintraub’s book, Cure Unknown Inside the Lyme Epidemic. (Excellent book)
  • On page 12, “Skeptical of chronic Lyme disease as an explanation of ongoing symptoms, Sigal often diagnosed such patients as having fibromyalgia, a pain syndrome, instead.”
  • Page 271, “The New York Times quote of the day was from Leonard Sigal”  ‘Lyme disease, although a problem, is not nearly as big a problem as most people think.  The bigger epidemic is Lyme anxiety.‘”
  • Page 306, “Leonard Sigal, for instance, consulted for Prudential, Aetna, Blue Cross Blue Shield, Anthem, and Metropolitan Life, passing diagnostic and treatment decrees.  His fee was $560 an hour in 1996, though he worked for a day rate as well.  Sigal was not alone:  Other top academics consulted too.  The consultancy fees would ‘pay for a lot of college tuition, actually, ‘ Sigal had quipped under oath, when testifying against a patient’s diagnosis of Lyme.”
  • Page 316, “It didn’t take long for two competing pharmaceutical giants – SmithKline Beecham and Pasteur Merieux Connaught – to launch two potential products  (creation of the Osp A vaccine).  The Connaught effort, with the clinical trial headed by Leonard Sigal, was killed by the company in the wake of lawsuits over side effects.”   https://madisonarealymesupportgroup.com/2017/07/01/pbs-lyme-vaccine/   “LYMERIX vaccine caused 640 emergency room visits, 34 life threatening reactions, 77 hospitalizations, 198 disabilities, and 6 deaths.”
  • Page 366, “Of particular concern are the publications, more prominent in recent months, suggesting that uncured patients are not really sick with Lyme disease, but with a strange psychiatric malaise.  ‘Psychiatric comorbidity and other psychological factors distinguishing (chronic Lyme Disease) patients from other patients commonly seen in Lyme disease referral centers, and were related to poor functional outcomes,’ Leonard Sigal wrote in the journal Arthritis and Rheumatism in 2008.”

In sum, Sigal is a doctor who is extremely skeptical of chronic Lyme who obtains hefty fees for consulting against patients, who was actively creating pharmaceutical products relating to Lyme at the same time, and who brazenly states many Lyme patients are not only anxious but psycho to boot.
Kudos to Pat Smith for not throwing something at him.

Sleeper Cells: The Stringent Response and Persistence in the Borreliella Burgdorferi Enzootic Cycle

Environ Microbiol. 2017 Aug 24. doi: 10.1111/1462-2920.13897. [Epub ahead of print]

Sleeper cells: The stringent response and persistence in the Borreliella (Borrelia) burgdorferi enzootic cycle.

Cabello FC1, Godfrey HP2, Bugrysheva J1,3, Newman SA4.

Abstract

Infections with tick-transmitted Borreliella (Borrelia) burgdorferi, the cause of Lyme disease, represent an increasingly large public health problem in North America and Europe. The ability of these spirochetes to maintain themselves for extended periods of time in their tick vectors and vertebrate reservoirs is crucial for continuance of the enzootic cycle as well as for the increasing exposure of humans to them. The stringent response mediated by the alarmone (p)ppGpp has been determined to be a master regulator in B. burgdorferi. It modulates the expression of identified and unidentified open reading frames needed to deal with and overcome the many nutritional stresses and other challenges faced by the spirochete in ticks and animal reservoirs. The metabolic and morphologic changes resulting from activation of the stringent response in B. burgdorferi may also be involved in the recently described non-genetic phenotypic phenomenon of tolerance to otherwise lethal doses of antimicrobials and to other antimicrobial activities. It may thus constitute a linchpin in multiple aspects of infections with Lyme disease borrelia, providing a link between the micro-ecological challenges of its enzootic life-cycle and long-term residence in the tissues of its animal reservoirs, with the evolutionary side-effect of potential persistence in incidental human hosts.

—————————————————————————————————————————————–

**Comment**

The idea of sleeper/persistent cells in Lyme and other TBI’s is nothing new to those actively treating patients.  It’s just a matter of time before enough people in power positions acknowledge it.  Also, it needs to be understood that those infected with Lyme often have numerous pathogens that don’t respond well to the mono therapy of Doxycycline and is one reason outcomes are not good.

For more on persistent infection:  https://madisonarealymesupportgroup.com/2017/05/10/chronic-lyme-disease-a-case-definition-at-last/

https://madisonarealymesupportgroup.com/2017/08/18/drexel-prof-lyme-persists/

https://madisonarealymesupportgroup.com/2016/12/21/dr-zhang-on-persisters/


Canine Maps – Better Than the CDC’s in Predicting Lyme Disease

https://www.lymedisease.org/lymepolicywonk-canine-maps-cdc/  by Lorraine Johnson, JD, MBA

LYMEPOLICYWONK: Canine maps predict Lyme disease risk better than the CDC does.

Dogs are considered a good gauge of the exposure of their human owners to infected ticks because they usually share the same environment and visit the same outdoor areas.  In other words, canines are considered to be sentinel indicators of Lyme disease risk for humans. Not all dogs who test positive for Lyme antibodies are ill. However, they have been exposed to the Lyme disease bacteria.

A combination of studies out of the Netherlands found that hunters and their hunting dogs had tested positive for Lyme disease at similar rates (17% hunting dogs vs. 15% hunters.)

However, the same study found that pet ownership itself did not increase risk, but that exposure was the primary factor: “Only 12% of the seropositive hunters had hunting dogs which were also seropositive. Moreover, hunters without dog ownership showed no significantly lower rates of seropositivity.”

Unlike people, dogs are routinely screened for Lyme disease and other common co-infections by their vets. IDEXX has tracked Lyme disease and other tick-borne diseases in canines for years by collecting data from veterinarians who test dogs at annual check-ups.

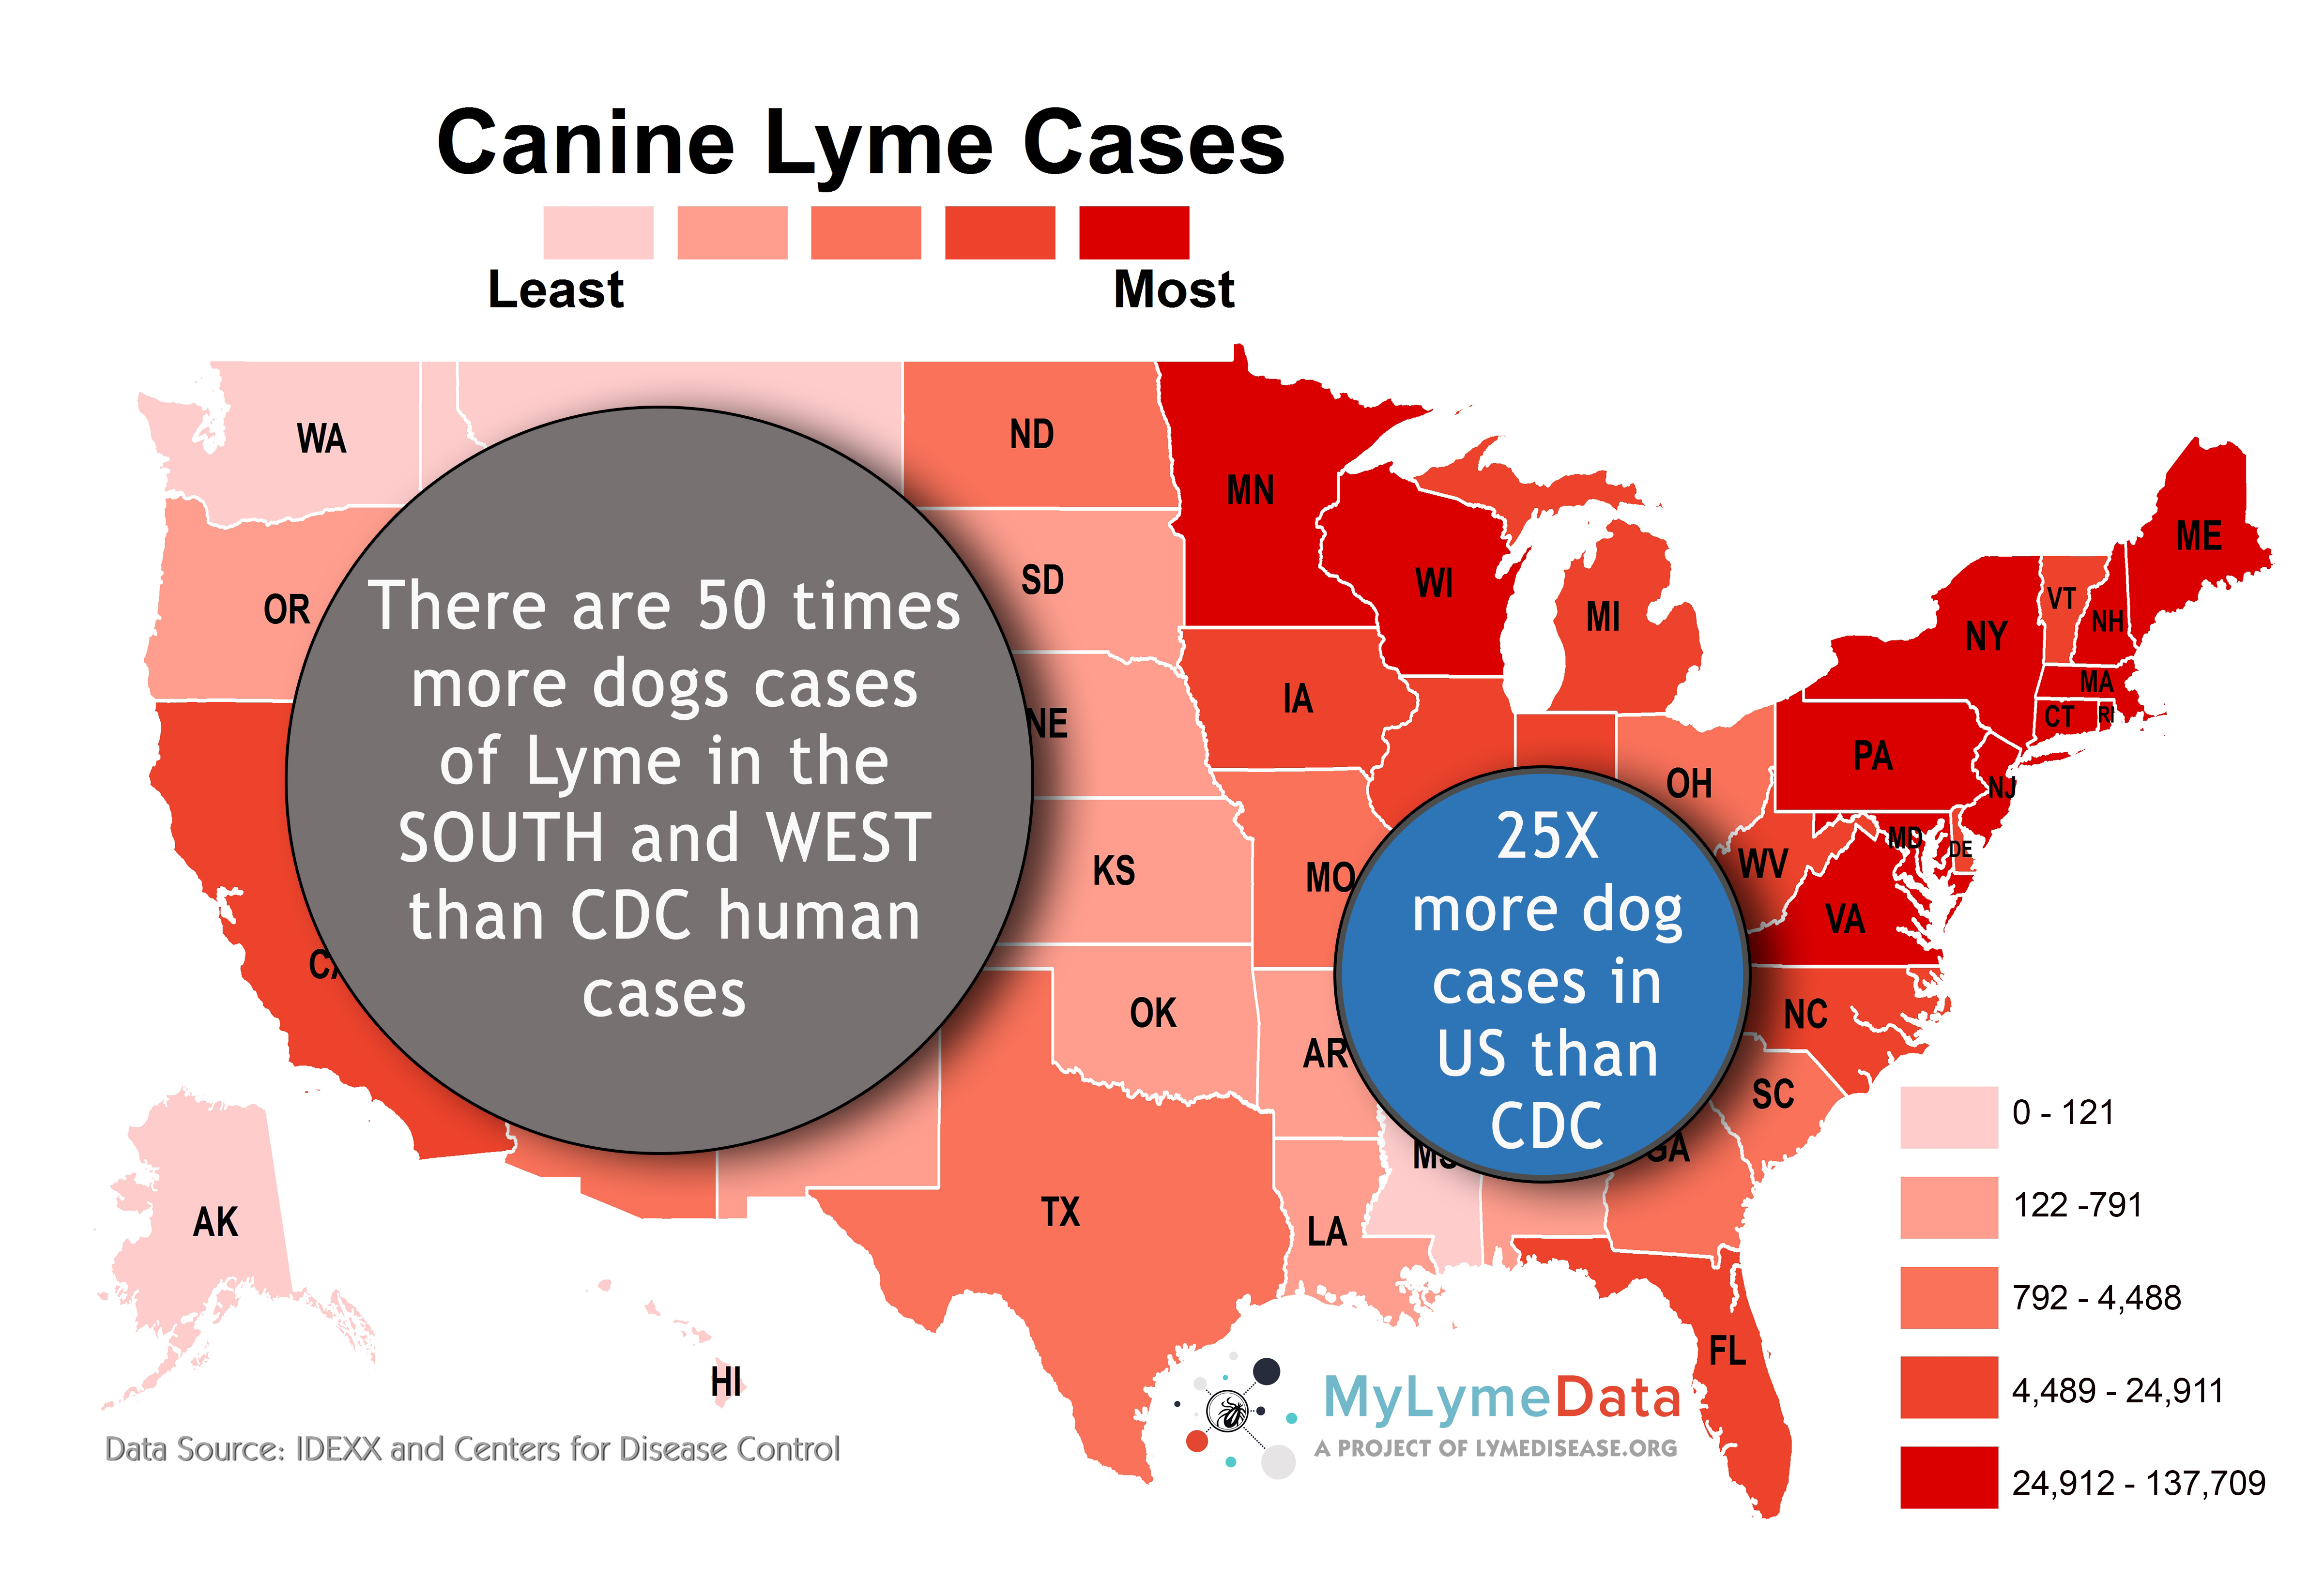
Between 2011 and 2015, IDEXX collected nearly 12 million Lyme disease test results from US veterinarians on a county-by-county basis. The data indicates that Lyme disease is present in abundance in every state in the US.

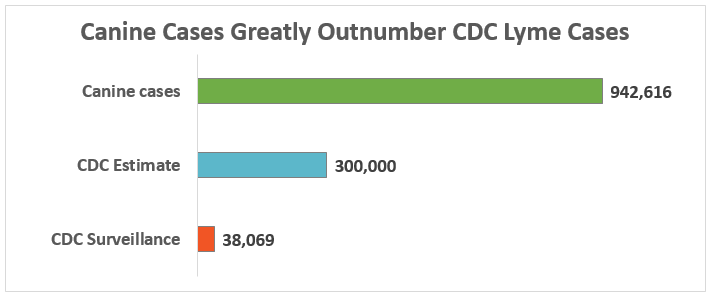
The number of canine positive test reports is vastly greater than the number of human cases reported by the Centers for Disease Control (CDC). There are close to one million canine positive test results annually in the US, compared to 38,069 cases included in CDC surveillance reports.

This means that there are roughly 25 times more canine cases than CDC surveillance cases. Even taking into account the fact that the CDC acknowledges that surveillance reports significantly underestimate the real incidence of Lyme disease by a factor of 10, the discrepancy is extraordinary. As the chart below reflects, canine cases are still more than three times the number of CDC estimated cases (300,000).

The discrepancy between CDC and canine cases is even more pronounced in the western and southern states. In the West and the South, there are 104,104 cases in dogs annually, compared to 2,342 CDC-reported cases. In other words, there are roughly 50 times more canine cases than CDC surveillance cases.

Michael Yabsley, a parasitologist at the University of Georgia, and Christopher McMahan, an assistant professor of mathematical sciences at Clemson University, have used the IDEXX canine data to develop a risk forecast map for the predicted Lyme disease prevalence — the percentage of dogs who are likely to test positive — by county in each of the 48 contiguous states.  Yabsley explains the predictive relationship:

“Dogs really are the canary in the coal mine for human infection. Our research team has evidence that the relationship between canine disease and human disease is strong. Because dogs are being tested for exposure during annual exams, these data are available on a national scale, something that is difficult to get when studying the ticks and environment directly.”

Aside from indicating environmental exposure risk, the data illustrates that people who own pets need to be aware that they face the same exposure when walking their animals or when their animals return home from outdoors carrying ticks.  Hence, preventative measures for pets—such as using appropriate tick and flea collars—are essential health matters for both people and their pets to avoid exposure.

LymeDisease.org believes that the IDEXX maps, which track Lyme disease as well as other tick-borne diseases such as ehrlichiosis and anaplasmosis, are the most accurate reflection of exposure. You can type in your zip code in the top right corner to assess your riskhere.

For example, in my zip code alone in Los Angeles, 626 cases of canine Lyme disease have been identified. (There are more than 3,500 zip codes in Los Angeles county.) That’s substantially more than the CDC reports for Californiaas a STATE for the last five years (2010-2015).

If you are interested in more information, check out the LymeSci blog on the predictive mapping of canine risk.

The LYME POLICY WONK blog is written by Lorraine Johnson, JD, MBA, who is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk.  If you have not signed up for our patient-centered big data project, MyLymeData, please register now.

Fantastic, informative article and so true.  My dog got better treatment than we did.  The tests for animals are much more accurate and veterinarians completely understand the seriousness of TBI’s (tick borne illness) unlike human doctors.  Our vet had NO TROUBLE treating my dog for over a month even though HE HAD NO SYMPTOMS.  Compare that attitude with the reality of multitudes of humans being continually turned away because of arbitrary reasons such as a lack of an EM rash, a map that demonstrating a lack of ticks or infected ticks on that geographical region, not enough time passed before accepted dogma of transmission, and so many other reasons.
For more on Pets and TBI’s:

Drexel Prof: Lyme Persists

https://newsblog.drexel.edu/2017/07/18/qa-what-happens-when-lyme-disease-is-not-treated-early/ by Lauren Ingeno July 18, 2017

Original Title: I.pacificus(F)_55sRGBBlacklegged ticks are known vectors for the bacteria Borrelia burgdorferi, which is the pathogen responsible for Lyme disease. Summer is tick season. (CDC / James Gathany)

Pennsylvania is the Lyme disease epicenter, with over 7,000 cases diagnosed in 2015.

The disease is caused by the spirochete bacteria Borrelia burgdorferi, which is carried by ticks and then transmitted to humans. When treated early, antibiotics can cure most patients. But making a diagnosis is often challenging, and chronic symptoms — such as memory problems, digestive issues and joint conditions — can linger for years, even after treatment.

Chronic Lyme is a controversial issue, dividing frustrated patients and some in the medical community who do not view their disease as a persistent infection. The Infectious Diseases Society of America, for instance, does not recommend longer courses of antibiotics even when symptoms continue.

Garth Ehrlich, PhD, a professor of microbiology and immunology at Drexel University College of Medicine, studies how chronic bacterial pathogens prevail after antibiotic therapy, and he was recently quoted in an Associated Press story about a Lehigh Valley woman who contracted the disease.

Below, he weighs in about chronic Lyme disease and why it is so hard to eliminate.

 What is the connection between your research and Lyme disease?
Lyme disease, in its persistent form, is most likely due to the bacteria forming a biofilm. I study bacterial biofilms, which are multicellular forms of bacteria, providing for increased resistance to antibiotics. If Lyme disease patients are not treated early enough or long enough, then it is possible the bacteria will form biofilms, and their acute disease will become chronic.

How is Lyme disease currently treated, and does that treatment work?
In many cases, Lyme can be treated by antibiotics, but it does not necessarily mean the disease won’t become chronic. There are many factors that contribute to the course of the disease, including the overall health and immune status of the patient, as well as the particular strain of the Lyme disease bacteria that they contract.

Why is there disagreement among the medical and scientific communities about chronic Lyme disease?
A few physicians involved in characterizing the disease in the early stages of its recognition staked their reputations on the fact that it only had an acute phase. But the bacteria that causes Lyme is a spirochete, and spirochetes are primarily associated with chronic infections, like gum disease and syphilis.

How is Lyme disease diagnosed? What are the challenges?
There is a huge problem with diagnosing it, and there are many reasons why it is difficult. There are two stages for the standard testing: an ELISA (enzyme-linked immunosorbent assay) is used to detect antibodies against B. burgdorferi proteins and a Western blot (used to separate and identify specific antibody proteins), which is more specific and used for confirmation of the ELISA.

Scientists are working to develop DNA-based tests, but they are not widely available yet, and they won’t be perfect. The problem with both types of testing is that there is enormous variability among the bacterial strains that cause the disease. Thus, an assay based on one strain might very well miss variant strains. And different individuals mount more or less of an immune response to the infection. If the infection becomes focal, then you might not be able to detect it with a DNA blood test.

What do we need to do to better combat Lyme disease?
The most important thing is to develop better diagnostics. And the next most important thing is better therapeutics. My lab is trying to develop drugs against biofilm bacteria.

For media inquiries, contact Lauren Ingeno at lingeno@drexel.edu or 215.895.2614.

________________________________________________________________________________________

**Comment**

Fantastic article revealing Oz behind the curtain:  biofilms.

I appreciate the careful wording about treating early – that it can cure most patients; however, the caveat is that treatment has to be early enough AND long enough.  I would add, and smart enough.  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

That said, there is an elephant in the room.  Since Eva Sapi discovered in vitro that doxycycline throws the spirochete into the cyst form, is it hiding out to reemerge later?  Many think so, and believe Lyme can be contributing to dementia and Alzheimer’s which means treatment should also include not only something that addresses biofilms, but something that addresses the non-cell wall form (even in acute cases).  For more:  https://madisonarealymesupportgroup.com/2016/06/03/borrelia-hiding-in-worms-causing-chronic-brain-diseases/

https://madisonarealymesupportgroup.com/2016/08/09/dr-paul-duray-research-fellowship-foundation-some-great-research-being-done-on-lyme-disease/

https://madisonarealymesupportgroup.com/2017/06/10/the-coming-pandemic-of-lyme-dementia/

The other elephant standing by the first is the prevalence of coinfections.  Research is absent on the compounding factors of coinfections.  For more:

https://madisonarealymesupportgroup.com/2017/05/01/co-infection-of-ticks-the-rule-rather-than-the-exception/

https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/


Of Birds and Ticks

http://mainepublic.org/post/battle-against-ticks-and-lyme-disease-scientists-look-skies#stream/0

In the Battle Against Ticks and Lyme Disease, Scientists Look to the Skies

 • JUL 3, 2017

As we head into the Maine outdoors this summer, the all-too-familiar warnings about how to avoid ticks reverberate in many of our heads.

Stay on the trail. Steer clear of wooded and brushy areas where ticks congregate.

But while most of us take pains to dodge the eight-legged pests, Chuck Lubelczyk heads straight for them.

As a field biologist at the Maine Medical Center Research Institute’s Lyme and Vector-Borne Disease Laboratory, he studies the spread of diseases carried by ticks, as well as by mosquitoes. That means venturing out into the fields, forests and coastlines of Maine to collect the bugs and evaluate where they pose the most risk to humans.

On a recent June day, Lubelczyk trudged into the greenery of the Wells Reserve, a 2,250-acre spread in York County headquartered at a restored saltwater farm. He partnered with researchers from the Biodiversity Research Institute in Portland to collect ticks from creatures less often associated with them: birds.

The team, assisted by several interns, set up wide nets to ensnare the birds as they flew through the area. They then delicately extricated them, tucked the birds into breathable collection bags, and toted them to a shady picnic table for easier handling. Using tweezers, the team plucked off each tick — typically feasting around the birds’ eyes, bills, and throats — and preserved the bugs for later testing at the lab.

Lubelczyk held up a vial containing at least 50 tiny nymphal deer ticks swirling in a preservative solution. They’d been tweezed off a single bird, a towhee, that morning.

Once free of ticks, the birds were then safely released to continue on their way.

https://bangordailynews.com/video/ticks-on-migratory-birds/ (Video here)

While mice, chipmunks and deer get most of the attention as hosts for ticks, “Not a lot of people talk about the bird issue,” he said. “They’re understudied in a big way, I think. They do have a real role to play.”

Ticks are an annoyance to birds, but they don’t transmit disease to them or slowly and lethally drain them of blood, as researchers have seen among moose calves in Maine. But birds facilitate the spread of ticks, picking them up in Maryland, Connecticut and other eastern states as they fly north in the spring, Lubelczyk explained.

“As they’re migrating, they’re either dropping the ticks off as they fly or when they land. They’re kind of seeding them along migration patterns.”

Emerging diseases

By tracking the birds and the ticks they carry, researchers hope to predict where Lyme and other tick-borne diseases are most likely to accelerate. Lyme is now present in every county in the state, after hitting a record of 1,488 cases in 2016, but ticks are just getting established in areas such as Aroostook and Washington counties, Lubelczyk said.

Along with Lyme, Lubelczyk tested the ticks for other two other emerging diseases, anaplasmosis and the rare but potentially devastating Powassan virus. Powassan, carried by both the deer tick and the groundhog or woodchuck tick, recently sickened two people in midcoast Maine, following the death in 2013 of a Rockland-area woman.

A recent survey Lubelczyk led found the virus in ticks crawling around southern Maine, Augusta and on Swan’s Island in Hancock County.

In the modest Scarborough lab, medical entomologist Rebecca Robich furthered the findings of that survey. Clad in a white coat and blue gloves, she cloned a tiny band of the Powassan virus’ inactivated RNA, using a sample derived from the ticks that tested positive in the survey. Robich began the work, designed to confirm the earlier test results, last winter.

She expects to know conclusively within the next month what percentage of the sampled ticks were infected with Powassan, she said.

“We’re this close to finishing,” Robich said.

Growing exposure

Ticks have become so prevalent in Maine that Lubelcyzk and his colleagues are increasingly called upon to educate the public about the health risks the arachnids pose. That includes speaking at community forums, town meetings, garden clubs and even to groups of employees.

“They’re widespread enough now that DOT, CMP, people like that are bumping into them on a regular basis,” he said. “Even people like law enforcement. The warden service, regular police with police dogs, they’re exposed.”

Their outreach also includes plenty of phone calls to the lab, fielded by its small staff of four, not counting summer interns.

“If somebody calls, we never really turn them down,” he said.

Many people don’t realize that the lab no longer identifies ticks for the public, Lubelczyk said. Now located in Scarborough along with MMC’s medical and psychiatric research centers, the lab formerly operated in South Portland, where it identified a tick’s species for anyone who walked in the door or mailed a sample. The University of Maine Cooperative Extension in Orono has since taken over that service (it does not test ticks for disease).

“It’s very hard to say no to someone when they’re really frantic because they found a tick on themselves, or their child, or even their pet,” he said. “And they’re sitting out in the parking lot.”

So far this season, the lab has fielded numerous calls from worried residents only to discover after viewing a photograph that the tick in question is a dog tick, not a deer tick. Maine is home to 15 species of ticks, and the dog tick is not among those that transmit disease to humans, at least in this region.

Through its outreach work, the lab has also found itself at the center of debates about how to manage ticks. Lubelczyk recalled a town forum on Long Island a couple of years ago that grew tense as residents discussed the use of pesticides.

“As soon as the topic of any kind of spray was brought up, not even by us, by somebody else, the fishing community was dead set against it,” he said. “Understandably, they’re worried about the stock. It really makes that difficult because you start to have divisions in how to control the ticks.”

The lab’s research on the role of birds in spreading tick-borne disease is similarly delicate, because many birds are under threat ecologically, Lubelczyk said.

“No one really cares if you try to target mice. Birds are federally protected in a lot of cases,” he said.

That other biting pest

Educating the public represents a large part of the lab’s mission but only a small part of its budget. Its outreach work is funded largely through small grants from foundations, Lubelczyk said.

Most of its research funding is targeted toward mosquitoes rather than ticks, boosted by the federal government’s initiative to combat the Zika virus, he said. While Zika hasn’t appeared in Maine, warming temperatures due to future climate change could make the state habitable for one of the mosquito species that carries it.

Lubelczyk explained this as he stood in the lab’s testing area, next to a large freezer storing petri dishes packed with frozen mosquitoes. A piece of yellow tape affixed to the door warned, “Not for food.”

While Lyme is far more prevalent, diseases carried by mosquitoes, such as West Nile virus and Eastern Equine Encephalitis, can lead to more acute illness. Both can cause inflammation of the brain and other serious complications.

Funding for tick research is generally less reliable, Lubelczyk said. The recent Powassan survey, for example, was funded by the Maine Outdoor Heritage Fund, which collects money through the sale of instant scratch lottery tickets.

A continuing threat

The lab’s role in helping to prevent tick-borne diseases has only grown as the tick population and the diseases they carry spread. The incidence of Lyme in Maine is among the highest rates in the country, averaging 82.5 cases per 100,000 people between 2013 and 2015.

Anaplasmosis and babesiosis are less common but becoming increasingly worrisome.

Lubelczyk understands the illnesses on both a professional and personal level. He contracted Lyme several years ago, after a deer tick latched onto him while he made a pitstop on the way home from work one steamy July day, he said. He had just changed into shorts and sandals and jumped out of his car for 30 seconds to hang a mosquito trap in Wells, he recalled.

A day and a half later, he spotted the tick bite. After a round of antibiotics, he recovered, Lubelczyk said.

His usual garb for field work includes long sleeves and pants treated with permethrin, along with gaiters over his boots.

“It’s embarrassing,” he said, wincing. “We always talk about wearing appropriate clothing.”

_____________________

**Comment**

I’m thankful someone is dealing with the bird issue in relation to tick propagation as I believe it will be found to be much more of an issue than previously thought.  It would help explain why folks insist they’ve been infected while near trees as birds would drop them onto trees (as well as various rodents).  Like deer, birds serve primarily as transits that can spread ticks far and wide.

While Lubelczyk doesn’t feel dog ticks are important carriers (at least in his area) – he’s mistaken.  Every tick should be suspect until proven otherwise.  Think about it:  they all exchange bodily fluids with their hosts.  Dog ticks are known to carry Tularemia, https://www.cdc.gov/ticks/diseases/index.html Rocky Mountain Spotted Fever, Ehrlichia, Mediterranean Spotted Fever, Babesia in dogs (which should also make it suspect for humans), and potentially Bartonella.  http://labs.russell.wisc.edu/wisconsin-ticks/rhipicephalus-sangineus/  No, it would not be wise to think of the Dog Tick in friendly terms.  Remember that ticks are moving all over the place defying commonly held beliefs about geography.  And while folks fighting for research grants want to promote and blame the supposed “global warming” mentioned in this article, there are many who disagree for good reasons:  https://madisonarealymesupportgroup.com/2017/07/08/global-warming-numbers-fudged/

https://madisonarealymesupportgroup.com/2017/08/14/canadian-tick-expert-climate-change-is-not-behind-lyme-disease/  John explains, “The climate change range expansion model is what the authorities have been using to rationalize how they have done nothing for more than thirty years. It’s a huge cover-up scheme that goes back to the 1980’s. The grandiose scheme was a nefarious plot to let doctors off the hook from having to deal with this debilitating disease. I caught onto it very quickly. Most people have been victims of it ever since.”
“This climate change ‘theory’ is all part of a well-planned scheme. Even the ticks are smarter than the people who’ve concocted this thing,” he says.
“Climate change has nothing to do with tick movement. Blacklegged ticks are ecoadaptive, and tolerate wide temperature fluctuations. On hot summer days, these ticks descend into the cool, moist leaf litter and rehydrate. In winter, they descend into the leaf litter, and are comfortable under an insulating blanket of snow. Ticks have antifreeze-like compounds in their bodies, and can tolerate a wide range of temperatures. For instance, at Kenora, Ontario, the air temperature peaks at 36°C and dips to –44°C, and blacklegged ticks survive successfully.

Also, please note that although there has only been one Zika death in an elderly man with a preexisting health condition in the continental U.S., all the funding is going to it and mosquito research.  This is causing untold harm here where Lyme is causing around 400,000 new cases per year.  There is no official tally on all the other coinfections that often come with Lyme as they aren’t even reportable in many states but are a crucial detail in understanding the complexity of Lyme/MSIDS.  People are often infected with numerous pathogens.  https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/

To treat this complex as a one organism/one disease would be folly.  

Also, he claims that West Nile virus and Eastern Equine Encephalitis, can lead to more acute illness, I would disagree again.  Lyme (borrelia), Babesia, Bartonella, Mycoplasma, and numerous other viruses, and funguses have killed people outright.  Heart block, encephalitis, meningitis, and other serious illnesses are caused by TBI’s. Powassan can be transmitted in under 15 minutes and can kill. Rocky Mountain Spotted Fever is another killer.  There is much to show that if the non-cell wall and biofilm formation of borrelia isn’t successfully dealt with, it could lead to dementia or Alzheimer’s in the future:  https://madisonarealymesupportgroup.com/2017/06/10/the-coming-pandemic-of-lyme-dementia/, https://madisonarealymesupportgroup.com/2016/06/03/borrelia-hiding-in-worms-causing-chronic-brain-diseases/, https://madisonarealymesupportgroup.com/2016/08/09/dr-paul-duray-research-fellowship-foundation-some-great-research-being-done-on-lyme-disease/, https://madisonarealymesupportgroup.com/2016/06/09/alzheimers-byproduct-of-infection/, https://madisonarealymesupportgroup.com/2017/01/18/a-bug-for-alzheimers/

And of course, while many cases of Lyme (borrelia) don’t kill immediately, it can make you want to die and disrupt life in such a way people commit suicide.  https://madisonarealymesupportgroup.com/2017/06/20/suicide-lyme-and-associated-diseases/, https://madisonarealymesupportgroup.com/2017/07/26/can-lyme-steal-your-mind/

If that isn’t serious, I don’t know what is.  We need to completely kill the idea that Lyme/MSIDS isn’t a severe disease(s).