Archive for the ‘research’ Category

In vitro and in vivo Evaluation of Cephalosporins for the Treatment of Lyme Disease

https://www.ncbi.nlm.nih.gov/m/pubmed/30254421/

In vitro and in vivo evaluation of cephalosporins for the treatment of Lyme disease.

Pothineni VR, et al. Drug Des Devel Ther. 2018. doi: 10.2147/DDDT.S164966. eCollection 2018.

Abstract

Background: Lyme disease accounts for >90% of all vector-borne disease cases in the United States and affect ~300,000 persons annually in North America. Though traditional tetracycline antibiotic therapy is generally prescribed for Lyme disease, still 10%-20% of patients treated with current antibiotic therapy still show lingering symptoms.

Methods: In order to identify new drugs, we have evaluated four cephalosporins as a therapeutic alternative to commonly used antibiotics for the treatment of Lyme disease by using microdilution techniques like minimum inhibitory concentration (MIC) and the minimum bactericidal concentration (MBC). We have determined the MIC and MBC of four drugs for three Borrelia burgdorferi s.s strains namely CA8, JLB31 and NP40. The binding studies were performed using in silico analysis.

Results: The MIC order of the four drugs tested is cefoxitin (1.25 µM/mL) > cefamandole (2.5 µM/mL), > cefuroxime (5 µM/mL) > cefapirin (10 µM/mL). Among the drugs that are tested in this study using in vivo C3H/HeN mouse model, cefoxitin effectively kills B. burgdorferi. The in silico analysis revealed that all four cephalosporins studied binds effectively to B. burgdorferi proteins, SecA subunit penicillin-binding protein (PBP) and Outer surface protein E (OspE).

Conclusion: Based on the data obtained, cefoxitin has shown high efficacy killing B. burgdorferi at concentration of 1.25 µM/mL. In addition to it, cefoxitin cleared B. burgdorferi infection in C3H/HeN mice model at 20 mg/kg.

________________

For more on Dr. Lewis’ work:  https://madisonarealymesupportgroup.com/2018/08/06/meet-the-researcher-kim-lewis-ph-d/

https://madisonarealymesupportgroup.com/2016/10/31/news-story-on-researcher-kim-lewis-and-chronic-lyme/

https://madisonarealymesupportgroup.com/2018/08/24/identifying-vancomycin-as-an-effective-antibiotic-for-killing-bb/


“Super responders” Are Key to Personalized Lyme Disease Treatment

https://www.lymedisease.org/personalized-lyme-disease-treatment/

By Lorraine Johnson

LYMEPOLICYWONK: “Super responders” are key to personalized Lyme disease treatment

I’m excited to report that the first study using information from MyLymeData has just been published in the medical journal Healthcare.

Using patient-reported outcome data from 3,900 people enrolled in MyLymeData, we looked at how individual patients vary in their response to treatment. Finding out who responds well to which treatments—and then learning more about those people—is an important step towards developing personalized Lyme disease treatment.

Treatment studies of patients with late/chronic Lyme disease usually take an average of how people have responded to treatment. But guess what? The average Lyme patient isn’t average! Some people improve a lot with treatment, some improve a little bit, and some people don’t improve at all. A few may even get worse.

Super responders

However, if we can identify the “super responders”—the ones who did particularly well—and take a closer look at them, we may be able to learn things that can help other patients in a similar situation. This can help drive the development of personalized Lyme disease treatment.

For lots of diseases, such as tuberculosis, pulmonary disease, and cancer, scientists are now identifying high treatment responders, but our study is the first to use this approach in Lyme disease.

The reason it hasn’t been done before in Lyme disease is because identifying how different groups of patients respond to treatment requires large samples. The largest trial funded by the National Institute of Health for patients with chronic Lyme disease enrolled just 129 people—way too small a group to look at individual treatment variation.

So instead, they lumped all of the treatment responses together—the good, the bad and the ugly—and said how patients responded “on average.” On average, there wasn’t much improvement from treatment.

But treatment averages don’t tell the whole story. A famous mathematician, Des MacHale, explains it this way: The average person has one testicle and one breast. And we all know how ridiculous that is. You can’t average a male and a female like that and get any meaningful information.

It’s the same thing when you measure patient treatment response in Lyme disease. If one person gets better and the other gets worse after treatment, you can say that on average, treatment did nothing. However, for the patient who got better, it made a world of difference. Yet, when we use an average to calculate treatment response, the favorable response of one patient is cancelled out by the negative response of another.

A better approach looks at variations in how different patients respond. Most Lyme disease patients already know this. Some patients get better, others get worse, and some don’t change with treatment. Treatment response variation is lost when individual responses are averaged.

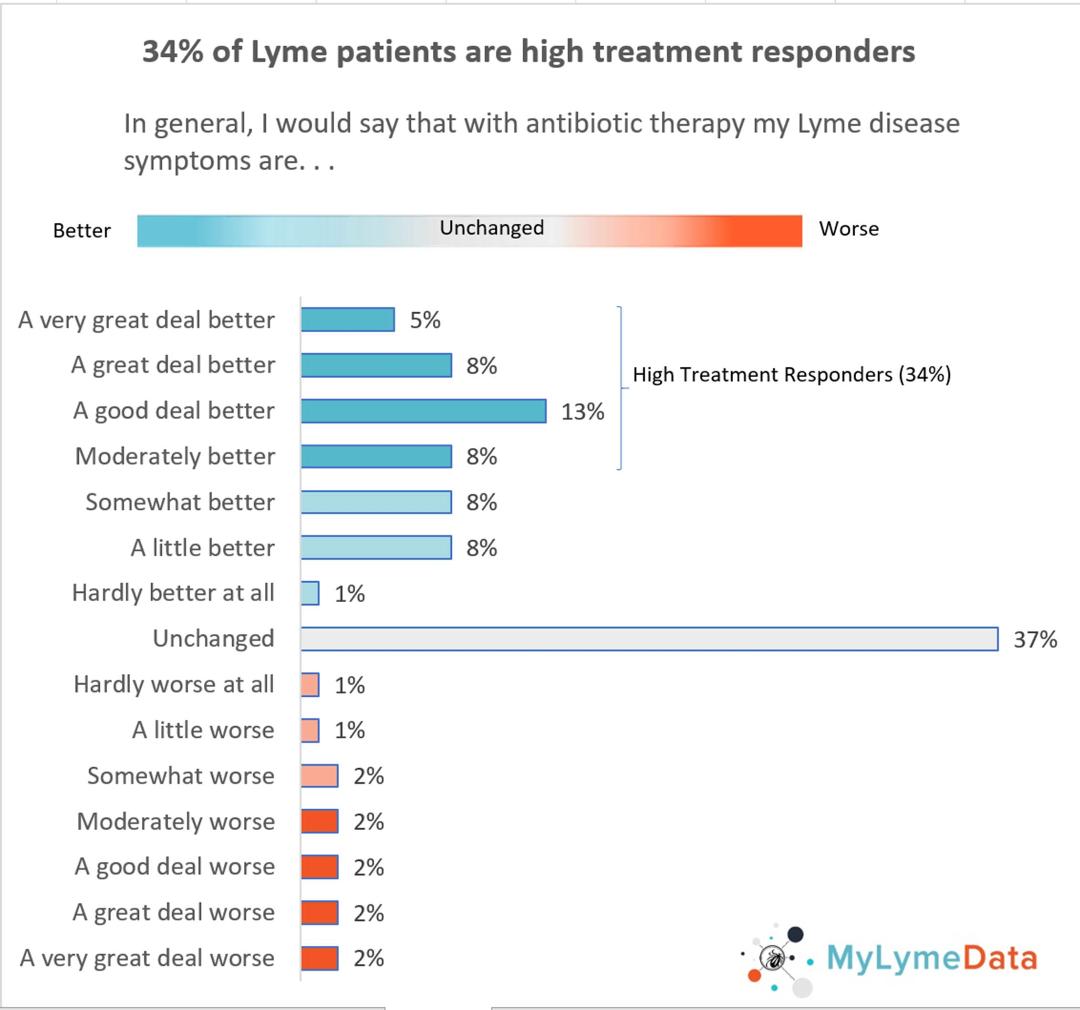
In our study, we included close to 4,000 patients, a large enough sample to look at variations in treatment response. Here’s what we found. Most patients (52%) responded positively to antibiotic treatment and some—roughly a third—responded very well to treatment. These patients said that they felt moderately to a very great deal better after taking antibiotics. Very few said that they felt worse after taking antibiotics (only 12%).
If I were a patient with chronic Lyme disease—which I was by the way–I would want to know that roughly a third of those in the sample were “high treatment responders”—meaning that they reported that after taking antibiotics their symptoms improved moderately to a very great deal. This is the type of information that patients want to know and that is why we conducted this study.

This is the first of many studies to be published using the data from MyLymeData.  So stay tuned! And if you are not enrolled in MyLymeData—I encourage you to stop what you are doing and sign up now. It is only by having patients pool their data that we will make progress in this disease.

Here is a short video I recorded explaining more about the study’s results.

Click here to read the full study.

Click here to enroll in MyLymeData.

Lorraine Johnson, JD, MBA, is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk. If you have not signed up for our patient-centered big data project, MyLymeData, please register now.

_________________

**Comment**

If you haven’t enrolled in this Bigdata research, please do.

The more people who do this, the more information we will have to look at.

Since the largest NIH study was done in 2008, EIGHT YEARS AGO, you’d think researchers & doctors would be a bit open-minded.  Can you imagine basing cancer or AIDS treatments on EIGHT YEAR OLD STUDIES?  https://www.niaid.nih.gov/diseases-conditions/chronic-lyme-disease.  Another, done in 2003 (15 years ago) only looked at 28 days of IV antibiotic compared to placebo in 55 patients, hardly a representative sample, and what’s 28 days of IV abx going to do with a persistent pathogen typically coupled with other pathogens making cases extremely complex?

No, The Cabal has run the research in a biased and skewed manner for over 40 years.  Time for a change.

Interestingly, an IDSA founder disagreed with their stance and used high powered antibiotics quite successfully:  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/ 51 difficult cases are represented.


Study Finds Q Fever & Rickettsia (Typhus) in Australian Ticks and People

https://www.ncbi.nlm.nih.gov/m/pubmed/30270855/

Ixodes holocyclus Tick-Transmitted Human Pathogens in North-Eastern New South Wales, Australia.

Graves SR, et al. Trop Med Infect Dis. 2016.

Abstract

A group of 14 persons who live in an area of Australia endemic for the Australian paralysis tick, Ixodes holocyclus, and who were involved in regularly collecting and handling these ticks, was examined for antibodies to tick-transmitted bacterial pathogens.

Five (36%) had antibodies to Coxiella burnetii, the causative agent of Q fever and three (21%) had antibodies to spotted fever group (SFG) rickettsiae (Rickettsia spp). None had antibodies to Ehrlichia, Anaplasma, Orientia, or Borrelia (Lymedisease) suggesting that they had not been exposed to these bacteria.

A total of 149 I. holocyclus ticks were examined for the citrate synthase (gltA) gene of the SFG rickettsiae and the com1 gene of C. burnetii; 23 (15.4%) ticks were positive for Rickettsia spp. and 8 (5.6%) positive for Coxiella spp. Sequencing of fragments of the gltA gene and the 17 kDa antigen gene from a selection of the ticks showed 99% and 100% homology, respectively, to Rickettsia australis, the bacterium causing Queensland tick typhus.

Thus, it appears that persons bitten by I. holocyclus in NE NSW, Australia have an approximate one in six risk of being infected with R. australis. Risks of Q fever were also high in this region but this may have been due to exposure by aerosol from the environment rather than by tick bite. A subset of 74 I. holocyclus ticks were further examined for DNA from Borrelia spp., Anaplasma spp. and Ehrlichia spp. but none was positive. Some of these recognised human bacterial pathogens associated with ticks may not be present in this Australian tick species from northeastern New South Wales.

_____________________

**Comments**

Folks in Australia have been fighting the denial of authorities for decades regarding Lyme Disease:  https://madisonarealymesupportgroup.com/2018/08/21/our-battle-ongoing-lyme-disease-in-australia/

https://madisonarealymesupportgroup.com/2016/11/03/ld-not-in-australia-here-we-go-again/

https://madisonarealymesupportgroup.com/2018/10/03/aussie-widow-of-lyme-disease-victim-to-sue-nsw-health/  A SYDNEY woman launches a class action against NSW Health after autopsy results showed her husband was riddled with Lyme in his liver, heart, kidney, and lungs.  He was only 44 years old and was bitten by a tick while filming a TV show in Sydney.

Now how in the world did that happen?

While they still deny Lyme (borrelia) this recent study definitively shows a number of pathogens in Australian ticks and humans including Rickettsia (more commonly known as Tick & arthropod Typhus, Queensland typhus or Rickettsia australis), as well as Q Fever.

Tick Typhus is similar to Rocky Mountain spotted fever, but deemed not as severe.  Symptoms include:

  • Fever
  • Headache
  • Malaise
  • Bloodshot eyes
  • Red lump at tick bite site
  • Ulceration at tick bite site
  • Black scab at tick bite site
  • Enlarged local lymph nodes
  • Forearm red rash
  • Red body rash
  • Palm rash
  • Rash on soles of feet

Doxycycline is the front-line drug for typhus and broad-spectrum antibiotics aren’t helpful.

Fact sheet on typhus:  https://www.health.nsw.gov.au/Infectious/factsheets/Factsheets/typhus.PDF  The perps are typically lice, fleas, mites, and ticks.

https://madisonarealymesupportgroup.com/2018/08/19/monster-ticks-found-in-germany-threaten-europe-with-deadly-disease-crimean-congo-fever/  In this article, they found a tropical form of tick typhus in tropical ticks found in Germany. Typhus is making a comeback, particularly in the southern U.S. Migrating birds are transporting ticks as well as the diseases they carry worldwide 

Fact sheet on Q Fever: http://www.stopticks.org/ticks/qfever.asp

Caused by the bacteria Coxiella burnetii, it can cause pneumonia and hepatitis (liver inflammation) in its early stage, and infection of the heart valves (endocarditis) in its chronic stage.  Perps are the Brown Dog Tick (Rhipicephalus sanguine us), Rocky Mountain Wood Tick (Dermacentor andersoni), and the Lone Star Tick (Amblyomma americium).

https://coloradoticks.org/tick-borne-diseases/q-fever/  This article states it’s usually a mild disease with flu-like symptoms but sometimes it can resurface years later.  This more deadly, chronic form, of Q fever can damage heart, liver, brain and lungs. C. burnetii is highly infectious. Humans that are susceptible to this disease can be infected by a single organism. It is considered a significant threat for bio warfare and is classified as a Category B agent of bioterrorism.

The severity and combination of signs and symptoms vary greatly. About half the people infected with Q fever will get sick. Symptoms include:

  • High fever (up to 105°F)
  • Fatigue
  • Severe headache
  • General malaise
  • Myalgia
  • Chills or sweats
  • Non-productive cough
  • Nausea
  • Vomiting
  • Diarrhea
  • Abdominal pain
  • Chest pain

Doxycycline is also the front-line drug for this with quinolone antibiotics as an alternative.

Add the Ixodes holocyclus tick to this list as well.

And before you think it can only ever be in Australia, this article in the 2013 issue of the Australian Veterinary Journal shows the likelihood of a population of Ixodes holocyclus breeding outside their common range.  https://conference.ava.com.au/13097.

Well there goes the neighborhood.

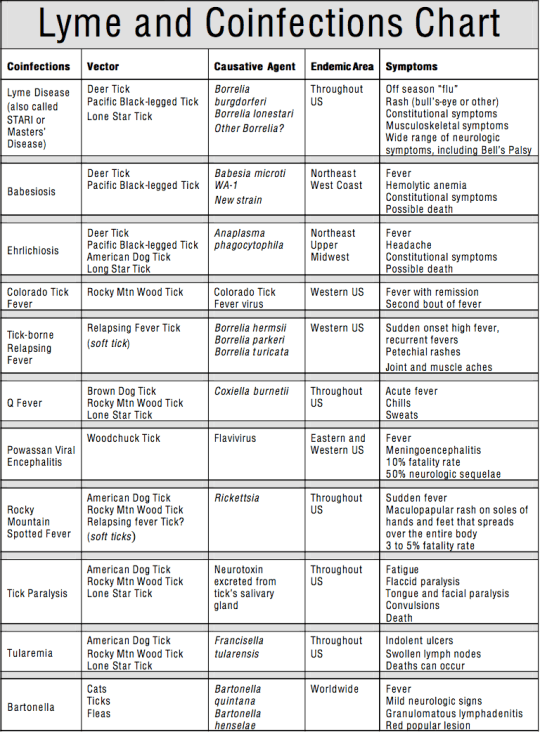
Here’s a nifty chart:  https://www.lymedisease.org/lyme-basics/co-infections/other-co-infections/ (Please remember this is constantly changing)

Screen-Shot-2014-08-26-at-5.27.54-PM

If there’s one think I know for sure, it’s that nothing about ticks and the diseases they carry is sure.

They are finding tropical ticks in Germany (where they shouldn’t be)  https://madisonarealymesupportgroup.com/2018/08/19/monster-ticks-found-in-germany-threaten-europe-with-deadly-disease-crimean-congo-fever/ and they are finding Asian ticks in the U.S. (where they shouldn’t be)  https://madisonarealymesupportgroup.com/2018/10/03/1st-person-bitten-by-east-asian-longhorned-tick/.

When is the CDC going to get the memo and scrap the tick maps?


Removing the Mask of Average Treatment Effects in Chronic Lyme Disease Research Using Big Data & Subgroup Analysis

https://www.mdpi.com/2227-9032/6/4/124

Healthcare 2018, 6(4), 124; https://doi.org/10.3390/healthcare6040124

Removing the Mask of Average Treatment Effects in Chronic Lyme Disease Research Using Big Data and Subgroup Analysis

1MyLymeData, Chico, CA 95927, USA
2Analytic Designers LLC., Bethesda, MD 20817, USA
3Paul G. Allen School of Computer Science and Engineering, University of Washington, Seattle, WA 98195, USA
Author to whom correspondence should be addressed.
Received: 4 September 2018 / Revised: 9 October 2018 / Accepted: 9 October 2018 / Published: 12 October 2018
Full-Text   |   PDF [1495 KB, uploaded 12 October 2018]

Abstract

Lyme disease is caused by the bacteria borrelia burgdorferi and is spread primarily through the bite of a tick. There is considerable uncertainty in the medical community regarding the best approach to treating patients with Lyme disease who do not respond fully to short-term antibiotic therapy. These patients have persistent Lyme disease symptoms resulting from lack of treatment, under-treatment, or lack of response to their antibiotic treatment protocol. In the past, treatment trials have used small restrictive samples and relied on average treatment effects as their measure of success and produced conflicting results. To provide individualized care, clinicians need information that reflects their patient population. Today, we have the ability to analyze large data bases, including patient registries, that reflect the broader range of patients more typically seen in clinical practice. This allows us to examine treatment variation within the sample and identify groups of patients that are most responsive to treatment. Using patient-reported outcome data from the MyLymeData online patient registry, we show that sub-group analysis techniques can unmask valuable information that is hidden if averages alone are used. In our analysis, this approach revealed treatment effectiveness for up to a third of patients with Lyme disease. This study is important because it can help open the door to more individualized patient care using patient-centered outcomes and real-world evidence. View Full-Text

___________________
**Comment**
Great work here.  We need to start the coinfection discussion; however, as Lyme is just one beast of many and the involvement of other pathogens muddies the water considerably and needs addressing.  Many, many patients WILL NOT improve on a Lyme only treatment.


Transmission of Borrelia Miyamotoi By Tranovarially-Infected Larval Ticks

https://www.ncbi.nlm.nih.gov/m/pubmed/30007502/

Transmission of the relapsing fever spirochete, Borrelia miyamotoi, by single transovarially-infected larval Ixodes scapularis ticks.

Breuner NE, et al. Ticks Tick Borne Dis. 2018.

Abstract

The relapsing fever spirochete, Borrelia miyamotoi, is increasingly recognized as a cause of human illness (hard tick-borne relapsing fever) in the United States. We previously demonstrated that single nymphs of the blacklegged tick, Ixodes scapularis, can transmit B. miyamotoi to experimental hosts. However, two recent epidemiological studies from the Northeastern United States indicate that human cases of hard tick-borne relapsing fever peak during late summer, after the spring peak for nymphal tick activity but coincident with the peak seasonal activity period of larval ticks in the Northeast. These epidemiological findings, together with evidence that B. miyamotoi can be passed from infected I. scapularis females to their offspring, suggest that bites by transovarially-infected larval ticks can be an important source of human infection. To demonstrate experimentally that transovarially-infected larval I. scapularis ticks can transmit B. miyamotoi, outbred Mus musculus CD1 mice were exposed to 1 or 2 potentially infected larvae. Individual fed larvae and mouse blood taken 10 d after larvae attached were tested for presence of B. miyamotoi DNA, and mice also were examined for seroreactivity to B. miyamotoi 8 wk after tick feeding.

We documented B. miyamotoi DNA in blood from 13 (57%) of 23 mice exposed to a single transovarially-infected larva and in 5 (83%) of 6 mice exposed to two infected larvae feeding simultaneously. All 18 positive mice also demonstrated seroreactivity to B. miyamotoi. Of the 11 remaining mice without detectable B. miyamotoi DNA in their blood 10 d after infected larvae attached, 7 (64%) had evidence of spirochete exposure by serology 8 wk later.

Because public health messaging for risk of exposure to Lyme disease spirochetes focuses on nymphal and female I. scapularis ticks, our finding that transovarially-infected larvae effectively transmit B. miyamotoi should lead to refined tick-bite prevention messages.

______________


**Comment**

A mother tick CAN transmit to her own children.  (Just as human mothers can):  https://madisonarealymesupportgroup.com/2018/06/19/33-years-of-documentation-of-maternal-child-transmission-of-lyme-disease-and-congenital-lyme-borreliosis-a-review/

This is why it is unwise to focus on months of the year regarding when you can and can not become infected.  First, ticks are marvelous ecoadaptors and can survive the harshest environments:  https://madisonarealymesupportgroup.com/2018/08/13/study-shows-lyme-not-propelled-by-climate-change/.  Second, we can’t just be concerned with one stage of the tick but recognize the potential transmission of ALL stages to infect.

There’s a high probability more than ticks can transmit:  https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/

Then, there’s the added complexity of being able to transmit many things simultaneously:  https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/

They are finding ticks in places they shouldn’t be making geographical maps virtually useless:  https://madisonarealymesupportgroup.com/2018/07/16/ticks-that-carry-lyme-disease-are-spreading-fast/  (Please also read my comment at end of article)

Time for researchers to quit sounding so “all knowing,” and write research articles carefully, making sure to remember that what they write will and has been used against patients in every possible way imaginable.
Plus, everything they thought they knew is constantly changing.