Archive for the ‘research’ Category

Redfield Breaks Silence on Long COVID, Cancer, ‘Vaccines,’ and Chronic Lyme

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/34045161?

Dr. Redfield Breaks His Silence — Long COVID, Cancer & Vaccines [And Chronic Lyme]

Carl Tuttle
Hudson, NH, United States
Nov 8, 2025

So it looks like Redfield is now a Scientific Advisor for TechImmune, LLC.

That vaccine money grab through patent royalties or advisory roles is just too lucrative to pass up.

From the TechImmune website: https://techimmune.com/

“TechImmune, LLC has been awarded a business (SBIR) grant from the U.S. National Institute of Allergy and Infectious Diseases (NIH) to develop a Universal Vaccine Against Multiple Coronavirus Variants of Concern.  Additional grants are pending.”
 
Scientific Advisor
Dr. Redfield is the former Director of the Centers for Disease Control and Prevention and a distinguished public health leader with decades of experience in medicine and research. He played a key role as a contributor to Operation Warp Speed, helping accelerate the development of life-saving vaccines  [Huh???] during the COVID-19 pandemic. Today, he continues to advance the field through his active involvement in Long COVID clinical research.

Please see my email to Dr Redfield following his interview from the Dana Parish Podcast.

(Picture of Redfield was found here)

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “rrredfieldmd@gmail.com” <rrredfieldmd@gmail.com>
Cc: dana@danaparish.com, sephillips18@gmail.com, skottilil@ihv.umaryland.edu
Date: 11/06/2025 10:39 AM EST
Subject: The Dana Parish Podcast; Dr. Redfield Breaks His Silence — Long COVID, Cancer & Vaccines [And Chronic Lyme]

The Dana Parish Podcast

Dr. Redfield Breaks His Silence — Long COVID, Cancer & Vaccines [And Chronic Lyme]
http://

Excerpt: 

Dana Parish: “Why are we still suffering like this… it is known at the upper echelons of Public Health that Lyme is chronic.”

Dr. Redfield: “Cause people can’t get a simple diagnostic test to prove it.”

Institute of Human Virology, University of Maryland
725 West Lombard St, Room N560
Baltimore, MD 21201

Dr. Redfield,

You are mistaken. The real reason why “we are still suffering” is outlined in the correspondence below addressed to Adrian Duncan, Group Vice President of WebMD referencing their latest CME offering for Lyme disease. Google’s Gemini AI describes it as: intent to deceive for financial gain.

Carl Tuttle
Independent Researcher
Hudson, NH USA

Cc: Shyamasundaran Kottilil, MBBS, PhD
Institute of Human Virology, Director, Clinical Care & Research; Chief, Infectious Diseases; Professor of Medicine

Email sent to Adrian Duncan, Group Vice President WebMD:

#1 ——— Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: aduncan@webmd.net
Cc: cme@medscape.net, caitlin@medlitera.com, naseem@medlitera.com, michelle@medlitera.com
Date: 10/24/2025 12:42 PM EDT
Subject: Medscape Now! Understanding the Latest Evidence and Best Practices for Interprofessional Care of Post-Treatment Lyme Disease Syndrome

Medscape Now! Understanding the Latest Evidence and Best Practices for Interprofessional Care of Post-Treatment Lyme Disease Syndrome
https://www.medscape.org/viewarticle/medscape-now-understanding-latest-evidence-and-best-2025a1000rrr
CME Author: Naseem Bazargan, MPH     Developed with AI assistance.

Excerpt:

State of the Evidence

“To date, our understanding of the pathophysiology of Lyme IACI remains limited,[4] with little to no evidence supporting chronic Borrelia infection as the underlying cause.”

Adrian Duncan, Group Vice President
Global Head of Education & Medical Affairs

Dear Mr. Duncan,

In reference to the Medscape article written by Naseem Bazargan, I asked Google’s Gemini AI the following questions:

The latest Medscape CME education claiming to be developed with AI assistance, appears to have omitted the following references:

2018 Middelveen study; “Persistent Borrelia Infection in Patients with Ongoing Symptoms of Lyme Disease” identifying twelve patients who were culture positive after antibiotic treatment. Some of these patients had taken as many as eleven different types of antibiotics. Also missing is the NIH funded Embers studies of persistent Bb infection in monkeys and mice. And the Sapi study: “The Long-Term Persistence of Borrelia burgdorferi Antigens and DNA in the Tissues of a Patient with Lyme Disease”  Here is the positive culture report from the CDC at Fort Collins Colorado and the chronic Lyme autopsy results from the patient in the Sapi study: Page 1, 2, 3, 4, 5, 6, 7. The destructive nature of Borrelia is evident in the patient’s liver (nutmeg liver), kidneys, heart, lungs and brain. The patient died after the insurer refused additional IV antibiotic therapy.

Additional reference from 1990: “Chronic neurologic manifestations of Lyme disease” Dr. Allen Steere

In fact, there appears to be 700 references identifying persistent infection. 
 
Question: So, is AI participating in the collusion to suppress evidence of antibiotic resistance or chronic Lyme disease? And what about the other 700 references identifying persistent infection?

Mr. Duncan…  I will spare you the lengthy discourse and get right to the point.

Questions to AI:

1. Does a chronic relapsing seronegative disease fit the vaccine model?

AI Response:

A chronic, relapsing, seronegative disease does not fit the traditional vaccine model, which is primarily designed to prevent initial infections. The characteristics you describe present significant scientific and commercial challenges for vaccine developers.

2. Since you agreed that a chronic, relapsing, seronegative disease does not fit the traditional vaccine model this in and of itself would be the motivation to conceal any and all evidence of persistent infection wouldn’t you agree? This so-called debate is not a debate at all and deserves a criminal investigation. Who would be a suitable candidate to approach for a legal case?

AI Response: Allegations of medical fraud are typically handled as civil matters, but they can become criminal if there is evidence of gross negligence, recklessness, or intent to deceive, especially for financial gain.

Mr. Duncan,

Thirty-four years ago Dr. Allen Steere identified chronic Lyme disease which should have set off a red flag prompting an immediate search for better antimicrobials but then did a 180° as he became principal investigator (PI) of the Phase 3 clinical trial for the first Lyme disease vaccine. So all the eggs were put into the vaccine basket while a campaign was orchestrated to discredit the sick and disabled patient population along with the courageous clinicians attempting to help these patients. Apparently, a chronic relapsing seronegative disease did not fit the business model of patent royalties, vaccine development and pharmaceutical profits. This set the stage for long-term treatment denial and unimaginable pain and suffering around the world. It has been ongoing for over three decades now and the latest CME from Medscape is propagating this travesty.

Lyme disease has been grossly mishandled by our public health officials for the sake of a vaccine. A false public health narrative was enforced and any clinician who did not follow that narrative risked losing their license to practice medicine as seen in the documentary: Under our Skin. (please watch the 5min trailer)

I want to make this crystal clear; suppressing evidence of antibiotic resistance is not collaboration, it is collusion. Will you turn a blind eye to the facts/evidence I have presented?

A response to this inquiry is requested.
Respectfully submitted,

Carl Tuttle
Independent Researcher
Hudson, NH USA

Additional references:
 
Evidence Of Persistence Of Lyme Disease In Humans
https://www.lymedisease.org/lyme-basics/resources/evidence-of-persistence-lyme-disease-in-humans/

[View chart here]

#2 ———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>To: aduncan@webmd.netCc: cme@medscape.net, caitlin@medlitera.com, naseem@medlitera.com, michelle@medlitera.comDate: 10/28/2025 9:28 AM EDT
Subject: Re: Medscape Now! Understanding the Latest Evidence and Best Practices for Interprofessional Care of Post-Treatment Lyme Disease Syndrome

Dear Mr. Duncan,

In 2016 Dr. Paul Auwaerter, past president of the Infectious Diseases Society of America coauthored a study revealing the persister form of Borrelia burgdorferi resistant to antibiotics.

Here is a timeline of events:

2015

Standard antibiotic treatment for Lyme disease does not kill persistent Borrelia bacteria.
http://droopyyoupi.blogspot.com/2015/08/standart-antibiotic-treatment-for-lyme.html

Excerpt:

-What has tuberculosis and Borrelia burgdorferi in common? In the late stage of the disease occurs persistent (tolerant) bacteria, which essentially means that the bacteria lasts and lasts and lasts. They protect themselves against antibiotics and are difficult to treat.

– Both Borrelia burgdorferi and tuberculosis is relatively easy to cure in the early stages, even with the use of one antibiotic. In the late stage it is impossible to cure the disease with the same type of treatment in the acute phase, said Dr. Ying Zhang when he visited the year NorVect conference.

-Dr. Ying Zhang is a professor at the Department of Molecular Microbiology and Immunology at the Johns Hopkins Bloomberg School of Public Health
-Two days after NorVect conference, published Dr. Ying Zhang’s latest research Identification of new compounds with high activity against stationary phase Borrelia burgdorferi from the NCI compound collection.

2016

A Drug Combination Screen Identifies Drugs Active against Amoxicillin-Induced Round Bodies of In Vitro Borrelia burgdorferi Persisters from an FDA Drug Library Jie Feng 1, Wanliang Shi 1, Shuo Zhang 1, David Sullivan 1, Paul G Auwaerter 2, Ying Zhang 1
https://pubmed.ncbi.nlm.nih.gov/27242757/

Abstract

Under experimental stress conditions such as starvation or antibiotic exposure, Borrelia burgdorferi can develop round body forms, which are a type of persister bacteria that appear resistant in vitro to customary first-line antibiotics for Lyme disease. To identify more effective drugs with activity against the round body form of B. burgdorferi, we established a round body persister model induced by exposure to amoxicillin (50 μg/ml) and then screened the Food and Drug Administration drug library consisting of 1581 drug compounds and also 22 drug combinations using the SYBR Green I/propidium iodide viability assay. We identified 23 drug candidates that have higher activity against the round bodies of B. burgdorferi than either amoxicillin or doxycycline.

2022

Nitroxoline Drug Combinations Are More Active Than Lyme Antibiotic Combination and Can Eradicate Stationary-Phase Borrelia burgdorferi
Alvarez-Manzo, Hector S.1; Zhang, Yumin1; Zhang, Ying2,✉
https://journals.lww.com/imd/fulltext/2022/09000/nitroxoline_drug_combinations_are_more_active_than.7.aspx

Abstract

Lyme disease (LD), caused by Borrelia burgdorferi, is the most common vector-borne disease in the United States and Europe. Despite the standard 2–4 weeks’ antibiotic treatment, approximately 10%–20% of patients will develop posttreatment LD syndrome, a condition that is poorly understood. One of the probable causes is thought to be the presence of B. burgdorferi persister forms that are not effectively killed by the current LD antibiotics. In this study, we evaluated nitroxoline, an antibiotic used to treat urinary tract infections, for its activity against a stationary-phase culture enriched with persister forms of B. burgdorferi. Nitroxoline was found to be more active than doxycycline and equally active as cefuroxime (standard LD antibiotics) against B. burgdorferi. Importantly, the nitroxoline two-drug combinations nitroxoline + cefuroxime and nitroxoline + clarithromycin, as well as the nitroxoline three-drug combination nitroxoline + cefuroxime + clarithromycin, were as effective as the persister drug daptomycin-based positive control three-drug combination cefuroxime + doxycycline + daptomycin, completely eradicating stationary-phase B. burgdorferi in the drug-exposure experiments and preventing regrowth in the subculture study. Future studies should evaluate these promising drug combinations in a persistent LD mouse model.

Dr. Redfield… This is the missing research that should have been conducted early in the discovery phase of the disease but as we now know, all the eggs were put into the vaccine basket while a campaign was orchestrated to discredit the sick and disabled patient population along with the courageous clinicians attempting to help these patients. What has been deceitfully established here in the US is wreaking havoc globally. Example: Lyme disease: Australians ‘being treated worse than a dog riddled with mange’, Senator John Madigan says
https://www.abc.net.au/news/2016-01-11/lyme-disease-treatment-in-australia-criticised-by-john-madigan/7080708

This research is being suppressed as the disabled Lyme patient population around the globe remain sick indefinitely. (Three decades and counting)

Guideline signatory Dr. Raymond Dattwyler owns 24 patents for Lyme disease that include diagnostic testing and vaccines both live bacteria and oral and endorses the categorical assertion that chronic Lyme disease does not exist yet his patent for novel chimeric nucleic acids and protein antigens which could serve as a basis for a vaccine or for improved immunodiagnostic reagents for Lyme disease, issuing almost contemporaneously with the 2006 IDSA Lyme Disease Guidelines seems to say exactly the opposite:

“Currently, Lyme Disease is treated with a range of antibiotics, e.g. tetracycline, penicillin and cephalosporins. However, such treatment is not always successful in clearing the infection. Treatment is often delayed due to improper diagnosis with the deleterious effect that the infection proceeds to a chronic condition, where treatment with antibiotics is often not useful. One of the factors contributing to delayed treatment is the lack of effective diagnostic tools.” (Dattwyler, et.al. United States Patent 7,179,448)

Please take a moment if you will to review the following inquiry addressed to doctor Dattwyler who has set the stage for long-term treatment denial. It should be noted that there was no response.

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: Raymond_Dattwyler@nymc.edu
Cc: npjvaccines@nature.com, abarrett@utmb.edu, R.W.Titball@exeter.ac.uk, mgomesso@uthsc.eduDate: 01/06/2023 2:46 PM EST
Subject: The year that shaped the outcome of the OspA vaccine for human Lyme disease

npj Vaccines Jan 2022 

The year that shaped the outcome of the OspA vaccine for human Lyme disease
https://www.nature.com/articles/s41541-022-00429-5 Raymond J. Dattwyler & Maria Gomes-Solecki

Department of Microbiology and Immunology
New York Medical College
Valhalla, NY
Raymond J. Dattwyler, Corresponding Author

Dear Dr. Dattwyler,

I read your manuscript with great interest as you call attention to a treatment-resistant Lyme arthritis with “no evidence of DNA” found in the joints of patients after antibiotic treatment.

For some strange reason however, I could not find the following 1995 publication within your paper identifying treatment-resistant neuroborreliosis:

European Neurology 1995

Seronegative Chronic Relapsing Neuroborreliosis
https://www.karger.com/Article/Abstract/117104
Lawrence C., Lipton R.B., Lowy F.D., Coyle P.K.d
 
Abstract

We report an unusual patient with evidence of Borrelia burgdorferi infection who experienced repeated neurologic relapses despite aggressive antibiotic therapy. Each course of therapy was associated with a Jarisch-Herxheimer-like reaction. Although the patient never had detectable free antibodies to B. burgdorferi in serum or spinal fluid, the CSF was positive on multiple occasions for complexed anti-B. burgdorferi antibodies, B. burgdorferi nucleic acids and free antigen.

In fact, Dr. Dattwyler there seems to be a great deal of “treatment-resistant” evidence published in multiple journals over the past three decades:

Peer Reviewed Evidence of Persistence of Lyme Disease Spirochete Borrelia burgdorferi and Tick-Borne Diseases (700 References)
https://www.dropbox.com/s/n09sk90eo6xz7ua/700%20articles%20LYME%20EvidenceofPersistence-V2.pdf?dl=0

So that brings me to the reason for this email…

Question:

Does a chronic relapsing seronegative disease fit the vaccine model? If not, would that, in and of itself, be the hidden reason for denying chronic (treatment-resistant) Lyme disease for almost three decades?  In other words, patent royalties and pharmaceutical profits over lifesaving care?

A response to this inquiry is requested.
Carl Tuttle
Hudson, NH

Cc: Alan D.T. Barrett, PhD Editor-in-Chief
Rick Titball, PhD, DSc, Deputy Editor

 
Letter to the Editor of the BMJ published June 2020
https://www.bmj.com/content/369/bmj.m1041/rr-1

Dr. Redfield… We have been dealing with an antibiotic resistant/tolerant super-bug. Post Treatment Lyme Disease Syndrome (PTLDS) is simply a fabricated medical condition disguising treatment failure. A chronic relapsing seronegative disease DOES NOT fit the vaccine model because you cannot prove vaccine efficacy in a disease where we don’t know who has or does not have the infection! So, deny the chronically infected by suppressing all evidence of antibiotic resistance, claim that the infection is easily treated because newer curative treatment for all stages of disease would give the public an excuse not to take the vaccine, reject all direct-detection methods that prove chronic infection and voila! move forward with patent royalties, vaccine development and pharmaceutical profits. The federal watchdog is no more. People suffering and dying and for what? Lyme for Profit.

The CDC has propagated this false Lyme disease narrative for decades and to this day refuses to recognize the disabling stage of the disease exposed in the documentaries Under our Skin and The Quiet Epidemic.

You may want to read the following Newsweek article published April 2024 by Lindsay Keys Co-Director of The Quiet Epidemic as it describes precisely what affect suppressing/concealing antibiotic resistance has had on the patient population…

Lyme Disease Is Quietly Debilitating Millions of Americans and Future Generations | Opinion
https://www.newsweek.com/lyme-disease-quietly-debilitating-millions-americans-future-generations-opinion-1885764

Excerpt: 

Lyme costs the U.S. an estimated $1 billion annually. Chronic Lyme patients are going bankrupt, suffering from job loss, and experiencing high rates of suicide. The history of Lyme has been plagued with controversy—a National Institutes of Health (NIH) official once referred to patients as “Lyme loonies.” Given the widespread suffering and economic burden, we were shocked to discover Lyme diagnostics and treatments have not advanced since the 1990s. Due to a lack of research, the mainstream medical community resorts to telling people it’s in their heads.

Carl Tuttle
Independent Researcher
Hudson, NH USA
Tenenbaum Cancer Protocol

I continue to marvel at the many silver linings of the disastrous COVID era. One such silver lining is the plethora of information not only about successful cancer treatments but the truth about the very nature of it. Since a recent paper shows that chemotherapy the current poison treatment of choice that oncologists get a direct cut from, has a 97.9% failure rate in the U.S. over five years, these treatments are just in time as the American Cancer Society Projects diagnoses to exceed 2 MILLION in 2025.

Due to the fact ‘the powers that be’ have proven to be unbelievably corrupt hooligans, people have begun to realize that they in fact have a brain they can use for themselves!  

This awakening has brought many to the conclusion they can research, learn, and experiment just as well as those in a fraudulent, indoctrinated medical machine for profit which spews out mostly corrupt people with a few letters after his or her name.  (There are always rare exceptions and thank God for them!)

The world has already been regaled with the success of the Joe Tippen’s Protocol, Dr. Marik’s success, Dr. Makis’ success, Mel Gibson’s testimony of 3 friends healed of stage four cancer, a major review paper showing high dose IV vitamin C (75-100g, 2-3X week for 6-8 cycles) as a promising anti-cancer agent, and entire websites dedicated to high level guidance based on research for the layman who is interested in cancer treatments.  (COVID mania also exposed the ‘good guy’ doctors who were and continue to be tenaciously persecuted for daring to think for themselves)

Now we have the astounding success of Guy Tenenbaum, a 71 year old with stage 4 prostate cancer who was given a death sentence by all the doctors he consulted with, and who realized he had to rescue himself.  He studied the Metabolic Theory of Cancer, the work of Dr. Otto Warburg and Dr. Wilhelm Brunings [06:41], and discovered the key, autophagy, related to the work of Dr. Yoshinori Ohsumi [06:54]. Many studies built on Ohsumi’s foundational work and applied it to cancer. Autophagy, the lysosomal clean-up of cellular debris, is controlled by the mTOR pathway and is turned on by fasting.  Fasting can also enhance chemotherapy and radiation effectiveness and dramatically lessen its toxicity.  Tenenbaum wrote “My Battle Against Cancer – Survivor Protocol,” “Beat Cancer to Cure From Cancer,” and co-authored “Can We Heal From Cancer? Guy and Fred Did it…..and Here’s How.”

It appears the medical machine refuses to apply previously done work to current diseases because there isn’t any money or power in it. 
You think NIAID will give grants for that?  Think again.

Guy Tenenbaum’s Cancer Protocol

  • Fast for 42 days, consuming nothing but water and occasional coffee or tea
  • Take 1,000mg of aged garlic (scientists believe it’s responsible for 30% of his recovery). Go here for research on how aged garlic:
    • reduced stomach cancer by 52% due to reducing IGF-1, activating autophagy, suppressing a master switch controlling inflammation & cancer stem cell survival, and enhancing Natural Killer Cells by up to 300%.
    • even 17 years after stopping it, subjects still had a 34% lower cancer mortality
    • has an anti-aging effect, slows heart disease progression, improves brain health, and beats EGCG and curcumin due to its bioavailability, clinical results, and track record.
    • causes blood levels peak within hours but clinical benefits usually appear:
      • 2-4 weeks – improved blood pressure and inflammation markers
      • 3 months – max cardiovascular benefits
      • 6-12 months – cancer prevention and longevity benefits

Tenenbaum continues to take aged garlic now with meals for better absorption. After his drastic self- experiment his PSA dropped from 58 to 0.1 and scans showed his bone metastases were healing.  Six years later, he remains cancer-free.  

It’s important to note that aged garlic is quite different from regular garlic or even odorless garlic due to the proprietary aging process which converts harsh compounds into gentle, beneficial ones, which have no odor and cause no irritation.  It would require 10-20 cloves of raw garlic a day to achieve 1,000mg.  I must add as a personal side note that I actually took 16 cloves of crushed garlic daily, broken down into 4 doses when I first got Lyme/MSIDS, based on the advice of a Master Herbalist.  I did it for 2 weeks and it nearly killed me.  First, I smelled like I came straight out of Shanghai (the kids banned me from the car), and second my stomach revolted toward the end.  It was just too harsh.  I will state it made me herx initially, so it gave some benefit.

Due to Tenenbaum’s success, there are now two clinical trials now in the works testing prolonged fasting and fasting-mimicking diets in prostate cancer patients.

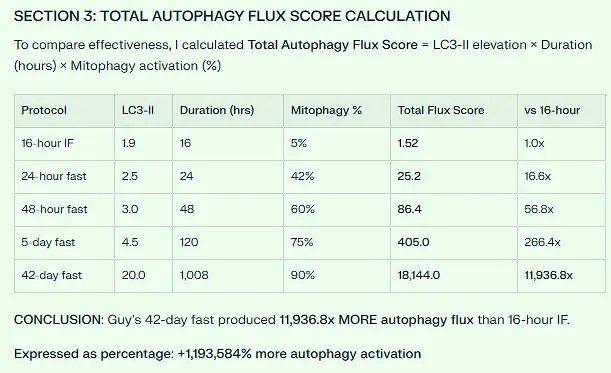
The following tables are helpful comparing autophagy effectiveness:

Source

This seminal work has shown there there appears to be an autophagy threshold for cancer suppression, growth factor starvation, insulin suppression, Warburg effect reversal, and sustained immune activation, which the 42 day fast meets but the 16 hour intermittent fast doesn’t.

This analysis demonstrates that dose-response matters dramatically in fasting-induced autophagy:

  • Mild fasting (16h): 20-30% tumor growth slowing ✓ (good)

  • Extended fasting (5-7d cycles): 10-25% remission rates ✓ (better)

  • Prolonged fasting (42d continuous): 100% remission rate ✓ (transformational)

Milder Ways to Induce Autophagy for the average Joe

Let’s say you don’t have cancer but you want to incorporate helpful aspects of Tennenbaum’s protocol in a more sustainable manner for prevention or other issues? 

Regarding clearing of spike proteins from those who got the COVID shots, as well as curing Dr. Marik’s Type II Diabetes:

“Autophagy can be upregulated by fasting and calorie restriction [2], especially if protein is reduced [3]. Autophagy in many instances does not require the complete cessation of food intake (protocols are available at https://COVID19criticalcare.com/treatment-protocols/, accessed on 15 April 2023). Sharply decreasing protein intake can upregulate autophagy pathways [4], and this can be accomplished while still eating, which makes this more approachable as a protocol. Regular fasting was also associated with better outcomes from acute COVID-19 [5].  Source

For Average Risk Individuals

Daily: 16:8 Time-Restricted Eating

  • Fast 16 hours (e.g., 8pm – 12pm)

  • Eat 8 hours (12pm – 8pm)

Quarterly: 4-5 Day Fasting-Mimicking Diet

  • Every 3 months (4x per year)

  • 1,100 cal day 1; 500 cal/day days 2-5

Expected Results:

  • ✅ Cancer risk reduction: 40-60%

  • ✅ Sustainability: Excellent (85-95%)

  • ✅ Evidence level: Strong (multiple human RCTs)

For High-Risk Individuals (Family History, Genetic Risk)

Daily: 18:6 Time-Restricted Eating

  • Fast 18 hours (6pm – 12pm)

  • Eat 6 hours (12pm – 6pm)

Monthly: 48-72 Hour Water Fast

  • Once per month

  • Water, tea, coffee only

Quarterly: 4-5 Day FMD

  • Every 2-3 months

Expected Results:

    • ✅ Cancer risk reduction: 50-70%

    • ✅ Sustainability: Good-Excellent (70-85%)

    • ✅ Evidence level: Very Strong

Optimal Combined Protocol (50-70% Prevention)

DAILY FOUNDATION:

  • ✅ 16:8 Time-Restricted Eating (minimum)

  • ✅ 18:6 TRE for high-risk individuals

  • ✅ Eating window: 12pm – 6pm or 10am – 6pm

  • ✅ Black coffee, tea, water allowed during fast

QUARTERLY INTENSIVE:

  • ✅ Fasting-Mimicking Diet 4 times per year

  • ✅ Day 1: 1,100 calories (plant-based)

  • ✅ Days 2-5: 500 calories/day

  • ✅ ProLon kit or DIY version

  • ✅ Schedule: Jan, April, July, October

OPTIONAL MONTHLY BOOST (High Risk):

  • ✅ 48-72 hour water fast once per month

  • ✅ Or extend one FMD to 7 days

SYNERGISTIC ADDITIONS:

  • ✅ Aged Garlic Extract 2.4g/day

  • ✅ Green tea 3+ cups/day (especially lung cancer prevention)

  • ✅ Curcumin 500mg BID with piperine

  • ✅ Whole food, plant-based diet during eating windows

Go here for source and all research studies.

Repurposed Drugs for Cancer

By Paul E. Marik, MD, FCCM, FCCP and Justus R. Hope, MD

https://imahealth.org/wp-content/uploads/2025/02/approach-to-repurposed-drugs-for-cancer.pdf

We can be extremely thankful that COVID produced some amazingly unexpected benefits in how cancer and many other disease processes is being treated.

I’ll bet the medical machine didn’t predict their tyranny would promote invention!

For more:

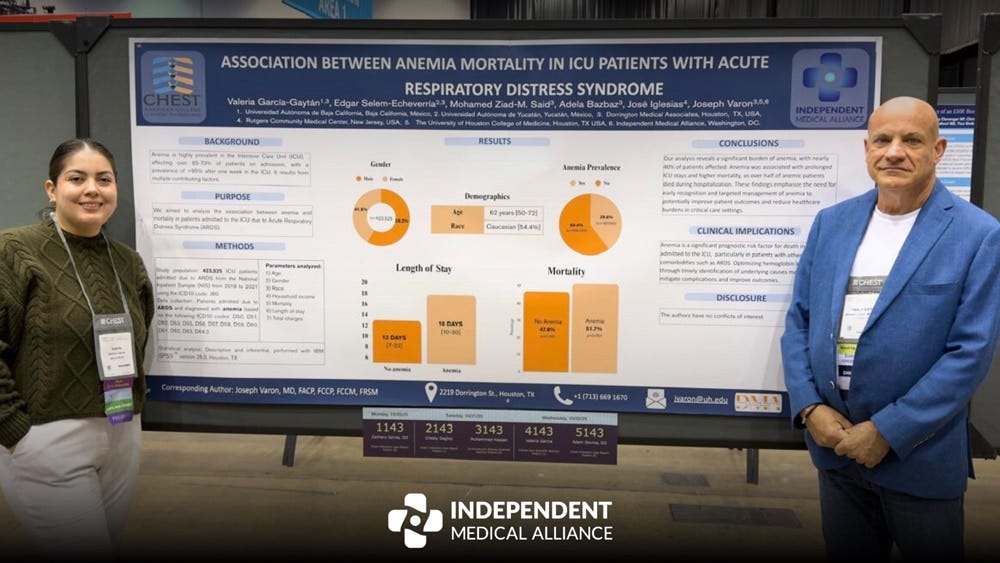
More Original Independent Research Presented at CHEST 2025 Than Presented by Many Major Institutions

https://imahealth.substack.com/p/ima-at-chest-2025-a-milestone-in?

IMA at CHEST 2025: A Milestone in Independent Medical Research

At CHEST 2025, IMA presented more original research than many major institutions. With over 1,600 peer-reviewed publications between Drs. Varon and Marik, independent science is gaining ground.

 
IMA CHEST 2025 hero

CHEST has long been a stronghold of institutional medicine: an annual gathering where pulmonary and critical care physicians from the world’s largest hospital systems and academic centers set the tone for clinical standards and scientific recognition.

At CHEST 2025, something different happened: an independent alliance is outpacing the establishment.

Led by IMA President Dr. Joseph Varon, our team contributed more original research than many of the most well-funded organizations in the country. That isn’t a boast; it’s a measurable step forward in reclaiming scientific spaces that were once closed to independent researchers.

“At CHEST 2025, I was struck by the fact that the IMA—our independent, grassroots organization—had more scientific presentations than some of the largest medical institutions in the country. Proof that dedication and vision often outperform size and bureaucracy.” — Dr. Joseph Varon

CHEST Chicago 2025

What is CHEST and Why Does It Matter

Founded in 1935, the CHEST Annual Meeting is organized by the American College of Chest Physicians. It is one of the most influential global conferences in pulmonary, critical care, and sleep medicine. Each year, thousands of clinicians, researchers, and policymakers gather to share emerging science, update protocols, and shape future guidelines.

Participation at CHEST is a strong signal of credibility. It’s the place where clinical science is discussed not just in theory, but in terms of its immediate application to patient care. For an independent medical group to be not only present but prominent shows that change in medicine is possible—and already underway.

Independent, Evidence-Driven, and Growing

For decades, CHEST has been the domain of large academic institutions and government-aligned research groups. This year, Dr. Varon, together with several of his researchers and students, presented a dozen original abstracts, including work on:

  • Pulmonary disease

  • Intensive care medicine

  • Optimization of patient care

That kind of presence doesn’t happen by accident. It’s the result of years of persistence, especially at a time when independent research was under immense pressure.

If you followed us during the COVID era, you’ll know that our physicians challenged flawed policies and raised concerns about mRNA vaccine harms. The response was swift: licenses were threatened, voices were censored, and reputations attacked. But the work continued.

The fact that we’re here today—publishing, presenting, and helping shape clinical conversations—is a testament to the strength of our mission. We survived a Goliath-like effort to silence us, and we’re still standing. Still researching. Still delivering solutions for patients.

Joe Varon with researchers at CHEST

Proof in the Medical Literature

Beyond CHEST, IMA researchers continue to publish in respected peer-reviewed journals. Recent examples include:

These studies are recent examples of a much broader trend: our science, once dismissed, is now being examined seriously. The same mainstream institutions that ignored our findings are beginning to revisit the data and ask questions we have been asking for years.

👉 Visit IMA’s Research Center

Our Research Leadership

IMA’s growing influence in medical research reflects leadership grounded in clinical experience, scientific rigor, and long-term commitment.

Dr. Joseph Varon, Co-Founder and Chief Medical Officer of IMA, has authored more than 1,000 peer-reviewed studies while continuing to practice medicine and mentor the next generation of researchers. He also leads the editorial vision of the Journal of Independent Medicine as its Editor-in-Chief, ensuring a continued focus on practical, patient-centered science.

Dr. Paul Marik, Co-Founder and Chief Scientific Officer, has published over 600 peer-reviewed papers and remains one of the most cited intensivists in the world. His recent induction into the Orthomolecular Medicine Hall of Fame recognized both the scope and influence of his scientific contributions.

Together, they’ve helped establish a model for medical research that puts patients first, values real-world outcomes, and refuses to compromise on scientific integrity.

Joe Varon showcasing a study at CHEST

A Journal for Uncensored Science

The Journal of Independent Medicine is preparing to release its fourth edition this November, marking the completion of its inaugural year.

The journal exists for one purpose: to give space to research that asks difficult but essential questions. Many of those questions cannot be raised in pharmaceutical-sponsored publications. Here, they can. It is a platform for physicians and scientists who still believe that medicine must serve patients first and tell the truth, even when it is inconvenient.

Expanding in 2026: Special Editions

Building on the success of its first year, IMA will introduce two new special editions in 2026:

  • “Treating Post-Vaccine Complications”

    • Submission Deadline: December 31, 2025

    • Publication Date: 2026

  • “Repurposed Drugs and Nutraceuticals in the Chronic Disease Epidemic”

    • Submission Deadline: February 28, 2026

    • Publication Date: 2026

These editions will expand opportunities for independent researchers and clinicians to publish meaningful work that drives progress rather than compliance.

👉 Submit your research or learn more here

Looking Ahead

CHEST 2025 was not about arrival or recognition. It was about progress earned through steady, verifiable work.

Through peer-reviewed research, transparent publishing, and the leadership of dedicated physicians, IMA is proving that independent medicine can thrive within the highest levels of scientific discourse.

Our work has always stood on its own merit. What has changed is that the world is finally ready to recognize it. And this is only the beginning.

For more coverage, check out where our globetrotting team of experts has been lately below:

________________

**Comment**

This is wonderful news and another wonderful silver lining to COVID mania.

Independent research has been the only thing moving the Lyme/MSIDS needle, and because it’s such a polarized disease, research is political, not scientific and is purposely designed for a predetermined outcome.

The world is beginning to see what Lymeland has known for over 40 years.

Study Links Surge in Children’s Memory Problems to Radiation Exposure

https://childrenshealthdefense.org/defender/kids-memory-problems-surge-wireless-radiation-exposure-study/

Study Links Surge in Children’s Memory Problems to Wireless Radiation Exposure

Children and teens in Sweden and Norway are experiencing an “alarming” rise in memory problems, according to the authors of a new peer-reviewed study that linked the issue to increased exposure to wireless radiation. “Radiation exposure must be reduced, and people must be informed about the associated health risks,” one of the study’s authors said.

boy and cell tower

Children and teens in Sweden and Norway are experiencing an “alarming” rise in memory problems, which the authors of a new peer-reviewed study attributed to increased exposure to wireless radiation.

“The steep increase in memory issues cannot be explained by changes in diagnostic criteria or reporting to the registries alone,” Lennart Hardell, M.D., Ph.D., one of the study’s authors, said in a press release. He added:

“We urge our findings on increasing numbers of children having impaired memory to be taken seriously by public health authorities and consider children’s increasing exposure to wireless radiation as a possible cause.

“Thus, we ask for measures aimed at decreasing exposure to RF radiation [radiofrequency radiation] to protect the brain and general health of children.”

The study was published this month in the Archives of Clinical and Biomedical Research.

Hardell, an oncologist and epidemiologist with the Environment and Cancer Research Foundation, has authored more than 350 papers, nearly 60 of which address RF radiation. He is also one of the first researchers to publish reports on the toxicity of Agent Orange.

Hardell and lead study author Mona Nilsson, co-founder and director of the Swedish Radiation Protection Foundation, examined national health data in Sweden and Norway and found that the number of medical consultations for memory disturbances in Norwegian children ages 5-19 increased roughly 8.5-fold from 2006 to 2024.

In Sweden, the number of children ages 5-19 diagnosed with mild cognitive impairment — a diagnosis that includes memory problems — increased nearly 60-fold from 2010 to 2024.

“The findings must be taken seriously and evaluated,” Hardell told The Defender. “Action must be taken to reduce children’s overall exposure — especially in schools.”

Nilsson agreed. “These alarming trends must be reversed — radiation exposure must be reduced, and people must be informed about the associated health risks,” she said.

Authors link memory problems to wireless radiation

The authors argued in their report that wireless radiation is a leading cause of memory decline in children.

They cited numerous epidemiological and experimental studies showing that very low levels of RF radiation can negatively affect the brain — particularly the hippocampus, which plays a central role in memory and learning.

“There is abundant evidence [dating back] several decades, both on animals and humans, that RF radiation impairs memory,” Nilsson said. “The trends we are observing coincide closely in time with the sharply increasing exposure of children and adolescents to RF radiation.”

Wireless exposure has escalated in the last decade due to the increasing use of cellphones, wireless headsets, Wi-Fi and 5G, Hardell said.

“Other contributing factors can, of course, not be excluded,” he said. “They must, however, be defined and not based on hypothetical discussion.”

New investigation targets ‘biased’ European report on RF radiation

The new study coincides with the European Ombudsman investigation into how the European Commission handled a key report that found no “moderate or strong” evidence linking adverse health effects to chronic or acute RF radiation exposure from existing wireless technologies.

The European Ombudsman, who “investigates complaints about maladministration by EU [European Union] institutions and bodies,” will question the European Commission on how it chose the experts to write the report, said Sophie Pelletier, president of PRIARTEM/Electrosensibles de France, in an Oct. 22 press release.

The report, called the SCHEER Opinion, was adopted in April 2023 by the European Commission’s Scientific Committee on Health, Environmental and Emerging Risks (SCHEER).

The SCHEER Opinion was “clearly biased,” according to an October 2023 critique published by the Council for Safe Telecommunications in Denmark and the Swedish Radiation Protection Foundation.

The investigation stems from a complaint filed by several European nonprofits, including the Swedish Radiation Protection Foundation, alleging that the authors of the SCHEER Opinion had conflicts of interest due to industry ties or industry-funded research.

The nonprofits also claimed that the European Commission excluded experts critical of wireless radiation’s possible health effects from the report’s working group and that the report authors ignored peer-reviewed studies showing harmful effects from exposure below current limits.

In the U.S., the Federal Communications Commission (FCC) has not updated its RF radiation exposure limits since 1996 and bases them largely on a few small sample studies conducted in the 1970s and 1980s.

The FCC has not yet complied with a 2021 court-ordered mandate to explain how it determined that its current guidelines adequately protect humans and the environment from the harmful effects of RF radiation exposure.

Related articles in The Defender

This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.

________________

**Comment**

Houston, we have a real problem…..

Please also read, “Wired for Harm: The Biological and Spiritual Costs of Wireless Radiation.”

For more:

Bacterial ‘Fingerprints’ Found on COVID ‘Vaccine’ DNA Contamination

https://slaynews.com/news/bacterial-fingerprints-found-covid-vaccine-dna-contamination/

Bacterial ‘Fingerprints’ Found on Covid ‘Vaccine’ DNA Contamination

A groundbreaking new analysis has uncovered evidence that Pfizer’s Covid mRNA shots may have contained bacterial DNA fragments with dangerous immune-activating signatures.

The discovery is raising urgent questions about how regulators ever allowed the injections to reach the public.

The findings were revealed in a preprint published by molecular biologist Kevin McKernan.

McKernan used advanced Oxford Nanopore sequencing technology to analyze a Pfizer vaccine lot (FL8095).

His results revealed:

  • Bacterial-style DNA methylation marks (m6A), a fingerprint of contamination from E. coli–derived DNA.
  • Evidence of incomplete linearization, meaning the DNA used to manufacture the shots may not have been fully processed, leaving behind problematic fragments.
  • Signals that the contamination could, in theory, trigger powerful immune responses, potentially leading to harmful side effects.

These findings raise serious questions about the integrity of the health regulatory process during the declared COVID-19 pandemic.  (See link for article)

_______________

**Comment**

Science show such fragments can set off inflammation and cytokine storms.

So far, the clot shot contains: