Author Archive

Molecular Detection of Lyme, Babesia, and Anaplasma in Canadian Ixodes Ticks

https://www.jelsciences.com/abstracts/1838

Molecular Detection of Borrelia burgdorferi sensu lato, Borrelia miyamotoi, Babesia odocoilei, Babesia microti and Anaplasma phagocytophilum in Ixodes Ticks Collected across Canada

John D Scott* and Catherine M Scott

Volume5-Issue10
Dates: Received: 2024-09-28 | Accepted: 2024-10-18 | Published: 2024-10-22
Pages: 1321-1337

Abstract

Tick-borne zoonotic diseases are a profound challenge to healthcare practitioners, and an overwhelming scourge to patients worldwide. On the whole, patients have great difficulty getting diagnosed and treated, and often become chronically ill. In this study, we tested 224 ticks consisting of Ixodes angustus, Ixodes pacificus, and Ixodes scapularis. Using real-time PCR and nested PCR, we obtained the following positives:

  • Borrelia burgdorferi sensu lato (n = 74)
  • Borrelia miyamotoi (n = 4)
  • Babesia odocoilei (n = 82)
  • Babesia microti (n = 1)
  • Anaplasma phagocytophilum (n = 8)

Markedly, B. odocoilei and B. burgdorferi were detected in I. scapularis ticks nationwide. As well, the Canada-wide prevalence of B. burgdorferi s.l. and B. odocoilei in I. scapularis adults was 40% and 36%, respectively. The statistical ratio of B. odocoilei to B. microti in I. scapularis adults was 60 to 1. Babesia odocoilei is, unquestionably, the predominant Babesia sp. across Canada. We provide the first report of B. odocoilei in an I. angustus tick. In addition, we unfurl the first report of B. odocoilei in I. scapularis in British Columbia, Alberta, Saskatchewan, Manitoba, Prince Edward Island, and Newfoundland and Labrador.

From a professional healthcare standpoint, I. scapularis ticks are just as likely to be infected with Babesia odocoilei as Borrelia burgdorferi s.l. Since people spend considerable time in outdoor areas, clinicians must be familiar with current acumen in tick-borne zoonotic diseases.

USDA Now Licensing DNA ‘Vaccines’ in Our Food Supply

https://lionessofjudah.substack.com/p/tainted-grub-usda-now-licensing-dna?

TAINTED GRUB: USDA Now Licensing DNA Vaccines in America’s FOOD SUPPLY

Ohio attorney Tom Renz has dropped another bombshell exposing the United States Department of Agriculture (USDA) for licensing the use of deadly DNA vaccines in America’s food supply.

Lioness of Judah Ministry


By Ethan Huff October 30, 2024

Ohio attorney Tom Renz has dropped another bombshell exposing the United States Department of Agriculture (USDA) for licensing the use of deadly DNA vaccines in America’s food supply.

While the USDA had previously given the green light for salmon to be vaccinated with the latest mRNA (modRNA) chemicals, this newest scheme is even worse in that it allows even more questionable pharmaceutical chemicals to be administered to animals that people consume as food.

“… the deadly mRNA poison vaccines weren’t enough for the Biden Harris administration,” Renz notes. “They and their big pharma partners are now licensing DNA vaccines for use in our foods.”

(See link for article)

_________________

**Comment**

We were warned about this previously:

ACTION: Flood Inboxes of Task Force on Health Care Monopolies and Collusion

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/32992416

Calling on all Lyme patients, caregivers, and clinicians across the globe!

Carl Tuttle
Hudson, NH, United States
Oct 26, 2024

The following timeline for the deliberate mishandling of Lyme disease was forwarded to Attorney Katrina Rouse of the United States Antitrust Division, head of a Task Force on Health Care Monopolies and Collusion. Please forward your respectful request for an investigation into the collusion to deny chronic Lyme disease which has stifled research for better antimicrobials in treating this antibiotic resistant/tolerant superbug. Your email should describe how this denial has affected your ability to obtain treatment and affordable healthcare. What has been deceitfully established here in the US is being emulated across the globe.

Note to clinicians: Your experience on the front lines in treating chronic Lyme and witnessing the devastation first hand should be described in detail.

Let’s flood the inboxes of these two attorneys!

Contact info for Attorney Katrina Rouse and Assistant Attorney General Jonathan Kanter

Katrina Rouse: katrina.rouse@usdoj.gov

Jonathan Kanter: jonathan.kanter@usdoj.gov

Letter to Grace E. Marx, MD Medical Epidemiologist, Centers for Disease Control and Prevention:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “grace.marx@cuanschutz.edu” <grace.marx@cuanschutz.edu>, “gmarx@cdc.gov” <gmarx@cdc.gov>
Cc: “katrina.rouse@usdoj.gov” <katrina.rouse@usdoj.gov>, “jonathan.kanter@usdoj.gov” <jonathan.kanter@usdoj.gov>
Date: 10/25/2024 9:11 AM EDT
Subject: Tick-Borne Diseases and Associated Illnesses, Community Engagement Series: Mental Health and Neurological Effects

Tick-Borne Diseases and Associated Illnesses, Community Engagement Series: Mental Health and Neurological Effects
https://www.hhs.gov/oidp/initiatives/tick-borne-diseases-associated-illnesses-national-community-engagement-initiative/index.html3:00 pm – 3:20 pm   A Clinician Toolkit: Improving Care for Patients with Prolonged Symptoms and Concerns about Lyme Disease By Grace E. Marx, MD Medical Epidemiologist, Centers for Disease Control and Prevention

Dear Dr. Marx,

I listened to your presentation yesterday with great interest and I must congratulate you for your outstanding performance in suppressing all evidence of persistent infection; chronic Lyme disease.

We have studies proving persistent infection after antibiotic treatment for mice, dogs, ponies, monkeys, cows, iris biopsy, and ligamentous tissue but if you perform a simple Google search for the following statement, “There is no convincing scientific evidence that chronic Lyme exists” you will find the top search results are connected to “elements of academic medicine” involved in the denial of the late stage Lyme epidemic.

In 1991 the Lyme disease organism, Borrelia burgdorferi, was grown from the cerebrospinal fluid of Lyme patient Vicki Logan at the Centers for Disease Control in Fort Collins, Colorado despite prior treatment with intravenous antibiotics. The patient died when the insurer refused additional IV antibiotics. Here is a copy of Logan’s CDC positive culture report for your review.

(Vicky Logan’s Chronic Lyme Autopsy results Page #1, 2, 3, 4, 5, 6, 7)

There are 700 peer-reviewed publications referencing persistent infection and in a 2018 study all patients were culture positive even after multiple years on antibiotics so there was no relief from current antimicrobials. Some of these patients had taken as many as eleven different types of antibiotics.

Thirty-four years ago Dr. Allen Steere identified chronic Lyme disease which should have set off a red flag prompting an immediate search for better antimicrobials but then did a 180° as he became principal investigator (PI) of the Phase 3 clinical trial for the first Lyme disease vaccine. So all the eggs were put into the vaccine basket while a campaign was orchestrated to discredit the sick and disabled patient population along with the courageous clinicians attempting to help these patients. Apparently, a chronic relapsing seronegative disease did not fit the business model of patent royalties, vaccine development and pharmaceutical profits.

Here is Dr. Steere’s 1990 publication summary for your review:

The New England Journal of Medicine 

Published November 22, 1990

Chronic neurologic manifestations of Lyme disease
https://www.nejm.org/doi/full/10.1056/NEJM199011223232102

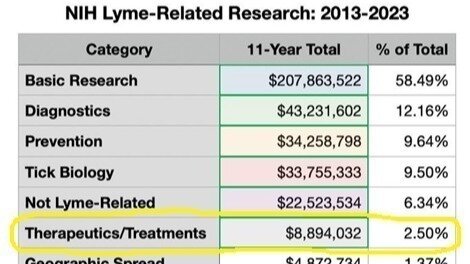
The chart below summarizes Lyme research funded by the NIH and only 2.5% has been allocated for treatment:

https://www.dropbox.com/scl/fi/4fpjivy7stiztfs5ib6sz/NIH-Lyme-Research.png?rlkey=71yrfa6r7e6osq2he7qwsjj75&dl=0

For the record there are many infections requiring long-term antibiotics so why Klempner stopped his NIH funded antibiotic treatment trials for Lyme after 90 days makes absolutely no sense whatsoever:

From the following publication:

Benefit of intravenous antibiotic therapy in patients referred for treatment of neurologic Lyme disease
https://www.dovepress.com/benefit-of-intravenous-antibiotic-therapy-in-patients-referred-for-tre-peer-reviewed-fulltext-article-IJGM

Infections requiring long-term antibiotics:

https://www.dropbox.com/scl/fi/pserdbenw4n1vovv14z2a/Infections-requiring-long-term-antibiotics.jpg?rlkey=281zg7alxl4gqm2e2jipy9szj&dl=0

Lyme misdiagnosed/undiagnosed for months, years or decades is far more incapacitating than “acute” Lyme and 2-4 weeks of antibiotics does not scratch the surface of this well-established/immune suppressive infection. These are the patients who need help the most but have been excluded in research for decades. There are countless stories of patients seroconverting after the initial few doses of Doxycycline and now that a toxin has been identified that puts Lyme disease in an altogether different category of infection:

Toxins 
Published: 21 May 2024

Borrelia burgdorferi 0755, a Novel Cytotoxin with Unknown Function in Lyme Disease
https://www.mdpi.com/2072-6651/16/6/233

So it would appear that one way to get a medical association (AMA) to go along with the suppression of evidence is to throw them a boatload of money… five million taxpayer dollars to be exact for a so-called IDSA biased “Clinician Toolkit”  (CDC grant number  NU50CK000597)

This controlling of the narrative has caused unimaginable pain and suffering all across America as insurance companies refuse to pay for long-term treatment, personal bankruptcies from out-of-pocket expenses to treat chronic infection, suicides from despair all while Valneva Received FDA Fast Track Designation for its Lyme Disease Vaccine.

Chronic Lyme must be recognized and finally addressed with 100% attention to effective antimicrobials for all stages of disease.

Question:

Is collusion to control the narrative through suppression of the truth, facts and scientific references a criminal offense?

Carl Tuttle
Hudson, NH

Cc: Assistant Attorney General Jonathan Kanter, Attorney Katrina Rouse
Attorneys for the United States Antitrust Division

Assistant Attorney General Jonathan Kanter Announces Task Force on Health Care Monopolies and Collusion
https://www.justice.gov/opa/pr/assistant-attorney-general-jonathan-kanter-announces-task-force-health-care-monopolies-and

“Every year, Americans spend trillions of dollars on health care, money that is increasingly being gobbled up by a small number of payers, providers and dominant intermediaries that have consolidated their way to power in communities across the country,” said Assistant Attorney General Jonathan Kanter of the Justice Department’s Antitrust Division. “Led by Katrina Rouse, the task force will identify and root out monopolies and collusive practices that increase costs, decrease quality and create single points of failure in the health care industry.”


“The Quiet Epidemic” Showing at the U.S. Capital Nov. 20, 2024

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/

The Quiet Epidemic Film Presentation at the U.S. Capitol November 20th

Carl Tuttle
Hudson, NH, United States
Oct 29, 2024

The Quiet Epidemic Film Presentation at the U.S. Capitol

Please join us on Capitol Hill for a special presentation of the award-winning documentary The Quiet Epidemic

Hosted by Senator Richard Blumenthal, with a special appearance by Chris Meloni, Actor & Global Lyme Alliance Celebrity Ambassador

Since the earliest days of production, the team and supporters behind The Quiet Epidemic hoped the film might one day screen on Capitol Hill, and that moment has arrived.

Please join us for a free and open to the public presentation of The Quiet Epidemic on Wednesday, November 20th, from 5:30 PM to 9:00 PM, at the U.S. Capitol. The film will be preceded by a reception and followed by a discussion and Q&A with the film’s subjects, experts and actor Chris Meloni.

While the event is free to attend, RSVPs via Eventbrite are required for entry. You’ll find a PDF invitation attached to this email which includes the RSVP link—please circulate this widely, as our team is prohibited from promoting the event on social media. Details regarding the exact venue location within the Capitol will be sent to all registrants via Eventbrite approximately one week prior to November 20th.

The Quiet Epidemic team would like to thank our generous sponsors who have made our Capitol Hill events possible: LymeLight Foundation, Global Lyme Alliance, Sarena Snider, Project Lyme, NatCapLyme and lymeLNK. Among our sponsors are The Quiet Epidemic Executive Producers Phyllis & Scott Bedford—founders of LymeLight Foundation—and Sarena Sarena, each of whom generously supported the creation of the film itself, the film’s festival tour and release, and our team since the very beginning.

Please share the Eventbrite link and the attached PDF with anyone in your network who may wish to attend this event—especally those in the Washington D.C. area. We also encourage you to invite your representatives and include a brief statement about the impact Lyme has had on your life, and the prevalence in their state.

PDF invitation

https://www.dropbox.com/scl/fi/rp1qqnln1w6ztk6yimecq/11.20.24_The-Quiet-Epidemic-on-Capitol-Hill.pdf?rlkey=ecmsm63kwn8w27pymi1x8dlqk&dl=0

This is a culminating moment for The Quiet Epidemic film and impact campaign, nine years in the making. Thank you for being a part of this journey and for making it possible in so many ways! We hope to see you in D.C.

With gratitude,
The Quiet Epidemic Team

Watch The Quiet Epidemic trailer:
https://www.youtube.com/watch?v=I4C71N290co

Over 30 Schoolchildren Died Suddenly This Week & Damning Testimony Against ALL Vaccines

Canada has just killed an Ontario man in his late 40’s injured by the COVID shot under it’s “assisted suicide” laws funded by tax-payers. The Canadian government is euthanizing citizens for depression, hearing loss, autism, poverty and homelessness, but is also pushing to expand laws to include children and infants.

The group that worked to legalize the program now admits it’s been “abused” and that doctors have been coercing people into dying.

https://thepeoplesvoice.tv/over-30-u-s-schoolchildren-died-suddenly-this-week-as-deaths-surge-among-covid-vaxxed/

Over 30 U.S. Schoolchildren Died Suddenly This Week As Deaths Surge Among COVID-Vaxxed

Fact checked by The People’s Voice Community

At least thirty US school children whose parents were told the COVID mRNA shots were “safe and effective” died suddenly and unexpectedly in the US this week as the death toll continues surging among the vaccinated and boosted.

Many of the children died of medical emergencies including cardiac arrest and strokes as doctors warn they are now regularly witnessing “once-in-a-lifetime” disorders in children.

“This is the new normal… turbo cancers, died suddenly. My friend lost three friends in one week! Turbo cancers like this were virtually non-existent before the COVID shots,” explained MIT scientist and vaccine researcher, Steve Kirsch.

How long before we as a society can have an open and honest discussion about what is happening to the Covid-vaccinated before our eyes?  (See link for article)

A large scale study from Korea revealed that the Pfizer and Moderna COVID shots have the greatest cardiac risk.

For more:  https://madisonarealymesupportgroup.com/2020/12/21/warning-3150-injuries-in-1st-week-of-covid-vaccines-among-american-healthcare-workers-pregnant-women-included/ Latest VAERS data and mounting list of adverse reactions and death.

______________

https://x.com/newstart_2024/status/1849826194914459706  Video Here (Approx. 5 Min)

Damning Testimony Against ALL Vaccines

Dr. Brian Hooker’s damning testimony against all vaccines “My name is Dr. Brian Hooker, and I am a vaccine safety scientist serving as a chief scientific officer of Children’s Health Defense. I’m also the father of a severely vaccine injured adult son.

Next slide, please. This slide shows the expansion of the infant child vaccination schedule since 1962, as recommended by the CDC. Multivalent vaccines are counted based on the number of disease antigens. For example, the MMR vaccine counts as three doses. In 1962, children received five vaccine doses, and in 1986, the schedule expanded to 25 doses of five different vaccine formulations.

Shortly after the passage of the 1986 National Childhood Vaccine Injury Act, the law was amended to essentially erect a liability shield protecting vaccine and the schedule expanded dramatically. By 2023, 73 doses of 16 different vaccine formulations were given to children up to age 18.

The FDA approved these formulations individually only with minimal and inadequate safety testing, and the CDC has never tested the cumulative effect of the vaccine schedule on childhood health outcomes. However, independent researchers have assessed the outcomes of vaccinated versus unvaccinated children. Next slide, please.

This slide shows the results of a paper that Neil Miller, a medical journalist, and I published in the journal Sage Open Medicine in 2020. Here, only vaccines given during the first year of life were considered.  Any child who received one vaccine or more during the first year of life was considered vaccinated, and any child who received no vaccines during the first year of life was considered unvaccinated.

Deidentified records were taken directly from three medical practices in different locations within the US. The odds ratios or likelihood of a diagnosis is shown on the graphic. This demonstrates that vaccinated children were at least twice as likely to be diagnosed with developmental delays, ear infections, and gastrointestinal disorders.

The likelihood of an asthma diagnosis among the vaccinated group was 4.5 times higher than the unvaccinated group. Next slide, please. Affirming and extending these results is a study completed by Joy Garner of the control group that was published in the International Journal of Vaccine Theory Practice and Research in 2022.

Here, a control group of over 1,800 unvaccinated children recruited from 46 different states in the US were compared to the national average rates of the listed disorders. The national averages represent a population of children where 99.7% of the participants are vaccinated. Incidence of each disorder is shown as a percentage of each group of children on the graphic.

For each of the autoimmune, neurodevelopmental, and other disorders considered, the unvaccinated group fares much better with incidence rates between four and 20 times lower than their vaccinated counterparts. Next slide, please.

This is a comparison of the myocarditis diagnosis rates following the COVID-19 mRNA vaccines given during the pandemic. The first graphic on this slide is from a paper published by Mazzari et al. in the Journal Plus Medicine in 2022. It shows the incidence of myocarditis and pericarditis diagnoses within seven days of receiving either the first or second dose of the Moderna vaccine versus the unvaccinated control group, four males between 12 and 39 years of age.

The second graphic on the slide is from a paper published by Mvorak et al in the New England Journal of Medicine in 2021. It shows the incidence of myocarditis within 30 days of receiving the second Pfizer vaccine in the general population, as well as for 16 to 19 year old boys compared to unvaccinated controls.

Myocarditis is a serious disorder and 76% of all cases following COVID vaccination, as reported by VAERS, requires emergency care and or hospitalization. CDC significantly downplays myocarditis as a side effect of the vaccine. Vaccine injury is neither minor nor rare.

The 1986 National Childhood Vaccine Injury Act requires that the Department of Health and Human Services report to Congress on the state of vaccine safety in the U.S. every two years. It’s been almost 40 years since the 1986 act was passed, and HHS has never submitted a vaccine safety report to Congress.

Federal authorities are derelict in their duty to protect the people of the United States from debilitating and often life-changing vaccine adverse events. Thank you.”

______________

http:// (Approx. 9 Min)

Oct. 27, 2024

BOOM!

Further damning vaccines is the fact that infant deaths due to vaccines are never listed on death certificates, but are listed as SIDS (sudden infant death syndrome) due to the lack of ICD (International Classification of Diseases) codes, sanctioned by the CDC and the WHO.  Coroners can’t choose to list a death as due to a vaccine even if they wanted to because no code exists for it.

Sudden Infant Death Syndrome or SIDS remains the leading cause of death for infants in the U.S.
This remains the perfect cover-up for vaccine deaths.

The youngest death from Pfizer COVID shot is a 5-month-old who died within 24 to 48 hours after injection. The youngest death after Moderna COVID shot is a one-year-old.  Source

Same story in both cases: found dead in the crib a couple of days after their injection. 

But in both cases it’s labeled SIDS.

Lastly, Dr. Andrew Wakefield states that a statement from the Federal Register says:

“The science of vaccine safety, whatever its merits, if there is doubt about a vaccine, that science can not be allowed to exist.”

That’s not science.

For more: