Covid-19 Patients No Longer Need Tests to End Isolation
Under new guidelines from the C.D.C., recovering coronavirus patients should be free to resume normal activity after 10 days, if they have no fever or other symptoms.
Coronavirus testing delays of up to two weeks persist in parts of the country.Credit…Max Whittaker for The New York Times
Most Americans recovering from Covid-19 can come out of isolation without further testing to show they no longer carry the coronavirus, federal health officials said on Wednesday.
Instead, patients may be judged to have recovered if 10 days have passed since they first felt ill; they no longer have any symptoms, such as shortness of breath or diarrhea; and they have not had a fever for 24 hours without taking fever-reducing medicine.
The new recommendations are not rules but guidelines intended for patients, doctors and health policymakers. The revisions should help relieve the burden on the country’s testing system, the Centers for Disease Control and Prevention said. (See link for article)
____________________
**Comment**
Ha ha, ha…..yeah right.…Lyme/MSIDS patients know all about “guidelines” that rule the land like the Iron Curtain.
Tests for SARS-CoV-2 in South Korea Can’t Distinguish Virus from Viral Fragments
by TVR Staff
Published July 26, 2020
A team of South Korean infectious disease researchers has concluded there is no evidence that people can be reinfected with the SARS-CoV-2 virus. The researchers, led by Oh Myoung-don, MD, head of Seoul National University Hospital’s division of infectious diseases, believe that reports of patients who have recovered from COVID-19 and subsequently tested positive again for SARS-CoV-2 were not due to reinfection or reactivation but, rather, to testing errors.123456
According to Dr. Oh, the PCR (polymerase chain reaction) tests used to determine the presence of the SARS-CoV-2 virus and help diagnose cases of COVID-19 cannot distinguish between the virus and harmless fragments of the virus.123456 Vaccine developer Seol Dai-wu of Chung-Ang University in Seoul, South Korea agrees.
“The RT-PCR machine itself cannot distinguish an infectious viral particle versus a non-infectious virus particle, as the test simply detects any viral component,” Seol said.2
As immunologist Beda Stadler, PhD, former director of the University Institute of Immunology at the Insel Hospital in Bern, Switzerland notes, people who recovered from COVID-19 can still test positive for SARS-CoV-2 because…
… the coronavirus test measures only a very tiny tiny piece of the genome of the virus, and if your immune cells have killed the virus, then you have debris, you have rotten pieces of the nucleic acids in your blood and everywhere, and the assay can pick up these rotten pieces and then it look like as if you’re infected. You’re not. You have won the fight, you’re immune. So [the test] cannot discriminate.7
In a recent case involving 260 people in South Korea who had been diagnosed with COVID-19 and recovered, tests detected fragments of the SARS-CoV-2 virus weeks after their recoveries. “The tests detected the ribonucleic acid of the dead virus,” Dr. Oh said.123456 He added:
PCR testing that amplifies genetics of the virus is used in Korea to test COVID-19, and relapse cases are due to technical limits of the PCR testing. The respiratory epithelial cell has a half-life of up to three months, and RNA virus in the cell can be detected with PCR testing one to two months after the elimination of the cell.1356
The findings by Dr. Oh and his research team have been confirmed by the Korean Centers for Disease Control and Prevention (KCDC). On May 18, 2020, the KCDC announced that it had studied 285 cases of patients who had recovered from SARS-CoV-2 infection and later tested positive again for the virus. Despite the positive tests, the agency determined that the patients were not contagious because they did not actually have the virus—that the PCR tests has “falsely identified dead viral matter as active COVID-19 infection.”89
The new research from South Korea has led to new protocols in that country for handling cases involving people who recovered from COVID-19, completed a period of isolation and then retested positive for the SARS-CoV-2 virus. Now, in South Korea, there is no longer a requirement for people, who have recovered from COVID-19 and gone through isolation, to test negative for SARS-CoV-2 before going back to work or school.9
Rasnick’s advice for people who want to be tested for COVID-19.
“DON’T DO IT, I SAY, WHEN PEOPLE ASK ME,” HE REPLIES. “NO HEALTHY PERSON SHOULD BE TESTED. IT MEANS NOTHING BUT IT CAN DESTROY YOUR LIFE, MAKE YOU ABSOLUTELY MISERABLE.”
When it was introduced in the mid-1980s, naltrexone was used for blocking opioid receptors. These receptors are meant to be activated by hormones produced by the body called endorphins and enkephalins. However, opioid drugs also stimulate these receptors.
Large doses of naltrexone were originally used for treating drug addiction by blocking the body’s opioid receptors, and therefore the effects of opioid drugs, completely. In doing so, however, it completely blocked the body’s endorphins and enkephalins as well. This was ultimately harmful to health since these hormones play critical roles in myriad parts of the body, such as the immune system.
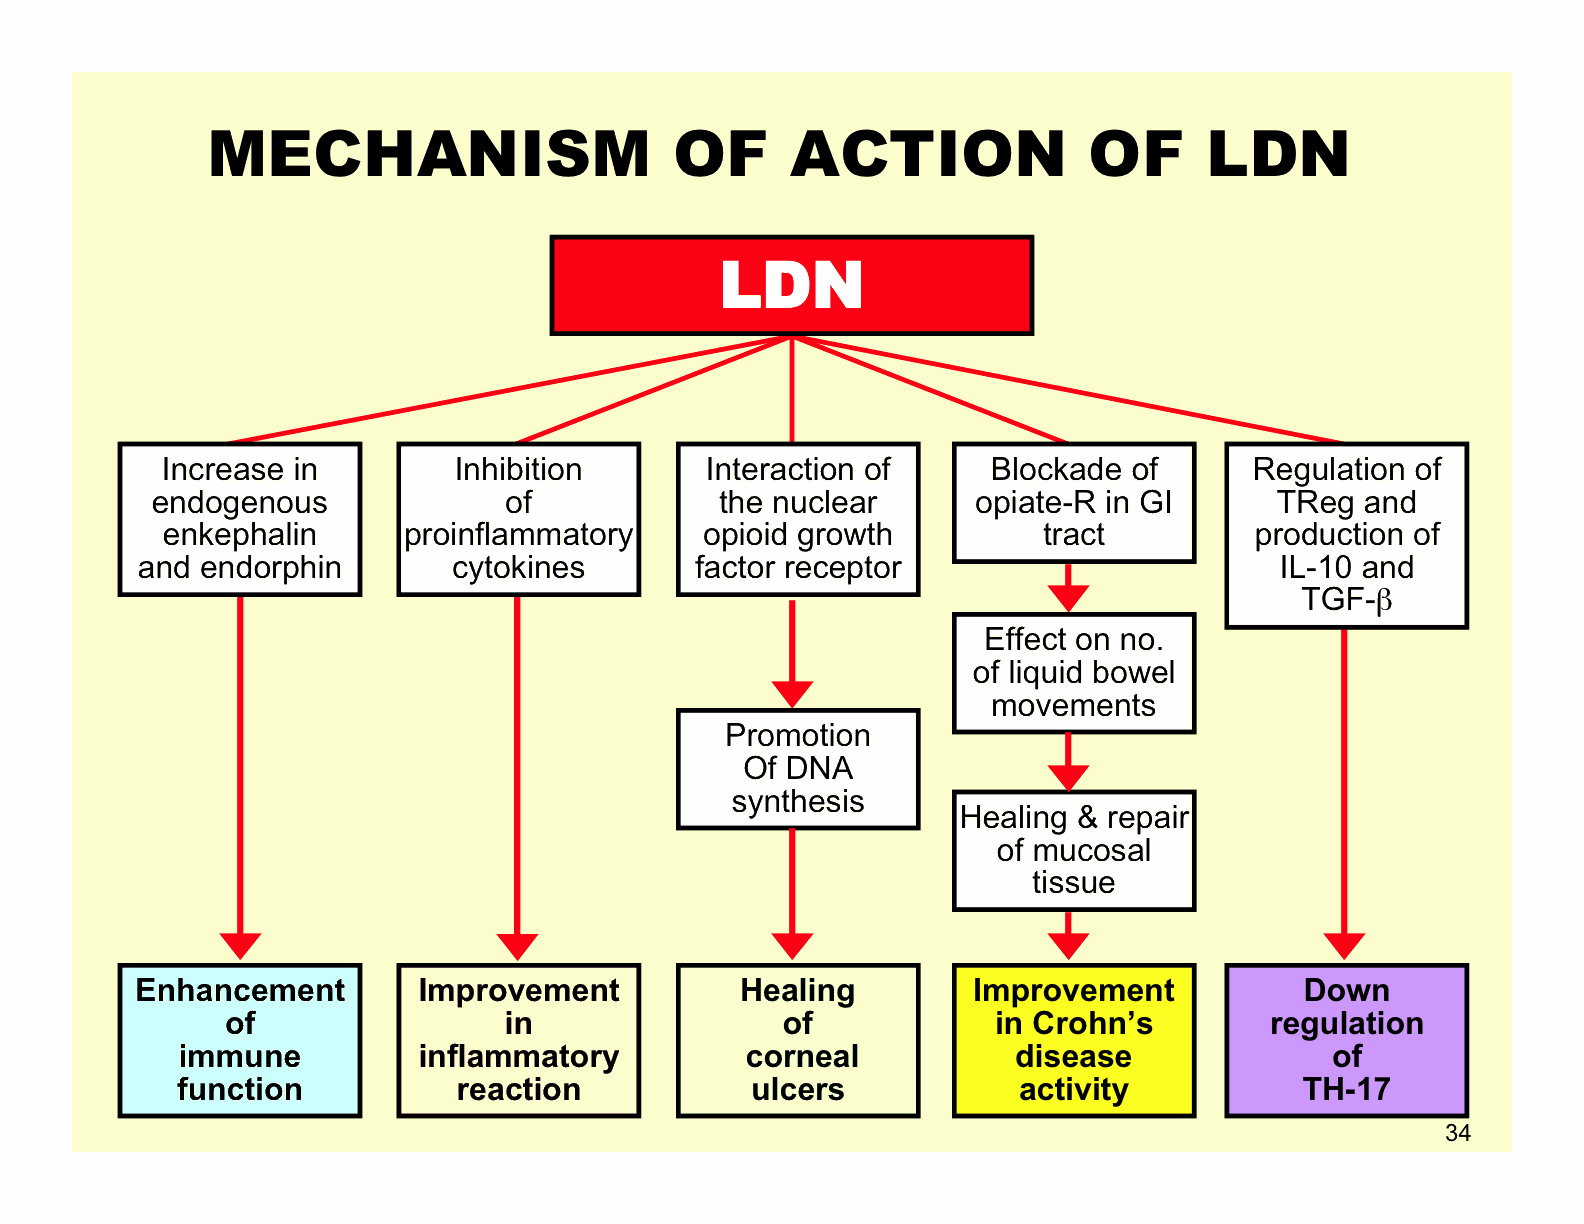
In contrast, low doses of naltrexone act by temporarily blocking opioid receptors.This causes the body to increase its production of endorphins and enkephalins. In turn, these hormones work to relieve pain, reduce inflammation, and contribute to well-being while avoiding the adverse health effects associated with larger naltrexone doses.
Studies have shown that low-dose naltrexone (LDN) offers multiple health benefits. It has been used in a wide range of treatments for a variety of conditions, including:
LDN, Autoimmune Disorders, Cancer, Treating Pain, and More
The late Dr. Bernard Bihari discovered and developed the therapeutic use of low-dose naltrexone (LDN) in the mid-1980s while practicing internal medicine in New York City. He was treating drug addicts with a new drug, Naltrexone, which blocked the heroin “high.” Unfortunately, 50 milligrams daily had unpleasant side effects. When his addicts started dying from AIDS, he began to search for a drug that would help them.
Dr. Bihari knew that endorphins, small neurochemicals produced by the body, had pain-relieving, anti-inflammatory properties. Dr. Bihari and his colleagues hired a lab scientist to measure patient endorphin levels. He discovered that his HIV patients had sub-normal endorphin levels. His team determined that LDN doses ranging from 1.75 to 4.5 milligrams increased endorphin levels by two to three hundred percent. By blocking the body’s endorphin receptors, LDN caused an overproduction of endorphins.
Dr. Bihari then started a small foundation to study the use of LDN in HIV patients. After one year, he discovered that the patients who took LDN had an eight percent death rate while patients taking placebo had a thirty-three percent death rate. He and his colleagues went on to treat hundreds of patients with LDN.
Endorphins have a positive effect on the immune system by increasingT-helper and natural killer cells. Not only does LDN help people with autoimmune diseases like multiple sclerosis (MS), it also seems to be beneficial as an adjunct treatment for certain types of cancer. (See link for article)
If you are a Lyme/MSIDS patient and do not know about LDN, please learn about it and talk about it with your doctor. Many patients have benefitted from LDN which is an inexpensive, compounded drug that helps so many things patients struggle with. For more:
S1E102 – Slyme – an interview with Jenna Luché-Thayer
Ms. Luché-Thayer is the 59-year-old founder and director of the Ad Hoc Committee for Health Equity in ICD11 Borreliosis Codes
Tick Boot Camp’s guest today is Jenna Luché-Thayer. Ms. Luché-Thayer is the 59-year-old founder and director of the Ad Hoc Committee for Health Equity in ICD11 Borreliosis Codes, and she’s from Florida. She first experienced the symptoms of a tick disease in 1976, when she was just 16 years old. She had a fever, extreme fatigue, joint pain, and Bell’s palsy. Her illness came and went, but it took over 35 years for Ms. Luché-Thayer to receive a Lyme diagnosis. This expert brilliantly details what it is like to be a woman on the Lyme journey. If you would like to learn more about the amazing work that Ms. Luché-Thayer has done to give back to the Lyme community since her diagnosis, then tune in now!
Reasons for Lyme Nonprofits to Disown Post Treatment Lyme Disease Syndrome: A Case Study
Jenna Luche-Thayer
Senior Advisor – US Government, United Nations, non-profits, corporate social responsibility programs
INTRODUCTION
The denial of evidence showing persistent Lyme infection is a critical obstacle to adequate treatment. This case study demonstrates how funding Post Treatment Lyme Disease Syndrome (PTLDS) and Post Treatment Lyme Symptoms (PTLS) research may create further impediments to sufficient treatment. PTLDS/PTLS are terminology developed for ‘limited research constructs’. These research terms are frequently misappropriated as clinical diagnoses that wrongly infer underlying infection has been adequately treated —even when the patient has recurring symptoms [1].
Persons suffering from persistent Lyme infection, or any chronic illness, may develop secondary psychosomatic and psychiatric disorders. The misuse of PTLDS/PTLS in clinical settings often results in treatment limited to the secondary psychosomatic and psychiatric disorders and denial of adequate antimicrobials for the underlying infection.
This situation is encouraged by government funders of PTLDS/PTLS studies that tend to concentrate on possible psychosomatic and psychiatric aspects of PTLDS/PTLS and largely ignore infectious causes.
This case study is limited to the PTLDS/PTLS research focus by one influential Lyme patient advocacy organization, namely the Lyme Disease Association, Inc (LDA). This organization was chosen because they have the only patient advocate who is a voting member of the Federal Tick Borne Diseases Working Group. This assessment is based on information taken from the LDA website —53 Publications for LDA-Funded Research— and focuses on the 11 publications that use PTLDS/PTLS terminology. (See tables below for publication details —retrieved July 20, 2020)
https://themodelhealthshow.com/maskfacts/ This video goes through mask history as well as all the research and lists the clinical evidence and supplementary data. There is information on how popular mask effectiveness studies ignore real world conditions and includes virus transmission info. It lists the research on the physiological and psychological damage caused by mask usage, and the health/immune system/covid-19 relationship and coronavirus susceptibility due to mask usage.
It only takes ONE viral particle to spread disease. ONE!
“We’re seeing inflammation in people’s gums that have been healthy forever, and cavities in people who have never had them before,” says Dr. Rob Ramondi, a dentist and co-founder of One Manhattan Dental. “About 50% of our patients are being impacted by this, [so] we decided to name it ‘mask mouth’ — after ‘meth mouth.’ ”
There is so much news on the topic of mandatory masks, that it is hard to keep up with it all. Countries and other large areas that do NOT mandate face masks are actually seeing FEWER new cases of COVID. (See the Liberty Report show video below.)
In Nashville, a Council Member has publicly stated that people who refuse to comply with government edicts to wear masks should be charged with murder or attempted murder. (Source.)
When are people going to wake up to the face mask scam?
if they are actually effective, then what type of mask?
How does one dispose of them as bio-hazard waste?
How often should one be worn before discarded?, etc.
The evidence is overwhelming now: face masks are harming people and protecting nobody.
Dr. Ron Paul covers these issues, and he has also written a new article about the rapid loss of civil rights as the police state tightens it grip on the public.
House Speaker Nancy Pelosi has proposed the next multi-trillion dollar “coronavirus relief” spending bill that will support testing, tracing, treatment, isolation, and mask policies that have been part of a “national strategic plan” she has been advocating.
The Trump administration is not opposing Pelosi’s plan on principle. Instead, it is haggling over the price.
But, even if the strategic plan could be implemented at little or no monetary cost, it would still impose an unacceptable cost in lost liberty.
Pelosi’s plan will lead to either a federal mask mandate or federal funding of state and local mask mandate enforcement. Those who resist wearing masks could likely be reported to the authorities by government-funded mask monitors.
We can label this the “Stasi” approach to health policy, after the infamous East German secret police force.
Contact tracing could lead to forcing individuals to download a tracing app. The app would record where an individual goes and alert authorities that an individual has been near someone who has tested positive for coronavirus.
The strategic plan could eventually include Bill Gates’ and Anthony Fauci’s suggestion that individuals receive “digital certificates” indicating they are vaccinated for or immune to coronavirus.
A certificate would be required before an individual can go to work, to school, or even to the grocery store.
The need to demonstrate vaccination for or immunity to coronavirus in order to resume normal life would cause many people to “voluntarily” receive a potentially dangerous coronavirus vaccine.
The Trump administration has already spent billions of dollars to support efforts of companies to develop a coronavirus vaccine. Policymakers have stated that once a vaccine is developed it will be rushed into production and onto the market.
Supporters of expediting production and use of a vaccine should remember the 1976 swine flu vaccine debacle. The swine flu vaccine was rushed into production in response to political pressure to “do something.”
The result was a vaccine that was more of a danger than the flu.
Unfortunately, those who raise legitimate concerns regarding the safety of vaccines are smeared as “conspiracy theorists.” This is the equivalent of stating that anyone who dares criticize our interventionist foreign policy “hates freedom” and is probably a “terrorist sympathizer.”
Unique Patient Identifier
The coronavirus panic has given new life to the push for a unique patient identifier. The unique patient identifier was authorized in 1996, but appropriations bills since 1998 have contained a provision forbidding the federal government from developing and implementing the identifier.
Unfortunately, two weeks ago, the House of Representatives voted to repeal the ban. The unique patient identifier would aid government efforts to track and vaccinate every American, as well as to infringe in other ways on liberty in the name of “health.”
Politicians and bureaucrats cannot eliminate a virus any more than they can eliminate terrorism. What they can do is use terrorism, a virus, and other real, exaggerated, or manufactured crises to expand their power at the expense of our liberty.
Politicians will never resist the temptation to use crises as excuses to gain more power. Therefore, it is up to those of us who know the truth to spread the message of liberty and grow the liberty movement.
A strong liberty movement is the only thing that can force the politicians to stop stealing our liberty while promising phantom security from terrorists and viruses.
Dr. Sherri Tenpenny – FACE MASKS ARE NOT EFFECTIVE AGAINST COVID-19: HOW MASKS ARE BEING USED TO CONTROL THE POPULATION
July 28, 2020
American Osteopathic Physician
Dr Sherri Tenpenny, is the American osteopathic medical doctor, researcher and author.
She has invested 20 years, and over 40,000 hours, researching, documenting and exposing the complex issues of vaccine development, testing and distribution.
As an internationally renownedspeaker and author, her articles have been translated into over 12 languages.
Dr. Tenpenny has worked as an Emergency Medicine physicianand were Director of a Level 2 Trauma centre for over a decade.
She now runs her own medical centre, providing an integrated approach to health, which has attracted patients from 50 states and 17 countries, with the doctrine “the body can heal itself”.
In our first conversation on London Real in May, we discussed vaccine legislation, testing and distribution. In this episode we’re going deeper on masksand why they won’t protect you, contact tracing, and the psychological damage of social distancing.
Dr. Fauci was recently interviewed by Dr. Jennifer Ashton , ABC’s Chief Medical Correspondent. He said,
“The wearing of masks and other coverings as we just discussed, are going to not only protect against COVID-19 but also help protect us against influenza. So we may find a secondary benefit of the lessons that we’ve learned over the past six months.”
Once again Fauci hypocritically uses the data he wants when he wants. A firm believer in “Big Science” he feels only randomized, controlled trials should be trusted, yet 14 RCT’s in a meta-analysis “did not support a substantial effect on transmission of laboratory-confirmed influenza.” https://vaxxter.com/wp-content/uploads/2020/07/Masks-Final.pdf
Translation: You can wash your hands all you want or take a bath in hand sanitizer. Or not. You can wear any mask you want. Or not. It’s not going to matter. It won’t make any difference on whether you get Wuhan flu or not. That’s the science.
Face masks are worthless and potentially dangerous. Free the faces!
Comments Off on Best Video on Masks Yet. New Health Problems Emerging From Continuous Mask Wearing, but “Attempted Murder” Charges Sought For Those Who Refuse Them