http://  Approx. 8 Min

Media Continues to Undermine Science

October 15, 2020

By Ivor Cummins

Let the facts and the data speak for themselves – after the shocking intro piece, I supply some of those for you. Don’t worry – science still lives, albeit under attack. Please everyone sign the Great Barrington Declaration. It’s one way of fighting back:   https://gbdeclaration.org/

NOTE: My extensive research and interviewing / video/sound editing and much more does require support – please consider helping if you can at my Patreon Link: https://www.patreon.com/IvorCummins For monthly donation to support me directly, or one-off payment – simply use the following link: https://www.tinyurl.com/IvorCummins

For more:  https://madisonarealymesupportgroup.com/2020/10/17/massive-lawsuit-launches-against-covid-19-lockdowns/

https://madisonarealymesupportgroup.com/2020/08/20/politicians-could-have-known-covid-facts-since-april-but-they-dont-care-about-facts/

https://madisonarealymesupportgroup.com/2020/04/16/israeli-study-reveals-covid19-lockdown-was-pointless/

https://madisonarealymesupportgroup.com/2020/10/12/top-who-official-to-world-leaders-stop-using-lockdowns-to-control-covid-terrible-ghastly-global-catastrophe/

https://madisonarealymesupportgroup.com/2020/10/15/over-30000-health-experts-sign-declaration-against-covid-19-lockdowns/

https://madisonarealymesupportgroup.com/2020/05/23/we-are-infectious-disease-experts-its-time-to-lift-the-covid-19-lockdowns/

https://madisonarealymesupportgroup.com/2020/07/17/thousands-of-doctors-write-letter-covid-panic-and-restrictions-a-mass-casualty-incident-sign-here/

https://madisonarealymesupportgroup.com/2020/10/07/current-covid-19-data-no-reason-for-lockdowns/

https://madisonarealymesupportgroup.com/2020/05/24/do-lockdowns-work-mounting-evidence-says-no/

https://childrenshealthdefense.org/news/airlines-proof-of-immunity-commonpass/

OCTOBER 13, 2020

Airlines Test ‘Proof-of-Immunity’ Technology, Privacy Watchdogs Call It ‘Troubling’

By Jeremy Loffredo

At least two airlines are testing CommonPass, a new technology designed to let passengers prove they’ve tested negative for COVID-19 before they fly.

Proponents tout the CommonPass technology as a panacea for global travel in a pandemic world. They hope that a public weary of COVID-19 lockdowns and restrictions — but still fearful of the virus — will embrace it.

But civil rights and privacy groups warn against any technology that monitors individuals’ movements and activities. That includes any digital health pass, like CommonPass, that can be adapted to provide proof of vaccination.

Here’s how CommonPass works. An individual takes a COVID-19 test at an approved lab, then uploads the results to a smartphone. At the airport, airline staff and border officials scan a QR code from the phone, which certifies that the passenger is COVID-19 free.

The groups behind CommonPass — Common Project Foundation and the World Economic Forum — say the technology has the potential to create a universal digital platform for COVID-19 testing that, if adopted across all governments, could hasten the reopening of international borders.

As it stands now, each government determines its own rules and procedures for quarantines and border entry. That’s unacceptable, according to the World Economic Forum’s head of mobility, Christoph Wolff. In a statement, Wolff said: “Individual national responses will not be sufficient to address this global crisis.”

The Electronic Frontier Foundation, a nonprofit that advocates for civil liberties in a digital world, takes a different view. In May, the group stated its opposition to any type of “immunity passport” that would require “people to present supposed proof of immunity to COVID-19 in order to access public spaces, work sites, airports, school or other venues.”

Electronic Frontier Foundation argues that such technology threatens privacy and “would be a significant step toward a system of national digital identification that can be used to collect and store our personal information and track our location.”

The American Civil Liberties Union similarly warned against “immunity surveillance infrastructure” and “conditioning travel on COVID-19 immunity.”

Still, proponents like Dr. Bradley Perkins, former chief strategy and innovation officer at the U.S. Centers for Disease Control and Prevention — and now chief medical officer for Common Project Foundation — argue that proof-of-immunity technology is the solution to opening up borders. Perkins told the travel magazine, Afar:

“Without the ability to trust COVID-19 tests — and eventually vaccine records — across international borders, many countries will feel compelled to retain full travel bans and mandatory quarantines for as long as the pandemic persists.”

With suicides, clinical depression, domestic violence and small business closures on the rise during COVID-19 lockdowns and travel restrictions, will a public hungry for a “return to normal” side with civil liberties groups? Or will they see CommonPass as a reasonable trade-off for increased mobility and perceived safety?

We’ll soon find out. On Oct. 8, two airlines launched trial runs. United Airlines tested CommonPass with volunteers flying between New York and London. Cathay Pacific did the same for passengers flying between Hong Kong and Singapore. The U.S. Customs and Border Patrol and the U.S. Centers for Disease Control and Prevention observed the process.

CommonPass said in a press release that after the trials it plans to expand to more airlines and routes across the globe. Right now it’s limited to certifying negative COVID-19 tests. But in the future, CommonPass will be able to certify proof of vaccination, the company said. This means that even if a future COVID-19 vaccine is not mandated globally, airlines could require CommonPass for anyone wishing to travel, domestically or internationally.

“The hope is that the CommonPass will ultimately help reduce or eliminate […] quarantine requirements,” according to the article in Afar.

The idea of deploying digital health technology on a global scale isn’t new. As far back as 2010, The Rockefeller Foundation — whose president, Rajiv Shah, once ran the vaccine financing operation for the Gates Foundation — simulated a series of plausible “scenario narratives” that might unfold in response to a pandemic.

The foundation described one of these scenarios as a “world of tighter top-down government control and more authoritarian leadership.” The foundation lists biometric IDs as one element of this “more controlled world” where “citizens willingly gave up some of their sovereignty — and their privacy.”

The Rockefeller Foundation, which has ties to Big Pharma, has provided funding for Common Project Foundation, including through a $300,000 grant in 2019 and a $500,000 grant in 2020.

Common Project Foundation markets itself as “beholden to no one government.” Yet the project has deep ties to COVID-19 vaccine manufacturers, who will inevitably benefit if their products are mandated in order for people to travel across borders. The foundation partners directly with the Pfizer Foundation and Novartis Foundation, both founded by pharmaceutical manufacturers that have COVID-19 vaccines in development.

Common Project Foundation also works in partnership with the CARIN Alliance, a digital healthcare group affiliated with Pfizer.

Pfizer CEO Henry McKinell once hailed Klaus Schwab, founder and chairman of the World Economic Forum, as “a person dedicated to a truly noble cause.”

In his book, “COVID-19: The Great Reset,” Schwab echoes Bill Gates’ sentiment that “a full return to ‘normal’ cannot be envisaged before a vaccine is available.” Schwab also writes, “The next hurdle is the political challenge of vaccinating enough people worldwide with a high enough compliance rate despite the rise of anti-vaxxers.”

Jeremy Loffredo is a reporter for Children’s Health Defense.


“© [10/13/20] Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

__________________

**Comment**

I find it interesting that former CDC’s Dr. Perkins, now the chief medical officer for Common Project Foundation, states that the reason for proof of immunity technology is needed due to inaccurate COVID tests.  The reason we have such poor COVID testing is due to the CDC!  https://madisonarealymesupportgroup.com/2020/03/27/cdcs-deadly-testing-fiasco-centralization-of-public-health-authority-a-threat-to-national-security/

Lyme disease testing has remained abysmal for over 40 years but still remains the ‘gold standard’!  https://madisonarealymesupportgroup.com/2020/03/01/study-cdcs-2-tier-lyme-testing-inaccurate-in-more-than-70-of-cases/

There are numerous reasons for this but in a nutshell, the CDC directly competes with the private sector and maligns anything that competes with their own lucrative products, including but not limited to testing:  

https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/

One other concerning issue being mentioned repeatedly is the desire for a ‘centralized’ ‘global’ response.  This is newspeak for control and censorship, which is already occurring at unprecedented levels:

For more:  https://madisonarealymesupportgroup.com/2020/05/28/health-passport-scandal-uk/


Patent #WO2020060606, which is described as a “Cryptocurrency System Using Body Activity Data,” senses body activity of the user.
“Human body activity associated with a task provided to a user(1) may be used in a mining process of a cryptocurrency system. A server may provide a task to a device of a user which is communicatively coupled to the server(2). A sensor communicatively coupled to or comprised in the device(3) of the user may sense body activity of the user. Body activity data may be generated based on the sensed body activity of the user. The cryptocurrency system communicatively coupled to the device of the user may verify if the body activity data satisfies one or more conditions set by the cryptocurrency system(4), and award cryptocurrency to the user whose body activity data is verified.”(5)  https://operation-nation.com/bill-gates-microsoft-file-patent-for-dystopian-body-activity-data-implants/
The patent states that “conditions set by the cryptocurrency system” can be awarded cryptocurrency to the user.  In other words, if you are a good boy or girl you get points.  What happens if you aren’t a good boy or girl?
Apple already has an app for all of this:  https://madisonarealymesupportgroup.com/2020/05/18/coronavirus-covid-19-antibody-tests-do-you-really-want-one-think-hard-about-it-maybe-not/  It doesn’t matter if it’s the antibody test or the PCR.  They are both worthless and shouldn’t be used for diagnosis, let alone for quarantining people.
 

https://zoom.us/webinar/register/

68c9bc61-f9e4-404f-afee-1662b8afc25e

Effective and Affordable Testing for Chronic Vector-borne Diseases

Join Vibrant and Amy Offutt MD for an introduction and discussion of Vibrant’s new expanded tickborne and infections panels, including additional Lyme and TBRF markers, added coinfections, and now with opportunistic infections commonly missed alongside Lyme and coinfections.
Time:  6:00 PM CT (US and Canada)

Date:  Oct 22, 2020

Webinar logo
Dr. Amy Offutt is a director on the ILADS board, and the medical director and co-owner of Heart & Soul Integrative Health and Yoga located in Marble Falls, Texas. She completed her undergraduate studies at Abilene Christian University, medical school at The University of Texas Health Sciences Center in San Antonio, and a residency in Family Medicine at Christus Health. She also has a Master’s Degree in Integrative Medicine from George Washington University and has completed a fellowship in Integrative Medicine. Her calling to look for the cause of disease, in addition to how to manage symptoms, led to her appointment by Governor Greg Abbott to the Pediatric Acute-Onset Neuropsychiatric Syndrome Advisory Council in the summer of 2019. She has been married to her high school sweetheart, Brad, for 30 years, and they have 3 children, ages 19, 17, and 12. They enjoy family time, being on the lake, traveling, and healthy living.

https://www.ijidonline.com/article/S1201-9712(20)32175-5/fulltext#%20

Early Hydroxychloroquine but not Chloroquine use reduces ICU admission in COVID-19 patients

 
Open AccessPublished:September 29, 2020DOI:https://doi.org/10.1016/j.ijid.2020.09.1460
This paper is only available as a PDF. To read, Please Download here.

Highlights

  • •
    After the global push for the use of Hydroxychloroquine and Chloroquine there is ongoing discussion about the effectivity of these drugs.
  • •
    Findings of this observational study provide crucial data on a potential protective effect of Hydroxychloroquine in non-ICU, hospitalized COVID-19 patients.
  • •
    Early treatment with HCQ on the first day of admission is associated with a reduced risk of 53% in transfer to the ICU for mechanical ventilation.
  • •
    This protective effect was not observed for Chloroquine, therefore these drugs cannot be regarded as interchangeable.

Abstract

Background

The global push for the use of hydroxychloroquine (HCQ) and chloroquine (CQ) against COVID-19 resulted in an ongoing discussion about the effectivity and toxicity of these drugs. Recent studies report no effect of (H)CQ on 28 day-mortality. We investigated the effect of HCQ and CQ in hospitalized patients on the non-ICU COVID-ward.

Methods

A nationwide, observational cohort study was performed in The Netherlands. Hospitals were given the opportunity to decide independently on the use of three different COVID-19 treatment strategies: HCQ or CQ, or no treatment. We compared the outcome between these groups. The primary outcomes were 1) death on the COVID-19 ward, and 2) transfer to the Intensive Care Unit (ICU).

Results

The analysis contained 1064 patients from 14 hospitals: 566 patients received treatment with either HCQ (n = 189) or CQ (n = 377), and 498 patients received no treatment. In a multivariate propensity matched weighted competing regression analysis, there was no significant effect of (H)CQ on mortality on the COVID-ward. HCQ however was associated with a significant decreased risk of transfer to the ICU (Hazard ratio (HR) = 0.47, 95%CI = 0.27–0.82, p = 0.008), when compared to controls. This effect was not found in the CQ group (HR = 0.80; 95%CI = 0.55–1.15, p = 0.207), and remained significant after competing risk analysis.

Conclusion

The results of this observational study demonstrate a lack of effect of (H)CQ on non-ICU mortality. However, we show that the use of HCQ – but not CQ – is associated with 53% decreased risk of transfer of COVID-19 patients from the regular ward to the ICU. Recent prospective studies have reported on 28 days all-cause mortality only, therefore additional prospective data on the early effect of HCQ in preventing transfer to the ICU is still needed.

______________________

**Comment**

This poor drug has been scrutinized like no other – all because of severe conflicts of interest held by our public ‘authorities’. While it isn’t for everyone, and it must be utilized in a certain way, it has been shown repeatedly to work in certain populations. To ban it from use shows the underhanded way ‘authorities’ have dealt with it.

https://madisonarealymesupportgroup.com/2020/06/01/rebuttal-on-huge-hcq-study-in-lancet/

https://madisonarealymesupportgroup.com/2020/08/26/hydroxychloroquine-a-morality-tale/

https://madisonarealymesupportgroup.com/2020/06/30/dr-meryl-nass-discovers-hydroxychloroquine-experiments-were-designed-to-kill-covid-patients-how-many-were-murdered/

BTW:  The favored golden calf – the expensive yet lucrative anti-viral Remdesivir our public ‘authorities’ are cashing in on is showing itself to be a dud:  https://madisonarealymesupportgroup.com/2020/07/02/remdesivir-for-covid-19-not-backed-by-results/

https://www.zerohedge.com/geopolitical/massive-who-study-shows-remdesivir-doesnt-lower-covid-19-mortality?  Excerpt:

The highly anticipated WHO drug trial called Solidarity found that Gilead’s COVID-19 treatment, remdesivir, had no substantial effect on a COVID-19 patient’s chances of survival. It also found that three other therapeutics were similarly ineffective.

One of those was HCQ, although it has been shown in numerous other studies that if used appropriately, will benefit patients:  

https://madisonarealymesupportgroup.com/2020/08/08/new-report-turkeys-use-of-hcq-early-saves-lives-fauci-should-be-in-jail/

https://madisonarealymesupportgroup.com/2020/10/13/another-1700-cured-of-covid-using-hcq/

Dr. Zelenko, a New York doctor, has successfully treated 1,450 COVID-19 patients with a 99% success rate using a cocktail of hydroxychloroquine, Zinc Sulfate and Azithromycin:  https://techstartups.com/2020/04/21/dr-vladimir-zelenko-now-treated-1450-coronavirus-patients-2-deaths-using-hydroxychloroquine-99-99-success-rate-latest-video-interview/  Video with Zelenko in link.

https://madisonarealymesupportgroup.com/2020/07/20/how-a-false-hydroxychloroquine-narrative-was-created/


https://pubmed.ncbi.nlm.nih.gov/33028242/

Chest palpitations in a teenager as an unusual presentation of Lyme disease: case report

Affiliations expand

Free PMC article

Abstract

Background: The incidence of Lyme disease (LD) in North America has increased substantially in the past two decades. Concomitant with the increased incidence of infection has been an enhancement in the recognition of LD complications. Here, we report a case of Lyme carditis complicated by heart block in a pediatric patient admitted to our children’s hospital. What is unique about this case is that the complaint of chest palpitations is an infrequent presentation of LD, and what it adds to the scientific literature is an improved understanding of LD in the pediatric population.

Case presentation: The patient was a 16-year-old male who presented with the main concerns of acute onset of palpitations and chest pain. An important clinical finding was Erythema migrans (EM) on physical exam. The primary diagnoses were LD with associated Lyme carditis, based on the finding of 1st degree atrioventricular heart block (AVB) and positive IgM and IgG antibodies to Borrelia burgdorferi. Interventions included echocardiography, electrocardiography (EKG), and intravenous antibiotics. The hospital course was further remarkable for transition to 2nd degree heart block and transient episodes of complete heart block. A normal sinus rhythm and PR interval were restored after antibiotic therapy and the primary outcome was that of an uneventful recovery.

Conclusions: Lyme carditis occurs in < 5% of LD cases, but the “take-away” lesson of this case is that carditis can be the presenting manifestation of B. burgdorferi infection in pediatric patients. Any patient with suspected Lyme carditis manifesting cardiac symptoms such as syncope, chest pain, or EKG changes should be admitted for parenteral antibiotic therapy and cardiac monitoring. The most common manifestation of Lyme carditis is AVB. AVB may manifest as first-degree block, or may present as high-grade second or third-degree block. Other manifestations of Lyme carditis may include myopericarditis, left ventricular dysfunction, and cardiomegaly. Resolution of carditis is typically achieved through antibiotic administration, although pacemaker placement should be considered if the PR interval fails to normalize or if higher degrees of heart block, with accompanying symptoms, are encountered. With the rising incidence of LD, providers must maintain a high level of suspicion in order to promptly diagnose and treat Lyme carditis.

___________________

**Comment**

Repeat:  Researchers need to refrain from stating that something is “rare” with Lyme disease as:
  • testing misses more than 70% of cases (thousands go undiagnosed)
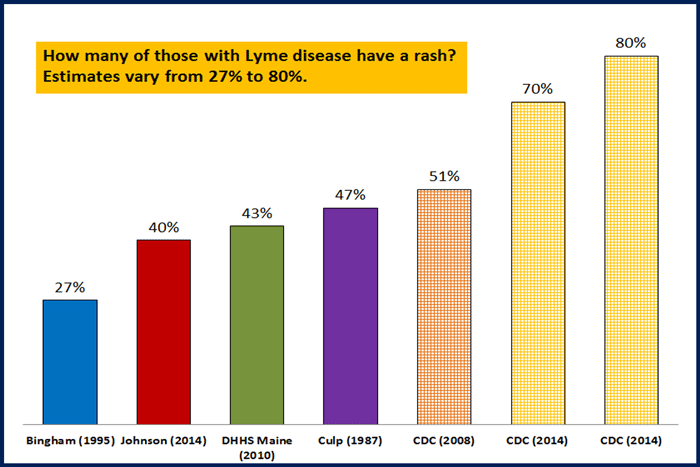
  • much fewer report the EM rash than is quoted
  • this is still a misunderstood illness that doctors are woefully uneducated on.  If a patient doesn’t present with the EM rash, doctors unfamiliar with the wide symptom presentation are not going to catching this.

For more:  https://madisonarealymesupportgroup.com/2020/03/01/study-cdcs-2-tier-lyme-testing-inaccurate-in-more-than-70-of-cases/

Click on image to see better. The graph is clear that there is a wide range of those with those finding the EM rash. While the EM rash is diagnostic for Lyme disease, many do not get it. In the first ever patient group in Lyme, Connecticut, only a quarter had the rash:

https://madisonarealymesupportgroup.com/2019/02/22/why-mainstream-lyme-msids-research-remains-in-the-dark-ages/

Again, mainstream medicine continues with abysmal testing and ancient dogma that is hurting patients.

More accurate scientific language would be: “Heart palpitations are rarely reported in the literature.”  What happens in the real world is often quite different than what is reported in the literature – particularly with Lyme as research has been hijacked by The Cabal:  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/

BTW: I had chest palpitations, my husband had chest palpitations, and most of the patients I work with have them.  I don’t think it’s nearly as rare as  is being reported.

It’s a good thing this teen was promptly diagnosed as people have died from this:  https://madisonarealymesupportgroup.com/2020/02/21/17-year-old-dies-from-lyme-carditis/ 

The following statement is quite frightening:

The hospital course was further remarkable for transition to 2nd degree heart block and transient episodes of complete heart block.

https://madisonarealymesupportgroup.com/2018/11/16/advanced-heart-block-in-children-with-lyme-disease-2/

https://madisonarealymesupportgroup.com/2019/12/09/study-identifies-189-children-with-lyme-carditis/

https://madisonarealymesupportgroup.com/2018/09/17/lyme-carditis-heart-block-other-complications-of-ld/  Excerpt:

In 90% of cases, the most common consequence of Lyme carditis is heart block. The severity of the heart block can fluctuate rapidly and the progression to complete heart block can be fatal. Importantly, the heart block in Lyme carditis can be transient and usually resolves with antibiotic therapy. Additionally, Lyme carditis can affect other parts of the heart’s conduction system, as well as the heart’s muscle, valves, and outer layer of the heart wall.

https://madisonarealymesupportgroup.com/2020/08/22/boothbay-harbor-man-recovering-from-near-fatal-lyme-disease-infection/

These links show heart issues caused by Lyme disease are not rare.

Lyme advocate, Phyllis Mervine, makes a case that autopsies should be performed on those with unexpected, sudden death:  https://madisonarealymesupportgroup.com/2018/07/09/with-unexpected-death-autopsies-should-look-for-lyme-carditis/