https://igenex.com/tick-talk/what-you-need-to-know-about-borrelia-miyamotoi/

What You Need to Know About Borrelia Miyamotoi

Researchers are paying more and more attention to Borrelia miyamotoi, a spiral-shaped bacteria related to the types of Borrelia that cause Lyme disease. This bacteria is prevalent on both coasts of the US and is a known cause of Tick-Borne Relapsing Fever, or TBRF.

What is Borrelia miyamotoi?

Borrelia miyamotoi is one of the most recently discovered species of Relapsing Fever-causing bacteria.  In fact, some experts consider it the causative agent of an “emerging” tick-borne disease, and it is not even reportable to the CDC yet.

As will be addressed in detail later in this blog, what makes B. miyamotoi different from other TBRF bacteria is that it is spread by a different type of tick. Whereas most TBRF cases in the US are spread by soft ticks, B. miyamotoi is spread by hard ticks – including the same species of ticks that spread Lyme disease.

Keep reading to learn more about B. miyamotoi and what it means for patients, doctors, and testing and diagnostics.

What you need to know about Borrelia miyamotoi

1. B. miyamotoi is closely related to other TBRF-causing bacteria.

B. miyamotoi is one of several closely related bacteria that cause Tick-Borne Relapsing Fever in the US. Like the bacteria that cause Lyme, these are spiral-shaped bacteria or “spirochetes” that cause serious symptoms, including rashes and fevers.

TBRF gets its name from the “relapsing” fevers that show up in some patients. According to the CDC, these are typically high fevers (e.g., 103 degrees) that last for about 3 days, followed by about 7 days without fever, then 3 days of fever again, and so on. Symptoms typically show up within 7 days of infection and can repeat several times if not treated with antibiotics.

However, it is important to note that not all patients experience fevers. Like Lyme disease, TBRF symptoms can vary widely among patients. The non-specific nature of these symptoms can lead to misdiagnosis, especially in the case of patients who think they have Lyme but test negative because the test is not designed to detect other types of bacteria, like those that cause TBRF.

2. B. miyamotoi was first discovered in Japan in 1995.

In 1995, Masahito Fukunaga et al. discovered and named Borrelia miyamotoi after the researcher who had first isolated spirochetes from hard-bodied ticks in Japan. According to the CDC, it wasn’t until 2011 that the first human case of B. miyamotoi infection was found in Russia. The first North American human case was found in 2013, though some research shows the presence of the bacteria in ticks in Connecticut as far back as 2001.

3. Some experts consider Borrelia miyamotoi disease separate from TBRF.

The CDC and some other entities refer to the illness caused by B. miyamotoi as Borrelia miyamotoi disease. Though the CDC does not provide explicit reasoning for this, there are some similarities and differences between B. miyamotoi and other TBRF-causing bacteria that may be of interest to readers. One difference, which will be covered more in detail later, is that B. miyamotoi is spread by a different type of tick than other TBRF-causing bacteria in North America.

However, what CDC calls Borrelia miyamotoi disease causes very similar symptoms to those of TBRF, namely fever, chills, and headache. Additionally, infections caused by B. miyamotoi and other TBRF-causing bacteria can be detected with both PCR tests and serological tests, and both are treated by antibiotics, usually doxycycline (as with TBRF and Lyme) but sometimes amoxicillin or ceftriaxone. For children and pregnant women, erythromycin or penicillin can be successful.

4. Even baby ticks can be infected with B. miyamotoi.

As IGeneX has covered in numerous articles before, humans are most commonly infected by bites from ticks in the nymph stage of development. This is because ticks at this stage have previously fed on animal reservoirs in the larval stage – such as the white-footed mouse – and then move onto blood meals from larger animals, such as dogs or humans, where they are able to transmit pathogens without being noticed due to their small size.

However, research has shown that B. miyamotoi can actually be spread directly from adult female ticks to their offspring through something called transovarial transmission. In other words, baby ticks can be “born” already infected with B. miyamotoi, rather than having to feed on an infected host (as is the case with Lyme-causing bacteria). Larval ticks still make up a very small percentage of overall infected ticks, with a recent San Francisco State University study showing just 0.11% of larvae in the sample being infected with B. miyamotoi. However, the prevalence of infection increases at each stage of life, and transovarial transmission gives B. miyamotoi a head start.

5. B. miyamotoi is the only known TBRF bacteria spread by hard ticks.

One of the main differences between Lyme disease and TBRF is that most cases of TBRF in the US result from the bites of soft ticks. Soft ticks come from the Argasidae family, as opposed to the Ixodidae family of hard-bodied ticks. Soft ticks have more rounded bodies and are missing the hard shell around the mouthparts that is characteristic of hard-bodied ticks. What’s more, soft ticks can transmit disease – typically via the bacteria B. hermsii, the most common TBRF pathogen in the U.S. – in under 15 minutes.

However, B. miyamotoi is the only cause of TBRF that is known to be spread by hard ticks from the Ixodidae family. In the US, B. miyamotoi is found specifically in Eastern and Western blacklegged ticks (also known as deer ticks) – the main causes of Lyme disease in the US. This means that those living in blacklegged tick-endemic regions, including states along both coasts, are at risk of both Lyme disease and TBRF. It is also possible to be infected with both Lyme and TBRF from the same tick bite.

Doctor uses an in-ear thermometer to take the temperature of a patient.
6. Symptoms of a B. miyamotoi infection look a lot like Lyme symptoms.

It’s important to understand that symptoms of B. miyamotoi infections and TBRF, in general, can look just like Lyme symptoms. These include:

  • Fever – can be recurring in a pattern of 3 days with fever, 7 days without, and so on
  • Chills
  • Headaches
  • Muscle and joint pain

Again, not all patients experience fevers, and patients who do have fevers will not necessarily experience recurring fevers. And since the same hard-bodied ticks that carry Lyme disease can also carry B. miyamotoi, you can be infected with both diseases at once (among other tick-borne co-infections). This means it is extremely important for doctors to test patients for all possible disease-causing bacteria, including B. miyamotoi.

IGeneX offers comprehensive tick-borne disease testing designed to detect all major tick-borne disease pathogens in the US, not just those that cause Lyme. Learn more about testing for TBRF with IGeneX today.

______________________

**Comment**

Great information on a pathogen that isn’t reportable yet. This is a real problem. Prevalence is completely unknown due to this – which desperately needs to change. Borrelia Miyamotoi (Bm) could very well be a reason many are going undiagnosed. Since Lyme testing will not pick it up, many with legitimate symptoms are being sent home after testing negative for Lyme.

For more: https://madisonarealymesupportgroup.com/?s=Borrelia+M

https://news.yale.edu/2020/11/11/yale-scientists-identify-protein-protects-against-lyme-disease

Yale scientists identify protein that protects against Lyme disease

Lyme tick
(© stock.adobe.com)

Yale researchers have discovered a protein that helps protect hosts from infection with the tick-borne spirochete that causes Lyme Disease, a finding that may help diagnose and treat this infection, they report Nov. 11 in the journal PLOS Pathogens.

Lyme Disease is the most common vector-borne disease in North America and is transmitted by ticks infected with the spirochete Borrelia burgdorferi. The course of the disease varies among individuals, with the majority experiencing mild symptoms easily treated by antibiotics. However, in some cases of untreated Lyme the infection can spread to the heart, joints, nervous system, and other organs.

For the study, the Yale team expressed more than 1,000 human genes in yeast and analyzed their interactions with 36 samples of B. burgdorferi. They found that one protein, Peptidoglycan Recognition Protein 1 (PGLYRP1), acts like an early warning signal to the immune system when exposed to the bacteria. When exposed to the Lyme spirochete, mice lacking PGLYRP1 had much higher levels of B. burgdorferi than mice with the protein and showed signs of immune system dysfunction, the researchers report.

“Stimulating the ability of people to make more of this protein could help fight infection,” said Yale’s Erol Fikrig, the Waldemar Von Zedtwitz Professor of Medicine (Infectious Diseases) and professor of epidemiology (microbial diseases) and of microbial pathogenesis and co-corresponding author of the study.

Fikrig and his colleagues are also investigating whether people with higher levels of PGLYRP1 may be less susceptible to infection by B. burgdorferi, which would help explain why some infected individuals have better outcomes.

Yale’s Noah Palm and Aaron Ring are co-corresponding authors of the paper.  Akash Gupta, Gunjun Arora, and Connor Rosen of Yale are co-lead authors.

The work was primarily funded by the National Institutes of Health and the Steven & Alexandra Cohen Foundation, a nonprofit that supports Lyme and tick-borne disease research.

______________________

**Comment**

A few points:

They state, “The course of the disease varies among individuals, with the majority experiencing mild symptoms easily treated by antibiotics. However, in some cases of untreated Lyme the infection can spread to the heart, joints, nervous system, and other organs.”

OK – this is FALSE.

No, a majority do NOT experience mild symptoms easily treated with antibiotics.
  • Current CDC 2-tiered testing is missing 70-86% of cases.  They have ZERO idea of prevalence due to all the people being misdiagnosed or undiagnosed.  Also, even the people who win the testing lotto and manage to test positive are told they have “false positives” and are sent home empty-handed to worsen.
  • As to being “easily treated with antibiotics,” how do you explain the 40-60% or more who go on with life-long symptoms?  https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/ and the fact there has been treatment failure in nearly every antibiotics study ever done?  https://madisonarealymesupportgroup.com/2019/02/22/why-mainstream-lyme-msids-research-remains-in-the-dark-ages/
  • They state that only the “untreated Lyme” patients struggle with infection in the heart, joints, CNS, and other organs when this can happen WITH those who are treated as well.  In fact, in my experience ALL the patients I deal with have these severe symptoms.  ALL!
  • While I don’t want to appear to be a stick in the mud, I’m highly skeptical that lacking a certain protein is the sole reason for having lower levels of Bb.  I can think of numerous reasons for this – including being infected with numerous pathogens – suppressing the immune system.
  • Stay tuned.  These studies promise a lot but often deliver little, especially when the premise behind it all is that this complex illness is due to immune dysregulation NOT the underlying persistent infection. Again, in my experience it’s both that are a problem but by treating the underlying infection, the immune dysregulation is also treated.

https://www.nytimes.com/2020/11/17/health/coronavirus-immunity

Blood samples from recovered patients suggest a powerful, long-lasting immune response, researchers reported.
Credit…Cheney Orr/Reuters

How long might immunity to the coronavirus last? Years, maybe even decades, according to a new study — the most hopeful answer yet to a question that has shadowed plans for widespread vaccination.

Eight months after infection, most people who have recovered still have enough immune cells to fend off the virus and prevent illness, the new data show. A slow rate of decline in the short term suggests, happily, that these cells may persist in the body for a very, very long time to come.

The research, published online, has not been peer-reviewed nor published in a scientific journal. But it is the most comprehensive and long-ranging study of immune memory to the coronavirus to date.  (See link for article)

____________________

**Comment**

While it’s true this study has not been peer-reviewed or published in a bought-out scientific journal, it completely aligns with other findings and what has occurred historically for viruses.

  • survivors of SARS carry certain important immune cells 17 years after recovering
  • a study at the University of Washington show “memory” cells persist for at least 3 months after infection
  • those recovered from COVID-19 have powerful and protective killer immune cells even when antibodies are not detectable.  Many immunologists have noted that it is completely  natural for antibody levels to drop, as they are just one arm of the immune system.
  • a Yale immunologist is not surprised by the long-lasting response because “that’s what is supposed to happen.”  Akiko Iwasaki
  • another immunologist stated that typically people get infected a second time but that the immune system recognizes it and resolves it so quickly you remain asymptomatic and not infectious, and that “sterilizing immunity” is rare and not the norm
  • the new study by Sette et al., the first to chart the immune response in such detail, looked at antibodies, B cells, and two types of T cells – to better understand the whole immune response over time
  • an author of the study frequently cited suggesting fading immunity admits that reinfections with the coronavirus are rare
  • while immunity duration is difficult to predict studies so far show even small numbers of antibodies or T & B cells may be enough and that study participants have been making “robust amounts”
  • emerging evidence on reinfections with common cold coronaviruses are a result of viral genetic variations and may not be relevant to COVID-19
These results along with successful COVID treatments reveal once again that an experimental, fast-tracked, adverse reaction riddled vaccine isn’t needed.

https://www.dailymail.co.uk/debate/article-8899277/Professor-Sunetra-Gupta-reveals-crisis-ruthlessly-weaponised

A contagion of hatred and hysteria: Oxford epidemiologist PROFESSOR SUNETRA GUPTA tells how she has been intimidated and shamed for backing shielding instead of lockdown

(See link for article)  Important excerpts from Professor Sunetra Gupta:

I was utterly unprepared for the onslaught of insults, personal criticism, intimidation and threats that met our proposal. The level of vitriol and hostility, not just from members of the public online but from journalists and academics, has horrified me.

Covid-19 is not a political phenomenon. It is a public health issue — indeed, it is one so serious that the response to it has already led to a humanitarian crisis. So I have been aghast to see a political rift open up, with outright abuse meted out to those who, like me, question the orthodoxy.

At the heart of our proposal is the recognition that mass lockdowns cause enormous damage. We are already seeing how current lockdown policies are producing devastating effects on short and long-term public health.

I was also deeply concerned that lockdowns only delay the inevitable spread of the virus. Indeed, we believe that a better way forward would be to target protective measures at specific vulnerable groups, such as the elderly in care homes.

This pandemic is an international crisis. To shut down the discussion with abuse and smears — that is truly dangerous.

Yet of all the criticisms flung at us, the one I find most upsetting is the accusation that we are indulging in ‘policy-based evidence-making’ — in other words, drumming up facts to fit our ideological agenda.

According to Wikipedia, for instance, the Great Barrington Declaration was funded by a Right-wing think-tank with links to climate-change deniers.

It should be obvious to anyone that writing a short proposal and posting it on a website requires no great financing. But let me spell it out, since, apparently, I have to: I did not accept payment to co-author the Great Barrington Declaration.

But rest assured. Whatever they throw at us, it won’t do anything to sway me — or my colleagues — from the principles that sit behind what we wrote.

Professor Sunetra Gupta is an infectious disease epidemiologist and a professor of theoretical epidemiology at the Department of Zoology, University of Oxford. Her fee for this article has been donated to The Childhood Trust, a charity which fights to alleviate the impact of child poverty.

____________________

**Comment**

The AMA/CDC/FDA with a complicit media is quite adept at smear campaigns. They bully anyone who defies their narrative or attempts to compete with their lucrative products. This happens continually to Lyme doctors and alternative health providers:

It has happened to researchers who defy the narrative:  

For more on those defying the COVID narrative (the number grows daily):  

Medicine is doomed when it quits listening to patients and when it bullies those with differing ideas.

https://www.prlog.org/12846049-galaxy-diagnostics-launches-the-most-sensitive-test-available-for-direct-detection-of-lyme-disease.html

Galaxy Diagnostics Launches the Most Sensitive Test Available for Direct Detection of Lyme Disease

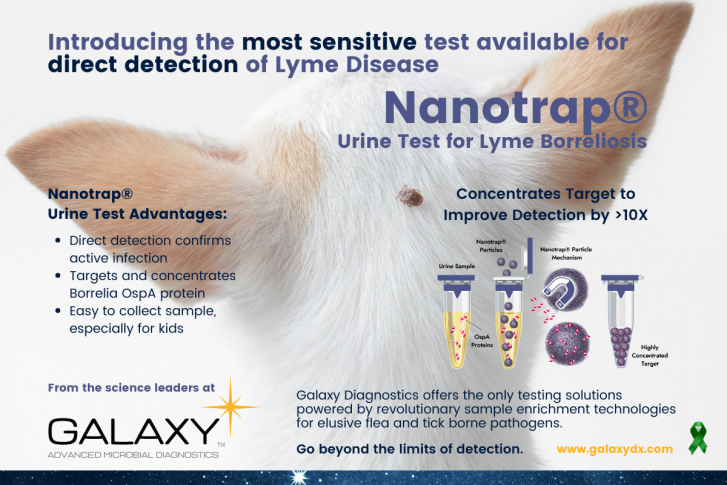
Science Leader in the Testing of Flea and Tick Borne Illness Introduces the Nanotrap® Urine Test for Lyme Borreliosis

By: Galaxy Diagnostics, Inc.123

Nanotrap Most Sensitive Test for Lyme Borreliosis

Nanotrap Most Sensitive Test for Lyme Borreliosis

DURHAM, N.C. – Nov. 10, 2020 – PRLog — Galaxy Diagnostics, Inc., the science leader in sample enrichment powered testing solutions for elusive flea and tick-borne pathogens, today announced the launch of the Nanotrap® Urine Test for Lyme Borreliosis.  This urine-based Lyme antigen test provides the most sensitive direct detection of Borrelia burgdorferi infection at all stages of the disease.  The test provides advantages antibody testing does not, namely:

  • Identifies positive cases missed by CDC-recommended Two-Tiered Testing (TTT)
  • Reduces concern for false positive results via direct detection of OspA proteins
  • Uses easy-to-collect urine sample

The revolutionary test greatly increases the likelihood of Lyme disease confirmation via innovative Nanotrap® technology developed by Ceres Nanosciences. Nanotrap® particles capture and concentrate low abundance Outer surface protein A (OspA) in urine samples confirmed by a highly sensitive Western blot.

Published data shows that the Nanotrap Urine Test is very effective for confirmation of early stage Lyme borreliosis in patients with EM rashes (24/24). Galaxy validation data (unpublished) shows that the Nanotrap® Urine Test will often confirm active infection in patients with negative TTT results. Further research is needed to confirm clinical utility for other presentations of Lyme borreliosis, including Lyme arthritis, Lyme carditis, and neuroborreliosis.

“The addition of the Nanotrap® test aligns with our mission to bring the most scientifically advanced sample enrichment technologies and diagnostic advances to the forefront of flea and tick borne disease”, said Galaxy CEO Amanda Elam. “Lyme disease is the fastest growing tick-borne illness in the United States. We are committed to improving the standard of care around detection of these elusive, low abundance pathogens to ensure better patient care for millions globally.”

Galaxy advocates for a new standard of care in Lyme Borreliosis testing and recommends a combination diagnostic protocol with Nanotrap® Urine test to confirm active infection and the CDC recommended TTT to detect the presence of antibodies.

You can order here and learn more at galaxydx.com.

About Galaxy Diagnostics

Galaxy Diagnostics is a privately held medical laboratory located in Research Triangle Park offering the only testing solutions powered by revolutionary sample enrichment technologies for elusive flea and tick borne pathogens. The company’s mission is to “Go Beyond” the limits of conventional detection by driving scientific innovation, creating new clinical knowledge through research and publication, and providing medical education and excellent customer support to healthcare providers, veterinarians, patients, and research customers in this important area of emerging infectious disease.

About Ceres Nanosciences

Ceres Nanosciences is a privately held company, located in Northern Virginia, focused on incorporating its novel Nanotrap® particle technology into a range of diagnostic products and workflows. The Nanotrap® particle technology can improve diagnostic testing by capturing, concentrating, and preserving low abundance analytes from biological samples. The Nanotrap® particle technology was developed with support from the National Institutes of Health (NIH), the Defense Advanced Research Projects Agency (DARPA), the Bill and Melinda Gates Foundation, Schmidt Futures, the Defense Threat Reduction Agency (DTRA), and the Commonwealth of Virginia.

Contact
James Rebenski
***@galaxydx.com

Photos:
https://www.prlog.org/12846049/1
https://www.prlog.org/12846049/2
https://www.prlog.org/12846049/3

_____________________

**Comment**

According to Dr. Shor, this “urine-based antigen test,” based on the OspA protein, is 100% sensitive for acute cases with EM rash (24/24 patients with EM rash tested positive). Please remember that while appearing successful for acute Lyme, this is a small study group. Also, having the EM rash is DIAGNOSTIC for Lyme – i.e. no testing even required.

It is far less effective for those who are chronically infected. It was positive for 42% out of 100 chronically ill patients.

I believe I heard Dr. Klinghardt recommend rolfing (deep tissue massage) before taking this test to force the organisms out in the blood where they can be excreted and picked up on this urine test.

To watch Dr. Shor’s presentation:

http://  Approx. 1 hour 20 Min

May 24, 2017

NatCapLyme Presentation

Diagnosing people early is critical as doctors, despite knowing this complex illness can become very severe and more difficult to treat if left untreated, continue to take a ‘wait and see’ approach. They continue to rely upon faulty testing that misses anywhere from 70-86% of cases, and often wait for test results before treating – dooming thousands of patients to a life-time of suffering. This test will hopefully help these early cases; however, it will not be as effective for the chronically infected – nor help with those who are coinfected.

Diagnosing tick-borne illness has always been a clinical diagnosis.

Time for doctors to become educated instead of lazily relying upon faulty testing.