https://vtdigger.org/2019/06/16/high-tick-populations-prompt-lyme-disease-concerns/
Vermont’s No. 2 ranking for Lyme disease prompts concerns
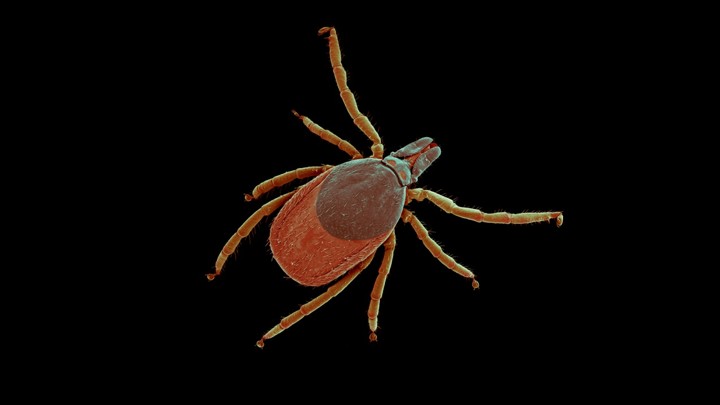
 A blacklegged tick, commonly known as a deer tick. Photo courtesy of Vermont Department of Health
Vermont currently ranks No. 2 in the country for Lyme disease — though many years, it’s No. 1. The CDC considers the disease endemic in the state.
Critics of the medical establishment, however, believe there is another problem contributing to the high incidence of the disease in Vermont: A lack of effective early diagnosis and treatment.
In 2017, there were 1,093 cases, according to the Vermont Department of Health. Data from 2018 hasn’t been finalized yet, but according to Natalie Kwit, the state public health veterinarian, there were likely approximately 500 to 600 cases, which she described as a normal year-to-year variance.
Other tick-borne diseases, like Babesiosis and Anaplasmosis, are also on the rise in Vermont, Kwit said. Since Vermont is on the northern edge of the area affected by tick-borne illnesses, the lower half of the state gets hit hardest. According to Kwit, Bennington County has the highest incidence of Lyme disease, followed by Rutland, Windsor, Windham, Addison and Grand Isle Counties.
Kwit said it’s hard to say how bad this year will be, but noted that with the ticks in their nymph form right now — when Lyme disease rates are highest — Vermonters should be particularly careful through June and July.
Bill Landesman, who researches ticks at Green Mountain College, said Vermont is kind of a perfect storm for Lyme rates. Not only are the black-legged ticks that populate the area ideal hosts for Borrelia burgdorferi, the bacteria that causes Lyme — the state also has plentiful numbers of white-tailed deer and deer mice, two primary tick carriers.
Landesman said the infection rate for nymphs, which are currently in season, is around 20% to 30%, while the adult rate, in season later in the summer, is twice that, 40% to 60%. He said on some of the sites he studies, there is a one in four chance that you’ll find a tick in any given square meter — meaning if you go on a hike through the woods, you’re at risk for Lyme.
Critics say the Lyme problem in Vermont isn’t just the result of a high tick incidence. They question whether the medical community could do more to respond to the endemic.
Medical professionals acknowledge that Lyme can be frustrating to diagnose.
Prompt diagnosis as prevention
Rebecca Zelis’ son didn’t have the bullseye rash or joint pain that doctors tend to look for to identify Lyme disease. But his symptoms presented behaviorally. By the time he reached kindergarten, Zelis said his symptoms were deeply troubling.
“Mommy I just want to die,” he told her. “I want to run in front of a car and die.”
Diagnoses for her son ranged from psychological problems to bad parenting. It wasn’t until her son started to get more classic symptoms, like headaches and chronic infections, that doctors finally recognized he had Lyme disease.
Since he went so long without treatment, there was a long road back to neurological recovery. He was homeschooled for a while in middle school because he was too sick to leave the house.
When Zelis looked online for more information, she found a lot about prevention, but not as much about symptoms, especially less typical symptoms like the ones her son was experiencing. So in 2015, she started VTLyme.org — now a nonprofit — to help other Vermonters navigate the disease and other tick-borne illnesses.
When caught early and treated effectively, Zelis said, Lyme disease typically won’t cause long term problems. But oftentimes, that isn’t the case.
“Not all medical providers in Vermont know how to accurately diagnose and effectively treat tick-borne diseases,” Zelis said. “Vermonters affected by complex tick-borne diseases need more resources, understanding and support.”
In 2014, Zelis said more than half of the children diagnosed with Lyme disease in Vermont did not have a bullseye rash, but all of the medical information she was seeing still centered around that symptom. The Center for Disease Control reports that nationally between 70% and 80% of Lyme disease cases involve a bullseye rash. But Zelis cautions that local variances can get forgotten among the broader national conversations.
She said in the past two months, patients have told her they haven’t received accurate information from doctors. In one case, a woman wrote to her about a friend’s child who was bitten by a tick and was told to wait, and if the child didn’t get a bullseye rash, they were in the clear. Another message was from a parent whose son had a bullseye rash after they got back from a camping trip, but was told by his doctor that as long as he had no other symptoms, he didn’t need to worry — though within a year, the child had almost every known symptom of Lyme.
“I would argue that accurate and prompt diagnosis is a form of prevention,” said Zelis, who is studying for a mental health degree with the aim of helping people affected by Lyme disease. “It’s preventing people from having a more complex and severe form of the disease.”
Seeking treatment
A little over a year ago, Monika Reis of Montpelier noticed an immature tick, called a nymph, lodged in her neck. She later saw a rash, though not the typical bullseye. She went to Plainfield Health Center, where a doctor took a picture of the rash and did blood work — which came back negative for Lyme. Within a week, she had night sweats that were so intense she checked the ceiling to see if there was a leak.
“I had it full on within two weeks. There’s no manufacturing that experience,” Reis said.
So she went back to the doctor, who decided to treat it as Lyme, even though her blood work wasn’t conclusive.
Reis’ experience was in contrast to friends who she knew were in similar situations, but whose doctors didn’t immediately treat it that way.
“We throw antibiotics at children 12 times before they’re 7 for earaches, and suddenly, an adult with a strong feeling and a photo of rash comes in, and you’re not going to treat for Lyme?” Reis said. “There’s a real problem here with the resistance to thinking that it’s Lyme.”
In addition to taking doxycycline, the antibiotic typically used to treat Lyme, Reis used herbal remedies and acupuncture. Several of her friends with Lyme regularly go out of state just to see specialists.
Reis stressed that people who suspect they have Lyme have to be assertive about their treatment.
“Even within my own story that’s true,” Reis said. “If someone is not willing to treat you, I’d highly recommend going to another person within a few days, or even a naturopath — somebody that is going to be empathetic to your situation and not have this blocked mentality about it.”
A state law passed in 2014 gave doctors more latitude in their treatment of Lyme by allowing them to treat outside of the guidelines set by the Infectious Disease Society of America.
But Rachel Nevitt, who advocated for the bill, believes Vermont’s response to the disease is badly outdated.
“The truth of the matter is providers here are clueless,” Nevitt said. “Some are catching on, but those catching on are afraid to treat it the way it needs to be treated because the medical boards will come after them.”
Nevitt had likely had the disease for years before she was finally diagnosed. In 2009, Nevitt suddenly fell to the floor with excruciating spinal pain. She presented like she had a herniated disc, but had no precipitating accident, and an MRI showed up normal. Today, Nevitt said, people know that means Lyme. But back then, it was just another bullet point in her laundry list of symptoms she couldn’t explain.
Nevitt was becoming dyslexic, forgetful, and losing spatial awareness. Once, she accused her husband of spending $80,000 on a new irrigation system for their farm simply because she couldn’t recognize the irrigation system that they’d been using for years.
It wasn’t until her farm manager tested positive for the disease and told Nevitt she should get tested that she began to even consider Lyme. But Nevitt knew she never saw a tick bite, and never had a rash — she couldn’t have Lyme. It took weeks before she finally realized, “Oh my God, that’s what I have.”
But even then, she struggled to get a diagnosis — or even get tested. Nevitt didn’t find treatment until she left the state to see a specialist in the Hudson River Valley.
“At that point, I really realized everything that people who have Lyme say is true,” she said. “Something is wrong with the medical community, they just think we’re all crazy.”
One thing that’s common with Lyme patients, Nevitt said, is that at some point, a stressful life event causes their symptoms to get very bad very quickly. She said for a lot of people, it can be something tragic like the loss of a child or a divorce. Nevitt said in her case, it was when her husband, now-Lt. Gov. David Zuckerman, ran for state Senate in 2012, which left her to run their organic farm alone.
Vermont’s Lyme research is 20 years behind, she said.
“Name one disease that they’re relying on that old of research for,” Nevitt said. “If you talk to anybody with Lyme, they’ll tell you the medical community here is woefully far behind.”
Frustrating for doctors and patients
“When we don’t understand the mechanisms for something, it’s very frustrating for patients and very frustrating for us.”– UVM Medical Center Rheumatologist Ralph Budd.
Doctors acknowledge that they don’t have all the answers on Lyme disease.
Ralph Budd, a rheumatologist at UVM Medical Center who specializes in Lyme-linked arthritis, said people are often convinced that if they have symptoms, they also have an ongoing infection, though that often isn’t the case. He said treating symptoms tends to be a very effective option once the infection period has passed.
“When we don’t understand the mechanisms for something, it’s very frustrating for patients and very frustrating for us,” Budd said. “Medicine has many of those — Lyme is not the only one.”
Budd is wary of specialized labs that cater to Lyme testing. He said unlike the tests he uses, which need the Lyme antibodies to develop for six weeks before they are accurate, other labs have faster tests that he says have been proven to return a higher rate of false positives.
“When patients think they have something, and they’re not feeling well, of course they shop around and look for something to help,” Budd said. “But if the lab gives them falsely positive results, that can really do a disservice to the medical community.”
Kwit, of the Vermont Department of Health, echoed this sentiment.
“It is important to correctly diagnose Lyme disease when someone has it. But it is equally important not to misdiagnose someone with Lyme disease when the cause is really something else,” she said.
A misdiagnosis of Lyme disease could lead to a long road of treatment that doesn’t work, and could result in an illness that lasts longer, she said. She urges the use of validated, evidence-based methods to diagnose the disease.
There’s currently a rift in the Lyme community over the best ways to address the disease. Some advocates are looking to guidelines put out by the International Lyme and Associated Diseases Society, which they believe are more accurate ways to test. But those standards are not endorsed by the Centers for Disease Control and are regarded with skepticism by many in the medical community.
Alexis Chesney, a naturopathic Lyme specialist, said the best way to address Lyme is to prevent it.
She pointed out a number of recommendations to help prevent the disease’s spread, including treating clothes with tick repellent, showering within two hours of being outdoors, checking pets to make sure they don’t carry ticks inside, and drying clothes on hot for 10 minutes as soon as you get inside to make sure any ticks — which are often as small as poppy seeds — are gone.
“I would love for people to stop getting tick bites,” Chesney said. “Then we could really solve this tick epidemic.”
_________________
**Comment**
Those getting the rash varies from 25-80% – hardly something to bank on. The myth that everyone gets the “classic” EM rash needs to be dropped like a bad habit.
The skepticism of smaller CLIA-certified labs is unwarranted. They undergo the most strenuous lab requirements and specialize in bacteriology and virology. Lyme has always been a clinical diagnosis.
Being told to “wait and see” after a tick bite is asinine. Insanity is doing the same thing over and over and expecting different results. We all know early treatment is everything – SO, WHY WAIT?
Doctors desperately need to become educated on tick borne illness. And yes, Lyme/MSIDS can cause psychological symptoms: https://madisonarealymesupportgroup.com/2018/08/25/neuropsychiatric-lyme-borreliosis-an-overview-with-a-focus-on-a-specialty-psychiatrists-clinical-practice/
https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/
https://madisonarealymesupportgroup.com/2019/02/16/lyme-is-all-in-your-head-a-wake-up-call-to-mental-health-professionals/
The fact doctors are STILL afraid to treat patients is telling. This is wrong on so many levels and indicates a huge problem: https://madisonarealymesupportgroup.com/2018/12/15/everything-about-lyme-disease-is-steeped-in-controversy-now-some-doctors-are-too-afraid-to-treat-patients/
Do you hear of doctors being afraid to treat diabetes, cancer, or syphilis?
No. Why? Because insurance companies aren’t pulling strings on those diseases.
Managed care is the problem: https://madisonarealymesupportgroup.com/2017/08/19/dr-liegner-guidelines-used-by-managed-care-causing-lyme-deaths/
https://madisonarealymesupportgroup.com/2019/08/01/why-we-need-to-stop-treating-lyme-disease-like-a-typical-infectious-disease/
https://madisonarealymesupportgroup.com/2018/06/14/corruption-human-rights-violations-against-lyme-doctors-scientists-and-parents-now-on-united-nations-record/