Archive for the ‘Viruses’ Category

Bb Can Cause Infectious Myelopathy

https://www.ncbi.nlm.nih.gov/pubmed/29613895
Continuum (Minneap Minn). 2018 Apr;24(2, Spinal Cord Disorders):441-473. doi: 10.1212/CON.0000000000000597.

Infectious Myelopathies.

Grill MF.

Abstract
PURPOSE OF REVIEW:
This article reviews bacterial, viral, fungal, and parasitic pathogens associated with myelopathy. Infectious myelopathies may be due to direct infection or parainfectious autoimmune-mediated mechanisms; this article focuses primarily on the former.
RECENT FINDINGS:
Some microorganisms exhibit neurotropism for the spinal cord (eg, enteroviruses such as poliovirus and flaviviruses such as West Nile virus), while others are more protean in neurologic manifestations (eg, herpesviruses such as varicella-zoster virus), and others are only rarely reported to cause myelopathy (eg, certain fungal and parasitic infections). Individuals who are immunocompromised are at increased risk of disseminated infection to the central nervous system. Within the last few years, an enterovirus D68 outbreak has been associated with cases of acute flaccid paralysis in children, and emerging Zika virus infection has been concurrent with cases of acute flaccid paralysis due to Guillain-Barré syndrome, although cases of myelitis have also been reported. Associated pathogens differ by geographic distribution, with myelopathies related to Borrelia burgdorferi (Lyme disease) and West Nile virus more commonly seen in the United States and parasitic infections encountered more often in Latin America, Southeast Asia, and Africa. Characteristic CSF and MRI patterns have been identified with many of these infections.
SUMMARY:
A myriad of pathogens are associated with infectious myelopathies. Host factors, geographic distribution, clinical features, CSF profiles, and MRI findings can assist in formulating the differential diagnosis and ultimately guide management.

_______________

**Comment**

Myelopathy is a neurologic deficit related to the spinal cord which can be caused by trauma (spinal cord injury) or inflammation (myelitis).  Inflammation can be caused by numerous things including pathogens such as Borrelia burgdorferi (Bb), the causative agent of Lyme Disease, as well as numerous viruses that can also be a part of the Lyme/MSIDS symptom picture which can be transmitted directly from ticks or activated due to the reaction of the body to the tick bite.  Much research is needed in this particular area.

Myelopathy is typically a clinical diagnosis with patients complaining of weakness, clumsiness, muscle atrophy, sensory deficits, bowel/bladder symptoms, sexual dysfunction, altered tons, spasticity, and hyperreflexia among other symptoms.  https://en.wikipedia.org/wiki/Myelopathy  Treatment depends upon the underlying cause.  If infectious, pathogen specific antibiotics, and/or things to reduce inflammation are in order.

Personal response:  While I was not diagnosed with myelopathy specifically, one of my hallmark symptoms was spinal and occipital pain.  After ruling out Chiari:  https://madisonarealymesupportgroup.com/2016/04/02/chiari/ and regularly seeing an upper cervical chiropractor for structural malalignment, MSM helped me tremendously.  Please read about MSM here:  https://madisonarealymesupportgroup.com/2018/03/02/dmso-msm-for-lyme-msids/

Make sure to discuss all treatment options with your health care provider.


Novel Viruses Found in Lone Star, American Dog, & Black Legged Ticks

http://msphere.asm.org/content/3/2/e00614-17

Identification of Novel Viruses in Amblyomma americanum, Dermacentor variabilis, and Ixodes scapularis Ticks

Rafal Tokarz, Stephen Sameroff, Teresa Tagliafierro, Komal Jain, Simon H. Williams, D. Moses Cucura, Ilia Rochlin, Javier Monzon, Giovanna Carpi, Danielle Tufts, Maria Diuk-Wasser, Jory Brinkerhoff, W. Ian Lipkin
James M. Pipas, Editor
DOI: 10.1128/mSphere.00614-17
ABSTRACT

Ticks carry a wide range of known human and animal pathogens and are postulated to carry others with the potential to cause disease. Here we report a discovery effort wherein unbiased high-throughput sequencing was used to characterize the virome of 2,021 ticks, including Ixodes scapularis (n = 1,138), Amblyomma americanum (n = 720), and Dermacentor variabilis (n = 163), collected in New York, Connecticut, and Virginia in 2015 and 2016. We identified 33 viruses, including 24 putative novel viral species. The most frequently detected viruses were phylogenetically related to members of the Bunyaviridae and Rhabdoviridae families, as well as the recently proposed Chuviridae. Our work expands our understanding of tick viromes and underscores the high viral diversity that is present in ticks.

IMPORTANCE The incidence of tick-borne disease is increasing, driven by rapid geographical expansion of ticks and the discovery of new tick-associated pathogens. The examination of the tick microbiome is essential in order to understand the relationship between microbes and their tick hosts and to facilitate the identification of new tick-borne pathogens. Genomic analyses using unbiased high-throughput sequencing platforms have proven valuable for investigations of tick bacterial diversity, but the examination of tick viromes has historically not been well explored. By performing a comprehensive virome analysis of the three primary tick species associated with human disease in the United States, we gained substantial insight into tick virome diversity and can begin to assess a potential role of these viruses in the tick life cycle.

_______________

**Comment**

The article states the high diversity of viruses was not unexpected and that some of these viruses have not been found in vertebrates and are not likely horizontally transmitted but that they are phylogenetically related to human & animal pathogens.  They also state some of the viruses do not replicate within the tick but rather parasitize hosts within the tick such as fungus or nematode.


Interestingly, the black legged tick, normally considered the biggest player in transmitting Lyme Disease, also had three times more viruses than the Lone Star Tick.


ME/CFS Summit – “Test for Lyme”

https://www.medscape.com/viewarticle/893766?nlid=121255_4503&src=wnl_dne_180313_mscpedit&uac=166940EN&impID=1580105&faf=1#vp_1

Much Can Be Done to Ease ‘Chronic Fatigue Syndrome’ Symptoms

Miriam E. Tucker, March 12, 2018

SALT LAKE CITY, UT — The illness commonly known as chronic fatigue syndrome is complex and currently incurable, but clinicians can still do a great deal to manage symptoms and improve patients’ quality of life, experts agree.

In a 2-day meeting held March 2 and 3, 2018, specialists in the condition, now termed myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), met to discuss their assessment and treatment approaches. The aim of the “summit,” organized by Lucinda Bateman, MD, and held at her Bateman-Horne Center facility here, was to initiate development of expert consensus ME/CFS guidance for primary care and specialist clinicians, and to identify research priorities to address major knowledge gaps.

“One of the messages I’d like to send to physicians is not to have an all-or-nothing approach to this illness, but to break it down into its parts, and see what you can get hold of with the history, objective markers, and clinical intuition. And then, it’s not unreasonable to try some things that are not harmful or expensive,” Bateman told Medscape Medical News.

The 13 panelists, who hail from primary care, infectious disease, immunology, neurology, endocrinology, pediatrics, and integrative medicine, discussed and prioritized elements of history-taking, physical exam findings, diagnostic tests, and treatment approaches for each of the illness’ major components. The core features include fatigue, impaired function, postexertional malaise, sleep dysregulation, neurocognitive impairment, and orthostatic intolerance; other commonly reported features are widespread pain, immune dysregulation, and infection.

Panel members focused on approaches they have found to be most helpful and that can be accomplished in primary care, as well as more advanced modalities that would be more feasible in specialty practices.

Assessing the Illness

The document the group produces will endorse the 2015 Institute of Medicine diagnostic criteria, which defineME/CFS as 6 months of unexplained fatigue with substantial functional impairment, postexertional malaise, unrefreshing sleep, and either cognitive dysfunction or orthostatic intolerance. The symptoms must be moderate to severe and present at least 50% of the time. (Five summit participants, including Bateman, were on the writing committee for that report, and three others served as reviewers for it.)

Assessing functional capacity is key, Bateman said.

“It’s an illness that impairs people’s ability to function in their daily lives. Clinicians need to ask about function, and what happens when people exert themselves both physically and cognitively.”

One revealing question is, “What would you be doing now if you weren’t ill?” Typically, as opposed to depressed patients, those with ME/CFS will have a laundry list. “Our patients are trapped in bodies that don’t work,” Bateman said. “They’re desperate to do more.”

Laboratory tests such as complete blood count with differential, complete metabolic panel, erythrocyte sedimentation rate and C-reactive protein, antinuclear antibody, rheumatoid factor, lipid panel, thyroid-stimulating hormone, and celiac screen should all be performed to investigate symptoms, but are often unhelpful. (As reported previously by Medscape Medical News, evidence suggests that the inflammatory cytokines involved in ME/CFS are different from those that induce C-reactive protein.)

In contrast, assessments that often yield valuable information in patients with ME/CFS include evaluation for orthostatic intolerance and autonomic dysregulation (ideally via tilt-table, but also can be accomplished with the 10-minute “Lean” test), and laboratory tests for Lyme immunoglobulin G (IgG) and IgM;lymphocyte subsets; IgG subclasses; Epstein-Barr virus, including early antigen antibody; herpes viruses; urine or serum markers of mast cell activation syndrome; small intestinal bacterial overgrowth; and natural killer cell function (almost universally low in patients with ME/CFS).

Brain imaging with magnetic resonance imaging or electroencephalography may be indicated in patients who exhibit “brain fog,” headaches, or other neurocognitive symptoms.

“A lot of the testing we do is the differential diagnosis, and we’re looking for comorbid conditions, treatment targets, and subgroups, like people with [small intestinal bacterial overgrowth] or mast cell activation. In the clinical setting, we don’t have to make sense of it all. We just have to identify it, and see if the patient responds to treatment,” Bateman said.
_______________

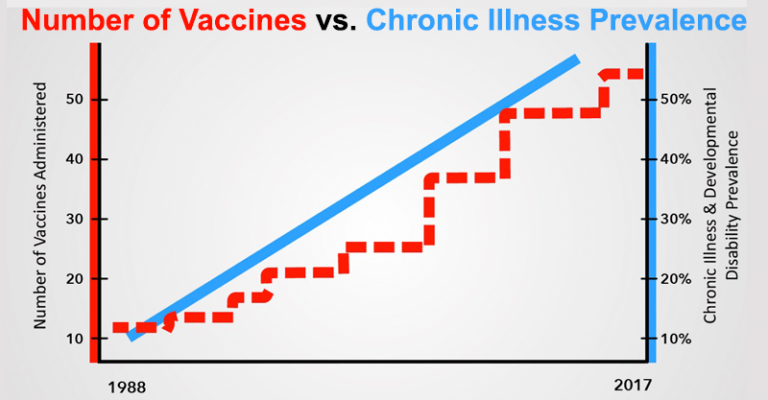
Congress Receives Vaccine Safety Project Details Since the CDC & FDA Ignore Their Own Data and Proclaim Vaccines Do Not Cause Autism

https://worldmercuryproject.org/news/congress-gets-vaccine-safety-project-details-including-actions-needed-for-sound-science-and-transparency/

Congress Receives Vaccine Safety Project Details Including Actions Needed for Sound Science and Transparency


 Approx. 9 Min.

Vaccine Safety Project Trailer

Since the FDA considers vaccines to be “biologics” not drugs, they have the capacity to fast track them without mandating rigorous studies as drugs must go through.

This short informative video shows exactly how vaccines are not rigorously studied with any sort of sincere science.

According to HHS’s own calculations, if they were able to capture ALL adverse events, they state that nearly 6 MILLION Americans would be adversely affected every year by vaccines if all of them were reported to the current Vaccine Adverse Events Reporting System (VAERS).

The committee overseeing vaccine safety should be absolutely free of any conflicts of interest, particularly the pharmaceutical industry, yet the opposite is true.

A new investigation in 2009 found that:

  • CDC has a systemic lack of oversight of the ethics program.
  • 97% of committee members’ conflict disclosures had omissions.
  • 58% had at least one unidentified potential conflict of interest.
  • CDC & FDA scientists receive royalties of $150K per year on vaccines they develop.

Looking at the IOM 700 page report on DTap, the conclusion reads,

“The evidence is inadequate to accept or reject a causal relationship between diphtheria toxoid-, tetanus toxoid-, or acellular pertussis-containing vaccine and autism.”

What this means is they claim they couldn’t find any study on the relationship between Dtap and autism.  But, in fact they acknowledge in the first paragraph that there is one study that does show a causal relationship between Dtap and autism, but they reject it because it provides data from passive surveillance (VAERS) that lacked a comparison of an unvaccinated population.

So while the CDC website cites the 2011 Institute of Medicine study that “vaccines do not cause autism,” they seem to be counting on people not reading the 700+ page report. Anyone who does can find that the researchers behind this study ignored existing research showing a correlation between vaccines and autism.

Rather than doing their due diligence (scientific studies) they just proclaim vaccines do not cause autism.

For more:  https://madisonarealymesupportgroup.com/2018/03/01/vaccines-could-contribute-to-disease-epidemics-due-to-retrovirus-contamination/

https://madisonarealymesupportgroup.com/2017/12/04/ingredients-in-kinrix-a-dtap-ipv-vaccine/

https://madisonarealymesupportgroup.com/2017/10/04/pharma-using-scare-tactics-over-pertussis-vaccine-failure/

https://madisonarealymesupportgroup.com/2017/09/21/aluminum-flawed-assumptions-fueling-autoimmune-disease-and-lyme/

Vaccines have been found to activate latent Lyme/MSIDS infections: https://madisonarealymesupportgroup.com/2017/12/02/scottish-doctor-gives-insight-on-lyme-msids/ (Please read comment section after article for more links)

https://madisonarealymesupportgroup.com/2016/04/24/gardasil-and-bartonella/ Asymptomatic girls after receiving Gardasil activated dormant Bartonella which was confirmed by testing.

https://madisonarealymesupportgroup.com/2018/01/28/the-secret-x-files-the-untold-history-of-the-lymerix-vaccine/


PCR of Skin Infections With Eschar on Travelers – Rickettsia Most Detected

https://www.ncbi.nlm.nih.gov/m/pubmed/29501703/

Seek and Find! PCR analyses of skin infections in West-European travelers returning from abroad with an eschar.

 Travel Med Infect Dis. 2018.

Abstract

BACKGROUND: Skin infections are among the leading causes of diseases in travelers. Diagnosing pathogens could be difficult.

METHOD: We applied molecular assays for the diagnostic of a large collection of skin biopsies and swabs from travelers with suspected skin infections. All samples were tested by qPCR for Coxiella burnetti, Bartonella sp., Rickettsia sp., Borrelia sp., Ehrlichia sp., Tropheryma whipplei, Francisella tularensis, Mycobacteria sp., Staphylococcus aureus, Streptococcus pyogenes, Leishmania spp., Ortho poxvirus and Para poxvirus and then screened for the presence of bacteria by PCR amplification and sequencing, targeting the 16S rRNA gene.

RESULTS: From January 2009 to January 2017, 100 international travelers presenting with a suspected skin infection were enrolled. We detected 51 patients with an identified pathogen on skin samples. Travelers presenting with eschars were more likely to have a positive PCR sample (n = 44/76, 57.9%) compared to other patients (n = 7/24, 29.2%). Spotted fever group Rickettsia (n = 28) was the most frequently detected pathogens (19 R. africae, 6 R. conorii, 3 R. mongolitimonae); S. aureus were detected in 11 patients; S. pyogenes in 3; Leishmania sp.; M. leprae and B. henselae in 1 patient, respectively.

CONCLUSION: By targeting the most commonly encountered causative agents of travel-related skin infections, our strategy provides a sensitive and rapid diagnostic method.