I-Team Deaths Incorrectly Attributed to COVID-19 in Palm Beach County
More questions about the accuracy of the [COVID-19] death count after the CBS12 News I-Team uncovers several cases of people listed as COVID deaths but clearly died of something else.
A 90-year-old man who fell and died from complications of a hip fracture.
A 60-year-old man dead from a gunshot wound to the head.
These are some of the deaths in Palm Beach County recently and incorrectly labeled as COVID deaths in medical examiner records.
…more than 600,000 Tricare users in the military health system’s East Region were asked to consider donating blood for research based on their supposed status as COVID-19 “survivors,” Military.com reported last week. As noted in the report, “31,000 persons affiliated with the U.S. military have been diagnosed with the coronavirus,” showing a clear error in the mass email.
Errors by other health care entities have likewise caused confusion at times about individuals’ COVID-19 status as well as infection rates.
Covid-19 Data Reporting System Gets Off to Rocky Start
New data system run by Health and Human Services faces delays, quality-control issues
By Robbie Whelan
Public release of hospital data about the coronavirus pandemic has slowed to a crawl, one month after the federal government ordered states to report it directly to the Department of Health and Human Services and bypass the Centers for Disease Control and Prevention. (See link for article)
California Public Health Director Suddenly Quits After Massive Virus Data Error Discovered
The director of the California Department of Public Health has abruptly resigned just days after the discovery of a computer system failure that resulted in the massive undercounting of COVID-19 cases.
Dr. Sonia Angell who had been in the position for less than a year (and had previously served as deputy commissioner for prevention and primary care at the New York City Department of Health and Mental Hygiene from 2014 to 2019) reportedly resigned via an email sent to the California Health and Human Services Agency. (See link for article)
NURSING HOMES SHOCKED AT ‘INSANELY WRONG’ CMS DATA ON COVID-19
— ONE FACILITY SUPPOSEDLY HAD EIGHT CORONAVIRUS DEATHS FOR EACH BED
by Cheryl Clark,Contributing Writer, MedPage TodayJune 9, 2020
When the administrator of the Saugus Rehab and Nursing Center in Saugus, Massachusetts, heard that a new Medicare website reported her facility had 794 confirmed cases of COVID-19 — the second highest in the country — and 281 cases among staff, she gasped.
“Oh my God. Where are they getting those numbers from?” said Josephine Ajayi. “That doesn’t make any sense.”
Those weren’t the numbers that her facility reported to the CDC’s National Healthcare Safety Network, under new rules from the Centers for Medicare & Medicaid Services (CMS), she said. (Please see link for article)
WATERTOWN — In the era of COVID-19, with the world preoccupied, it can be easy to overlook other more common diseases such as Lyme disease. Because both COVID and Lyme are flu-like and share some similar symptoms, one can easily be mistaken for the other in the beginning stages of the diseases.
“At the beginning, it might not be clear which one is what,” said Marylene J. Duah, MD, of the Infectious Disease department at Samaritan Medical Center. “And now everybody thinks everything’s COVID, so my knee jerk response would be first test for COVID to get it out of the way.”
COVID symptoms differ widely, but the most common indicators are fever, muscle or body aches, headache, shortness of breath, nausea, and vomiting. According to the CDC, symptoms appear two to 14 days after exposure to the virus. (See link for article)
______________________
**Comment**
Important quote:
“I actually saw a patient in the hospital and they tested him twice for COVID,” Dr. Duah said. “He was hospitalized for a week and nobody tested for Lyme, he sounded more Lyme than any COVID symptoms, he had no pulmonary symptoms, and nobody tested him for Lyme until I saw him. Patients and doctors are panicked so much about COVID that it takes over your thinking, COVID has taken over our world.”
And this is a problem. Not everything is COVID.
Notice that they push the anti-viral Remdesivir. Not a surprise. It’s their lucrative baby they want in the forefront, while they refuse to mention inexpensive treatments that are working (The media is complicit in the spinning of the COVID narrative – even regarding drugs and treatements):
And while doxycycline is a great front-line drug for Lyme – many patients are coinfected with other things. Regarding shortness of breath and a cough – this can happen with Lyme/MSIDS as well. Babesia can cause this as well as other coinfections.
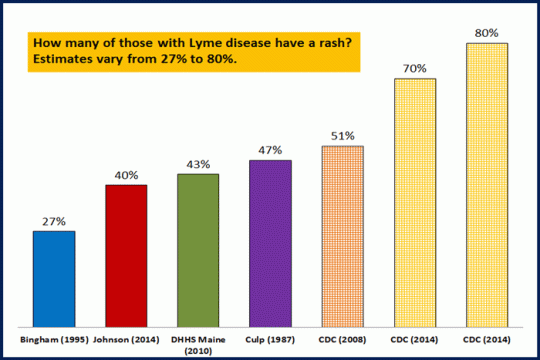
Regarding the figure that 20% don’t get the EM rash, I’ve written about before but this graph says it all. The rash is highly variable and if you have it – you HAVE Lyme, but if you don’t have it, you could still have Lyme. Way more than 20% don’t see it:
Nearly 11% of American adults seriously considered suicide this June, according to CDC data.
Among 5,470 people surveyed in the last week of June:
30.9% reported symptoms of an anxiety or a depressive disorder
25.3% reported a traumatic or stressor-related disorder (TSRD)
13.3% said they were using substances to cope with the pandemic’s stressors, said Rashon Lane, MA, of the CDC’s COVID-19 Response Team
10.7% reported seriously considering suicide in the prior month, more than double the rate reported in a 2018 CDC survey, the researchers wrote in the agency’s Morbidity and Mortality Weekly Report.
Specifically, the risk for suicidal ideation was elevated among respondents:
between ages 18 and 25 (25.5%)
Hispanic respondents (18.6%)
Black respondents (15.1%)
unpaid adult caregivers (30.7%)
essential workers (21.7%)
The “markedly” high rates of mental and behavioral health conditions show the “broad impact of the pandemic and the need to prevent and treat these conditions,” the authors wrote, adding that interventions to reduce these numbers should target financial strain, racial discrimination, social connectedness, and community supports for patients considering suicide.
However, suicidal ideation should not be seen as an inevitability from this data, commented Jessica Gold, MD, MS, of the department of psychiatry at Washington University in St. Louis.
Instead, it should be seen as “a call for help,” and motivate the government, employers, families, and individuals to focus on the mental health needs of the population, Gold said.
“This study says we need help, especially in certain populations, and mental health needs to be a focus of all of our conversations,” she told MedPage Today in an email.
The web-based survey used the Patient Health Questionnaire to assess depression and anxiety symptoms and the Impact of Event Scale to assess pandemic-related TSRD. Substance use and suicidal ideation were self-reported.
Altogether, 40.9% reported having at least one mental or behavioral health condition. That proportion was higher among the following groups:
Young adults ages 18-24 (74.9%) and 25-44 (51.9%)
Hispanic respondents (52.1%)
Individuals who did not receive a high school diploma (66.2%)
Essential workers (54%)
Unpaid adult caregivers (66.6%)
Individuals with baseline mental health conditions (68.8%-88%)
Compared with CDC data from the second quarter of 2019, adults in this survey reported three times the rate of anxiety symptoms (25.5% vs 8.1%) and four times the rate of depression symptoms (24.3% vs 6.5%), the researchers stated. Overall, young people ages 18-24 had a far greater risk of considering suicide in the past 30 days than adults ages 45-64 (6.66, 95% CI 5.115-8.61) and adults ages 65 and up (12.51, 95% CI 7.88-19.86).
Hispanic and Black individuals were also at an elevated risk for anxiety or depressive symptoms, substance use, and suicidal ideation in the past 30 days compared with white respondents.
In an analysis of 1,497 respondents who also completed surveys in April and May, unpaid adult caregivers were more likely to start using substances to cope in June than they were in May (adjusted odds ratio 3.33, 95% CI1.75-6.31, P<0.001), and more likely to report new suicidal ideation in June (aOR 3.03,95% CI 1.20-7.63, P=0.019).
The survey relied on self-reported answers for some classifications and was web-based, both of which are limitations, Lane and co-authors noted.
If you or someone you know is considering suicide, call the National Suicide Prevention Lifeline at 1-800-273-8255.
International Pharmaceuticals Expert Exposes Pandemic Fakery!
Published on
Written by John O’Sullivan
In a scathing assessment of governmental responses to the COVID-19 pandemic a respected former pharmaceutical assessor for Health Canada condemns systemic “lies”about antibody testing which, he says, “lacks scientific validity.”
Saeed Qureshi, Ph.D. is a top pharmaceuticals expert with over 30 years in the industry. He conducted hands-on and multi-disciplinary laboratory research for regulatory assessment purposes while working with Health Canada.
Heaping particular criticism on the FDA approved under Emergency Use Authorization or EUA, Dr Qureshi condemns the testing kits widely used as ineffective and “such tests should be avoided in making predictions or projections about the infection and its spread. It certainly is a false science.”
We cite sections of Dr Qureshi’s findings below:
“Considering the statements below, from a randomly selected fact sheet FDA approved under Emergency Use Authorization or EUA, the current antibody testing lacks scientific validity. This is really sad that such tests [kits] are being promoted or used to establish COVID-19 [1]. As noted below the test monitors protein levels commonly known as [IgM, IgA and IgG] not specifically COVID-19. Logically data obtained from such tests should be avoided in making predictions or projections about the infection and its spread. It certainly is a false science.
“A positive result with VITROS Immunodiagnostic Products Anti-SARS-CoV-2 Total Reagent Pack test may not mean that an individual’s current symptoms are due to COVID-19 infection.”
2. “However, a negative result does not rule out COVID-19.”
3. “The absolute sensitivity of the VITROS Immunodiagnostic Products Anti-SARS-CoV-2 Total Reagent Pack test is unknown.”
4. FDA statement [2] “This limits the test’s effectiveness for diagnosing COVID-19 and why it should not be used as the sole basis to diagnose COVID-19.”
In addition, if vaccines would be developed based on such antibody tests, which does not appear to be sufficiently validated as noted above, then how reliable and valid vaccines would be? Please be cautious with claims in this regard.
Do FDA and USP lie? Of course, all the time!
For example:
FDA claims that it establishes and monitors quality of pharmaceutical products such as tablet and capsule. A lie – FDA neither defines quality of the products nor its measurable parameter hence it does not, or cannot, determine quality of the products.
FDA claims that it establishes safety and efficacy (as well as quality) of pharmaceutical products using valid clinical testing (e.g. bioequivalence assessment) and in vitro (drug dissolution) testing using USP apparatuses. A lie – these tests, along with associated testers, have never been validated for the intended purpose. In fact, these tests have been shown to be scientifically invalid and irrelevant for their intended purpose.
USP claims that it provides reference standards for establishing quality of the pharmaceutical products such as tablets and capsules. A lie – USP never provides reference standards for any product. It provides powder or liquid samples of pure chemical compounds, not the products which patients use, however falsely promotes as reference standards of medicines.
USP claims that it provides a valid analytical test for the assessment drug release characteristics of the products for establishing and monitoring quality of the products. A lie – the test has never been validated for the intended purpose. The test cannot determine drug dissolution/release characteristics of any product. It has been shown experimentally that the test provides irrelevant and highly unpredictable results/data with no relevance to product quality.
For more examples please visit here. Manufacturers and patients should be cautious in accepting such claims from FDA and USP as well as other national and international authorities which often follow FDA/USP claims and guidances.
Please consider accepting the Citizen Petition (under review with FDA for more than a year and a half, link) for addressing the underlying lies concerning products development, manufacturing and their regulatory approval.
Can we say?
Flu came and gone!
Why it was called a pandemic – not clear
Discredited the bench top science – as disease state monitored with charts and their shapes (humpy or dumpy) with protocol/testing developed on the fly
Discredited the medicines approval system with the approval of medicines without requiring established protocols
Treatments could be suggested and implemented without having knowledge or expertise in the area of medicine.
Exposed the great weakness, perhaps more accurately ignorance, of “science” at the authorities!
The unfortunate situation created by this Coronavirus pandemic is providing a serious opportunity for reassessing the current regulatory approaches in pharmaceutical products development as well as their manufacturing so that in future such irrelevant discussion can be avoided and patients can have access to modern and multiple options to treat ailments. Hopefully in the future patients will be treated with well-established products rather than products developed on the fly or with the use of disposable gowns, masks, washing hands and/or staying home policy which certainly are not the treatments – patients expect and deserve something better from us as scientists, physicians and regulators. Follow the link for complete article (link)
(2) Authorities (including FDA) and pharmacopeias (including USP) never establish quality of products!
Reasons:
(1) They do not define quality of the products, hence it cannot be measured and/or established (link).
(2) Suggested methods and procedures lack scientifically relevancy and validity (link)
(3) GMP practices, including inspections, are about operation of manufacturing not per se reflection of products quality (link).
(3) Is Coronavirus really causing abnormally higher number of deaths?
Mortality in the United States, 2018 (as of January 2020, link).
“The age-adjusted death rate decreased by 1.1{154653b9ea5f83bbbf00f55de12e21cba2da5b4b158a426ee0e27ae0c1b44117} from 731.9 deaths per 100,000 standard population in 2017 to 723.6 in 2018.” i.e. death rate is about 0.7236{154653b9ea5f83bbbf00f55de12e21cba2da5b4b158a426ee0e27ae0c1b44117}
For the USA, having population of 331 million (link), normal/standard death (attrition) rate should be 199,593 deaths/month. Now compare this number with the reported number of deaths caused by Coronavirus pandemic, which are 21,435 in about a month’s time as of April 12, 2020 (link) which is far less than normal/standard death (attrition) rate.
The death rate, therefore, does not appear to support the thesis that the pandemic is killing people with abnormally high numbers.
About the author: Dr. Qureshi gained extensive (30+ year) experience in conducting hands-on and multi-disciplinary laboratory research in pharmaceutical areas for regulatory assessment purposes while working with Health Canada.
He is an internationally recognised expert in the areas of pharmacokinetics, biopharmaceutics, drug dissolution testing, analytical chemistry as related to characterization of pharmaceuticals, in particular, based on in vitro (dissolution) and bioavailability/bioequivalence (humans and animals) assessments.
At present, Dr. Qureshi provides teaching, training and consulting services, in the area of his expertise as noted above, for improved pharmaceutical products development and assessments. Dr. Qureshi can be reached by email (principal@pharmacomechanics.com) or Tel (+1 613 797 9815)
PRINCIPIA SCIENTIFIC INTERNATIONAL, legally registered in the UK as a company incorporated for charitable purposes. Head Office: 27 Old Gloucester Street, London WC1N 3AX.
Covid-19 Patients No Longer Need Tests to End Isolation
Under new guidelines from the C.D.C., recovering coronavirus patients should be free to resume normal activity after 10 days, if they have no fever or other symptoms.
Coronavirus testing delays of up to two weeks persist in parts of the country.Credit…Max Whittaker for The New York Times
Most Americans recovering from Covid-19 can come out of isolation without further testing to show they no longer carry the coronavirus, federal health officials said on Wednesday.
Instead, patients may be judged to have recovered if 10 days have passed since they first felt ill; they no longer have any symptoms, such as shortness of breath or diarrhea; and they have not had a fever for 24 hours without taking fever-reducing medicine.
The new recommendations are not rules but guidelines intended for patients, doctors and health policymakers. The revisions should help relieve the burden on the country’s testing system, the Centers for Disease Control and Prevention said. (See link for article)
____________________
**Comment**
Ha ha, ha…..yeah right.…Lyme/MSIDS patients know all about “guidelines” that rule the land like the Iron Curtain.