Archive for the ‘Viruses’ Category

Vaccine Studies: Flu Vaccine Increases Risk of Pneumonia & Death and There’s no Science Behind School Vaccine Mandates

https://www.thefocalpoints.com/p/breaking-223-million-person-study?

BREAKING: 2.23 Million-Person Study Finds Pneumococcal Vaccines Increase Risk of Pneumonia and Death

The vaccines given to nearly every U.S. child and senior were linked to higher pneumonia and death rates in one of the largest real-world studies ever conducted.

For decades, U.S. and European health authorities have promoted pneumococcal vaccination as an “essential” tool to prevent serious bacterial pneumonia, meningitis, and sepsis caused by Streptococcus pneumoniae.

In the United States, the CDC’s Advisory Committee on Immunization Practices (ACIP) currently recommends:

  • Infants and children <5 years: a 4-dose series of a pneumococcal conjugate vaccine—PCV15 or PCV20—at 2, 4, 6, and 12–15 months.
  • Adults ≥50 years (PCV-naïve or unknown history): one dose of a PCV—PCV15, PCV20, or PCV21. If PCV15 is used, give PPSV23 one year later (minimum 8 weeks for certain high-risk conditions).
These vaccines are given to tens of millions of Americans every year.

Now, a landmark population-based study published in BMC Infectious Diseases has shattered the rationale for current pneumococcal conjugate vaccine (PCV) recommendations. Analyzing outcomes among 2,234,003 adults aged 50 and older in Catalonia, Spain, the authors found that recipients of both PCV13 and PPSV23 were significantly more likely to be hospitalized for pneumonia and more likely to die from pneumonia-related causes compared to their unvaccinated counterparts—even after adjusting for age, sex, comorbidities, and influenza vaccination status.  (See link for article)

BTW: This is not new info:  https://madisonarealymesupportgroup.com/2020/11/10/flu-vaccine-education/

_________________

https://pubmed.ncbi.nlm.nih.gov/29061349/

Patterns of childhood immunization and all-cause mortality

Abstract

Background: Evidence supports the safety of the recommended childhood immunization schedule as a whole. However, additional research is warranted as parents’ refusing or delaying vaccinations has increased in recent years. All-cause mortality has been identified as a priority outcome to study in the context of the recommended immunization schedule.

Methods: We included children born January 1, 2004 through December 31, 2009, enrolled in the Vaccine Safety Datalink (VSD) from birth through 18 months of age. We examined vaccination patterns during the first 18 months of life among 8 vaccines, and identified deaths occurring between 19 and 48 months of age. We excluded children with complex chronic conditions, contraindications to vaccination, and deaths due to injuries, congenital anomalies, or diseases with onset prior to 19 months of age. We calculated mortality rates among children with different patterns of immunization, and incidence rate ratios (IRR) using the Cox proportional hazards model for children vaccinated according to the schedule versus undervaccinated children, adjusting for outpatient healthcare utilization, influenza vaccination, sex, and VSD site.

Results: Among 312,388 children in the study, 199,661 (64%) were vaccinated according to the schedule, and 112,727 (36%) were delayed or not vaccinated for at least one vaccine dose. Of 18 deaths eligible for analysis, 11 occurred in children following the schedule (2.28 per 100,000 person-years), and seven occurred in undervaccinated children (2.57 per 100,000 person-years). Mortality rates among children following the schedule were not significantly different from those of undervaccinated children when excluding deaths with unknown causes (IRR = 1.29, 95% CI = 0.33-4.99), as well as when including deaths with unknown causes (IRR = 0.84, 95% CI = 0.32-2.99).

Conclusion: Although there were few deaths, our results do not indicate a difference in risk of all-cause mortality among fully vaccinated versus undervaccinated children. Our findings support the safety of the currently recommended immunization schedule with regard to all-cause mortality.

And I agree entirely with Steve Kirsch’s statement:

“I bet those CDC authors cut the time period short to just before things were starting to get interesting.”

This proves school ‘vaccine’ mandates are unfounded and unscientific.

For more:

The Spike Protein and the Spirochete: SARS-CoV-2 Infections, Reinfections and Exposures to its Spike Protein May Effectively Simulate “Lyme Disease”

https://wmcresearch.substack.com/p/the-spike-protein-and-the-spirochete?

Just like the Lyme Disease pathogen, the Spike Protein invades organs through – the endothelium – with remarkably similar results.

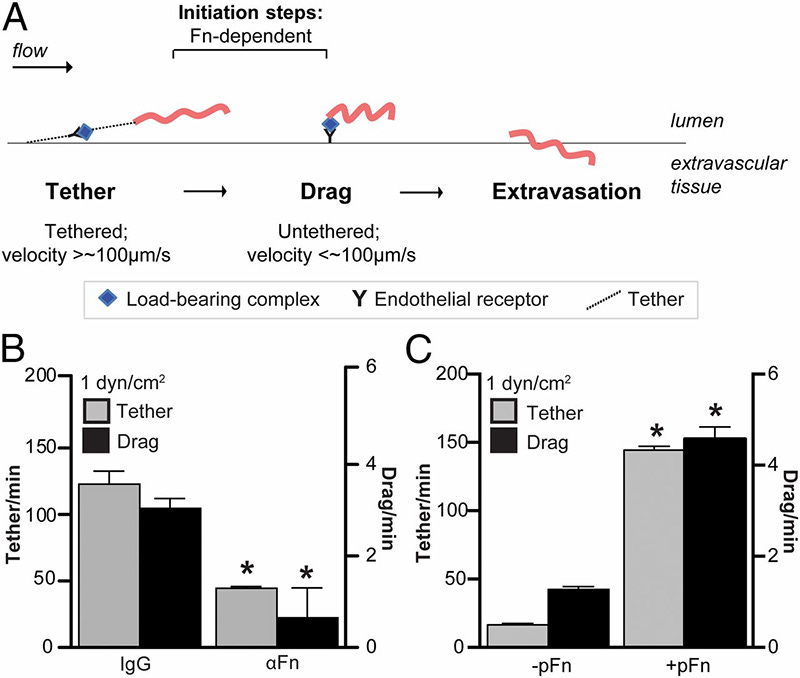
Dependence of B. burgdorferi–endothelial interactions under physiological shear stress on pFn. (A) Schematic illustrating initiation steps (tethering, dragging) of the B. burgdorferi–endothelial interaction cascade leading to bacterial transmigration across endothelial barriers into extravascular tissues. Tethering bacteria anchor to endothelial surfaces via tethers, pause repeatedly as they move over endothelial surfaces, but move faster than 100 μm⋅s−1. Dragging bacteria move more slowly (<100 μm⋅s−1) and are untethered. Both tethering and dragging are Fn-dependent in mouse PCVs (18). There are reduced numbers of B. burgdorferi tethering and dragging on primary human endothelial monolayers in flow chambers at typical PCV shear stress (1 dyn/cm2) following treatment with polyclonal anti-Fn antiserum (B) and depletion of pFn from serum in bacterial cultivation medium (C). Numbers of tethering and dragging GFP-expressing B. burgdorferi (strain GCB966) in the presence of nonspecific IgGs or polyclonal αFn IgGs were measured by manual counting. In B, GCB966 was cultivated in the presence of mouse blood before imaging. In C, bacteria were cultivated without mouse blood to eliminate all sources of pFn. In C, −pFn indicates pFn-depleted growth conditions; for +pFn samples, bacteria grown under pFn-depleted conditions were supplemented with human pFn (+pFn) to the concentration present in blood (0.3 mg/mL) before imaging. Summary values: mean ± SEM. Statistics: two-way ANOVA, Holm–Sidak posttest (n = 3 independent bacterial and endothelial cultures per group). *P < 0.05 vs. IgG (B) or −pFn (C) within the same interaction type.

We can learn much about the Spike Protein by studying Lyme Disease. It is remarkable how much commonality Spike Protein-related disease and Lyme Disease share. Let’s start with infection. For Lyme Disease, it is through a tick bite. For the Spike Protein, it is through the respiratory tract (directly into the bloodstream, too, unfortunately). For example, we can edit Lyme Disease pathogenesis to mirror the Spike Protein’s.  (See link for article)

______________

**Comment**

This is the first time I’ve seen Lyme compared to the spike protein; however, when you study how both disseminate in the body, there are similarities – not to mention how ‘the powers that be’ have treated both diseases (censorship, denial of effective treatment, the push for a ‘vaccine,’ etc.)

Just today, a study came out stating:

Our findings reveal that the first contact of B. burgdorferi and blood vessels is not random but involves close interactions with pericytes. We also capture the infiltration of immune cells in the skin and their interactions with invading bacteria. Altogether, these observations suggest that Borrelia strategically targets vascular regions with lower mechanical resistance to breach the endothelial barrier, thereby enhancing its dissemination.

In other words, Bb has tricks up its sleeve.  But we always knew that.

In the Discussion section the authors admit:

Due to the wave-like morphology and typically low abundance of pathogenic spirochetes in tissues, it is challenging to accurately identify the bacteria from random 2D electron microscopy projections. To reliably confirm the presence of Bb, one must either employ a correlative approach35 or conduct a complete 3D reconstruction of the spirochete.

And herein lies the problem: researchers are not using advanced enough techniques to find these elusive organisms causing so much damage.

The authors also state they found Bb in collagen bundles which provide natural pathways for migration through connective tissue which then gets degraded in later disease stages, but that by:

avoiding overt destruction of host tissues, Bb may reduce the likelihood of triggering host defense mechanisms that could thwart its spread.

So, no, you are not going nuts.
You are infected with a sneaky organism with an affinity for skin, bones, tissues, and tendons and yes, you will painfully feel it. 

Further, the study demonstrates a sort of intelligence to Bb:

The initial phase likely represents a “probing” stage during which the bacteria survey the microenvironment. At this stage, Bb interacts with the vasculature using a smaller area of its cell body, without penetrating either the PCs, ECs, or the surrounding BM (Fig. 2). This is followed by a second phase characterized by a gradual increase in the number of endothelial contact sites, suggesting a transition from transient adhesion to a more stable interaction prior to traversal.

You can read my comments to the top article by going to the top link.

Inside the Vaccine Trials

http://  Approx. 1 hour 10 Min

Inside the Vaccine Trials

7/30/25

This film offers an intimate look into the lives of vaccine trial volunteers. These individuals came forward with hope and trust, only to encounter serious, lasting health complications.

www.vaccinetrialstories.com

Go to link for transcript

_______________

**Comment**

I don’t think the word ‘vaccine’ should be used in the title for this piece because it’s an experimental gene therapy injection in an ongoing clinical trial.  It is not a vaccine at all.  The only reason it can legally receive that title is because the CDC changed the definition of a vaccine so mRNA would fit.

Again, people receive different things.  Some one dose, some another dose, and some don’t get the mRNA at all but a placebo.  ‘The powers that be’ were and continue to be dishonest and have led people to believe everyone is getting an effective vaccine.

But the Covid injection is ineffective, doesn’t stop infection or transmission, but actually increases your risk of infection, myocarditis, blood clots, cancer, sets you up for prion disease, and causes more harm than good.

 It’s all a crock.
Buyer beware.

For more:

SOT For Lyme: Experimental, Expensive, but Full of Potential

https://www.lymedisease.org/sot-lyme-treatment/

SOT therapy for Lyme is experimental, expensive—and full of potential.

Oct. 3, 2025

Part One of a two-part series.

By Maria Marian, ND, MSE

For many people facing chronic infections such as Lyme disease, Epstein–Barr virus (EBV), herpes simplex virus (HSV-1 and HSV-2), or cytomegalovirus (CMV), the journey can be long and frustrating.

Antibiotics, antivirals, herbal therapies, and IV treatments may help initially, yet symptoms often persist or recur. This has led both patients and clinicians to explore innovative therapies that move beyond conventional antimicrobial approaches.

One such emerging option is Supportive Oligonucleotide Therapy (SOT), also referred to as antisense oligonucleotide therapy. Although still considered experimental in the context of Lyme and chronic viral infections, SOT builds upon decades of genetic medicine research and has even reached FDA approval in select infectious and cancer-related applications.

What is SOT?

At its core, SOT is a gene-silencing technique. Scientists design a short synthetic strand of nucleic acid (called an oligonucleotide) that binds to a very specific piece of genetic code inside the pathogen—such as Borrelia burgdorferi (the bacterium that causes Lyme disease) or EBV.

When this oligonucleotide binds, it blocks the pathogen’s ability to produce a protein essential for replication or metabolism. In simple terms, it’s like removing a crucial page from the pathogen’s instruction manual. Without that instruction, the organism can’t replicate efficiently, and its numbers gradually decline.

This strategy falls under the larger field of “antisense therapy.” The term comes from the fact that these therapeutic molecules bind to the “sense” strand of RNA or DNA, neutralizing its ability to produce proteins.

Reference: Crooke ST. Antisense Drug Technology: Principles, Strategies, and Applications. CRC Press; 2008.

How the therapy works

The process of SOT treatment involves several carefully orchestrated steps:

  1. Blood Draw & Testing – A blood sample is taken and analyzed using molecular techniques such as PCR to identify which pathogens are active.
  2. Custom Design – A laboratory designs a patient-specific oligonucleotide tailored to silence a genetic target in that pathogen. Newer approaches like QRE-strain technology (Quasispecies Resistant Engineered strain) aim to account for genetic variations in pathogens, ensuring the oligonucleotide is effective across slightly different strains.
  3. Infusion – Once prepared, the oligonucleotide solution is returned to the clinic and administered as a single intravenous infusion.
  4. Ongoing Action – Unlike antibiotics or antivirals that are metabolized quickly, SOT molecules remain active for months (often up to six months), continuously working “day and night” to suppress pathogen replication.

The Science Behind It

Antisense oligonucleotides are not a new idea. In fact, the first FDA-approved antisense therapy, fomivirsen (Vitravene), was approved in 1998 to treat CMV retinitis in immunocompromised patients【PMID: 9815174】. Since then, several antisense and RNA-based drugs have reached the market for conditions ranging from high cholesterol (mipomersen) to spinal muscular atrophy (nusinersen)【PMID: 29191460】.

In infectious disease specifically:

  • CMV: Fomivirsen demonstrated that gene-silencing therapy can effectively reduce viral activity in humans.
  • Herpesviruses: Preclinical studies have shown that antisense molecules can block HSV and EBV replication in vitro【PMID: 19920191】.
  • Lyme disease: Pilot clinical data suggest that one or two SOT infusions can lead to statistically significant reductions in Borrelia burgdorferi DNA levels detected by PCR. For viral infections, two or three treatments may be needed to achieve measurable decreases.

While more research is essential, these early findings provide a rationale for SOT as a potential adjunctive therapy in chronic infections where other approaches fall short.

Why patients are interested

For individuals struggling with persistent infections, SOT offers several appealing features:

  • Precision targeting: Instead of broadly killing microbes (as antibiotics do), SOT goes after one critical genetic sequence, leaving other microbes untouched.
  • Durability: A single infusion provides months of activity, reducing the need for daily medication.
  • Immune-independent mechanism: Because SOT directly silences genes, it doesn’t rely on the immune system’s strength—a key advantage for patients with immune dysfunction.
  • Potential synergy: Many clinicians use SOT alongside integrative therapies (nutrition, detoxification, antimicrobials) for a more comprehensive approach.

Current limitations

Despite the excitement, it’s important to emphasize what SOT is not at this stage:

  • It is not FDA-approved for Lyme disease, EBV, or HSV. Its only infectious disease approval was for CMV retinitis, and that drug is no longer commercially available.
  • Clinical research in Lyme and chronic viral infections is preliminary, mostly limited to small pilot studies and case reports.
  • Costs can be significant, and insurance rarely covers it.
  • The decline in pathogen burden is gradual, and multiple treatments may be required.

In short: SOT is promising, but it remains an emerging therapy.

Looking ahead with both hope and caution

The field of RNA medicine is growing rapidly, with antisense oligonucleotides, small interfering RNAs (siRNAs), and messenger RNA (mRNA) therapies transforming the landscape of medicine. With continued research, we may see gene-silencing strategies like SOT become mainstream tools in the fight against chronic infections.

For now, patients and clinicians should approach SOT with both hope and caution—hope that it represents a real step forward in treating persistent pathogens, and caution because large, peer-reviewed trials are still needed to fully establish safety, efficacy, and long-term outcomes.

Part two will be published next week.

Maria Marian, ND, MSE, is a naturopathic physician at Jyzen Wellness in Mill Valley, California. In addition to her Doctorate of Naturopathic Medicine, she holds both a Bachelor and Master of Science in Chemical Engineering. She specializes in complex chronic illness, Lyme disease, and integrative approaches to immune dysfunction. Follow her on Instagram: @dr.marian.nd

For more:

According to both Dr. Ross and Dr. Cameron, it’s still too early to confidently recommend SOT for Lyme/MSIDS.

FDA Belatedly Admits Ivermectin Works for COVID But Red Cross Suppresses Malaria Cure Since 2012

https://www.2ndsmartestguyintheworld.com/p/breaking-fda-finally-admits-ivermectin?

BREAKING: FDA Finally Admits Ivermectin Works — After Years of Calling It ‘Horse Paste’ 🚨

Readers of this Substack appreciate just how murderously corrupt the FDA is, and how Ivermectin is a miracle compound…

PetMectin: Pharmaceutical Grade Pure Ivermectin

PetMectin: Pharmaceutical Grade Pure Ivermectin

Ivermectin is perhaps the single best treatment not just for PSYOP-19, but for the spike protein damage that is induced by the slow kill bioweapon injections.  Read full story

…but now, under MAHA leadership, it appears that the FDA is finally backing down on its war against Ivermectin, with journalist Maria Bartiromo stating matter of factly:

The FDA is now saying that it’s okay to take ivermectin if you have COVID.

The following clip is currently trending on X:

🚨 BREAKING: FDA Finally Admits Ivermectin Works — After Years of Calling It ‘Horse Paste’

🚨 For YEARS, Americans were mocked, censored, and silenced for even mentioning Ivermectin — branded as nothing but “horse paste.” Doctors risked their licenses, patients were denied care, and the media ran cover for Big Pharma.

Now the FDA quietly admits: Ivermectin is fine to treat COVID.

👉 A cheap, Nobel Prize-winning medicine smeared to protect profits.

👉 Hundreds of thousands may have died needlessly while “experts” pushed endless boosters.

👉 Families were left in the dark — while the truth was ridiculed and suppressed.

The FDA has blood on its hands. Lives were lost. Trust was shattered. All for politics and profit. America deserves answers. America deserves accountability.

Source

Imagine if you will during the PSYOP-19 scamdemic that Ivermectin administration was widely adopted, and that all of a sudden cases of cancer, Alzheimer’s, mood disorders, even Parkinson’s started plummeting (alongside BigPharma profits)?  (See link for article and video)

_______________

https://pierrekorymedicalmusings.com/p/the-red-cross-suppressed-a-cure-for?

The Red Cross Suppressed A Cure For Malaria in 2012, Causing Over Half A Million People To Die Every Year Since

More evidence that international health care organizations (and all governmental health care and regulatory agencies) are fully captured by Big Pharma.

I am going to start this post out with my standard declaration that: 1) I am not suicidal, 2) I am in good health, and 3) I am living my best life. For what that is worth.

The Red Cross Malaria Trial

“The Water Reference Center (WRC)” is a research center within the International Federation of Red Cross and Red Crescent Societies (IFRC). In 2012, their CEO at the time, Klaas Proesmans, conducted a study testing the efficacy of a common water purification agent called chlorine dioxide to treat malaria. The treatment consisted of increasing the concentration in cups of drinking water to levels above those typically used solely for water purification. Note that this effective treatment was first accidentally discovered by an applied scientist working in Nigeria in 1982, as I reported in this prior post.

In that study, the WRC and the Ugandan Red Cross identified 154 patients from the community around Iganga, Uganda, using skin pricks to gather drops of blood from patients suspected of being ill with malaria. They then placed the blood on slides and examined them under a microscope to look for the malaria parasite. Then they treated the patients who were positive for malaria by giving them cups of water to drink that had been treated with chlorine dioxide in the form of what Jim Humble called “Master Mineral Solution” (a mixture of sodium chlorite and hydrochloric acid). They then had the patients return to the testing/study center daily for re-testing and clinical follow-up.

They rapidly cured 154 malaria patients within two days. Sounds historic, right? A cure for malaria had been found! But no, it was not to be. Not even close.

As word of the trial and its success began to circulate, the “authorities” sprang into action, culminating in the Ugandan Red Cross and the International Federation of Red Cross and Red Crescent Societies (IFRC) issuing statements denying any official involvement in the study. They then went even further, stating that no formal clinical trial or endorsement of MMS took place under their auspices. The IFRC also added that “chlorine dioxide is not approved for the treatment of malaria and that any suggestion of Red Cross involvement was misleading.” They even got the CEO of the Water Reference Center who had planned and conducted the trial… to deny it ever happened.

Interestingly, none of the statements above were published in an official Press Release or statement; they were instead communicated solely via quotes in an interview with an investigative journalist in a blatantly obvious “debunking article” published by Business Insider.

First, I will review the extensive evidence verifying both the conduct and results of that trial. Then I will cover the above “Disinformation Response” from the media and the Red Cross in more detail. However, to understand the importance of the documented evidence that I will provide below, you need to know that the Business Insider article tried to “debunk” the claim that the trial was done by: 1) claiming it never took place, and 2) that Red Cross officials were “duped” into taking part. Yes, I know, the argument contradicts itself – either the trial never took place or Red Cross officials were “duped” into taking part, you can’t have both. Later, you will see how they later reconciled those two statements.  (See link for article and documentation and results of the trial)

____________

**Comment**

For those of you who are late to the party, know this: government ‘health agencies’ are not about health at all and have covered up and lied and continue to lie about effective, safe, cheap treatments for decades.  Further, they are riddled with conflicts of interest and are in bed with Big Pharma.

Both ivermectin and chlorine dioxide have cured people of innumerable diseases.

For more:

Ivermectin:

Chlorine Dioxide (MMS, MMS1, CDS)