Archive for the ‘Treatment’ Category

DMSO Protects & Heals Organs and Revolutionizes the Skin

https://www.midwesterndoctor.com/p/how-dmso-protects-and-heals-the-internal?

How DMSO Protects and Heals the Internal Organs

The evidence behind DMSO’s utility for a myriad of challenging diseases

Story at a Glance:

•The therapeutic actions of DMSO make it well suited to treat challenging conditions throughout the body, including many of the internal organs.

•In this article, we will examine how DMSO protects organs from injury (e.g., poisoning or blood loss) and some of the specific diseases DMSO has been proven to treat.

•These include: heart attacks, liver cirrhosis, gallstones, ARDS, lung damage from inhaling smoke, pulmonary fibrosis, pancreatitis, diabetes, nephritis, kidney stones, polycystic kidney disease, cystitis, epididymitis, genital pain, prostatitis, urethral syndrome, enlarged prostates, tubal infertility, endometrial inflammation, and fibrosis.

•This article will review DMSO treatment protocols for those conditions (along with non-DMSO approaches we utilize for them) and provide general DMSO information for those looking to use DMSO for their own health.  (See link for article)

______________

https://www.midwesterndoctor.com/p/dmso-revolutionizes-skin-care-and?

DMSO Revolutionizes Skin Care and Dermatology

Exploring how skin health goes hand in hand with whole body health

Story at a Glance:

•DMSO has a variety of unique therapeutic properties that allow it to address the root causes of many different illnesses—including those of the skin.

•DMSO effectively protects the skin from damage (e.g., radiation, chemotherapy, freezing, blood loss) and rapidly heals skin injuries (e.g., burns, chronic wounds or surgical incisions).

•DMSO addresses many circulatory disorders such as hemorrhoids, varicose veins, venous and diabetic ulcers, and Raynaud’s.

•DMSO also effectively addresses many common (but often challenging) dermatological conditions such as hair loss, psoriasis, shingles, herpes, skin cancer, lichen sclerosis, skin infections, nail issues, acne, eczema, pruritus, mastitis, insect and animal bites, sunburns and skin growths.

•This article will review DMSO treatment protocols for those conditions (along with non-DMSO approaches we utilize for them) and provide general DMSO information for those looking to use DMSO for their own health.

The American medical industry has accomplished a remarkable feat; each year it consumes a greater portion of the national budget (currently over 17.3% of GDP) yet it continues to have some of the worst outcomes in the developed world (despite spending 2-4 times as much on healthcare). This is made possible by a vast medical monopoly that prevents economical therapies from out-competing the medical industry’s cash cows and systemic corruption that makes the government unwilling to confront the sources of illness in our society (e.g., processed food companies or vaccine manufacturers).

The natural therapy I decided to focus on, dimethyl sulfoxide (DMSO), was an ideal choice for this task, as it’s very safe (provided you use it correctly) and rapidly improves a variety of conditions medicine struggles with—particularly chronic pain (discussed here). As such, I’ve received many reports of life-changing benefits from it that left even the reader in disbelief.  (See link for article)

______________

  • Strokes, traumatic brain injuries, spinal cord injuries, and many circulatory disorders (discussed here).
  • Acute and chronic tissue injuries (discussed here).
  • “Incurable” autoimmune and connective tissue disorders (discussed here).
  • Eye, ear, sinus, and dental conditions such as tinnitus and blindness (discussed here).
  • Internal organ disorders (discussed here).
  • Accelerates wound healing, prevents adhesions, eliminates scars, treats psoriasis and mastitis, insect bites, skin growths and skin cancer (discussed here)

For more:

Letter Breaking Down Timeline & Deception of Lyme Disease: No Studies Have Ruled out Sexual Transmission

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/

Question for Aaron Siri, Managing Partner Siri & Glimstad

Carl Tuttle
Hudson, NH, United States
Dec 18, 2024

If antibiotic resistance was acknowledged early on by our Public Health Officials as it was by Dr. Allen Steere in 1977 the focus would have been on developing new antimicrobials (or different combinations) as seen in the treatment of Brucellosis but the potential money grab from a Lyme vaccine was far too lucrative to pass up. Everything about Lyme from that point forward had to support vaccine development. A chronic relapsing SERONEGATIVE disease did not fit the vaccine model. The money orgy produced by vaccines could not be more obvious through recent Covid events. The rest of the world now has a bird’s eye view of what our Public Health Officials are capable of when a false narrative has been dictated. The disabled Lyme community has been shouting from the rooftops for decades and everyone reading this knows of someone severely affected from Lyme disease; shame on you for not speaking up!

The following letter to Aaron Siri, Managing Partner of Siri & Glimstad breaks down the timeline and deception. Attorney Siri recently exposed the truth/facts about childhood vaccines through the depositions of Stanley Plotkin world’s leading authority on vaccines and Dr. Kathryn Edwards world’s leading vaccinologist.

Letter to Attorney Siri:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: “aaron@sirillp.com” <aaron@sirillp.com>
Cc: “mbarney@sirillp.com” <mbarney@sirillp.com>, “ebrehm@sirillp.com” <ebrehm@sirillp.com>, “ddisabato@sirillp.com” <ddisabato@sirillp.com>, “lconsidine@sirillp.com” <lconsidine@sirillp.com>, “wmoller@sirillp.com” <wmoller@sirillp.com>, “mconnett@sirillp.com” <mconnett@sirillp.com>, “ahaskins@sirillp.com” <ahaskins@sirillp.com>, “cxenides@sirillp.com” <cxenides@sirillp.com>
Date: 12/13/2024 12:29 PM EST
Subject: Question for Aaron Siri, Managing Partner Siri & Glimstad

Siri & Glimstad
Aaron Siri, Managing Partner

Dear Attorney Siri,

When and who ruled out sexually transmitted Lyme disease?

Hold that thought for one moment please….

Weren’t we told by IDSA/Eugene Shapiro that there has never been one case of congenital Lyme? WRONG! WRONG!

Weren’t we told by the New York Times that Lyme is “hard to catch and easy to halt”? WRONG!

Weren’t we told by Wormser that persistent symptoms are nothing more than the aches and pains of daily living? WRONG!

Weren’t we told by Mainstream media that LYMErix was taken off the market due to poor sales? WRONG!

Weren’t we told by the CDC/IDSA that the bulls-eye rash appears 80% of the time?  WRONG!

Weren’t we told by the CDC/IDSA Paul Auwaerter that the two-tier Lyme test is a good test?  WRONG! WRONG!

Weren’t we told by Wormser that single dose Doxycycline as a prophylaxis after tick bite is sufficient in stopping the disease? WRONG!

Weren’t we told by the CDC/IDSA that there’s no Lyme disease in the south?  WRONG!

Weren’t we told by the CDC/IDSA that it takes 48hrs of tick attachment before the disease can be transmitted. WRONG! WRONG!

Weren’t we told by the (CDC/IDSA/ALDF) that there is no toxin involved in Lyme disease? WRONG! Again.

So what else have they gotten wrong??

Getting back to my original question: “sexually transmitted Lyme disease” ...

The 2014 study below found culture positive evidence of Borrelia spirochetes in the genital secretions of these patients:

Culture and identification of Borrelia spirochetes in human vaginal and seminal secretions
https://pmc.ncbi.nlm.nih.gov/articles/PMC5482345/

Conclusions:  The culture of viable Borrelia spirochetes in genital secretions suggests that Lyme disease could be transmitted by intimate contact from person to person. Further studies are needed to evaluate this hypothesis.

Here is the CDC’s stance on sexually transmitted Lyme disease:

About other modes of transmission
https://www.cdc.gov/lyme/causes/index.html

There is no credible scientific evidence that Lyme disease is spread through touching, kissing, or sexual contact. Published studies in animals do not support sexual transmission (Moody 1991; Woodrum 1999), and the biology of the Lyme disease spirochete is not compatible this route of exposure (Porcella 2001).

Carl Tuttle’s comment: ONE SINGLE PUBLICATION 23 YEARS AGO! This is not an actual study proving or ruling out sexual transmission; this is one man’s perspective using the words “suggest/suggests/suggesting.”

Don’t look!  That assures you won’t find!

Isn’t that exactly what you just exposed Attorney Siri in the depositions of Stanley Plotkin and Dr. Kathryn Edwards regarding the vaccine and autism debate? There have been no autism studies for the childhood vaccine schedule to challenge the mantra “Vaccines Do Not Cause Autism because we say so.”

There have been no studies to rule out sexually transmitted Lyme disease so how much sexually transmitted Lyme has been circulating in the public for the past three decades or more?

In 2003 Texas physicians Harvey and Salvato tested their chronically ill patients for Lyme disease via CDC Western blot criteria finding all patients positive for the infection in a state where the prevalence of Lyme infected ticks is only about 1-2%. “No history of bull’s-eye rash or illness following tick bite was reported by these patients.” The CDC defines “Lyme disease” exclusively as a zoonotic illness. Congenital and gestational transfer cases have been disregarded for reasons not evident to us.”

Here is an example of how other infections have been managed:

Chronic Brucellosis and Persistence of Brucella melitensis DNA
https://www.ncbi.nlm.nih.gov/pubmed/?term=Chronic+Brucellosis+and+Persistence+of+Brucella+melitensis+DNA

After acute brucellosis infection, symptoms persist in a minority of patients for more than 1 year. Such patients are defined as having chronic brucellosis. Since no objective laboratory methods exist to confirm the presence of chronic disease, these patients suffer delays in both diagnosis and treatment.

Why haven’t we done this with Borrelia burgdorferi infection…..

1. Administration of a triple versus a standard double antimicrobial regimen for human brucellosis more efficiently eliminates bacterial DNA load.
https://www.ncbi.nlm.nih.gov/pubmed/25246401

The doxycycline-streptomycin-rifampin regimen eliminates Brucella DNA more efficiently than doxycycline-streptomycin, which may result in superior long-term clearance of Brucella.

2. Different Clinical Presentations of Brucellosis.
https://www.ncbi.nlm.nih.gov/pubmed/27284398

It was once believed that rifampin was curative in treating Brucellosis but when symptoms returned doxycycline was added to the mix and when that too failed a third antibiotic, streptomycin was added to the current treatment regimen.

In contrast, oral amoxicillin or doxycycline remains the treatment of choice for treating Lyme disease for over thirty years regardless if debilitating symptoms return. Dr. Allen Steere knew that these antibiotics were not effective for all patients (see 1977 reference) but there has been no change in treatment or research to find more effective ways to eradicate the infection in all stages of disease.

Lyme arthritis: an epidemic of oligoarticular arthritis in children and adults in three connecticut communities. (1977)  https://pubmed.ncbi.nlm.nih.gov/836338/

Steere AC, Malawista SE, Snydman DR, Shope RE, Andiman WA, Ross MR, Steele FM.

Excerpt:

“The best treatment for this illness is not clear. Some physicians have reported that penicillin or tetracycline results in disappearance of the skin lesion (41,42), but others find antibiotics ineffective. Four of the patients with expanding skin lesions received penicillin but still developed arthritis.”

In contrast, the only action item we have in the pipeline after FORTY years for Lyme disease is a vaccine fast-tracked by the FDA in 2017. Since all the eggs have been put into the vaccine basket it would appear that our Health Agencies are in the shot business with annual revenue of $4.3 billion from the sales and patent royalties.

A chronic relapsing seronegative disease DOES NOT fit the vaccine model because you cannot prove vaccine efficacy in a disease where we don’t know who has or does not have the infection! So, deny the chronically infected by suppressing all evidence of antibiotic resistance, claim that the infection is easily treated because newer curative treatment for all stages of disease would give the public an excuse not to take the vaccine, reject all direct-detection methods that prove chronic infection and voila! move forward with patent royalties, vaccine development and pharmaceutical profits. The federal watchdog is no more. People suffering and dying and for what? Lyme for Profit.

The CDC has propagated this false Lyme disease narrative for decades and to this day refuses to recognize the disabling stage of the disease exposed in the documentaries Under our Skin and The Quiet Epidemic.

Suppressing evidence of antibiotic resistance for the sake of a vaccine is a crime Attorney Siri!

This is a criminal case that must be exposed as you have done with the childhood vaccine mantra; “Vaccines do not cause autism because we say so.”

Chronic Lyme does not exist because we say so! DO NOT QUESTION OUR PUBLIC HEALTH NARRATIVE, PERIOD!!! Or else…

We need your help Attorney Siri! We need your help!

Respectfully submitted,

Carl Tuttle
Independent Researcher
Lyme Endemic Hudson, NH

PS. Publication from our public health officials of Vector Borne Division of the CDC:

Post-treatment Lyme borreliosis in context: Advancing the science and patient care
Grace E. Marx*, Alison F. Hinckley, Paul S. Mead

Published 27 June 2021
https://www.thelancet.com/pdfs/journals/lanepe/PIIS2666-7762(21)00130-7.pdf

Tuttle’s comment:

This is the same old garbage (junk science) regurgitated by the CDC/IDSA year after year, decade after decade while avoiding the elephant in the room.

Conclusion: “Fortunately, safe and effective vaccines for Lyme disease may be on the horizon which could both reduce LB incidence on a population scale while averting long-term patient suffering”  Voila and there you have it folks!!!!

_________________

**Comment**

Our case is a perfect example of sexual transmission.  For our story:   https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/

Lida Mattman was able to culture spirochetes from tears, sweat, urine, CSF, blood, plasma, fleas, mites, mosquitoes, etc. and UW researcher Elizabeth Burgess could infect cats orally, ocularly, via IV, and via contact transmission in dogs:  https://madisonarealymesupportgroup.com/2019/04/02/transmission-of-lyme-disease-lida-mattman-phd/  She almost lost her job over these findings because they didn’t want them found.

The Quackery Foundations of Modern Medicine & Who’s Trying to Stop MAHA?

https://popularrationalism.substack.com/p/popular-rationalism-on-the-quackery?

Popular Rationalism on: The Quackery Foundations of Modern Medicine

Once you know the history of Allopathic Medicine, you’ll never see the medical world quite the same way again. Rationally speaking, we have much to do to Make America Health Again. Feel free to repost

Founding Fraudsters: Prominent Founding Figures with Ties to Questionable Medical Practices

The late 19th and early 20th centuries represent a pivotal moment in the history of medicine. This era witnessed the rise of professional healthcare and pharmaceutical industries, yet it also bore the imprint of practices today deemed unscientific or outright fraudulent. Many key figures in this transformative period straddled the divide between groundbreaking advancements and methods that echoed the quackery of their time.

William Radam, a German immigrant to the United States, became a prominent yet controversial figure with his creation of “Radam’s Microbe Killer.” Radam claimed his solution could destroy all disease-causing microbes in the body, an assertion supported by fervent advertising campaigns. The product, a mixture of water, sulfuric acid, and red wine, was ineffective and potentially harmful. Yet, Radam’s marketing mastery—emphasizing dramatic claims of universal cures—foreshadowed the branding strategies that pharmaceutical companies would later refine, prioritizing trust and appeal over scientific evidence.

Wm RADAM'S MICROBE KILLER NEW YORK CITY 1890s QUACK MED STONEWARE GALLON JUG - Picture 1 of 9

Similarly, Benjamin Brandreth, a New York-based entrepreneur, capitalized on public gullibility with his “Vegetable Universal Pills.” Brandreth promised that these pills, composed primarily of cayenne pepper and other innocuous ingredients, could purify the blood and cure myriad ailments. Despite their lack of medical efficacy, the pills became a household staple, and Brandreth amassed a fortune. His success illustrated not only the public’s willingness to embrace unverified remedies but also the power of colorful, engaging advertising—a practice that became a cornerstone of pharmaceutical promotion.

Image credit: Smithsonian Institution

In the United Kingdom, Dr. John Collis Browne gained fame and notoriety with his creation of “Chlorodyne,” a mixture containing opiates, chloroform, and cannabis. Marketed as a remedy for coughs, colds, diarrhea, and even cholera, Chlorodyne provided symptomatic relief but posed significant risks, including addiction and overdose. The product exemplifies the tension between addressing immediate symptoms and ensuring long-term safety—a debate that persists in discussions about modern opioid use.

undefined

Image credit: Wikipedia

Dr. Thomas Holloway, another British figure, amassed wealth selling “Holloway’s Pills and Ointments,” remedies marketed as cures for conditions ranging from indigestion to tuberculosis. Holloway’s products lacked scientific validation, but his advertisements, filled with testimonials and dramatic imagery, captivated audiences and cemented his legacy as a pioneer of persuasive marketing. His approach to consumer trust and branding heavily influenced the pharmaceutical industry, even as it perpetuated the sale of ineffective treatments.

Image source: Library of Congress

The partnership of Silas Burroughs and Henry Wellcome further illustrates the complexity of this era. Co-founders of Burroughs Wellcome & Co. in London, they introduced “Tabloid” medicines, standardized doses of drugs in pill form. Their contributions to pharmaceutical standardization were significant, yet many of their early products were insufficiently tested, prioritizing marketability over rigorous scientific validation. This dual focus on innovation and profit laid the groundwork for the modern pharmaceutical industry while highlighting its enduring challenges.

In the United States, Dr. George H. Simmons, president of the American Medical Association (AMA) from 1899 to 1924, played a critical role in professionalizing medicine. Contradictions marked yet Simmons’ career; before joining the AMA, he practiced homeopathy and engaged in aggressive advertising tactics often bordering on the unethical. Under his leadership, the AMA advanced scientific medicine, but Simmons’ background underscored the blurred lines between legitimate practice and quackery during this transitional period.

James Morison, a British merchant who styled himself as a “doctor,” founded the British College of Health and became infamous for marketing “Morison’s Pills.” These purgatives, sold as universal remedies, often caused severe complications, including fatalities. Despite public outrage and debates over his practices, Morison’s “Hygeists” traveled door-to-door selling his pills, prefiguring pharmaceutical sales tactics. His story reflects the dangers of unregulated medicine and the enduring appeal of direct-to-consumer marketing.

Have you heard about... - The Old ...

Even respected educators like Dr. William Osler, one of the founders of modern medical education, were not immune to outdated practices. Osler advocated treatments such as bloodletting and purging, inherited from earlier medical traditions. These methods focused on alleviating symptoms, such as fever, while often ignoring underlying pathologies. Osler’s contributions to medical training were profound, but his reliance on antiquated treatments illustrates the slow evolution of medical science from symptom-focused approaches to more comprehensive care.

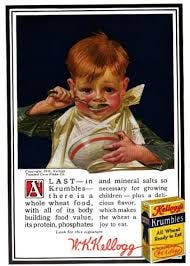
Dr. John Harvey Kellogg, director of the Battle Creek Sanitarium, also exemplified this focus on symptoms over root causes. Kellogg promoted dietary and hydrotherapy treatments to relieve discomfort like indigestion or constipation. While some of his ideas gained traction, many were later debunked. Nonetheless, his emphasis on symptom management persists in certain aspects of modern healthcare, where immediate relief often precedes systemic solutions.

1916 Kellogg's Krumbles Ad

These figures, both celebrated and controversial, embody the transitional nature of the late 19th and early 20th centuries. Their work laid the foundations for modern medicine and pharmaceuticals but also carried forward practices that blurred the lines between innovation and quackery. Understanding their contributions and controversies offers a critical perspective on how the medical profession has evolved—and how some of its early challenges remain relevant today.

Allopathic Medicine Doubles Down on Treating Symptoms for Mass Profits

The American Medical Association (AMA) emerged in 1847 with lofty aspirations to unify medical professionals and elevate the standards of medical practice. However, by the late 19th and early 20th centuries, the AMA’s role had evolved into gatekeeping within a chaotic and fragmented healthcare landscape. While it was instrumental in defining and enforcing professional norms, its efforts were not without controversy. The AMA frequently targeted medical traditions like homeopathy and eclecticism, branding these practices as quackery to consolidate its authority.

In the mid-20th century, doctors of chiropractic successfully fought a legal and professional battle to distinguish their practice from allopathic medicine and establish their own jurisdiction. The landmark case Wilk v. AMA (1976) was pivotal in exposing efforts by the American Medical Association (AMA) to marginalize chiropractic care through what was ruled as an organized campaign of anticompetitive practices. Chiropractors argued that their focus on spinal adjustments and holistic health addressed root causes of ailments, in contrast to the symptom-focused approaches of allopathic medicine. The courts ultimately ruled in favor of the chiropractors, affirming their professional legitimacy and granting them the autonomy to operate as a separate healthcare discipline. This victory solidified chiropractic care’s identity outside of the allopathic paradigm, enabling practitioners to define their own standards and scope of practice.

The AMA’s strategy of attacking competing professions, while successful in professionalizing medicine, often aligned the AMA with emerging pharmaceutical interests. By promoting treatments supported by these companies, the AMA helped establish and open new marketplaces where the lines between evidence-based care and commercial success were blurred. The organization’s endorsement of certain drugs and therapies, often marketed aggressively by pharmaceutical companies, underscored the extent to which medical practice was shaped by commercial imperatives as much as scientific rigor.

Similarly, the British Medical Association (BMA) faced significant challenges in addressing the pervasiveness of patent medicines. Founded in 1832, the BMA sought to instill ethical standards and unify medical practitioners under a professional banner. However, during the late 19th century, Britain was flooded with patent medicines promising miraculous cures for a range of ailments. The BMA’s efforts to regulate these products were hampered by the lack of legal authority to enforce its recommendations and the public’s reliance on these remedies. Adding to this complexity, some BMA members themselves profited from selling questionable treatments, illustrating the difficulty of disentangling professional credibility from commercial ventures. While the BMA’s eventual success in advocating for stricter regulation of patent medicines helped improve public health, this achievement came alongside the entrenchment of symptom-focused remedies in both medical practice and public expectations.

Pharmaceutical companies played an increasingly central role during this period, often shaping the direction of medical science through their influence on education and research. Burroughs Wellcome & Co., founded in 1880, revolutionized the standardization of pharmaceuticals by introducing pre-measured doses in tablet form. While this innovation addressed the need for consistent dosing, the company’s products frequently lacked the clinical testing necessary to substantiate their claims. Similarly, Parke, Davis & Co. in the United States pioneered standardized plant extracts but marketed addictive substances like heroin and cocaine-based products as therapeutic agents. Both companies engaged in aggressive marketing campaigns that emphasized the reliability of their products while sidestepping deeper questions about safety and efficacy. These marketing strategies shaped public perception of medicine, fostering a culture in which immediate relief was often prioritized over addressing underlying causes of illness.

The pharmaceutical industry’s influence extended into medical education and research, often steering these institutions toward commercially viable treatments. Companies provided funding for medical schools and clinical trials, ensuring that their products became central to medical curricula and practice. This symbiotic relationship between pharmaceutical companies and medical institutions helped establish the dominance of allopathic medicine but also entrenched a commercial model that occasionally undermined scientific objectivity.

The emphasis on treating symptoms rather than root causes, a hallmark of patent medicines, became institutionalized in modern medical practice. The industrialization of medicine during this era created pressure to produce quick, scalable solutions that aligned with the needs of an expanding healthcare system. For example, Dr. John Collis Browne’s Chlorodyne provided effective symptomatic relief for conditions like pain and diarrhea but ignored the underlying causes and contributed to widespread opiate addiction. Similarly, the rise of analgesics like aspirin marked a breakthrough in symptom management but also reinforced the perception that addressing discomfort was more important than understanding its origins. These trends, while addressing immediate patient needs, laid the groundwork for criticisms of modern medicine as overly focused on short-term relief at the expense of long-term health.

The legacy of these historical developments continues to shape contemporary healthcare. The commercialization of medicine, rooted in the practices of organizations and pharmaceutical companies during this period, is evident in today’s debates over chronic disease management, mental health treatment, and the opioid epidemic. The prioritization of symptom management over prevention and the influence of corporate interests on medical research and practice remain enduring challenges. By tracing these issues back to their historical roots, we can better understand the systemic forces that continue to shape healthcare today.

“Allo-pathy”: Come to Me for One Disease, I’ll Give You Another?

The term “allopathy” was coined by Samuel Hahnemann, the founder of homeopathy, in the early 19th century. Hahnemann used the term to criticize the prevailing medical practices of his time, which he believed treated disease by inducing effects opposite to the symptoms rather than addressing the underlying causes. Derived from the Greek words “allos” (other) and “pathos” (suffering or disease), allopathy was meant to contrast with homeopathy, which relied on the principle of “like cures like.” Over time, the term became associated with conventional Western medicine, though it was originally intended as a pejorative label for its symptom-focused methods

The model of perpetual symptom management has become a cornerstone of modern allopathic medicine. By focusing on alleviating symptoms rather than addressing the root causes of illness, the system inadvertently creates a cycle of dependency. This approach not only exacerbates underlying conditions but also generates new health issues that require further interventions. The parallels between 19th-century quackery and contemporary pharmaceutical practices are striking. Just as mercury-laced remedies once sickened patients while offering additional treatments to address those symptoms, today’s medicines often introduce side effects that necessitate more prescriptions, particularly among older adults. This phenomenon, known as polypharmacy, has become a defining characteristic of modern healthcare.

Just Like Doc Grandad

Historically, quack doctors in the 19th century used mercury-based treatments for a range of ailments, including syphilis and skin conditions. While initially marketed as a cure-all, these treatments caused severe toxic side effects, including damage to the kidneys and nervous system. Rather than abandoning these dangerous remedies, practitioners often compounded the issue by prescribing additional drugs to mitigate the damage caused by mercury, creating a profit-driven cycle of dependency. Similarly, in modern medicine, drugs designed to treat symptoms frequently lead to new health issues. Nonsteroidal anti-inflammatory drugs (NSAIDs), for example, are commonly used to relieve pain but are known to cause gastrointestinal irritation and ulcers. To address these side effects, patients are often prescribed proton pump inhibitors (PPIs), which carry their own risks, such as nutrient deficiencies and an increased likelihood of bone fractures. This cycle mirrors the strategies of historical quacks, perpetuating a model that prioritizes symptom management over holistic healing.

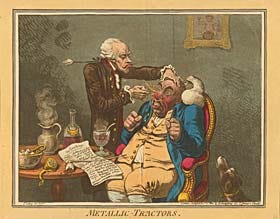
Metallic-Tractors

The emphasis on treating symptoms rather than root causes has profound implications, particularly for chronic diseases. Conditions such as hypertension and Type 2 diabetes are typically managed through medications aimed at controlling blood pressure and blood sugar levels. While these drugs provide measurable short-term benefits, they often fail to address underlying lifestyle or environmental contributors, such as diet and physical inactivity. This focus creates a long-term revenue stream for pharmaceutical companies, as patients remain dependent on medication for life.

In the case of autoimmune disorders, the use of aluminum-based adjuvants in vaccines provides another example. Aluminum is employed to enhance the immune response in vaccines. Still, research has shown that it is also used in animal studies to induce autoimmunity for testing drugs targeting such conditions in humans. These findings, detailed in a 2017 IPAK report, raise ethical concerns about the potential long-term consequences of aluminum exposure in humans, particularly for individuals predisposed to autoimmune conditions. The resultant autoimmune diseases require management with immunosuppressive drugs, further entrenching patients in the cycle of pharmaceutical dependency.

This pattern is most pronounced among older adults, where the prevalence of polypharmacy is staggering. Defined as the use of five or more medications simultaneously, polypharmacy is often the result of a cascade of prescribing practices. For instance, chronic pain patients may be prescribed opioids for pain relief, only to develop gastrointestinal issues and depression as side effects. These issues are then treated with additional medications, such as PPIs and antidepressants, each carrying its own risks and side effects. Diabetics on glucose-lowering medications frequently face cardiovascular side effects, prompting prescriptions for statins and antihypertensives, which can lead to fatigue, cognitive decline, and other complications. This layered approach to medication management not only diminishes quality of life but also places an enormous financial burden on healthcare systems.

Regulatory frameworks and institutional practices play a critical role in perpetuating these cycles. Agencies like the FDA approve drugs despite well-documented side effects, often viewing these risks as acceptable trade-offs. For instance, selective serotonin reuptake inhibitors (SSRIs) are widely prescribed for depression but can cause weight gain and sexual dysfunction. These side effects often lead to additional prescriptions for weight management drugs or PDE5 inhibitors like sildenafil, further entrenching the patient in a pharmaceutical feedback loop. Direct-to-consumer advertising exacerbates this issue by normalizing symptom-focused treatments and encouraging patients to request specific drugs. Advertisements for biologics targeting autoimmune diseases, for example, include long lists of potential side effects, many of which require additional medical interventions.

The broader implications of symptom-focused medicine are significant. Healthcare costs spiral as billions of dollars are spent annually on preventable complications and drug-related side effects. Hospitals face mounting challenges in managing polypharmacy-related hospitalizations and adverse drug interactions. Public trust in medicine also erodes as patients become increasingly disillusioned with a system that seems more focused on profits than genuine healing. This discontent is evident in the growing backlash against overreach, including controversies surrounding vaccine safety and pharmaceutical transparency.

MAHA via Root-Cause Medicine and Integrative Pathways to Health (IP2H)

There are, however, alternative models that prioritize root-cause analysis and prevention. Lifestyle medicine has demonstrated remarkable success in addressing chronic diseases like Type 2 diabetes through dietary and lifestyle interventions. Programs emphasizing whole-food plant-based diets or ketogenic diets have helped many patients reduce or even eliminate their dependence on medication. Preventive care models, such as those implemented in “Blue Zones” communities known for their longevity and low rates of chronic disease, offer compelling evidence that addressing root causes is both feasible and effective.

The parallels between historical quackery and modern symptom-focused practices highlight the dangers of a system that prioritizes profits over patient health. To break this cycle, systemic changes are needed, including a greater emphasis on preventive care, root-cause analysis, and patient education. Regulatory bodies must also be held accountable for approving drugs with significant side effects and for fostering a culture of transparency and safety in pharmaceutical development. By learning from history and addressing these issues head-on, the healthcare system can move toward a model that truly prioritizes patient well-being over perpetual dependency.

________________

https://www.midwesterndoctor.com/p/whos-trying-to-stop-america-becoming?

Who’s Trying to Stop America Becoming Healthy Again?

Untangling the century of dark industry tactics that have poisoned the health of America

Since COVID-19 began, those who tried to warn the public about the clear dangers of how we were addressing COVID-19 (e.g., lockdowns, vaccines, and remdesivir) have been targeted and silenced. While many were initially in disbelief our government could do something like this, more cynical parties (e.g., myself) suspected something like this would happen (as it always does) and caught the early warning signs of it.

In my eyes, beyond the over-the-top marketing throughout the media to promote the COVID boondoggle, there were three particularly noteworthy (and interwoven) facets to this campaign:

1. Widespread censorship of opposing ideas (e.g., GoFundMe deleting fundraisers for individuals who had severe COVID vaccine injuries and nowhere else to turn for help since those fundraisers alerted people to the vaccines not being completely “safe and effective” and most of the news networks refusing to question the COVID narrative). Of note, from the start, I assumed there had to be shadow banning occurring (as I could see the effects of it happen in real time) and coordination between the social media platforms and the Biden administration—an illegal activity which was gradually confirmed by lawsuits (e.g., due to the Twitter file) and other leaks that revealed shadow banning was widespread on the tech platforms.

2. The establishment targeted anyone who dissented against the narrative in a coordinated fashion. For example, many absurd complaints were used to target the medical licenses of physicians who were saving patients from dying from COVID (e.g., Meryl Nass, whose suspension was so absurd that 13 members of Maine’s legislature formally complained to the medical board about it).

3. A very aggressive and coordinated campaign to neutralize anyone who disputed the narrative on social media. Early on, I began to suspect this was happening because I’d see the same bad actors (typically doctors) use the same sculpted talking points. In April 2024, I found out an industry funded group did indeed exist, and that:

  • Many of the people I’d suspected were in a coordinated conspiracy did indeed belong to a secret group (“Shots Heard”) dedicated to fighting misinformation online.
  • That group was tied to the Federal Government and funded by the pharmaceutical industry.
  • That group, one by one, would target dissident healthcare workers and attempt to both get them removed from social media, to have their medical licenses taken away or get them fired from work, and in some cases, to directly harass them at their homes.  (See link for ‘must read’ article)

________________

Highlights:

  • CNN features anti-vaxxer turned pro-vaccine woman to discredit RFK Jr., but doesn’t disclose links to dark pharma-backed censorship groups.  Oops.
  • The highly sculpted language is sometimes clever, but is often ridiculously false.
  • John Davidson highlighted how another prominent “grassroots” and “parent-created” vaccine advocacy organization (Voices for Vaccines) takes money from almost every large pharmaceutical company on the planet.  Oops again!
  • Due to cutthroat lobbying, blackmailing newspapers not to support clean food laws, and aggressively peddling paid off scientific ‘experts’ to promote junk science, the first head of the FDA resigned as he felt the only way to create change and a safe food supply was for the public to demand it.
  • Monopolization by Robber Barons like Rockefeller always enslaves and never empowers the public.
  • Monopolization follows a similar pattern and gradually makes it impossible to obtain resources and once competition is eliminated, costs skyrocket and make it significantly worse than what preceded it.
  • Richard Nixon’s Secretary of Agriculture made the decision that America needed to transition from small family farms to large monoculture operations (his motto was “get big or get out”), a policy which coincided with major agribusinesses taking over the farming sector and farming subsidies which entrenched this new status quo.
  • After the tobacco industry suffered devastating defeat in courts they then invested in the processed food industry and used their skills from making cigarettes addictive to now making processed foods addictive.
  • The US completely relaxed all regulatory safeguards regarding patented GMOs which monopolize agriculture, allowing companies to sue farmers who had GMO crops growing in their field due to drifting from a neighbor’s farm, that also require higher amounts of dangerous chemicals, and adversely affect human health.
  • See link for a series of interview clips on Ozempic and the systemic corruption and dysfunction throughout healthcare.
  • See link on how dirty tricks are used against those who expose industry corruption.
  • Read an article by The Union of Concerned Scientists describing the playbook industry always uses to suppress inconvenient science. Also see the flow-chart for government PR campaigns.
  • A common PR tactic is to PAY a third party ‘expert’ to promote the desired message.
  • Protect Our Care is financed by the Sixteen Thirty Fund, a 501(c)(4), a special type of non-profit that is allowed to engage in political lobbying and more importantly, does not have to disclose its donors. This group in turn, has been used to fund various left-wing political causes and has been repeatedly criticized by left-leaning media outlets (e.g., the New York Times) as a “dark money” organization. According to Politico, the Sixteen Thirty Fund (which received 51.7 million from a single anonymous donor to influence the 2018 elections) was one of the largest television advertisers during the 2018 midterm elections—elections where coincidently a massive number of military intelligence operatives (e.g., from the CIA) ran as Democrats for Congressional seats and completely changed the direction of the party. As such, I feel it’s reasonable to suspect some of those invisible donors also have financial interests in the pharmaceutical industry.
  • Also see link for flow chart of who is funding these dark online groups censoring anyone challenging the COVID cartel.
  • Senator Elizabeth Warren received $821,941 from Big Pharma making her the second most bought-off person in Congress.  Bernie Sanders got $1,417,811.

For more:

Medical Detective: An Overview of Lyme Disease Signs and Symptoms

https://www.lymedisease.org/overview-lyme-signs-symptoms/

MEDICAL DETECTIVE: An overview of Lyme disease signs and symptoms

This article was originally posted on Dr. Richard Horowitz’s Medical Detective Substack. You can find more helpful content by subscribing to it here.

Now that you know that Lyme disease presents a regular risk for you and your family due to its worldwide spread, rapidly increasing tick populations due to a warming climate (ticks reproduce faster at higher temperatures), and lack of accurate testing, what are the most common Lyme symptoms, aside from the telltale rash, that you should be looking for to suspect an infection?

Signs and Symptoms of Lyme Disease

There are six major signs and symptoms that allow the Medical Detective to suspect an infection with Borrelia burgdorferi, the agent of Lyme disease:

(1) It is a multisystemic illness. Although it is possible to just have one joint that hurts and may be swollen as your primary symptom, this is not the usual manifestation that I have seen among the 13,000 chronically ill individuals I have diagnosed and treated. A broad range of body systems is usually affected, including the heart, musculoskeletal system, along with neurological, psychological, hormonal, and even immunological consequences, including immune deficiency.

So if you have a multisystemic illness, with many of the symptoms listed below, and your doctor has sent you to specialist after specialist looking for answers, that is a telltale sign Lyme disease may be present.

(2) Symptoms of Lyme disease tend to come and go with good and bad days. In many other chronic illnesses, symptoms tend to be daily without huge variations in intensity or frequency.

(3) The hallmark symptom of Lyme disease is migratory pain. Migratory joint pain, migratory muscle pain and/or migratory nerve pain (neuropathy, which is usually experienced as a burning, tingling, numbness or stabbing sensation) lets the Medical Detective know that a diagnosis of Lyme is likely. (There are only seven diseases that cause migratory pain.)

(4) Symptoms of Lyme disease usually get better or worse with antibiotics. This would not be the case with a chronic fatiguing, musculoskeletal, cardiac, neuropsychiatric illness due to a pure viral infection (which can be the case in CFS/ME, FM, and/or long Covid). Symptoms that can get better (lowering the load of the bacteria) or worse (known as a Herxheimer reaction, which is an inflammatory reaction due to killing off of the bacteria) include the following:

*Muscle and joint pain (which can be migratory in nature)

*Severe fatigue

*Tingling and/or numbness/and/or burning and/or stabbing sensations (neuropathy, which can be migratory in nature)

*A stiff neck

*Headaches

*Light and sound sensitivity

*Dizziness

*Memory and concentration problems

*Mood disorders such as depression and/or anxiety

*Difficulty falling asleep and staying asleep

*Fever and/or chills

*Gastrointestinal issues

*Chest pain with palpitations

*Shortness of breath…and more.

*(I’ll have more details about symptoms in my next article.)

(5) Women usually have a worsening of Lyme disease symptoms around their menstrual cycle: before, during or right afterwards. This is because when estrogen levels drop, the bacteria can become more active.

(6) Finally, there are clues on blood tests that you have been exposed to Lyme disease and associated tick-borne infections, but it is important to know that standard two-tiered testing (STTT), using an ELISA followed by a Western blot–one of the primary ways doctors try to diagnose Lyme disease–is highly insensitive, with the accuracy of about a coin flip.

Insensitive testing

For early Lyme disease, doctors may use a version of the STTT, called “Modified two-tiered testing (MTTT),” where two enzyme immunoassays (EIAs) are used instead of the traditional Immunoblot. (Although in one Canadian study it was 25% better at diagnosing some early cases, it is still an imperfect test, and other studies have found the MTTT to be more or less equivalent to the STTT.)

Which means that, ultimately, Lyme disease is a clinical diagnosis. An EM rash, the classic rash of Lyme disease, is proof of exposure and does not require a positive blood test. But if you did not see the rash, you need to know that negative testing with a STTT and/or a MTTT does not rule out exposure.

Clues that you have been exposed are Borrelia specific bands in your blood, such as the 23 kDa (Outer surface protein C, i.e., Osp C), 31 kDa (Osp A), 34 kDa (Osp B), 39 kDa and the 83/93 kDa bands. The exception is the 31 kDa band on a Western blot may cross react with viral proteins or reflect an autoimmune process. The 31 kDa band on an Immunoblot, a test that uses recombinant DNA, is however specific, which is why we prefer using Immunoblots as our first line test.

Standard treatment for Lyme disease

Because testing and treatment can be so complicated, there’s much more info to come….

For now, know that if caught early, the standard treatment for Lyme by some infectious disease doctors is a 14-day course of antibiotics, usually doxycycline or amoxicillin. For an EM rash, some doctors will prescribe antibiotics for up to 30 days.

However, if you have multiple EM rashes, or an EM rash with peripheral nervous system (PNS) involvement (tingling, numbness, burning, and/or stabbing sensations of the arms and legs) and/or central nervous system (CNS) involvement with nerve palsy like Bell’s palsy (where your facial muscles don’t work properly) with associated neuropathy, cognitive difficulties with memory/concentration problems, light or sound sensitivity, dizziness, sleep disorders, new or exacerbated psychological symptoms–short courses of antibiotics will not clear the infection, and you will go on to the chronic form of the disease.

When symptoms persist–Stephen’s story 

If symptoms persist, brace yourself! You could find yourself at the mercy of the bacteria that will make your life a misery. Like Stephen.

When Stephen came to see me in March 2020, he told me he’d had to drop out of his first semester at college because he couldn’t function anymore. He’d been suffering for 10 years—no, that is not a typo!–from a strange disease that had brought his life to a halt, going from one doctor to another trying to find a cure.

When I asked him to describe his symptoms, he took a deep breath. The list was long. “Well, I’m tired all the time, no matter what I do,” he told me. “My joints and muscles always ache. I get these sharp stabbing pain in my hands or legs or chest. Sometimes it’s a burning pain.” He shook his head, confused. After all these years, he still couldn’t understand why this was happening. It didn’t make sense.

Working on a theory, I asked if he experienced shortness of breath or night sweats. He did. But then, carefully avoiding my eyes, he confessed to the worst symptom of all. “Sometimes —not always—I see or hear things that aren’t really there.”

My heart went out to him. This bright young man with such a promising future had suddenly developed auditory and visual hallucinations when he was 18 for no apparent reason. A psychiatrist decided he was schizophrenic, and prescribed an antipsychotic that came with serious side effects. Once Stephen had this diagnosis, no doctor had ever listened to him the same way again. Until now.

An important piece of the puzzle

“Have you ever been around cats?” I asked him.

“Not lately,” he said. Then he remembered that, growing up in rural Pennsylvania, he’d had a cat. Inevitably, she had scratched and bitten him more times than he could remember.

“How about tick bites?”

“Sure,” he said. “But that was years ago…”

As I questioned him, the pieces of the medical puzzle started to fall into place. I’d seen the same series of infectious and environmental assaults in patients with this illness for decades. I thought it might also stem from the same infections.

When I asked Stephen to stand up for the physical exam, he felt dizzy. I checked his pulse. It had jumped more than 30 beat per minute and stayed high for several more minutes.

That was a clear sign of POTS (Postural Orthostatic Tachycardia Syndrome), a dysregulation in areas of the nervous system that controls our blood pressure and pulse rate. I see this problem regularly in my chronic Lyme disease patients, those suffering from long Covid, as well as those with problems due to environmental toxins like mold.

When he lifted his shirt so I could listen to his lungs, Stephen muttered, apologetically, “Oh, I have a rash…” That was an understatement. Spreading across his entire middle and upper back was a distinctive purple rash that looked like horizontal stretch marks.

I smiled. “I need to confirm it with blood tests, but I think I know what’s causing your symptoms.”

Stephen was stunned. “What is it?”

“A parasite,” I told him. “It’s called Babesia. It’s a protozoan, like malaria, that can cause sweats, chills, shortness of breath. And I also strongly suspect you have contracted a bacterial infection called Bartonella, often transmitted through cat bites and scratches.”

When we got his laboratory results back, they confirmed my suspicions. “Bartonella could’ve caused all of your neuropsychiatric symptoms—and the rash!” I told him.

Other factors

That said, a condition as extreme as Stephen’s is not just about parasites and little-known bacterial infections. There were a lot of contributing factors. He’d been exposed to environmental toxins like mold, along with vitamin and mineral deficiencies, and this had exacerbated and compounded his symptoms, preventing his immune system from clearing away any lingering infections and making it difficult for him to detoxify and improve.

With so many things going on, it was clear that Stephen didn’t just have Lyme disease. He had Multiple Systemic Infectious Disease Syndrome (MSIDS). He had multiple overlapping sources of inflammation with downstream effects making him ill.

When I started Stephen’s treatment, using dapsone combination therapy for chronic Lyme disease and Bartonella, he soon felt like a completely different person. For the first time in over a decade, his pain was gone. His joint and muscles didn’t ache. The stabbing, burning nerve pains had disappeared. No more night sweats (we will devote an entire article to Babesia in the future). No fatigue.

Even the hallucinations were almost gone. After struggling to regain his health for so long that he had nearly given up hope, Stephen was almost completely back to normal — in months — after finally getting the right treatment.

And you can get the right treatment too.

More to come

In upcoming articles, I’m going to talk much, much more about MSIDS, and the 16-point treatment plan that I used my Medical Detective skills to develop. It’s a treatment plan that works for not only chronic Lyme disease, but many other chronic illnesses which share overlapping biological processes with the three I’s: multiple infections, inflammation, and immune dysfunction.

Coming up next, I’m going to share the Lyme questionnaire, taken from my book. How Can I Get Better? and published in the International Journal of General Medicine. We validated this questionnaire in 1,600 individuals, both healthy and sick, with help from researchers at the State University of New Paltz. I know it’s going to help if you worry at all that you or someone you know might have Lyme disease. Then, in future articles, we are going to dive into the broad range of testing available to help diagnose early and late disease.

This article was originally published on Substack by Dr. Richard Horowitz. 

Dr. Richard Horowitz has treated 13,000 Lyme and tick-borne disease patients over the last 40 years and is the best-selling author of  How Can I Get Better? and Why Can’t I Get Better? You can subscribe to read more of his work on Substack or join his Lyme-based newsletter for regular insights, tips, and advice.

For more:

FLCCC Co-Founders Join AAPS Lawsuit Against ABIM & Board-Certifying Organizations For Censoring Physicians

https://flccc.substack.com/p/flccc-co-founders-join-aaps-lawsuit?

FLCCC Co-Founders Join AAPS Lawsuit Against ABIM and Board-Certifying Organizations for Censoring Physicians

“Without open scientific debate, we risk losing the opportunity to discover effective treatments and provide the best patient care.”

FLCCC ALLIANCE

FLCCC Co-Founders Join AAPS Lawsuit Against ABIM and Board-Certifying Organizations for Censoring Physicians

Washington, D.C. (November 12, 2024) – The FLCCC Alliance announced that its co-founders, Dr. Pierre Kory and Dr. Paul Marik, are seeking by motion to join the Association of American Physicians and Surgeons (AAPS) Educational Foundation’s federal lawsuit against the American Board of Internal Medicine (ABIM) and other board-certifying organizations as well as the Biden Administration. This lawsuit, filed in U.S. District Court in Galveston, TX, seeks to hold accountable entities that have not only censored but retaliated against physicians, including Drs. Kory and Marik, for advocating evidence-based approaches to patient care that are contrary to public health agency directives. Drs. Kory and Marik asked the court to join the suit after ABIM’s unprecedented decision to revoke their board certifications for their public advocacy despite their expertise acquired through long and distinguished careers.

FLCCC Co-founders Dr. Paul Marik and Dr. Pierre Kory

The lawsuit alleges that ABIM engaged in tortious interference with their efforts to engage in a national debate over repurposed drugs and concerns about mRNA vaccination. The suit alleges that ABIM infringed on their freedom of speech, contractual due process rights, and includes defamation claims on behalf of Drs. Kory and Marik.

“Consensus-Driven” Medicine Cited as Rationale for Decertification

Since May 2022, when the ABIM first issued a Notice of Potential Disciplinary Action, Drs. Kory and Marik have tirelessly defended their efforts on the part of FLCCC’s positions, providing substantial medical and scientific evidence to support their recommendations for early COVID-19 treatment and critiques of vaccine risks. Despite these eminent physicians’ submitting over 170 references in a comprehensive 60-page response in January 2023, the ABIM chose to dismiss these scientific contributions in favor of a narrow, “consensus-driven” narrative—a rationale used as grounds for the revocation of their board certifications.

The AAPS case against ABIM and its co-defendants was originally dismissed by the District Court but was reinstated against the board defendants by the Fifth Circuit in its opinion that expressed strong concern about the suppression of medical viewpoints.

In response to their recent decertifications, Dr. Marik underscored the pressing need to protect medical freedom and accountability in healthcare:

“True progress in medicine depends on the free exchange of ideas and the courage to challenge established norms. Without open scientific debate, we risk losing the opportunity to discover effective treatments and provide the best patient care.”

“This fight is about more than just our right to speak—it’s about protecting the future of healthcare and putting these organizations on notice. When doctors are silenced for questioning the prevailing narrative, we all lose,” said Dr. Kory.

“We must ensure that medical decisions are guided by expertise and evidence, not by fear of reprisal.”

A Stand for Free Medical Speech and Patient Care

The lawsuit contends that board-certifying organizations, including the ABIM, the American Board of Family Medicine (ABFM), and the American Board of Obstetrics & Gynecology (ABOG), have acted in concert together and with the federal government to suppress and retaliate against physicians with dissenting viewpoints, thus infringing upon First Amendment rights. President and Chief Medical Officer of FLCCC Dr. Joseph Varon highlighted the critical need for organizations like FLCCC to stand behind medical professionals facing such reprisals.

“The FLCCC Alliance firmly believes that the essence of medical science lies in the open dialogue, exchange of ideas, and rigorous debate of differing perspectives. However, the actions of the ABIM reflect a troubling trend towards censoring any opinions that challenge the status quo. This censorship stifles innovation, limits treatment options for patients, and ultimately harms the doctor-patient relationship.”

Seeking Justice and Accountability

This case represents a broader fight for the integrity of healthcare, protecting physicians’ right to practice honest medicine based on clinical experience and scientific evidence. The FLCCC Alliance remains steadfast in its mission to advocate for healthcare providers’ autonomy, ensuring that the voices of Drs. Kory and Marik, and other medical professionals, are not silenced. This lawsuit is a pivotal step toward safeguarding medical integrity and patient care freedom for practitioners and patients around the world. 

About the FLCCC Alliance
The FLCCC Alliance, a nonprofit 501(c)(3) organization, was formed in March 2020 by a group of highly published, world-renowned critical care physicians and scholars with the academic support of allied physicians worldwide. Known for its lifesaving protocols for preventing and treating COVID-19 in all stages of illness, including “long COVID” and post-vaccination syndrome, the FLCCC has expanded its work to include treatment guides for various other conditions, such as sepsis, metabolic disease, cancer, and depression. The organization is dedicated to Honest Medicine™ that prioritizes patients above profits and emphasizes long-term wellness and the empowerment of both physicians and their patients. For more information, visit flccc.net

About AAPS

The Association of American Physicians and Surgeons – AAPS – is a non-partisan professional association of physicians in all types of practices and specialties across the country.

Since 1943, AAPS has been dedicated to the highest ethical standards of the Oath of Hippocrates and to preserving the sanctity of the patient-physician relationship and the practice of private medicine. www.aapsonline.org


Will You Support Honest Medicine?

Your support is vital to advancing our mission. As the ABIM situation continues to unfold, we need your support to defend doctors and uphold your right to healthcare free from harmful influences.

By contributing to the Honest Medicine Movement, you’re not just donating—you’re becoming a crucial part of our effort to transform healthcare. Your support helps us expand our network of experts, amplify our global advocacy, and drive impactful initiatives.

Together, we can enhance patient care, reform broken systems, and champion the cause of transparent, evidence-based medicine. Every contribution fuels our key initiatives and brings us closer to a future where honest, reliable healthcare is accessible to all.

For more: