Archive for the ‘Treatment’ Category

Start Treatment if TBI’s are Suspected

http://www.mdedge.com/ccjm/article/141387/dermatology/tickborne-diseases-other-lyme-united-states  Cleveland Clinic Journal of Medicine. 2017 July;84(7):555-567

KEY POINTS

  • Tickborne illnesses should be considered in patients with known or potential tick exposure presenting with fever or vague constitutional symptoms in tick-endemic regions.
  • Given that tick-bite history is commonly unknown, absence of a known tick bite does not exclude the diagnosis of a tick-borne illness.
  • Starting empiric treatment is usually warranted before the diagnosis of tickborne illness is confirmed.
  • Tick avoidance is the most effective measure for preventing tickborne infections.

____________________________________________________________________________

The article delineates symptoms, transmission, reservoirs, testing, and treatment of the following TBI’s:  Rocky Mountain Spotted Fever, Rickettsiosis, Ehrlichioses, Babesiosis, Tickborne relapsing fever, Borrelia miyamotoi, Southern Tick-associated Rash illness, Tularemia, and Tickborne viral infections.


101_emrash316x316

47_rash316x316

I need to address the following statements at the end of the article:

“Knowledge of the geographic locations of potential exposure is paramount to determining which tickborne infections to consider, and the absence of a tick bite history should not exclude the diagnosis in the correct clinical presentation.

Clinicians need to tread carefully here.  Many patients have been denied testing and treatment due to a map.  These maps should be viewed with the same suspicion as the testing.  

25_antibody316x316

01_test_petri316x316

38_sensitive316x316

Until you tell the fox, squirrel, bird, deer, lizards, and hundreds of other reservoirs to stay put, ticks will be traveling everywhere along with the pathogens they carry.  Since Lyme Disease (borrelia) has been found in every continent except for Antarctia (it will be found there too), you can assume that means ticks are there too.  

I’m glad the authors stated this:

In addition, it is important to recognize the limitations of diagnostic testing for many tickborne infections; empiric treatment is most often warranted before confirming the diagnosis.”132_fail316x316

For those of us in this war, this “empiric treatment” by mainstream medicine is new.  Patient after patient has had to wait for test results before doctors will treat them.  Often, since the testing is so poor, it comes back negative and the patient is sent packing, even if the patient has every symptom in the book.  The next step is for authorities to admit and acknowledge that diagnosis of Tick borne infections is a clinical one.  This means doctors need to learn a whole lot more.  For docs willing to learn, please see:  https://www.lymecme.info

Even the CDC admits the tests suck: https://madisonarealymesupportgroup.com/2017/07/01/good-morning-america-cdc-advises-multiple-lyme-tests-due-to-false-negative-results/ CDC spokesperson at end of video.

Another very important point needs to be made.  The CDC has pushed this one pathogen for one tick mantra for too long.  Many patients are co-infected making cases infinitely more complex and challenging to treat.  Lyme literate doctors trained by ILADS understand this and treat accordingly.  Until mainstream medicine realizes and admits people can have numerous pathogens, and treat for them, people will not get better.  This is why all the doxycycline in the world will not help some patients.

32_co316x316

One last point is that mycoplasma, Bartonella, and other pathogens are not included here but are quite common in patients.  Many of these pathogens are persistent and are adept at surviving.  More research needs to be done on these co-infections.

Please see:

https://madisonarealymesupportgroup.com/2017/05/01/co-infection-of-ticks-the-rule-rather-than-the-exception/  If ticks are co-infected, so are patients.

https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/

https://madisonarealymesupportgroup.com/2016/03/20/why-we-cant-get-better/


2600% Increase in Babesia in 12 Years in Wisconsin

CDC Reports 2600% Increase in Tick-Borne Babesiosis Infections in Wisconsin in 12 Years

It is not just a bad summer for ticks — it has been a bad decade for the spread of tick-borne infections. New surveillance from the CDC reports rapid expansion and increase in cases of babesiosis, a sometimes life-threatening disease, in Wisconsin.The CDC compiled the new report from surveillance conducted every three years during the period between 2001 through 2015. During that time, electronic surveillance came online to provide faster, more thorough, case reports. While a boost in case counts as monitoring methods improve is sometimes due to under-reporting, the CDC says the increase in Wisconsin is due to an actual uptick in cases — not just better reporting.

Total confirmed babesiosis case counts (N = 294) initially reported directly and electronically through the Wisconsin Electronic Disease Surveillance System (WEDSS),* Electronic Laboratory Report (ELR) — Wisconsin, 2001–2015.Image via MMWR

What Is Babesiosis and Why Should You Be Concerned?

The black-legged tick Ixodes scapularis transmits the Babesiosis bacteria. This is the same tick that spreads Lyme disease, anaplasmosis, and recently the more immediately deadly Powassan virus.

These ”black-legged ticks”, Ixodes scapularis, are capable of spreading babesiosis, Lyme disease, anaplasmosis, and Powassan disease, this small arthropod packs powerful poison.Image by Jim Gathany/CDC

Babesia microti, a relative of the parasite that causes malaria, causes the babesiosis infection. While some people have no symptoms when infected, in others, the illness can be fatal. Symptoms of babesiosis include fatigue and weakness, nausea, diarrhea, and often a high fever. More severe complications include kidney damage and heart failure.

Because babesiosis is spread by I. scapularis, the geographic range of the infection is expanding along with the tick. While ticks are the agent, or “vector,” that spreads the bacteria, rodents like white-footed mice are the reservoir culprits who carry the disease. Ticks are infected when they feed on mice, and in turn, ticks infect white-tailed deer, that then become the primary hosts for tickborne infections carried by black-legged ticks.

The blacklegged tick (Ixodes scapularis) is widely distributed in the northeastern and upper midwestern United States.Image via CDC

Here are some of the findings of the new babesiosis report:

  • The length of time between infection to symptoms can be about two weeks, with 96% of cases reported between April and October.
  • Between 2001 and 2015, there were 430 cases reported in Wisconsin. Of those, laboratory testing confirmed 68%. For the victims with confirmed cases, 158, or 65%, were hospitalized, and three people died as a result of the infection.
  • Of the 108 patients with probable babesiosis, 24% were hospitalized, and none died.
  • Wisconsin did not begin screening its blood supply for the babesiosis parasite until 2016. Before that, three cases of the infection spread through transfusion with contaminated blood.

The threat is rising. Between the years of 2001–2003 and 2004–2006, there was a 400% increase in the mean annual incidence of babesiosis cases. The rate rose incrementally after that until it jumped again between 2007–2009 and 2010–2012 with a 235% increase.

Overall, the incidence rose 2600% between 2001–2003 (o.03 mean annual incidence) and 2013–2015 (0.80 mean annual incidence).

Number and incidence of reported confirmed babesiosis cases by 3-year interval and percentage confirmed using polymerase chain reaction (PCR) — Wisconsin, 2001–2015. Mean annual incidence is the average number of cases per 100,000 residents in a single year.Image by MMWR, July 7, 2017/66(26);687–691

The number of counties reporting the incidence of babesiosis rose from 20 to 46 between 2011 and 2015.

Geographic distribution of confirmed cases of babesiosis per 100,000 residents by county of residence — Wisconsin, 2001–2005, 2006–2010, and 2011–2015.Image by MMWR, July 7, 2017/66(26);687–691

This report and physical observations of ticks on hunter-harvested deer, support the finding that the range of the black-legged tick has expanded rapidly, and will continue to do so with a warming climate and clearance of forest stands. As essential the ticks, so go the infections they transmit to humans.

Study authors write: “Babesiosis cases in Wisconsin are increasing in number and geographic range. These trends might be occurring in other states with endemic disease, similar suburbanization, and forest fragmentation patterns, and warming average temperatures.”

If you have reason to believe a tick could have bitten you, and experience symptoms, contact your doctor. Prompt treatment is important. The best defense to tick infection is offense — use repellent containing DEET, stay clear of tick territory, wear long sleeves, and pants — and most important, shower and check for ticks each time you return from time in the wild — or just your backyard.

With warming temperatures, ticks are getting worse — readiness is the best way for you, and family members, to avoid infection.


**For more on Babesia:  https://madisonarealymesupportgroup.com/2016/01/16/babesia-treatment/

https://madisonarealymesupportgroup.com/2011/09/25/the-babesia-checklist-copyrighted-2011-james-schaller-md-mar-version-20/

https://madisonarealymesupportgroup.com/2016/12/15/blood-screening-for-babesia/

https://madisonarealymesupportgroup.com/2016/06/17/babesia-cure/

https://madisonarealymesupportgroup.com/2016/12/05/babesia-cure-update/

https://madisonarealymesupportgroup.com/2016/10/31/the-gift-that-keeps-giving-wisconsin-organ-donor-gives-babesiosis-to-two-recipients/

IDSA Founder Used Potent IV Antibiotics for Chronic Lyme

Dr. Burton Waisbren Sr. of Milwaukee, Wisconsin is no longer with us but he would be speaking out about the CDC’s recent paper in the MMWR of five case reports of people who developed complications with IV antibiotics for Lyme disease. https://www.ncbi.nlm.nih.gov/pubmed/28617768https://www.ncbi.nlm.nih.gov/pubmed/28617768

A founding member of the IDSA, Waisbren disagreed with their stance that Lyme is hard to get and easy to treat, is not persistent, and that IV antibiotics are too dangerous to use as a treatment option.

In his book, Treatment of Chronic Lyme Disease, he discusses 51 difficult cases, nearly all Chronic Lyme disease sufferers that had been misdiagnosed with everything from ALS to mental disorders. They had all been neglected by main stream medicine that was following the CDC/IDSA stringent guidelines of essentially 21 days of doxycycline.

Interestingly, Waisbren stated, “Back in the 1950’s, when many of these drugs were first coming out, infectious disease doctors studied and used them widely,” he says. “We would put children with rheumatic fever on penicillin for twenty years or more to prevent strep throat and it (the penicillin) did not hurt them,” he says. https://www.uppitywis.org/blogarticle/making-difference-milwaukee-doctor-chronicles-silent-epidemic

In regard to IV antibiotic treatment for Lyme disease and other tick born illnesses, Waisbren used it often – and heavy doses at that.  In fact, in essay 10 of his book he gives two protocols to be considered for the treatment of chronic LD that includes 6-8 grams of IV ceftriazone for at least 6 weeks and longer if the syndrome has entrenched itself for over a year or if the response is coming along slowly. In tandem with the IV antibiotics he typically also used doxycycline, an erythromycin, Diflucan, Flagyl, Valtrex, and gamma globulin. When there was not a satisfactory clinical response he would treat Babesia with Mepron and/or other antimalarials. For evidence of intransigent bartonellosis (Bell’s palsy of the face and gut, and chronic dermatitis) he would add rifampin and sometimes intravenous genamicin.

That’s a far cry more than the CDC/IDSA mono treatment mandate of doxycycline.

There were no IV complications mentioned at all in his book from the myriad of patients he treated.

Here’s another case:  https://madisonarealymesupportgroup.com/2017/06/26/important-example-of-iv-antibiotics-for-lymemsids/   Initially diagnosed with dementia, “Once home, McGhee, who had begun receiving two weeks of IV antibiotics, seemed to be getting better. His confusion began to clear, his short-term memory improved and his tremors abated. ‘I could feel myself recovering,’ he recalled.”  This link also shows that Lyme/MSIDS can often present as dementia, ALS, Lupus, MS, and numerous other autoimmune diseases.  

About testing he states that the Western Blot appears to be the most positive finding in clinical LD, but…“setting arbitrary level of antibodies to diagnose a disease that has not been amenable to Koch’s postulates seems open to question.  By the same token, ignoring antibody results unless they meet arbitrary levels seems suspect.  The vast majority of patients in this series showed some WB antibody exposure, but many did not meet the arbitrary limits set….in our present state of knowledge, the diagnosis of chronic Lyme disease is a clinical one.  Many of the patients in this series have suffered serious ‘hurts’ when they have been told that they could not have LD because their WB did not meet arbitrary limits.”  

Waisbren gives a stern warning that the public should insist that any new Lyme vaccine be devoid of peptides that mimic those present in humans as this is a potential problem as researchers do not know whether the vaccine can cause molecular mimicry which in turn can cause autoimmunity and circulation with myelin T-cells.  For more:  https://madisonarealymesupportgroup.com/2017/01/26/lyme-vaccine-to-be-tested-on-humans/

Waisbren states in his foreword, “I have to come to the conclusion that there is an epidemic of chronic Lyme disease occurring in the United States that warrants more attention than it is getting from the government and the academic medical establishment. It is hard for me to believe that 51 cases of what I call the chronic Lyme disease syndrome represent a figment of my imagination….I suggest that those who doubt that the Lyme disease syndrome exists and that it can be treated turn to the over 200 peer-reviewed references included in summary articles written by two giants in the Lyme disease field: Dr. B.A. Fallon and Dr. Steven Phillips.”

If Waisbren thought chronic Lyme disease was an epidemic in 2011, what would he think now?

For more rebuttals to the MMWR article:

https://madisonarealymesupportgroup.com/2017/06/23/no-bias-in-mmwr-for-any-other-infectious-disease-requiring-iv-antibiotics-except-for-lyme/

https://madisonarealymesupportgroup.com/2017/06/19/stricker-johnson-rebuttal-to-article-in-mmwr/

https://madisonarealymesupportgroup.com/2017/06/21/ilads-rebuttal-to-mmwr-article/

https://madisonarealymesupportgroup.com/2017/07/01/dr-maloney-comments-on-mmwr-article/

https://madisonarealymesupportgroup.com/2017/06/26/lorraine-johnson-interview-on-cdc-mmwr-article/

https://madisonarealymesupportgroup.com/2017/07/01/dr-shor-on-mmwr-article/

https://madisonarealymesupportgroup.com/2017/06/19/lees-rebuttal-to-cdc-article-in-mmwr/

CDC Advises Multiple Lyme Tests Due to False-negative Results

http://wtnh.com/2017/06/30/officials-this-summer-expected-to-be-worst-tick-season-ever/

News8 wtnh.com June, 2017

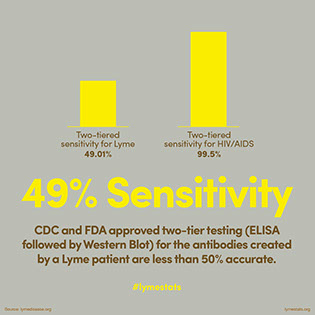
The CDC states one Lyme test may not be enough and to be cautious with false-negative results from Lyme disease tests after getting a tick bite.  The test in the early stages only tests positive from 29-40% of the time.  

Lyme disease testing can be negative in the first month following infection and this is because we’re really waiting for the human immune response to mount in response to the infection,” said Claudia Molins, a CDC Microbiologist.


**Doctors who suspect Lyme/MSIDS should should make a clinical diagnosis due to the inaccuracy of testing.  Empiric treatment is also  warranted:  https://madisonarealymesupportgroup.com/2017/07/12/start-treatment-if-tbis-are-suspected/

38_sensitive316x316

According to one of the most experienced Wisconsin LLMD’s, some folks never mount enough of an immune response to meet the stringent and arbitrary CDC two-tiered testing.  Often these are the sickest of patients.

The elephant in the room hasn’t budged in over 40 years.


Dr. Shor on MMWR Article

https://www.ncbi.nlm.nih.gov/pubmed/28617768#cm28617768_69799

Marzec, et al (1) described 5 cases of treated chronic Lyme disease that resulted in poor outcomes. We are concerned about 3 conclusions:

1. Characterization of chronic Lyme disease as an invalid nebulous condition

2 “…..evidence that the recommended two-tiered serologic testing is actually more sensitive the longer B. burgeorferi infection has been present”

3. “Studies have not shown that such treatments lead to substantial long-term improvements for patients.”

  1. We too are concerned about any individual whose outcomes represent complications to well-intentioned intervention. However, there is substantive support in the literature for the existence of 1. Chronic Lyme disease-Our perspective is that this represents the clinical manifestations of ongoing active infection by Borrelia burgdorferi (Bb) sensu latu complex in the setting of either chronic untreated or inadequately treated individuals. The likelihood of undiagnosed acute Lyme is increased by the infrequency of patients recalling tick bites. In one study representing CDC criteria diagnosed Lyme disease, only 14% had that recollection. (2) Not all cases of acute Lyme are associated with an erythema (EM) rash. Over 15 years, 31% of the reported surveillance cases lacked an EM rash. (3) The ILADS guidelines (4) describe the Lyme post treatment “….persistence of B. burgdorferi in specific individuals and animal models..” The 2012 Embers (5) nonhuman primate and 2014 Hodzic (6) murine studies provide evidence of persistence of Bb infection after MBC adequate courses of antimicrobials. Additional animal and human studies support this concept (references upon request). We want to emphasize that other etiologies may be causal, but that a cohort of these patients likely have a perpetuation of chronic signs and symptoms due to an active Bb infection.
  2. Sensitivity of two tiered testing in late Lyme: Based upon a 2008 study by Steere et al (7) “the sensitivity of 2-tier testing in patients with later manifestations of Lyme disease was 100%, and the specificity was 99%” Entrance criteria for late stage Lyme: “In all patients with neurologic, cardiac, or joint involvement, a serologic result positive for B. burgdorferi by ELISA and Western blot was required for case inclusion….” “Because the entrance criteria for the aforementioned analysis REQUIRED positive serologies … by definition, all patients with disseminated or persistent Lyme disease were required to have a positive serologic test result. It is disingenuous to define a condition by a positive test result and then state that the test has 100% sensitivity…” (8) By extension, the concept of seronegativity is well-documented in cases of chronic Lyme disease. (references upon request)
  3. “Studies have not shown that such treatments lead to substantial long-term improvements for patients.” A number of studies discount this claim. In 2 of the 4 NIH supported prospective human trials by Fallon (9) and Krupp (10), sub-cohort analysis showed statistically significant benefit to retreatment. In the former study 37 patients who were suspected of having active neuroborreliosis, and were treated with 10 weeks of 2gms/day IV Ceftriaxone. Pain and physical functioning improved at 12 and was sustained at 24 weeks. The authors indicated that “these benefits were felt to be independent of carefully assessed placebo effects.” In the latter study 55 patients who were felt to have active infection by Bb, with persistent severe fatigue of 6 or more months received 28 days of IV Ceftriaxone. A significant improvement in fatigue was sustained at 6 months. Other prospective trials of prolonged antimicrobial treatment were employed that revealed statistically significant improved outcomes. (11-13)

In summary, as unfortunate are the 5 cases reported by Marzec, it is this author’s belief that they should not be used to discount a real entity, chronic Lyme disease. Whether due to the lack of timely diagnosis or adequacy of intervention, the literature supports the concept of chronic active Bb infection. That the diagnostic sensitivity of the 2 tiered paradigm is flawed, and seronegative active Bb infection exists. That emphasis should be made to generate a careful differential diagnosis, proactive management with probiotics and careful monitoring in the selective utility of long term antibiotics. As such, these often disabled individuals will more readily have access to the care they deserve, with compassion and empathetic oversight.

Samuel Shor, MD, FACP President ILADS [International Lyme and Associated Diseases Society] Associate Clinical Professor George Washington University Health Care Sciences 1. Marzec NS, 2017 2. Berger BW, 1989 3. Bacon RM, 2008 4. Cameron DJ, 2014 5. Embers ME, 2012 6. Hodzic E, 2014 7. Steere AC, 2008 8. Stricker RB, 2008 9. Fallon BA, 2008 10. Krupp LB, 2003 11. Cameron D, 2008 12. Wahlberg P, 1994 13. Oksi J, 1998
PermalinkShare