Archive for the ‘Treatment’ Category

‘Brain on Fire’ Cases Epitomize Benefits of Dual-trained Doctors

https://www.utsouthwestern.edu/newsroom/articles/year-2018/brain-on-fire.html?fbclid=IwAR0mMorVXdusRc88gqePYP0J5ERh0Jx_R3vpvqdPcbSctwsyTjk_CSNh_j4

‘Brain on Fire’ cases epitomize benefits of dual-trained doctors

Rare program looks to expand blended expertise in psychiatry, neurology

(Video here)

Story highlights

  • New program addresses national shortage of physicians with combined training in psychiatry, neurology
  • Integrated knowledge helps doctors diagnose conditions with overlapping symptoms

DALLAS – Nov. 29, 2018 – Glen Carter woke up on a white linen bed inside a psychiatric unit, the excruciating pain in his shoulder mingling with a growing sense of alarm.

How had he arrived here? What was wrong with his shoulder?

Mr. Carter later learned he had driven to UT Southwestern for help and had been acting erratically – hearing voices, seeing visions, and sputtering to doctors thoughts of his imminent death.

“I had no recollection of any of it,” said Mr. Carter, 58.

Glen Carter

Glen Carter (left) had been a pillar of stability for his children (middle) and wife Janet (far right) until last year when he began behaving increasingly erratic. A UT Southwestern doctor determined Mr. Carter was not schizophrenic but instead had a rare autoimmune disorder.


The uncharacteristic behavior indicated a potential case of schizophrenia, yet his doctor noticed a few factors that didn’t add up. For instance, the longtime husband and father of two had no history of mental illness and had a severely dislocated shoulder usually only seen after major trauma such as car accidents or seizures.

The doctor ordered X-rays, brain imaging, and other tests that confirmed his suspicion: Mr. Carter did not have schizophrenia but rather a rare form of brain inflammation that would not have been reversed with antipsychotic medication.

“The shoulder was a big clue, then we noticed a bite mark on the side of his tongue that indicated he probably had a seizure,” said Dr. Robert Weir, who last December diagnosed Mr. Carter with a neurological condition called autoimmune encephalitis. “He responded remarkably well within a day of putting him on high-dose steroids, and he was soon able to resume his life as normal.”

Mr. Carter was the beneficiary of a blend of medical training that until recently was only offered to a select group of doctors on the East Coast: combined certification in psychiatry and neurology. Following a lengthy national moratorium that prevented medical schools from adding the dual training, the country’s newest such program at UT Southwestern represents a modest but notable step in filling a lingering national shortage of physicians skilled in the two fields.

The effects of the shortage are sometimes as benign as a slightly delayed diagnosis, but in extreme cases, patients may bounce from clinic to clinic and meander through a series of misdiagnoses and ineffective treatments, wreaking havoc on their personal and professional lives. A similar ordeal was publicized in the autobiography and subsequent film “Brain on Fire,” the story of a journalist who was mislabeled as having a primary psychotic disorder until she – like Mr. Carter – was diagnosed with autoimmune encephalitis.

Coming up on the one-year anniversary of Mr. Carter’s diagnosis, the bond broker is enjoying a holiday season much different than the last, when his normally joyous time with family and friends was riddled with emotional distress and medical mystery.

Dr. Robert Weir

Dr. Robert Weir helped develop the curriculum for UT Southwestern’s combined residency program for neurology and psychiatry.


Dr. Weir is encouraged to hear about the impact his expertise had on Mr. Carter, who no longer needs treatment for the condition and hasn’t missed any significant time from work this year.

“The term ‘mental illness’ is thrown around a lot and frequently misused,” said Dr. Weir, who helped develop the curriculum for UT Southwestern’s combined residency program for neurology and psychiatry. “People with certain conditions are sometimes misdiagnosed and undertreated because we can’t tell them on a biomolecular level what’s really happening to them.”

Filling the gap

Only five medical centers across the country offer the combined training, each one producing less than a handful of doctors a year – not nearly enough to cover the country’s vast expanse of patients who could benefit from their integrated skills.

UT Southwestern took its first step to create the curriculum after the national board that certifies these programs lifted a five-year moratorium on submitting applications in 2014, due to a change in certification protocol.

The addition of the Dallas-based program – the only one approved since the freeze was lifted – will only slightly help the overall physician numbers. However, it will likely play a crucial role in expanding access for patients who don’t live out East. Other programs are at places such as Brown University and the University of Massachusetts.

 “That’s one of the reasons why we’re so excited about creating this combined residency,” said Dr. Adam Brenner, Co-Director of UT Southwestern’s program. “The odds are greater that doctors will stay near where they’re trained, which is important because this training hasn’t existed in Texas and most other parts of the country.”

Dr. Adam Brenner

Dr. Adam Brenner, Professor of Psychiatry


UT Southwestern offers a six-year combined residency for doctors that includes a clinical track dividing time between neurology and psychiatry. The expertise has been helpful in diagnosing patients like Mr. Carter with rare autoimmune disorders, as well as a number of other conditions with overlapping symptoms, including epilepsy, Alzheimer’s disease, multiple sclerosis, and Parkinson’s disease.

The creation of the country’s newest program comes amid a growing push to utilize neurology tools in psychiatry, including an award-winning approach to objectively diagnose and treat different types of psychoses through evaluating neural images and electrical activity in the brain, among other strategies. National clinical trials are also providing early glimpses into how these high-tech tools – including magnetic seizure therapymay impact treatment in depression and psychosis.

“It’s an exciting time to be involved in psychiatry and neurology,” said Dr. Weir, who is in the fourth year of the combined residency program he spearheaded. “Our technology is finally catching up to our curiosity.”

‘A desperate need’

Mr. Carter had been a pillar of stability for his family. The breadwinner, the caring husband, the father who helped raise two children.

Then his life unraveled last year when he began having hallucinations. He took anxiety medications, but his condition only worsened in the following months. On one occasion he thought he was having a heart attack. Another time he asked his wife if she could hear God talking to her too.

“He was asking to go to the hospital, but even after a few trips to the emergency room we couldn’t put our finger on it,” said Janet Carter, Mr. Carter’s wife of 28 years. “This was nothing like Glen Carter.”

Her husband reached a breaking point on Dec. 8, 2017. Shortly after arriving at work, he drove himself to UT Southwestern and was admitted into the psychiatric unit, where Dr. Weir was on rotation that month.

Glen and Janet Carter

Glen (left) and Janet Carter had tried for months last year to pinpoint the reason for Mr. Carter’s increasingly erratic behavior. He was eventually diagnosed with an autoimmune disorder at UT Southwestern.


Dr. Weir recalls Mr. Carter acting strangely, taking his clothes off and putting them in the shower, predicting his own death within 12 hours, and hearing voices in his head.

“None of that is very odd with psychotic behavior, but some things just didn’t add up,” Dr. Weir said. “He had been previously healthy and had a very abrupt change in behavior.”

Mr. Carter’s injured shoulder, likely dislocated during a seizure, set Dr. Weir on the path to solve the mystery that had perplexed the family for months. He was not schizophrenic after all. He suffered from autoimmune encephalitis, which occurs when the body’s immune system attacks healthy brain cells and inflames the brain, sometimes prompting psychiatric symptoms.

Mr. Carter was given steroids – a treatment that normally could be harmful to a hallucinating patient – and was back to normal within several days.

“I was in a desperate need,” Mr. Carter said during a recent visit to UT Southwestern to share his story. “I honestly don’t know how I got through this without losing my dignity. … We’re very grateful for what took place here.”

Growing demand

Mr. Carter’s case is not unique.

One study indicates at least 3 to 5 percent of psychotic behavior first seen in patients is due to an autoimmune condition.

How many of those patients are accurately diagnosed the first time and put on proper treatment is more difficult to determine.

Although awareness of autoimmune encephalitis has improved since the “Brain on Fire” book published in 2012, some doctors anticipate the demand will only grow for combined training in neurology and psychiatry.

“These two specialties have an area of overlap,” said Dr. Brenner, Professor of Psychiatry at UT Southwestern’s Peter O’Donnell Jr. Brain Institute. “And patients with conditions in this overlap sometimes really benefit from having one doctor who can encompass the whole picture. I’m confident that when Dr. Weir and others finish their residency, other medical students will see their work and want to follow in their path.”

About UT Southwestern Medical Center

UT Southwestern, one of the premier academic medical centers in the nation, integrates pioneering biomedical research with exceptional clinical care and education. The institution’s faculty has received six Nobel Prizes, and includes 22 members of the National Academy of Sciences, 17 members of the National Academy of Medicine, and 15 Howard Hughes Medical Institute Investigators. The faculty of more than 2,700 is responsible for groundbreaking medical advances and is committed to translating science-driven research quickly to new clinical treatments. UT Southwestern physicians provide care in about 80 specialties to more than 105,000 hospitalized patients, nearly 370,000 emergency room cases, and oversee approximately 2.4 million outpatient visits a year.

___________________

**Comment**

This is wonderful news.  There has been a dearth of specialized doctors qualified to diagnose this condition which has been known to be a part of the Lyme/MSIDS picture:  https://madisonarealymesupportgroup.com/2017/10/01/panspandas-steroids-autoimmune-disease-lymemsids-the-need-for-medical-collaboration/

Within this link boy’s Lyme Disease Morphs into Autoimmune encephalopathy. It took 10 years and 20 doctors to find out 12-year-old Patrik had Lyme disease. Just 4 months later the doctors discovered he also has a condition where his immune system attacks his brain. Dr. Souhel Najjar, Cahalan’s doctor, heroically saves the day again.  (Video within link)

According to a prominent Wisconsin LLMD, 80% of his patients have tick borne illness along with PANS/PANDAS as well as Autism.  If a child has an abrupt change in behavior such as the man in the main article, please consider this and get him to someone trained in this area.

https://madisonarealymesupportgroup.com/2018/02/20/mysterious-disease-where-the-body-attacks-the-brain-more-common-than-initially-thought/

The treatment for autoimmune encephalitis can vary based on the trigger, but timing is always key. If doctors treat whatever is triggering the condition, many people with the disease can go on to lead fairly normal, full lives.

For more:

https://madisonarealymesupportgroup.com/2017/10/08/misdiagnosed-how-children-with-treatable-medical-issues-are-mistakenly-labeled-as-mentally-ill/

https://madisonarealymesupportgroup.com/2018/07/28/stories-of-pandas/

https://madisonarealymesupportgroup.com/2018/11/06/diagnosing-treating-autoimmune-encephalitis-in-patients-with-persistent-lyme-symptoms/

https://madisonarealymesupportgroup.com/2018/10/10/pans-pandas-awareness/


Everything That’s Known About Ehrlichiosis

https://www.news-medical.net/health/Epidemiology-of-Ehrlichiosis.aspx

Epidemiology of Ehrlichiosis


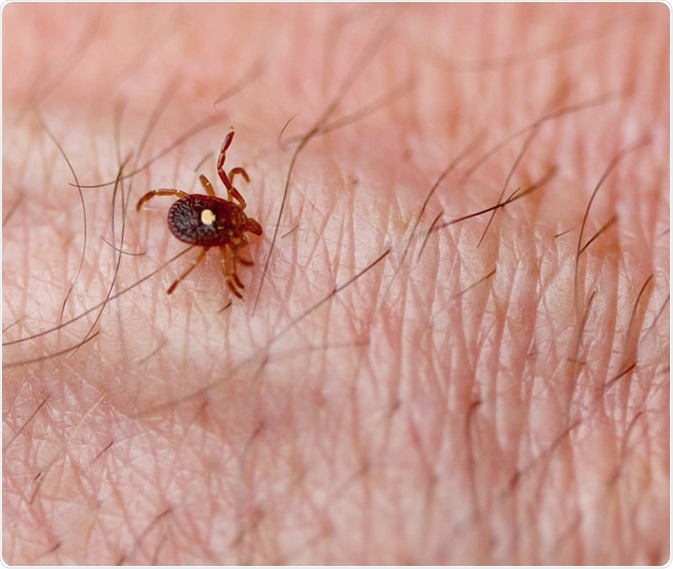
Ehrlichiosis is a disease caused by several Gram-negative obligate intracellular bacteria that are transmitted by a tick vector. The frequency of ehrlichiosis is increasing, which is ascribed to the increased awareness and diagnostic availability, as well as the expansion of regions populated with the most common tick vector – Amblyomma americanum (also known as the Lone Star tick).

Lone Star Tick (Amblyomma americanum). Image Credit: Melinda Fawver / Shutterstock

Symptoms of the disease usually include fever, anorexia, headache and myalgia, with a relatively low incidence of rash (present only in 20% of affected individuals). The knowledge of disease epidemiology is vital, as early recognition may prevent a large number of cases (and thus avoid rare fatal outcomes).

Generally, the median age for acquiring ehrlichiosis is 51-53 years, while Caucasian males are the most commonly affected group. Even though cases of the disease are found year-round, the greatest number is observed between May and August, which coincides with periods of abundant populations of ticks and human open air recreation.

Epidemiology of Human Monocytic Ehrlichiosis

Human monocytic ehrlichiosis (caused by the species Ehrlichia chaffeensis and Ehrlichia canis) was initially described in 1986, and almost three thousand cases have been reported to the U.S. Centers for Disease Control and Prevention (CDC) in the last three decades. Even though the average incidence of this disease in the United States is 0.7 cases per million inhabitants, this estimation is based on passive surveillance and probably represents substantial underestimation of the actual incidence.

For example, in one seroprevalence study conducted on children it was demonstrated that 20% of infected individuals from endemic areas had detectable antibodies to Ehrlichia chaffeensis, without any previous history of apparent clinical disease. This is in line with the finding that more than two-thirds of all infections with causative agents of human monocytic ehrlichiosis are either without any symptoms or minimally symptomatic.

Akin to other tick-borne illnesses, the distribution of arthropod vectors and reservoirs in vertebrates highly correlates with the disease occurrence in humans. The predominant zoonotic cycle of Ehrlichia chaffeensis is comprised of infected white-tailed deer as the reservoir and Amblyomma americanum as the tick vector, both prevalent across southcentral and southeast United States.

This tick also has three feeding stages (known as larval, nymph and adult stages), and each developmental representative feeds only once. Transstadial transmission of Ehrlichia can be seen during nymph and adult feeding, because larvae are uninfected. Unlike some other species (most notably Rickettsia), Ehrlichia cannot be maintained via trans-ovarial transmission pathway.

Epidemiology of Human Granulocytic Anaplasmosis

In the 1990s certain patients from Wisconsin and Michigan with a history of tick bite presented with a febrile illness similar quite similar to human monocytic ehrlichiosis. These cases were characterized by inclusion bodies in granulocytes rather than agranulocytes (monocytes), which is why this syndrome was initially named human granulocytic ehrlichiosis. After recent reclassification of Ehrlichia phagocytophilum to the genus Anaplasma, the disease has been renamed to human granulocytic anaplasmosis.

The annual number of human granulocytic anaplasmosis cases exceeds those of human monocytic ehrlichiosis, with an incidence case rate of 1.6 per million inhabitants in the U.S. As with Ehrlichia chaffeensis, different serosurveillence studies evince that asymptomatic disease is quite common. The disease is primarily caused by Anaplasma phagocytophilum.

This disease is seen in Europe as well, where the majority of cases is found in central Europe (e.g. Slovenia) and Scandinavian countries (e.g. Sweden), though individual reports have come from other countries as well. Nonetheless, there is limited knowledge as to the exact epidemiological features and implicated animal reservoirs in Europe.

Different ticks transmit human granulocytic anaplasmosis in different continents; Ixodes scapularis and Ixodes pacificus are the predominant tick species in the United States, Ixodes ricinus in Europe, while Ixodes persulcatus transfers the infectious agent in Asia. Small mammals (such as White-footed mouse and Dusky-footed wood rat) are primary reservoirs of the disease.

Epidemiology of Ehrlichia ewingii

The epidemiology of Ehrlichia ewingii is usually addressed separately as there are certain problems with this species, such as the absence of specific serological tests and the lack of adequate reporting systems. What we do know is that most infections have been observed in immunosuppressed patients (after organ transplantation) and in those infected with human immunodeficiency virus (HIV).

The primary vector for Ehrlichia ewingii is the Lone Star tick, as for Ehrlichia chaffeensis. Most human cases of the disease have been documented in Missouri, Oklahoma and Tennessee in the United States, although infection has been described in dogs and deer throughout the range of the tick that transmits the disease, suggesting that the infection with this specific species might be even more widespread.

Pathophysiology of the Disease

Infection with bacterial species causing ehrlichiosis occurs when the extracellular infectious form of the organism is taken up by the host cell. These infectious forms are either the elementary body or the dense core, and are taken up by the cell via a process known as endocytosis. Once inside the cell, the infecting organism divides and matures until it forms a reticulate body/reticulate core, and then a morula; these are then redifferentiated again into an elementary body/dense core so it can leave the infected host cell and spread further.

During this process, Ehrlichia and Anaplasma utilize a range of immune evasion mechanisms, such as suppression of apoptosis in host cells, down-regulation of recognition receptors in the host that could enable clearance of the infection, as well as modulation of cytokine and chemokine responses. Some species have a preference for granulocytic cells (Anaplasma phagocytophilum and Ehrlichia ewingii), while others target mononuclear phagocytes (Ehrlichia chaffeensis and Ehrlichia canis)

Furthermore, multisystem involvement is also a potential consequence, as microorganisms are found in the spleen, bone marrow, lymph nodes and peripheral blood. In fact, all the clinical manifestations are thought to be a result of a host inflammatory response to disseminated infection, rather than because of direct bacteria-induced damage.

Clinical Presentation

Patients with ehrlichiosis (regardless of the putative organism) clinically present with fever, chills, severe headache, confusion, malaise, nausea, vomiting, and generalized body aches. Respiratory symptoms such as cough may also be observed, but they are more common in adults than in  children.

Symptoms are typically seen one to two weeks following a tick bite, with a median of nine days. The problem with tick bites is that they are usually painless, and therefore many people do not even remember being bitten. Due to immune suppression, secondary infections (usually caused by cytomegalovirus or fungi) are also frequent in severely diseased patients.

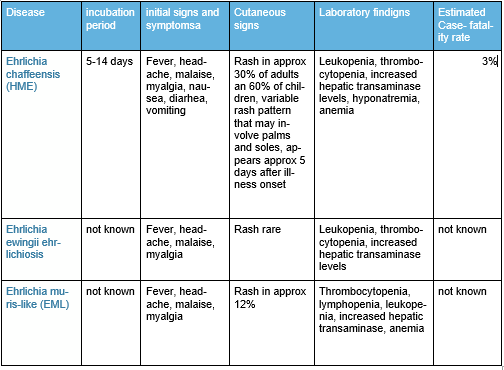
In approximately one-third of individuals with ehrlichiosis there is a visible rash that is maculopapular or petechial. The rash is more commonly observed in children and typically develops five days after fever ensues. If present, the rash typically spares the palms, soles and the face.

Akin to rickettsial infections, central nervous system involvement may occur in up to 20% of affected individuals, including dangerous manifestations like meningoencephalitis. Moreover, in some patients the disease may advance to acute respiratory distress syndrome or a shock-like presentation coupled with bleeding disorders and cardiovascular instability.

However, the overall death rate is substantially lower in ehrlichiosis when compared to rickettsial diseases. According to the data published by U.S. Centers for Disease Control and Prevention (CDC), the mortality rates in patients who are seen by a healthcare professional due to ehrlichiosis range from 1% to 3%.

On the other hand, a large number of patients may be infected with Ehrlichia and Anaplasma, but do not come for medical evaluation; therefore, these percentages may be overestimations of mortality. Naturally, immunocompromised individuals, elderly and those previously treated with sulfonamide antibiotics are at higher risk of more severe disease.

Differential Diagnosis

Since ehrlichiosis is a multisystem disease characterized by protean manifestations (i.e. without pathognomonic and highly characteristic clinical features), the differentials are often quite broad. Initial symptoms are often generalized and somewhat vague, which is why the illness may first be diagnosed as a possible “viral syndrome” in the context of upper respiratory infection, gastroenteritis and/or meningoencephalitis.

A history of tick exposure or tick bite in the recent past can be elicited from a majority of patients, but it is important to emphasize that this feature may be absent in up to 30% of all cases. Therefore, pursuing other appropriate diagnostic procedures to confirm this disease is of the utmost importance.

Pancytopenia (i.e. an abnormally low count for all three types of blood cells) is a hallmark laboratory finding of human ehrlichiosis during the early days of the disease.

  • leukopenia (mild or moderate) in 70% of patients (with the most significant decline being in the lymphocyte population) during the first week.
  • Anemia in 50% of acute patients
  • Low platelet count
  • elevated liver transaminases

The next step towards accurate diagnosis is making blood smears from peripheral blood, cerebrospinal fluid or bone marrow, which are stained with Giemsa or Wright’s stains to detect specific bacterial structures known as morulae.

Albeit this technique is rapid, it is rather insensitive in comparison to other confirmatory tests, and particularly in immunocompetent patients who have extremely low bacterial loads in blood and body organs.

The Use of Serology

The most sensitive method of infection confirmation is a seroconversion or a 4-fold change in antibody titers during the convalescent phase of the disease.

Specific serologic testing of IgM and IgG antibodies to Ehrlichia chaffeensis or Anaplasma phagocytophilum by means of indirect immunofluorescence assay is considered the “gold standard” and thus the most frequently employed confirmatory test.

Nonetheless, serology has its limitations, and these include a negative IgG test and uninformative levels of IgM titers in 80% of affected individuals during the first week of the disease, a high false positive rate, seroconversion failures due to weak immune function, as well as alteration of antibody response because of early antibiotic treatment.

Molecular Diagnostic Procedures

Due to high specificity and sensitivity values, as well as a very rapid turnaround time, polymerase chain reaction (PCR) became the preferred test for confirming serology findings indicative of human monocytic ehrlichiosis and human granulocytic anaplasmosis.

The use of PCR is especially important in the detection of early stages of infection, when antibody levels are low or undetectable.

A large number of kits are commercially available for whole blood PCR testing, which enables rapid diagnosis in up to 85% of infected individuals. Recent advances in molecular research even allow multiplex testing that can identify several agents of ehrlichiosis from one test.

Laboratory Culture

Although the possibility of culturing Ehrlichia and Anaplasma species is also available to clinicians and researchers, the isolation of these organisms requires cell lines and typically takes 2-6 weeks of incubation.

The sensitivity of this approach for the isolation of Ehrlichia chaffeensis is very low when compared to PCR, but higher (and almost comparable to PCR) for Anaplasma phagocytophilum.

The major pitfall of the laboratory culture approach is the paucity of competent laboratories, since this technique necessitates unique and antibiotic-free cell culture methods that are not usually available in clinical microbiology laboratories.

In addition, prior treatment with doxycycline or some other antimicrobial drugs lowers the sensitivity of culture to a greater degree when compared with blood smear analysis or PCR.

Immunohistochemistry

This is another confirmatory technique and is especially valuable when the diagnosis is to be made before antibiotic treatment is begun, or at least within 48 hours of its initiation. It can also be applied to bone marrow and autopsy specimens.

All those factors have to be taken into account when assessing patients with suspected ehrlichiosis, which is the reason why some propose combining different diagnostic methods to increase the likelihood of early diagnosis. Naturally, clinicians always have to consider other diseases that have similar clinical and laboratory findings to ehrlichiosis.

Treatment Options for Ehrlichiosis

Ehrlichia chaffeensis and Ehrlichia canis, the causative agents of human monocytic ehrlichiosis, are susceptible to all tetracycline antibiotics and their derivatives. These drugs exhibit broad spectrum activity by binding to bacterial ribosomes and inhibiting protein synthesis by interrupting peptide chain formation. A plethora of other human pathogens (such as rickettsiae, borreliae, chlamydiae, as well as some mycobacterial and protozoal species) are susceptible to tetracyclines as well.

Treatment considerations for human granulocytic anaplasmosis are similar to those for human monocytic ehrlichiosis, with tetracyclines being very effective against Anaplasma phagocytophilum and Ehrlichia ewingii. The possibility of Babesia co-infection often has to be considered, which means monotherapy is sometimes not sufficient.

In both groups of diseases treatment response is usually rapid. Therefore, an alternative diagnosis should be considered if fever persists for more than 72 hours after the initiation of appropriate antibiotics. Even though research studies did not specifically address recommended treatment duration, many experts advocate continued antibiotics for 3-5 days after fever abates, and perhaps even longer (up to 14 days) if there were signs of central nervous system involvement.  (Please see my comment at end of article)

A particular challenge for clinicians is ehrlichiosis in pregnancy, as tetracyclines are contraindicated in this population. Antibiotic sensitivity studies show that certain anti-tuberculous drugs have bactericidal activity in vitro against Ehrlichia and Anaplasma. This is also a viable and appropriate alternative approach in pregnant women.

Since clinical experience with other drugs that show activity in vitro is lacking, there are no fixed treatment recommendations for children younger than eight years of age, as well as for individuals who are hypersensitive to tetracycline drugs. Furthermore, there is no clinical data on the potential usefulness of adjunctive corticosteroid application to suppress the inflammatory manifestations of the disease.

Pertinent Prevention Strategies

Avoiding tick bites and removing any adherent tick immediately are the first steps in disease prevention. Individuals who reside in endemic areas are advised to wear long sleeves and light colored clothing during outdoor activities, since the latter permits easier visualization of crawling ticks. Adults at high risk of tick bites should apply repellents such as N,N-diethyl-meta-toluamide (commonly known as DEET) or permethrin to prevent this.

After visiting tick-infested regions, a careful inspection of body, hair and clothes should always be done with immediate removal of attached ticks. Research studies have demonstrated that a period lasting from 4 to 24 hours after infected ticks attach to the host is possibly essential for the  successful transmission of Ehrlichia and Anaplasma. Hence, swift and thorough removal of attached ticks is of the utmost importance for preventing transmission and subsequent disease.

At the moment there are no commercially available or experimental vaccines for prevention of either human or veterinary ehrlichiosis. In conclusion, it has to be emphasized that the diagnosis of ehrlichiosis necessitates a high level of suspicion, which is why it is often made retrospectively, with potentially dire consequences for the affected individuals in rare cases.

Sources

Sources for treatment and prevention

_________________

**Comment**

Lyme/MSIDS patients are often coinfected with numerous pathogens making them immunocompromised.  Cortico-steroids are not recommended for this population.  Also, as a rule, ILADS (International Lyme and Associated Diseases Society) recommends longer treatment and numerous antimicrobials due to the polymicrobial nature of tick-borne illness as well as the fact many of these pathogens are persistent.

For another great read:  https://www.lymedisease.org/ehrlichiosis-tick-borne-disease-no-one-heard/  The author brings up a valid point about the potential of there being undiagnosed Ehrlichia behind a ME/CFS diagnosis in a subset of patients since it infects white blood cells and the mitochondria.  The article also gives helpful percentages of symptoms and the following information:

Other symptoms of ehrlichiosis can include:

  • Fever/chills and headache (majority of cases)
  • Fatigue/malaise (over two-thirds of cases)
  • Muscle/joint pain (25% – 50%)
  • Nausea, vomiting and/or diarrhea (25% – 50%)
  • Cough (25% – 50%)
  • Confusion or brain fog (50% of children, less common in adults)
  • Lymphadenopathy (47% – 56% of children, less common in adults)
  • Red eyes (occasionally)
  • Rash (approximately 60% of children and 30% of adults)

Other modes of transmission

Ehrlichia chaffeensis has been shown to survive for over a week in refrigerated blood. Therefore these bacteria may present a risk for transmission through blood transfusion and organ donation. It has also been suggested that ehrlichiosis can be transmitted from mother to child, and through direct contact with slaughtered deer. (14, 15)

Summary of Ehrlichiosis

As you can see from this nifty table, much is UNKNOWN.  This right here is another example of research begging to be done.  The results would be practical, effectual, and essential in treating patients – unlike climate data which will only line the pockets of research institutions.  Remember Zika?  It caused a media blitz with research being done everywhere.  As you can see from this article, Ehrlichia can be deadly and is spreading.  Why no news and research?

For more:  https://madisonarealymesupportgroup.com/2018/10/15/ehrlichiosis-masquerading-as-thrombotic-thrombocytopenia-purpura/

https://madisonarealymesupportgroup.com/2018/10/02/north-carolina-ehrlichia-often-overlooked-when-tick-borne-illness-suspected/

https://madisonarealymesupportgroup.com/2018/07/24/oklahoma-ehrlichiosis-central/

https://madisonarealymesupportgroup.com/2018/03/09/dogs-ehrlichiosis/

https://madisonarealymesupportgroup.com/2018/11/11/gestational-lyme-other-tick-borne-diseases-dr-jones/

FREE Book on LYME

https://rawlsmd.com/books/unlocking-lyme?utm_campaign=ul-5-days-of-giving+promo_12.1.18+%28NZUqWs%29&utm_medium=email&_ke=eyJrbF9lbWFpb

Screenshot_2018-12-02 Unlocking Lyme Best-Selling Lyme Disease Book by Dr Bill Rawls

The Quantum World, Rife Machines & Lyme Disease

https://www.linkedin.com/pulse/quantum-world-rife-machines-lyme-disease-chris-newton/

The quantum world, Rife machines and Lyme disease!

Published on November 26, 2018

By Chris Newton
Research Director CIMMBER (Center for Immuno-Metabolism, MicrobioSee more
rife
Why now an interest in the strangeness of the electromagnetic (EM) quantum world and what’s the connection with ‘Rife machines’ and Lyme disease………


Quite a number of years ago now an interest in the quantum world was sparked by reading Rupert Sheldrake’s book on morphic fields and formative causation (Sheldrake, 1982). There appeared to be an awful lot going on behind the veil. Sheldrake’s work suggested (and still does, see: The Presence of the Past: Morphic Resonance and the Habits of Nature) that life is directed by information fields that may or may not, be EM in nature.

Interest in the quantum world went dormant for a while as a career was developed in biochemistry and molecular biology. (Human endeavour, even science, is conducted on very much a need-to-know basis- one focuses-down on one’s speciality, often ignoring related disciplines). Whilst still working on cancer-related cell and molecular biology in the early 2000s, some fascinating work from the early part of the 20th century came to my attention. These were studies by Royal Rife. Rife was a pioneer in the field of ‘Electromagnetic Medicine‘. He worked with cancer patients and was convinced that cancer was due to a microorganisms with characteristics somewhere between virus and bacteria (pleomorphic). He developed a new type microscope and used radio frequencies to treat not only organisms in the lab., but patients with cancer. Rife’s story is described by Barry Lynes in his excellent book, entitled, “The Cancer Cure That Worked‘.

From being ‘the darling of US medicine‘ in the early 1930s his work was stopped and his ideas and treatments were forced ‘underground‘.

My interest in Rife’s work in the 2000s was from a perspective of microorganisms and cancer (we eventually reported work showing that microorganisms and their components might ‘activate’ tumour cells (Newton et al. 2011). Later-on that decade, a good friend of mine, Dr Beryl Beynon asked whether I could help with patients suspected of having Lyme disease. Following some more literature research, I realized that a variant of Rife therapy ‘had resurfaced‘ and was being used to treat individuals with Lyme disease. Unlike the device Rife used in the 1930s, Doug MacLean- an electrical engineer who had Lyme disease- built what has become known as the Doug Coil. This device uses a fairly hefty audio power amplifier to drive, instead of a loudspeaker, a large coil of wire from which a magnetic field emanates (for technical details see CIMMBER.org.uk). We discussed this in the Clinic and following some more prompting from a friend/patient, a device was built.

Strictly, this device is not a Rife machine, it uses audio frequencies (between 200 and 2000Hz). Although there are many mentions of resonance effects (at various websites), no details as to how EM at audio frequency might couple with biological systems have been worked-out (certainly in the form of an alternating magnetic field, at audio frequencies). Despite this, the clinic has noted some marked responses and these include Herxheimer reactions; responses typical of bacterial dye-off following antibiotic therapy.

A striking aspect of the response for some patients has been a physical sensation at one frequency and not another- even when the separation between these frequencies is only 1 cycle per second (1 Hz). In electrical engineering terms, this suggests a highly specific coupling between the alternating magnetic field and a biological system- the sort of coupling one might expect between a broadcast signal and a receiving system (a receiving system tuned to the broadcast frequency). When systems are tuned in this way, there is a maximum transfer of energy between transmitter and receiver.

Returning to the quantum world, from experiments on the photoelectric effect and the absorption and emission spectra of gases, it became apparent that EM radiation (EMR), couples with electrons in the atom. For example, the Balmer series of spectral lines are due to electronic transition in the hydrogen atom. Each of these correspond to a certain transition that requires an input of energy carried by an EM wave (after an EM input, the electron drops down to a lower orbital, emitting light). This energy is often described in electron volts (eV), where 1eV is equivalent to 1.6 x 10^-19 joules of energy (joule is a unit of energy). To ionize a hydrogen atom (remove its single electron) from its ground state (a state where the electron is closest to the nucleus-also called the zero point state) requires 13.6 eV of energy.

In the early 1900s Max Planck defined a constant that when multiplied by the frequency of EM radiation gave, what Einstein in 1905 defined as a quantum of energy– the minimum unit (packet) of energy of an EM wave. This quantum of energy is also defined as a photon and it is calculated by multiplying the frequency of the EMR, by the Planck constant.

By converting eV to joules and then using the equation E =hf (where E is energy, h is the Plank constant and f, is the frequency), the frequency of EMR required to ionize hydrogen is around 3.3 x 10^15 Hz. This very high frequency corresponds a wavelength around 90nm. This is a region of the EM spectrum called vacuum UV and it is usually absorbed by the atmosphere on Earth.

Although the ground state of hydrogen requires vacuum UV light to free its single electron, what about when hydrogen it is part of a chemical structure or biological molecule like an amino acid, a protein, glucose or a molecule like NADH. Often text books on cellular energetics, have a sentence like, ‘High energy electrons are passed from NADH to the electron transport chain of mitochondria‘ (see LinkedIn article: 42: it might just as well be!: August 20th). Does this mean that electrons in NADH molecules are in an excited state (i.e. above the ground state). If so, where does the energy come from to lift two electron to an excited state and to finally release them from NADH for delivery to the electron transport chain? Also what characteristic of an electron, that when released from its atomic/molecular cage, manifests as high energy? Electrons are suggested to be particles/wave packets with very high velocity. So perhaps raising the electron to a higher atomic orbital is the result of increasing their velocity and hence kinetic energy (for the uninitiated, kinetic energy is a product of mass, multiplied by velocity squared and divided by 2!)?

When EMR couples with electrons at frequencies below vacuum UV, something else must be going on. The frequencies most often used for therapy are between 200 to 2000Hz. At 500 Hz, for example, the wavelength is around 600km and using E = hf, the photonic energy at 1000 Hz is so extremely low (6.6 x 10^-31 joules). In eV this is 4.1 x 10^-12 eV- a billionth billionth of and eV, a tiny fraction of the amount needed for an electron transition. So what’s the target of this EM wave/magnetic pulse?

One possibility is that the magnetic pulse couples with electrons that have escaped their normal atomic leash – electrons that have become delocalized. These electrons are no longer tied to one atomic nucleus, they have been released and shared between atoms in a molecular structure (how these have been released, in other words, where the energy comes from to do this will be ignored for now). Bio-molecules such as amino- acids and nucleic acids (DNA) have specialized configurations of delocalised electrons… and so too does water.

The last article published at this site (see LinkedIn article October 18th) and also at CIMMBER.org.uk, has outlined the work of Gerald Pollack and his team who have shown that water next to a charged surface (negatively charged like the majority of biomolecules and membranes) has a hexagonal structure where a proton (hydrogen ion) is lost and its electron is shared as a delocalised electron around the hexagonal ring.

Work by other groups has suggested structure of an even more bizarre form. Luc Montagnier (Nobel prize winner for work on HIV) and team reported studies where DNA diluted in water emitted signals over the frequency range, 300 to 3000 Hz (Montagnier et al., 2011). Their work also revealed that this ‘information’ could be transferred magnetically to water. When this signalized water was used as a template for a polymerase chain reaction (PCR), the original DNA sequence was reproduced with at least 98% accuracy. In several publications, they suggested structure exists in water and this stores information that is somehow able to direct DNA polymerase to reproduce a DNA sequence (see October 18th for further discussion).

As might be expected, the press of all denominations had a field day (week/month etc) over this work, especially when it was revealed that only sequences from pathogens produced signals. Despite this extreme cynicism and downright disbelief, it is hard to explain how water signalized from digital information transferred (over the web) to labs never having performed PCR on these sequences (e.g. Borrelia burgdorferi and HIV), produced near perfect sequence homology. Considering these findings, one wonders whether the correspondence between audio frequencies used in the coil system and those emitted by DNA of Borrelia might provide a mechanism for therapeutic effects. But, how?

Before answering this question, one has to consider how DNA might communicate information to water, in other words, the mechanism of signalling.

Much of the above discussion has focused a great deal on the two-way coupling/interaction between electrons and EMR. Whilst it is clear that EM fields at audio frequency hold very low photonic energy, an alternating magnetic field will induce oscillation of electrons when they have shed their leash of atomic confinement. The analogy is conduction band electrons in a conducting wire. These electrons ‘feel the force‘ when exposed to a changing magnetic field.

As mentioned, a commonality between DNA and water is that they have delocalized electrons. When the negatively charged DNA is diluted (dispersed) in water (based on Gerald Pollack’s work), at the interface between DNA and water, an EZ will form. This is composed of stacked hexagonal rings, not of H2O, but H3O2- a proton is lost (to the intervening bulk water) leaving behind an electron that becomes delocalized around the ring. DNA itself has delocalized electrons and these extend throughout the fractal structure of DNA molecule (Cattani, 2010). Indeed Martin Blank (who sadly passed away earlier this year*) and his team have shown that DNA can act as a fractal antenna (Bank and Goodman, 2011). Antennae can both send and receive EM information. However, to do so requires that electrons within antennae are placed under a variable electric or magnetic field. One key element of the Montagnier team’s work was that information transfer only occurred when the diluted DNA was exposed to an external oscillating magnetic field. Perhaps the external field acted as both an energetic EM input and carrier wave, that was modulated by electronic signals (from the base sequences within the DNA strand). The adjacent EZ may have acted as an amplifier of these weak EM signals.

The next problem is how water that has not been exposed to DNA can be signalized. Montagnier et al. have recently published a rigorous mathematical treatment of this problem (Montagnier et al., 2017). They have suggested that quantum coherence domains exist that act as some kind of quantum liquid crystal memory.

Whilst the details of the proposed memory properties of water are mathematically highly complex, it is not necessary to understand these to be able to propose a potential mechanism for the effect of audio frequencies in the Rife-type therapy.

Based on the fractal antenna nature of DNA, an external signal, by way of an alternating magnetic field that matches a resonance condition of electrons within a particular sequence of Borrelia burgdorferi, may induce DNA damage sufficient to disrupt the transcription of a key gene and this may lead to a form of bacterial programmed cell death (Peetersa and de Jonge, 2018).

Sheldrake (1982) A New Science of Life: the hypothesis of formative causation, Los Angeles, CA: J.P. Tarcher, 1981 (second edition 1985, third edition 2009). ISBN 978-1-84831-042-1.

Newton CJ, Bilko D, Stalla G, Renner U (2011) Toll receptor-mediated inflammatory system is present in tumour cells from endocrine-related tissues. Endocrine Abstracts 25: P172

CIMMBER.org.uk: under construction

Montagnier L, Aissa J, Del Giudice E, Lavallee C, Tedeschi A, Vitiello G. (2011) DNA waves and water. J. Phys.: Conf. Ser. doi:10.1088/1742-6596/306/1/012007

Cattani C (2010) Fractals and Hidden Symmetries in DNA. Mathematical Problems in Engineering Volume 2010, Article ID 507056, 31 pages doi:10.1155/2010/507056

*Martin Blank: http://www.emfsa.co.za/wp-content/uploads/2018/06/Martin-Blank-Obituary-2018.pdf

Blank M, Goodman R. (2011) DNA is a fractal antenna in electromagnetic fields. Int J Radiat Biol. 87(4):409-15. doi: 10.3109/09553002.2011.538130

Montagnier L, Aïssa J. Capolupo A , Craddock TJA, Kurian P, Lavallee C, Polcari A, Romano P, Tedeschi A, Vitiello G (2017) Water Bridging Dynamics of Polymerase Chain Reaction in the Gauge Theory Paradigm of Quantum Fields. Water 9: 339; doi:10.3390/w9050339

Peetersa SH, de Jonge MI (2018) For the greater good: Programmed cell death in bacterial communities. Microbiological Research 207: 161-169

Medical Cannabis Superior to Opioids for Chronic Pain, Study Finds

http://www.greenmedinfo.com/blog/medical-cannabis-superior-opioids-chronic-pain-study-finds?

Medical Cannabis Superior To Opioids for Chronic Pain, Study Finds

“© [Nov 4, 2018] GreenMedInfo LLC. This work is reproduced and distributed with the permission of GreenMedInfo LLC. Want to learn more from GreenMedInfo? Sign up for the newsletter here http://www.greenmedinfo.com/greenmed/newsletter.”

Sufferers of chronic pain have been faced with a perilous decision—risk a crippling addiction to opioids or find a way to live with the pain. A new clinical study has focused on medical cannabis as an alternative to opioids, and the results may be a turning point towards a safe, plant-based option for easing pain

A new study published in the European Journal of Internal Medicine represents hope for millions of sufferers of chronic pain. Researchers at the Cannabis Clinical Research Institute at Soroka University Medical Center, and Ben-Gurion University of the Negev (BGU), found that medical cannabis can significantly reduce chronic pain without adverse effects, particularly among adults aged 65 and older. Use of cannabis, aka medical marijuana, was found to be both safe and effective for elderly patients experiencing pain because of another medical condition, such as cancer, multiple sclerosis, Parkinson’s disease, Crohn’s disease, ulcerative colitis, and post-traumatic stress disorder.

One of the head researchers in this study, Prof. Victor Novack, M.D., is a professor of medicine in the BGU Faculty of Health Sciences (FOHS), as well as BGU’s Chair in Internal Medicine. He also heads the Soroka Cannabis Clinical Research Institute. According to Prof. Novack, M.D.:

“Older patients represent a large and growing population of medical cannabis users, [yet] few studies have addressed how it affects this particular group, which also suffers from dementia, frequent falls, mobility problems, and hearing and visual impairments.”[1]

The study surveyed 2,736 patients aged 65 years and older, at the inception of medical cannabis treatment, and throughout the 33-month study period. Surveys indicated the most common reasons for using cannabis were pain (66.6%) and cancer (60.8%). Methods of ingestion included cannabis-infused oils and smoking or vaporizing the herb. After six months of cannabis therapy, researchers provided a follow-up questionnaire which sought to determine any changes to pain intensity and quality of life, as well as any adverse events that were experienced. 901 of the original respondents replied.

After 6-months of medical marijuana treatment (all statistics are +/-):

  • 94% reported an improved overall condition, and a 50% reduction in pain
  • 60% reported improved quality of life, from “bad” or “very bad” to “good” or “very good”
  • 70% reported moderate to significant improvement in their condition
  • 20% of respondents stopped using opioids or reduced their dose

Notably, the most common side effects reported were mild: dizziness (9.7%) and dry mouth (7.1%), a far cry from the high-percentage of opioid-related deaths that are linked to chronic pain.[2] BGU researchers believe that utilizing cannabis may decrease the use of other prescription medications, including opioids, and encourage further research into this plant-based alternative, especially as it relates to an aging population.

Chronic pain is a problem that affects an estimated 100 million Americans.[3] It is also one of the most significant public health problems in the United States, with an estimated cost to society of $560-$635 billion annually, an amount equal to about $2,000 for every person living in the U.S.[4] Meanwhile, the nation’s growing opioid epidemic sees 1 of every 550 chronic opioid users dying within three years of their first opioid prescription.[5] While natural alternatives to deadly opiates are rarely offered by medical doctors, medical marijuana may be the drug that bridges this senseless gap. Research is beginning to mount that shows more promise than the medical establishment can long ignore.

Neuropathy is a type of chronic pain that presents as tingling and numbness in the hands and feet, often due to nerve damage from complications of cancer or diabetes, among other causes. A 2017 meta-analysis of prior studies on neuropathy found that cannabis, particularly selected isolates called cannabinoids, can provide analgesic benefit in patients with chronic neuropathy. Cannabis can also be used as an adjunct to other pain therapies, potentially lowering the amount of dangerous synthetic medication that is required to relieve pain. A recent study on the Opioid-Sparing Effect of Cannabinoids found that when cannabinoids were administered with opioids, specifically morphine, nearly four times less morphine was needed to achieve the same analgesic effect. This presents further evidence for cannabis as a means of reducing cases of opiate dependency and death.

While the politics of cannabis are exceedingly complex, the truth of this miraculous plant is becoming increasingly obvious: it heals the human body. The fact that it does so without the need for a black-box warning of Serious Adverse Events ensures that cannabis is the future of medicine. While clinical studies in the United States have been impeded due to cannabis’s classification as a Schedule One Controlled Substance (meaning the substance has no medicinal value), other countries have taken the lead. A UK study seeking to reduce chronic pain in advanced cancer patients not fully relieved from use of opioids, found that a cannabis extract composed of THC (Tetrahydrocannabinol) and CBD (Cannabidiol), two of the active constituents in cannabis, reduced pain by more than 30% from baseline when compared with placebo, with no serious adverse effects.

Beyond the realm of chronic pain, cannabis has been shown to positively support individuals dealing with post-traumatic stress. It has demonstrated effectiveness at calming the often-debilitating side effects of inflammatory bowel disease, aka Crohn’s disease. Isolates from the cannabis plant have shown promise at treating “incurable” diseases such as Grave’s disease and brain cancer, and work better than traditional medications for Alzheimer’s disease. With so much evidence of profound medicinal value, legislation based on old systems of control will not long hold back the tide. There are simply too many health benefits to be obtained from the cannabis plant.

For additiona research on the medical benefits of cannabis, visit the GreenMedInfo database on the subject.


Resources

[1] https://www.sciencedaily.com/releases/2018/02/180213111508.htm

[2] Service Use Preceding Opioid-Related Fatality. Olfson, Wall, Wang, Crystal, Blanco. Am J Psychiatry. 2017 Nov 28:appiajp201717070808. doi: 10.1176/appi.ajp.2017.17070808.

[3] Institute of Medicine Report from the Committee on Advancing Pain Research, Care, and Education: Relieving Pain in America, A Blueprint for Transforming Prevention, Care, Education and Research. The National Academies Press, 2011. http://books.nap.edu/openbook.php?record_id=13172&page=1.

[4] IOM (Institute of Medicine) 2011. Relieving Pain in America: A Blueprint for Transforming Prevention, Care, Education and Research, Washington, DC; The National Academies Press.

[5] Gabapentin, opioids, and the risk of opioid-related death: A population-based nested case-control study. Gomes, Juurlink, Antoniou, Mamdani, Paterson, van den Brink. PLoS Med. 2017 Oct 3;14(10):e1002396. doi: 10.1371/journal.pmed.1002396. eCollection 2017 Oct.