Archive for the ‘Treatment’ Category

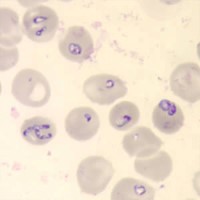
Could it be Babesia?

https://www.galaxydx.com/could-it-be-babesia/

Could it be Babesia?


Lyme Disease: Don’t Wait For Blood Tests Where Patients Have ‘Bullseye’ Rash

https://www.independent.co.uk/news/health/lyme-disease-rash-tick-bite-infection-antibiotics-gp-nice-bulls-eye-a8774511.html  (News Story in Link)

Alex Matthews-King Health Correspondent

11 Feb 2019

Lyme Disease:  Doctors Told Don’t Wait For Blood Tests Where Patients Have ‘Bullseye’ Rash

Doctors have been told to diagnose Lyme disease without waiting for blood test results if patients have the characteristic “bull’s eye” rash.

Blood tests for the tick-borne infections may miss the condition in the early weeks, according to new draft guidance published by the National Institute for Health and Care Excellence (Nice).

This could reduce the chances of a full recovery, the NHS treatment watchdog said. As a result, it said patients should be offered antibiotics where they show the characteristic ringed rash, known as erythema migrans.

The bull’s eye rash appears in around two thirds of cases usually within a month of a bite from an infected tick.

“For most people with Lyme disease, a course of antibiotics will be effective, so it is important we diagnose and treat people as soon as possible,” Professor Gillian Leng, director of health and social care at Nice, said. “A person with Lyme disease may present with a wide range of symptoms, so we have clear advice for professionals about the use of lab tests for diagnosis and the most appropriate antibiotic treatments.”

Tests can check for antibodies in the blood, however these may not appear until up to eight weeks after the patient is bitten.

It is hoped the new draft guidance will increase the number of early diagnoses and allow patients to receive treatment immediately, reducing the risk of further symptoms developing.

When there is no rash present and symptoms are unclear, doctors will be advised to carry out blood tests.

Professor Saul Faust, chairman of the guideline committee, said:

“Lab tests are necessary when a person’s symptoms are unclear, but they are not needed if a person presents the characteristic red rash, erythema migransDoctors should feel confident to prescribe antibiotics immediately for those with erythema migrans.”

Veronica Hughes, chief executive of Caudwell LymeCo, a UK charity for patients with Lyme disease, said:

Waiting for blood test results always delays treatment. When a patient has the rash, this delay is unnecessary and reduces the likelihood of total cure.”

Additional reporting by Press Association

____________________

**Comment**

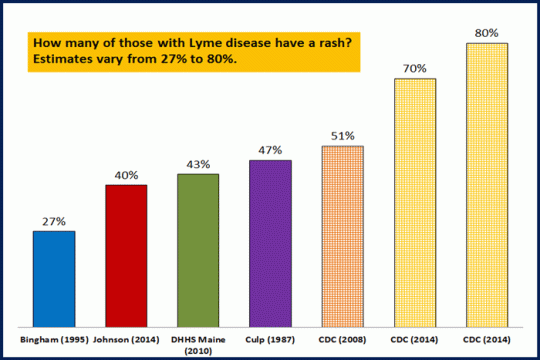
EM rash = Lyme.  Period.  The sad thing is many do not present with the classic EM rash, if they have a rash at all.  The statement that two thirds present with the rash is objectionable.  This article states the percentage varies from 27-80%, hardly a set number.  https://www.lymedisease.org/lymepolicywonk-how-many-of-those-with-lyme-disease-have-the-rash-estimates-range-from-27-80-2/  (Table from this link)

Rashes-larger-blog

Please notice that the CDC has much higher percentages.  Why?  They are using the surveillance definition for recording Lyme cases.  This will naturally skew percentages towards rash reporting.  It won’t include the thousands upon thousands that don’t notice or have the rash.  Even the CDC with it’s stringent criteria report the percentages vary widely depending upon the state.

Also, rashes vary widely.  Clinical diagnosis must consider any skin rash, regardless of its resemblance to the bull’s-eye.   

“Researchers note that multiple textbooks and websites prominently feature the bull’s-eye image as a visual representation of Lyme disease.” They write, “This emphasis on target-like lesions may have inadvertently contributed to an underappreciation for atypical skin lesions caused by Lyme disease.Some Visible Signs of Lyme Disease Are Easily Missed or Mistaken, Science Daily, Apr 22, 2013 https://www.sciencedaily.com/releases/2013/04/130422132507.htm?utm_source=feedburner&utm_medium=email&utm_campaign=Feed%3A+sciencedaily%2Fhealth_medicine%2Flyme_disease+%28ScienceDaily%3A+Health+%26+Medicine+News+–+Lyme+Disease%29

Good news:  you have a perfect EM rash you get treatment.  Bad news:  those with an atypical rash and those without a rash are hung out to dry.


CDC Endorsement of Single Dose Antibiotic for Lyme Challenged

https://www.webwire.com/ViewPressRel.asp?aId=235946

CDC Endorsement of Single Dose Antibiotic for Lyme Disease Prevention Challenged

Advocates claim policy harms patients and violates HHS standards for information quality

Washington, DC – WEBWIRE – Tuesday, February 19, 2019

CDC’s endorsement of the IDSA recomendation for a single dose of doxyclycline to prevent Lyme Disease has potential to cause serious harm to patients for whom the prophylaxis fails to prevent infection.

Advocates for Lyme disease patients are calling on the Centers for Disease Control and Prevention (CDC) to withdraw its endorsement of single-dose antibiotic prophylaxis for prevention of Lyme disease after a tick bite.

A key limitation of the recommendation is that it is based on a single study that has not been replicated and which did not prove that the prophylaxis actually prevented Lyme disease. In addition, the recommendation is restrictive since it is only recommended if certain criteria are met. This is likely to confuse both the public and health care providers.

The recommendation on tick bite prophylaxis is from the Infectious Diseases Society of America (IDSA) 2006 guidelines for diagnosis and treatment of Lyme disease.

In addition to being more than a decade out of date, the IDSA guidelines are based on low-quality evidence and are widely regarded as critically flawed. The National Academy of Medicine report, Clinical Practice Guidelines We Can Trust, cites the 2006 IDSA Lyme guidelines to illustrate the problems of conflicts of interests, lack of transparency, and scientific bias in guidelines development.

On February 14, the Patient Centered Care Advocacy Group filed an “information quality request for correction” with CDC’s Office of the Associate Director for Science.

The complaint argues that the IDSA recommendation endorsed by CDC

“lacks utility, objectivity, and integrity and misleads patients and healthcare providers. This not only can result in human harm but can increase the number of long-term Lyme disease cases, worsening the current Lyme epidemic and increasing the financial impact on our country in terms of lost productivity, disability, and increased medical expenses.”

The contested information on tick-bite prophylaxis—which is included on CDC’s website and in the CDC publication, Tick-Borne Diseases of the United States, Fifth Edition, 2018—states:

“The Infectious Disease Society of America (IDSA) does not generally recommend antimicrobial prophylaxis for prevention of Lyme disease after a recognized tick bite. However, in areas that are highly endemic for Lyme disease, a single dose of doxycycline may be offered to adult patients (200 mg) who are not pregnant and to children older than 8 years of age…”

According to Holly Ahern, associate professor of microbiology at SUNY Adirondack and Lyme Action Network board member, this recommendation is based on a single study from 2001 that has not been reproduced and which has the following scientific limitations:

  1. The “primary endpoint” used to determine whether the prophylactic treatment “prevented” Lyme disease was the appearance of an erythema migrans rash at the site of the tick bite. More recent studies consistently show that the rate of any type of skin rash is less than 50%, and the rate of EM is less than 10%. Therefore this study excludes more than half of true cases of Lyme disease from the data analysis.
  2. Subjects who developed subjective symptoms of Lyme disease such as headaches, profound fatigue, brain fog, joint pain without swelling, weakness, numbness, or difficulty controlling specific muscles were excluded from the data analysis.
  3. Participants were only observed for 6 weeks before being considered “negative” for Lyme disease, and therefore persons who developed symptoms after 6 weeks were excluded from the data analysis.

The complaint maintains that,

“Patients and healthcare providers alike gain a false sense that a tick-borne disease was prevented with this prophylaxis and, therefore, full treatment may be delayed or denied. Research shows that delayed treatment increases the rate of treatment failure. In addition, this partial treatment has been shown to result in false negative blood test results for Lyme disease in the future.”

According to Bruce Fries, president of the Patient Centered Care Advocacy Group and lead author of the complaint:

“CDC’s endorsement of the IDSA recommendation for a single dose of doxycycline to prevent Lyme Disease has potential to cause serious harm to patients for whom the prophylaxis fails to prevent infection.  CDC’s dissemination of this information also violates HHS Guidelines for Ensuring and Maximizing the Quality, Objectivity, Utility, and Integrity of Information Disseminated to the Public.”

Fries says

“It should be noted that the IDSA guidelines represent one of two standards of care for Lyme disease. More recent and comprehensive evidence-based guidelines for Lyme disease were published by the International Lyme and Associated Diseases Society (ILADS) in 2014. The ILADS guidelines, which are fully compliant with current standards, specifically recommend against a single dose of doxycycline for prevention of Lyme disease.”

To read the full complaint visit: https://tinyurl.com/CDC-Misinfo

___________________

For More:

Yet, despite the lack of evidence, many are doing it:  https://madisonarealymesupportgroup.com/2017/08/09/one-dose-of-antibiotic-for-lyme-disease-in-rhode-island/

Dr. Zhang has stated that it has been shown that doxycycline as a mono therapy can throw borrelia into a more persistent form (round body forms).  This is something the CDC/NIH/IDSA isn’t acknowledging at all.  https://www.ncbi.nlm.nih.gov/pubmed/21753890# Doxycycline reduced spirochetal structures ∼90% but increased the number of round body forms about twofold.
I guess since a researcher outside The Cabal discovered this – it is tossed out like yesterday’s garbage.


Germs in Your Gut Are Talking to Your Brain. Scientists Want to Know What They’re Saying.

https://www.nytimes.com/2019/01/28/health/microbiome-brain-behavior-dementia.html?smid=fb-nytimes&smtyp=cur

The body’s microbial community may influence the brain and behavior, perhaps even playing a role in dementia, autism and other disorders.

Credit Sean McSorley

In 2014 John Cryan, a professor at University College Cork in Ireland, attended a meeting in California about Alzheimer’s disease. He wasn’t an expert on dementia. Instead, he studied the microbiome, the trillions of microbes inside the healthy human body.

Dr. Cryan and other scientists were beginning to find hints that these microbes could influence the brain and behavior. Perhaps, he told the scientific gathering, the microbiome has a role in the development of Alzheimer’s disease.

The idea was not well received.

“I’ve never given a talk to so many people who didn’t believe what I was saying,” Dr. Cryan recalled.

A lot has changed since then: Research continues to turn up remarkable links between the microbiome and the brain. Scientists are finding evidence that microbiome may play a role not just in Alzheimer’s disease, but Parkinson’s disease, depression, schizophrenia, autism and other conditions.

For some neuroscientists, new studies have changed the way they think about the brain.

One of the skeptics at that Alzheimer’s meeting was Sangram Sisodia, a neurobiologist at the University of Chicago. He wasn’t swayed by Dr. Cryan’s talk, but later he decided to put the idea to a simple test.

“It was just on a lark,” said Dr. Sisodia. “We had no idea how it would turn out.”

He and his colleagues gave antibiotics to mice prone to develop a version of Alzheimer’s disease, in order to kill off much of the gut bacteria in the mice. Later, when the scientists inspected the animals’ brains, they found far fewer of the protein clumps linked to dementia.

Just a little disruption of the microbiome was enough to produce this effect. Young mice given antibiotics for a week had fewer clumps in their brains when they grew old, too.

“I never imagined it would be such a striking result,” Dr. Sisodia said. “For someone with a background in molecular biology and neuroscience, this is like going into outer space.”

Following a string of similar experiments, he now suspects that just a few species in the gut — perhaps even one — influence the course of Alzheimer’s disease, perhaps by releasing chemical that alters how immune cells work in the brain.

He hasn’t found those microbes, let alone that chemical. But “there’s something’s in there,” he said. “And we have to figure out what it is.”

Scientists have long known that microbes live inside us. In 1683, the Dutch scientist Antonie van Leeuwenhoek put plaque from his teeth under a microscope and discovered tiny creatures swimming about.

But the microbiome has stubbornly resisted scientific discovery. For generations, microbiologists only studied the species that they could grow in the lab. Most of our interior occupants can’t survive in petri dishes.

In the early 2000s, however, the science of the microbiome took a sudden leap forward when researchers figured out how to sequence DNA from these microbes. Researchers initially used this new technology to examine how the microbiome influences parts of our bodies rife with bacteria, such as the gut and the skin.

Few of them gave much thought to the brain — there didn’t seem to be much point. The brain is shielded from microbial invasion by the so-called blood-brain barrier. Normally, only small molecules pass through.

“As recently as 2011, it was considered crazy to look for associations between the microbiome and behavior,” said Rob Knight, a microbiologist at the University of California, San Diego.

He and his colleagues discovered some of the earliest hints of these links. Investigators took stool from mice with a genetic mutation that caused them to eat a lot and put on weight. They transferred the stool to mice that had been raised germ-free — that is, entirely without gut microbiomes — since birth.

After receiving this so-called fecal transplant, the germ-free mice got hungry, too, and put on weight.

Altering appetite isn’t the only thing that the microbiome can do to the brain, it turns out. Dr. Cryan and his colleagues, for example, have found that mice without microbiomes become loners, preferring to stay away from fellow rodents.

The scientists eventually discovered changes in the brains of these antisocial mice. One region, called the amygdala, is important for processing social emotions. In germ-free mice, the neurons in the amygdala make unusual sets of proteins, changing the connections they make with other cells.

Studies of humans revealed some surprising patterns, too. Children with autism have unusual patterns of microbial species in their stool. Differences in the gut bacteria of people with a host of other brain-based conditions also have been reported.

But none of these associations proves cause and effect. Finding an unusual microbiome in people with Alzheimer’s doesn’t mean that the bacteria drive the disease. It could be the reverse: People with Alzheimer’s disease often change their eating habits, for example, and that switch might favor different species of gut microbes.

Fecal transplants can help pin down these links. In his research on Alzheimer’s, Dr. Sisodia and his colleagues transferred stool from ordinary mice into the mice they had treated with antibiotics. Once their microbiomes were restored, the antibiotic-treated mice started developing protein clumps again.

“We’re extremely confident that it’s the bacteria that’s driving this,” he said.

Other researchers have taken these experiments a step further by using human fecal transplants.

If you hold a mouse by its tail, it normally wriggles in an effort to escape. If you give it a fecal transplant from humans with major depression, you get a completely different result: The mice give up sooner, simply hanging motionless.

As intriguing as this sort of research can be, it has a major limitation. Because researchers are transferring hundreds of bacterial species at once, the experiments can’t reveal which in particular are responsible for changing the brain.

Now researchers are pinpointing individual strains that seem to have an effect.

To study autism, Dr. Mauro Costa-Mattioli and his colleagues at the Baylor College of Medicine in Houston investigated different kinds of mice, each of which display some symptoms of autism. A mutation in a gene called SHANK3 can cause mice to groom themselves repetitively and avoid contact with other mice, for example.

In another mouse strain, Dr. Costa-Mattioli found that feeding mothers a high-fat diet makes it more likely their pups will behave this way.

When the researchers investigated the microbiomes of these mice, they found the animals lacked a common species called Lactobacillus reuteri. When they added a strain of that bacteria to the diet, the animals became social again.

Dr. Costa-Mattioli found evidence that L. reuteri releases compounds that send a signal to nerve endings in the intestines. The vagus nerve sends these signals from the gut to the brain, where they alter production of a hormone called oxytocin that promotes social bonds.

Other microbial species also send signals along the vagus nerve, it turns out. Still others communicate with the brain via the bloodstream.

It’s likely that this influence begins before birth, as a pregnant mother’s microbiome releases molecules that make their way into the fetal brain.

Mothers seed their babies with microbes during childbirth and breast feeding. During the first few years of life, both the brain and the microbiome rapidly mature.

To understand the microbiome’s influence on the developing brain, Rebecca Knickmeyer, a neuroscientist at Michigan State University, is studying fMRI scans of infants.

In her first study, published in January, she focused on the amygdala, the emotion-processing region of the brain that Dr. Cryan and others have found to be altered in germ-free mice.

Dr. Knickmeyer and her colleagues measured the strength of the connections between the amygdala and other regions of the brain. Babies with a lower diversity of species in their guts have stronger connections, the researchers found.

Does that mean a low-diversity microbiome makes babies more fearful of others? It’s not possible to say yet — but Dr. Knickmeyer hopes to find out by running more studies on babies.

Credit Sean McSorley

As researchers better understand how the microbiome influences the brain, they hope doctors will be able to use it to treat psychiatric and neurological conditions.

It’s possible they’ve been doing it for a long time — without knowing.

In the early 1900s, neurologists found that putting people with epilepsy on a diet low in carbohydrates and high in protein and fat sometimes reduced their seizures.

Epileptic mice experience the same protection from a so-called ketogenic diet. But no one could say why. Elaine Hsiao, a microbiologist at the University of California, Los Angeles, suspected that the microbiome was the reason.

To test the microbiome’s importance, Dr. Hsiao and her colleagues raised mice free of microbes. When they put the germ-free epileptic mice on a ketogenic diet, they found that the animals got no protection from seizures.

But if they gave the germ-free animals stool from mice on a ketogenic diet, seizures were reduced.

Dr. Hsiao found that two types of gut bacteria in particular thrive in mice on a ketogenic diet. They may provide their hosts with building blocks for neurotransmitters that put a brake on electrical activity in the brain.

It’s conceivable that people with epilepsy wouldn’t need to go on a ketogenic diet to get its benefits — one day, they may just take a pill containing the bacteria that do well on the diet.

Sarkis Mazmanian, a microbiologist at Caltech, and his colleagues have identified a single strain of bacteria that triggers symptoms of Parkinson’s disease in mice. He has started a company that is testing a compound that may block signals that the microbe sends to the vagus nerve.

Dr. Mazmanian and other researchers now must manage a tricky balancing act. On one hand, their experiments have proven remarkably encouraging; on the other, scientists don’t want to encourage the notion that microbiome-based cures for diseases like Parkinson’s are around the corner.

That’s not easy when people can buy probiotics without a prescription, and when some companies are willing to use preliminary research to peddle microbes to treat conditions like depression.

“The science can get mixed up with what the pseudoscientists are doing,” said Dr. Hsiao.

Dr. Costa-Mattioli hopes that L. reuteri some day will help some people with autism, but he warns parents against treating their children with store-bought probiotics. Some strains of L. reuteri alter the behavior of mice, he’s found, and others don’t.

Dr. Costa-Mattioli and his colleagues are still searching for the most effective strain and figuring out the right dose to try on people.

“You want to go into a clinical trial with the best weapon, and I’m not sure we have it,” he said.

Katarzyna B. Hooks, a computational biologist at the University of Bordeaux in France, warned that studies like Dr. Costa-Mattioli’s are still unusual. Most of these findings come from research with fecal transplants or germ-free mice — experiments in which it’s especially hard to pinpoint the causes of changes in behavior.

“We have the edges of the puzzle, and we’re now trying to figure out what’s in the picture itself,” she said.


I Just Got Diagnosed With Lyme Disease. What Should I Do?

https://globallymealliance.org/diagnosed-with-lyme-disease/

diagnosed-w-lyme-disease

WELCOME TO THE SCHOOL OF LYME. 6 TIPS FOR THOSE NEWLY DIAGNOSED WITH LYME DISEASE.

by Jennifer Crystal

Every day, I receive emails from people who have recently been diagnosed with Lyme disease. As most of us do when we hear a new medical term or leave a doctor’s office, these people frantically search the web looking for information. Sometimes they come across one of my blog posts. Then they write with questions about treatment, with requests for finding a good doctor and with prayers that I will be able to offer them some hope. Most of all, they want to know: “What do I do to get better?”

Because I find myself offering the same responses to many such patients, I thought I would create a “School of Lyme For the Newly Diagnosed.” Consider this a brief survey course on tick-borne illness, open to anyone who wants to learn the basics of what to do when you get (or suspect) a Lyme diagnosis.

Lesson 1: It’s Lyme, not Lyme’s!

It’s important to know the correct name of your disease! Many people mistakenly call it Lyme’s disease, assuming it was discovered by a Dr. Lyme. In fact, Lyme is named for the town in which it was first detected: Lyme, Connecticut. As for the names of co-infections, those are not as simple, but should still be part of your working vocabulary; we’ll get to those in Lesson 5.

Lesson 2: All cases are different

Everyone’s looking for a one-size-fits-all treatment protocol. Unfortunately, that doesn’t exist, and here’s why: Lyme bacteria, called spirochetes, impact every victim differently. It depends how quickly the infection was caught and diagnosed; how far it’s spread, and to where. The bacteria can affect different organs, muscles, bones and cells in different patients. It can cross the blood-brain barrier and enter the central nervous system. Moreover, there may be co-infections present—the list goes on and on. A Lyme doctor can see a thousand patients and use a thousand different protocols. Telling you what antibiotics I took won’t help you; you need to work with your doctor to figure out the best combination for you.

Lesson 3: Find an LLMD

An LLMD is a Lyme Literate Medical Doctor. This is a physician who has trained with ILADS (The International Lyme and Associated Diseases Society). Some practitioners claiming to be Lyme literate may not be versed in all tick-borne disease. The best way to know you are getting good treatment is to make sure your doctor is ILADS-trained. You can find an ILADS-trained physician in your area through Global Lyme Alliance, by clicking on GLA.org/find.

Lesson 4: Get tested for co-infections

Unfortunately, ticks don’t only carry Lyme disease. Many of them harbor what are known as co-infections: other tick-borne diseases besides Lyme. The most common are babesiosis, ehrlichiosis, anaplasmosis, and bartonella, but there are many others. It’s critical that you get tested for co-infections along with Lyme disease. If you are receiving treatment for Lyme and haven’t been tested for other tick-borne infections, you may be fighting only half the battle.

Lesson 5: Take probiotics

Antibiotics kill spirochetes, but they also kill the good bacteria in your gut, which can cause a yeast infection. To combat this, take probiotics (available at any pharmacy or health food store). Important: make sure you take the probiotics at least two hours before or after you take the antibiotics; if you take them too close together, the antibiotics will kill the probiotics.

Lesson 6: Don’t panic

The information available at our fingertips in this internet age is a double-edged sword. You may read stories that terrify you. Remember, every case of Lyme disease is different. If you catch tick-borne illnesses and treat them immediately, chances are you will not suffer as long those who have been sick for many years. Don’t let my story or those of other chronically ill patients frighten you. Do let these stories offer you hope, however, especially if you have been sick for a long time. I am living proof that even the worst cases of tick-borne illness can eventually be wrestled into remission. I am living proof that long-term treatment works. I am living proof that it’s a long road between being bedridden and skiing, but it can be traveled.

Most importantly, know that you are not alone in this fight. There are many of us battling tick-borne diseases right alongside you. We feel your pain. We validate your suffering. And we know that it can get better. There is hope!


jennifer crystal

Opinions expressed by contributors are their own.

Jennifer Crystal is a writer and educator in Boston. She has written a memoir, One Tick Stopped the Clock for which she is seeking representation. Contact her at: 

lymewarriorjennifercrystal@gmail.com

____________________

**Comment**

  1. Lyme has been around since the beginning of time:  https://www.utoronto.ca/news/u-t-researchers-find-ancient-iceman-s-infection-helps-lyme-disease-bone-loss-discovery, and https://madisonarealymesupportgroup.com/2018/02/12/the-persistent-spiral-the-ancient-history-of-lyme-disease-and-tick-borne-infections/.  Wisconsin has the first published case from Taylor County in 1969:  https://www.ncbi.nlm.nih.gov/pubmed/5497158.  https://www.publichealthalert.org/how-lyme-got-a-bad-rap—lyme-connecticut-that-is.html  This article discusses how dermatologist Dr. Rudolf J. Scrimenti diagnosed the Borrelia infection and described both neurologic and arthritic symptoms exhibited by the patient. He took his knowledge & experience, and attempted to educate Dr. Steere, the person called to the scene of the Lyme, Connecticut “outbreak.”  Excerpt:  Scrimenti even corresponded with Steere and visited Yale to inform him of the long European history and strong possibility that the Lyme clusters were likely a form of Borreliosis. However, Steere, the rheumatologist-to-be had been summoned to investigate outbreaks of juvenile rheumatoid arthritis. After extensive study and consideration, guess what he concluded? He believed that he was observing a previously unrecognized form of JRA.  And, we’ve been paying for it ever since.
  2. Doctor lists constantly change.  The best way for you to find credible doctors is through your local support group. While organizations like Global Lyme Alliance are a place to start, they aren’t aware of changes that can occur quite rapidly.  You can also ask people their experiences with various doctors, keeping in mind that people are going to have differing opinions.
  3. Testing for coinfections is abysmal.  Most LLMD’s will diagnose and treat people clinically, which means, individually based on symptoms.  Seronegativity is common with Lyme/MSIDS which just means you can test negative over and over and over yet be infected.  I’ve found that getting a negative on a test can lead to a false sense of security.  Also, treating this for many people is like peeling an onion.  You start out with certain symptoms and then as you treat, other symptoms can rear their ugly little heads.  For instance, we started treating for Lyme only to discover further down the road Babesia symptoms which needed addressing.
  4. Taking probiotics is a great place to start; however, as Dr. Burrascano states, “Now is the time for pristine health habits.”  Eat a whole-food based diet and avoid junk food, soda, alcohol, and anything that could lower your immune system & cause inflammation:  https://articles.mercola.com/lyme-disease/diet.aspx and https://www.tiredoflyme.com/diet.html.  Many patients also find they are sensitive to many things and omitting dairy or gluten, for instance, can really help some patients.  Being willing to try things is important as sometimes the only way we learn is by trying.  Support groups are also good for this type of information.  You will find people who are making their own bone broth, kefir/yogurt, kombucha, and have ideas for recipes that are healthy yet don’t taste like cardboard.
  5. Treating this is unlike anything else you’ve ever treated.  Treatment is hard and costly.  You feel far worse for a long time before you start feeling better.  This is one of the hardest things to accept as a patient, but accept it you must.  People are so relieved to finally be diagnosed that starting treatment is like a slap in the face.  They expect to feel better but in fact, they feel worse.  This is due to the herxheimer reaction:  https://madisonarealymesupportgroup.com/2015/08/15/herxheimer-die-off-reaction-explained/.  Also, once patients hit a plateau, LLMD’s switch the meds around typically bringing back the dreaded herx.  You go up and down like the waves of the sea.  You have many bad days and a few good.  You have to learn to adjust your life around Lyme/MSIDS.  It will sift you like wheat and you will find in the end you are made of much sterner stuff than you ever realized.  For more:  https://madisonarealymesupportgroup.com/2015/12/06/tips-for-newbies/
  6. The silver lining.  After this you never take life for granted (or a day without pain!) and you become much more aware of and sympathetic of others.  All in all, it makes you a better human and God knows, we need more of them!