Archive for the ‘Ticks’ Category

Public Hearing Video on WI Lyme Bills 315 & 316

https://wiseye.org/2019/08/15/assembly-committee-on-environment/

Scroll to 1:20 to hear the Representatives behind the bills, their purpose and intent

All the speakers were for the two bills presented
  • Speaker from UWM Center of Excellence of Vector Borne Diseases
  • Friends of WI State Parks
  • 2 Patients
  • I speak at 2:16:00

While the two bills presented deal specifically with education and prevention, other bills have been proposed. Those are the ones I have deep concerns about. To read about the bills go here:  https://madisonarealymesupportgroup.com/wp-content/uploads/2019/05/time-to-bite-back-against-lyme-disease-05-23-19.pdf

Specifically –

  1. LRBs 1652 and 3362 – Establishes a sixteen-member Tick-Borne Disease Study Committee to create a report for the legislature on consensus-based recommendations for policy changes on awareness, prevention, surveillance, diagnosis, reporting, and treatment of Lyme Disease

Since everything about Lyme/MSIDS is steeped in controversy, this panel could be made up of those who do not recognize that Lyme can be persistent, and that it’s common for coinfection involvement necessitating numerous drugs for extended periods of time. A great example of this happening as we speak is in the federal Tick Borne Disease Working Group:  https://madisonarealymesupportgroup.com/2019/06/15/working-groups-abrupt-shift-excludes-lyme-patients/  Excerpt:

Dr. Shapiro is much more than just a representative of the IDSA. In addition to financial conflicts of interest that should preclude him from serving on the Working Group, for years Dr. Shapiro has notoriously waged war on Lyme patients, their doctors, and advocacy groups. Putting him on the Working Group shows tremendous lack of respect for Lyme patients and their concerns. (More than 21,000 people have signed our petition to remove Shapiro from the TBDWG.

On top of this, Shapiro accuses chronically infected, suffering patients with medically unexplained symptoms (MUS) and urges the medical community to develop ways to prevent “healthcare-seeking behaviors” by parents who believed their children may have Lyme disease:  https://madisonarealymesupportgroup.com/2019/06/11/dr-eugene-shapiro-medically-unexplained-symptoms/

https://madisonarealymesupportgroup.com/2019/05/03/when-lyme-disease-doesnt-go-away/  Dr. Brian Fallon, a Columbia University Irving Medical Center psychiatrist states that patients with chronic, unexplained symptoms had all been healthy—until they got Lyme disease. These patients suffered from chronic pain, fatigue and cognitive problems that had a debilitating effect on their lives. They all had been treated with antibiotics with partial response but then relapsed.

SINCE SUCH PERSISTENT INFECTION WAS CONSIDERED IMPOSSIBLE, THEY WERE TOLD THEY WERE HYPOCHONDRIACS.


Animal Health & Nutrition Forum – “Pets & Parasites: Diseases Transmitted by Fleas and Ticks and Their Impact on Animal and Human Health”

https://www.ncbiotech.org/events/pets-and-parasites-diseases-transmitted-fleas-and-ticks-and-their-impact-animal-and-human

“Pets and Parasites: Diseases transmitted by fleas and ticks and their impact on animal and human health” – An Animal Health and Nutrition Forum

Fleas and ticks are the most common ectoparasites (external parasites) of dogs and cats worldwide. In addition to just being a nuisance, fleas are responsible for flea allergy dermatitis and Bartonellosis while ticks are important vectors of diseases that affect humans and animals. The geographic distribution of ticks is changing due to climate change, de-foresting, and the changing living and migrating patterns of deer, birds, and rodents. Ticks are in virtually all parts of the United States, including some urban areas, and many parts of the world. Tick-transmitted diseases include: Lyme disease, Ehrlichiosis, Anaplasmosis, Rocky Mountain Spotted Fever, Babesiosis, and Hepatozoonosis.

Featured Speakers:

Dr. Edward B. Breitschwerdt
Edward B. Breitschwerdt,
Ph.D., NCSU College of
Veterinary Medicine
Dr. Kerrie Powell
Kerrie Powell, Ph.D.,
Cambrex


The AH&N EG forum will discuss Bartonellosis as well as outline the discovery and development of molecules that treat flea and tick infestations on companion animals.


Agenda

4:30 p.m. – 5:00 p.m. Registration

5:00 p.m. – 6:00 p.m. Presentations

6:00 p.m. – 7:00 p.m. Networking & Refreshments

Directions/Parking

Parking is free

Registration

RSVP is required to reserve your seat.

  • NCBiotech
    15 TW Alexander Drive
    RTP, NC  27709
  • FREE

Public Hearing Tomorrow (Aug. 15, 2019) Two WI Bills on Tick Prevention

I apologize for this late notice.  I just received it myself. I was told the two Lyme bills would be presented around noon.

https://docs.legis.wisconsin.gov/raw/cid/1509726

Assembly

PUBLIC HEARING Committee on Environment

The committee will hold a public hearing on the following items at the time specified below:

Thursday, August 15, 2019 11:00 AM
412 East

Assembly Bill 190

Relating to: wetland mitigation banks, providing an exemption from emergency rule procedures, providing an exemption from rule-making procedures, and requiring the exercise of rule-making authority.

By Representatives Tusler, Ohnstad, Sinicki, Kerkman and Mursau; cosponsored by Senators Wanggaard, Cowles, Wirch and Olsen.

Assembly Bill 210

Relating to: time limits for correcting violations found by the environmental compliance audit program.

By Representatives Brooks, Brandtjen, Knodl, Kulp, Skowronski, Tusler and Wichgers; cosponsored by Senators Jacque, Cowles and Miller.

Assembly Bill 297

Relating to: changes to the electronic waste recycling program and granting rule- making authority.

By Representatives Mursau, Hebl, Anderson, Ballweg, Billings, Ohnstad, Shankland, Sinicki, Skowronski, Spreitzer, Stubbs, Tusler, Vruwink, Spiros and Subeck; cosponsored by Senators Miller, Cowles, Larson, Smith, L. Taylor, Wirch and Carpenter.

Assembly Bill 315

Relating to: signs informing about Lyme disease in state parks, state trails, state recreational areas, and state forests and making an appropriation.

By Representatives Mursau, Milroy, Anderson, Considine, Crowley, Edming, Emerson, Gruszynski, Hesselbein, Kulp, B. Meyers, Ohnstad, Ott, Pope, Ramthun, Rodriguez, Sargent, Shankland, Sinicki, Snyder, Spiros, Spreitzer, Tauchen, C. Taylor, Thiesfeldt, Tusler and Rohrkaste; cosponsored by Senators Cowles, Miller, Carpenter, Hansen, Larson, Olsen, Petrowski, Ringhand and Smith.

Assembly Bill 316

Relating to: making insect repellant available for sale in state parks and state forests.

By Representatives Mursau, Milroy, Anderson, Crowley, Edming, Emerson, Gruszynski, Hesselbein, Kulp, B. Meyers, Ohnstad, Ott, Pope, Ramthun, Shankland, Sinicki, Snyder, Spiros, Spreitzer, Tauchen, C. Taylor, Thiesfeldt, Tusler and Rohrkaste; cosponsored by Senators Cowles, Miller, Carpenter, Hansen, Larson, Olsen, Petrowski, Ringhand and Smith.

Representative Joel Kitchens Chair

__________________

For more on the bills:  https://madisonarealymesupportgroup.com/wp-content/uploads/2019/05/time-to-bite-back-against-lyme-disease-05-23-19.pdf

News story on bills:  https://madisonarealymesupportgroup.com/2019/06/01/news-story-update-lawmakers-introduce-package-of-bills-aimed-at-lyme-awareness-in-wisconsin/

https://madisonarealymesupportgroup.com/2019/06/30/lawmakers-want-to-combat-lyme-disease-with-more-signs-insect-repellent-in-public-parks/


What Tick Saliva Does to the Human Body

https://www.theatlantic.com/science/archive/2019/07/the-marvels-of-tick-saliva/594652/

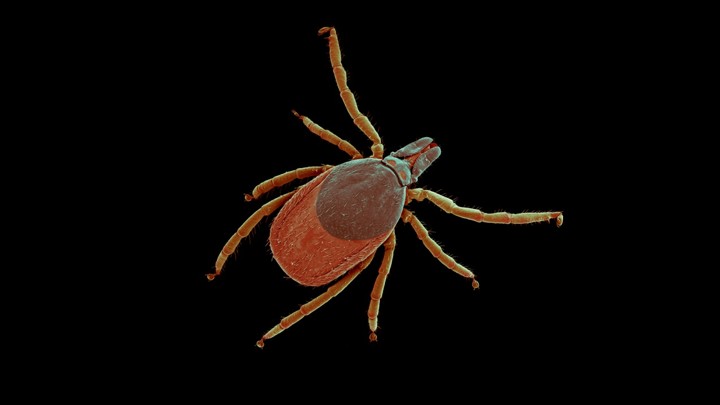
A castor bean tick under a scanning electron microscope
Hard ticks inject saliva that suppresses the host immune systemJANA BULANTOVÁ / CREATIVE COMMONS

José Ribeiro was 33 when he got his first tick bite, in the 1980s, and he remembers it as a momentous occasion. He had recently started studying tick saliva, a complex molecular cocktail that ticks inject into their hosts to inhibit pain, prevent blood clotting, and suppress the immune system—all so the tick can feed undetected for days and days and days. Ribeiro had been studying this in a lab, but now he was finally witnessing it in the flesh. In his flesh.

He marveled at the bite. It did not hurt. It did not itch. “I was amazed at how they could be so stealthy,” recalls Ribeiro, who now studies disease-carrying insects and ticks at the National Institute of Allergy and Infectious Diseases. Ticks use saliva to manipulate the body of their hosts so their bites stay painless, itchless, and as unobtrusive as a bug swelling with blood can be. Scientists have since cataloged more than 3,500 proteins from the saliva of various tick species.

Ticks evolved this molecular cocktail because they, unlike virtually any other blood feeder, feed for days at a time on a single host. Most tick species feed only once during each stage of their life cycle (larva, nymph, adult), so they have to get a “voluminous blood meal” out of each host, says Sarah Bonnet, who studies ticks at the French National Institute for Agricultural Research. A tick might even wait years between feedings. In the meantime, it must subsist entirely on its previous blood meal. Each meal counts for a lot.

When a tick starts to feed, it doesn’t suck blood out of blood vessels. Instead, it secretes enzymes in its saliva that destroy a small ring of host tissue. This creates a “feeding cavity,” which Ribeiro likens to a “lake of blood.” “The tick sucks blood from that lake,” he says. For this strategy to work though, ticks also need to make proteins that prevent blood from clotting, as it normally wants to do in an injury site. Over the course of days, a host’s body will try to heal the wound by sending cells that make collagen. Normally, this would allow the wound to scar over, but tick saliva has molecules to counteract this, too.

Lastly, the tick has to evade a host’s immune system. Mammals, including humans, have complex immune systems with multiple lines of defense, and tick saliva can neutralize pretty much all of them. To start, ticks secrete molecular “mops,” which bind to and neutralize histamine. Histamine is best known for causing itching and redness, but it also plays an important role in opening up blood vessels to allow immune cells to get to a site of injury. Tick saliva prevents this, so tick bites don’t itch and immune cells can’t get to the bite. Tick saliva also degrades pain-inducing molecular signals in a host. That’s why tick bites also do not hurt. Ticks then inject molecules that neutralize or evade a suite of white blood cells that would otherwise be eating or attacking an invader.

The exact cocktail of a tick’s saliva proteins changes every few hours, Ribeiro says. The thousands of proteins in its saliva are highly redundant in function, and the tick cycles through them as a way of circumventing a host’s immune system. Immune systems take time to recognize and react to a foreign tick protein, and this strategy simply doesn’t give a host’s cells a chance to do that. Suppose, Ribeiro says, “Monday a tick starts feeding on you and injecting the saliva in you.” By Friday, when your body can mount a proper immune response against those first proteins, “the tick has already changed the repertoire.”

Ticks, of course, are noteworthy not just because they bite, but because they transmit diseases when they bite—including Lyme disease, babesiosis, Rocky Mountain spotted fever, and many, many others. And pathogens may take advantage of the fact that tick saliva suppresses a host’s immune system. Bonnet has found that ticks carrying the bacteria for cat-scratch disease (which, despite the name, is also transmitted by ticks) make more of a saliva protein called IrSPI. In a recent preprint, which has not yet been peer-reviewed, her team isolated IrSPI and found that it suppresses multiple types of white blood cells, weakening a host’s defenses at the bite. The upshot is that ticks can feed undetected, and bacteria can spread into a new host undetected. Tick saliva seems to help not just ticks, but the bacteria that live inside them.

But Bonnet thinks IrSPI could also be turned into a weakness. It could be a target for vaccines. If people are inoculated against IrSPI, their bodies might immediately recognize a tick bite and mount an immune response, preventing the tick from working its saliva tricks. (That’s why people who are bitten repeatedly will sometimes find the bites starting to itch.) Scientists are also interested in components of tick saliva that could be useful in cases where doctors want to inhibit pain or prevent blood from clotting. Ribeiro notes that this could be challenging because the proteins in tick saliva tend to be large and complicated—in other words, difficult to mass produce. But molecules from tick saliva are already being used to study certain unknown pathways in the human immune system. For example, scientists have used tick saliva to study how HIV infects cells.

Using tick saliva to study the human immune system makes a kind of sense. Over millions of years of evolution, ticks have essentially reverse engineered their hosts’ immune systems to evade them.

________________

For more:  https://madisonarealymesupportgroup.com/2018/01/20/potential-medical-adhesive-tick-saliva/

https://madisonarealymesupportgroup.com/2019/04/26/three-strains-of-borrelia-other-pathogens-found-in-salivary-glands-of-ixodes-ticks-suggesting-quicker-transmission-time/

https://madisonarealymesupportgroup.com/2018/12/28/relapsing-fever-spirochete-uniquely-adapted-to-highly-oxidative-salivary-glands-of-soft-bodied-tick/

https://madisonarealymesupportgroup.com/2019/07/29/how-quickly-can-an-attached-tick-make-you-sick/

https://madisonarealymesupportgroup.com/2018/05/22/mosquito-spit-alone-may-significantly-alter-your-immune-system-for-days-after-a-bite/

Vermont’s No. 2 Ranking For Lyme Disease Prompts Concerns

https://vtdigger.org/2019/06/16/high-tick-populations-prompt-lyme-disease-concerns/

Vermont’s No. 2 ranking for Lyme disease prompts concerns

tickA blacklegged tick, commonly known as a deer tick. Photo courtesy of Vermont Department of Health

Vermont currently ranks No. 2 in the country for Lyme disease — though many years, it’s No. 1. The CDC considers the disease endemic in the state.

Critics of the medical establishment, however, believe there is another problem contributing to the high incidence of the disease in Vermont: A lack of effective early diagnosis and treatment.

In 2017, there were 1,093 cases, according to the Vermont Department of Health. Data from 2018 hasn’t been finalized yet, but according to Natalie Kwit, the state public health veterinarian, there were likely approximately 500 to 600 cases, which she described as a normal year-to-year variance.

Other tick-borne diseases, like Babesiosis and Anaplasmosis, are also on the rise in Vermont, Kwit said. Since Vermont is on the northern edge of the area affected by tick-borne illnesses, the lower half of the state gets hit hardest. According to Kwit, Bennington County has the highest incidence of Lyme disease, followed by Rutland, Windsor, Windham, Addison and Grand Isle Counties.

Kwit said it’s hard to say how bad this year will be, but noted that with the ticks in their nymph form right now — when Lyme disease rates are highest — Vermonters should be particularly careful through June and July.

Bill Landesman, who researches ticks at Green Mountain College, said Vermont is kind of a perfect storm for Lyme rates. Not only are the black-legged ticks that populate the area ideal hosts for Borrelia burgdorferi, the bacteria that causes Lyme — the state also has plentiful numbers of white-tailed deer and deer mice, two primary tick carriers.

Landesman said the infection rate for nymphs, which are currently in season, is around 20% to 30%, while the adult rate, in season later in the summer, is twice that, 40% to 60%. He said on some of the sites he studies, there is a one in four chance that you’ll find a tick in any given square meter — meaning if you go on a hike through the woods, you’re at risk for Lyme.

Critics say the Lyme problem in Vermont isn’t just the result of a high tick incidence. They question whether the medical community could do more to respond to the endemic.

Medical professionals acknowledge that Lyme can be frustrating to diagnose.

Prompt diagnosis as prevention

Rebecca Zelis’ son didn’t have the bullseye rash or joint pain that doctors tend to look for to identify Lyme disease. But his symptoms presented behaviorally. By the time he reached kindergarten, Zelis said his symptoms were deeply troubling.

“Mommy I just want to die,” he told her. “I want to run in front of a car and die.”

Diagnoses for her son ranged from psychological problems to bad parenting. It wasn’t until her son started to get more classic symptoms, like headaches and chronic infections, that doctors finally recognized he had Lyme disease.

Since he went so long without treatment, there was a long road back to neurological recovery. He was homeschooled for a while in middle school because he was too sick to leave the house.

When Zelis looked online for more information, she found a lot about prevention, but not as much about symptoms, especially less typical symptoms like the ones her son was experiencing. So in 2015, she started VTLyme.org — now a nonprofit — to help other Vermonters navigate the disease and other tick-borne illnesses.

When caught early and treated effectively, Zelis said, Lyme disease typically won’t cause long term problems. But oftentimes, that isn’t the case.

“Not all medical providers in Vermont know how to accurately diagnose and effectively treat tick-borne diseases,” Zelis said. “Vermonters affected by complex tick-borne diseases need more resources, understanding and support.”

In 2014, Zelis said more than half of the children diagnosed with Lyme disease in Vermont did not have a bullseye rash, but all of the medical information she was seeing still centered around that symptom. The Center for Disease Control reports that nationally between 70% and 80% of Lyme disease cases involve a bullseye rash. But Zelis cautions that local variances can get forgotten among the broader national conversations.

She said in the past two months, patients have told her they haven’t received accurate information from doctors. In one case, a woman wrote to her about a friend’s child who was bitten by a tick and was told to wait, and if the child didn’t get a bullseye rash, they were in the clear. Another message was from a parent whose son had a bullseye rash after they got back from a camping trip, but was told by his doctor that as long as he had no other symptoms, he didn’t need to worry — though within a year, the child had almost every known symptom of Lyme.

“I would argue that accurate and prompt diagnosis is a form of prevention,” said Zelis, who is studying for a mental health degree with the aim of helping people affected by Lyme disease. “It’s preventing people from having a more complex and severe form of the disease.”

Seeking treatment

A little over a year ago, Monika Reis of Montpelier noticed an immature tick, called a nymph, lodged in her neck. She later saw a rash, though not the typical bullseye. She went to Plainfield Health Center, where a doctor took a picture of the rash and did blood work — which came back negative for Lyme. Within a week, she had night sweats that were so intense she checked the ceiling to see if there was a leak.

“I had it full on within two weeks. There’s no manufacturing that experience,” Reis said.

So she went back to the doctor, who decided to treat it as Lyme, even though her blood work wasn’t conclusive.

Reis’ experience was in contrast to friends who she knew were in similar situations, but whose doctors didn’t immediately treat it that way.

“We throw antibiotics at children 12 times before they’re 7 for earaches, and suddenly, an adult with a strong feeling and a photo of rash comes in, and you’re not going to treat for Lyme?” Reis said. “There’s a real problem here with the resistance to thinking that it’s Lyme.

In addition to taking doxycycline, the antibiotic typically used to treat Lyme, Reis used herbal remedies and acupuncture. Several of her friends with Lyme regularly go out of state just to see specialists.

Reis stressed that people who suspect they have Lyme have to be assertive about their treatment.

“Even within my own story that’s true,” Reis said. “If someone is not willing to treat you, I’d highly recommend going to another person within a few days, or even a naturopath — somebody that is going to be empathetic to your situation and not have this blocked mentality about it.”

A state law passed in 2014 gave doctors more latitude in their treatment of Lyme by allowing them to treat outside of the guidelines set by the Infectious Disease Society of America.

But Rachel Nevitt, who advocated for the bill, believes Vermont’s response to the disease is badly outdated.

“The truth of the matter is providers here are clueless,” Nevitt said. “Some are catching on, but those catching on are afraid to treat it the way it needs to be treated because the medical boards will come after them.”

Nevitt had likely had the disease for years before she was finally diagnosed. In 2009, Nevitt suddenly fell to the floor with excruciating spinal pain. She presented like she had a herniated disc, but had no precipitating accident, and an MRI showed up normal. Today, Nevitt said, people know that means Lyme. But back then, it was just another bullet point in her laundry list of symptoms she couldn’t explain.

Nevitt was becoming dyslexic, forgetful, and losing spatial awareness. Once, she accused her husband of spending $80,000 on a new irrigation system for their farm simply because she couldn’t recognize the irrigation system that they’d been using for years.

It wasn’t until her farm manager tested positive for the disease and told Nevitt she should get tested that she began to even consider Lyme. But Nevitt knew she never saw a tick bite, and never had a rash — she couldn’t have Lyme. It took weeks before she finally realized, “Oh my God, that’s what I have.”

But even then, she struggled to get a diagnosis — or even get tested. Nevitt didn’t find treatment until she left the state to see a specialist in the Hudson River Valley.

“At that point, I really realized everything that people who have Lyme say is true,” she said. “Something is wrong with the medical community, they just think we’re all crazy.

One thing that’s common with Lyme patients, Nevitt said, is that at some point, a stressful life event causes their symptoms to get very bad very quickly. She said for a lot of people, it can be something tragic like the loss of a child or a divorce. Nevitt said in her case, it was when her husband, now-Lt. Gov. David Zuckerman, ran for state Senate in 2012, which left her to run their organic farm alone.

Vermont’s Lyme research is 20 years behind, she said.

“Name one disease that they’re relying on that old of research for,” Nevitt said. “If you talk to anybody with Lyme, they’ll tell you the medical community here is woefully far behind.”

Frustrating for doctors and patients

“When we don’t understand the mechanisms for something, it’s very frustrating for patients and very frustrating for us.”– UVM Medical Center Rheumatologist Ralph Budd.

Doctors acknowledge that they don’t have all the answers on Lyme disease.

Ralph Budd, a rheumatologist at UVM Medical Center who specializes in Lyme-linked arthritis, said people are often convinced that if they have symptoms, they also have an ongoing infection, though that often isn’t the case. He said treating symptoms tends to be a very effective option once the infection period has passed.

“When we don’t understand the mechanisms for something, it’s very frustrating for patients and very frustrating for us,” Budd said. “Medicine has many of those — Lyme is not the only one.”

Budd is wary of specialized labs that cater to Lyme testing. He said unlike the tests he uses, which need the Lyme antibodies to develop for six weeks before they are accurate, other labs have faster tests that he says have been proven to return a higher rate of false positives.

“When patients think they have something, and they’re not feeling well, of course they shop around and look for something to help,” Budd said. “But if the lab gives them falsely positive results, that can really do a disservice to the medical community.”

Kwit, of the Vermont Department of Health, echoed this sentiment.

“It is important to correctly diagnose Lyme disease when someone has it. But it is equally important not to misdiagnose someone with Lyme disease when the cause is really something else,” she said.

A misdiagnosis of Lyme disease could lead to a long road of treatment that doesn’t work, and could result in an illness that lasts longer, she said. She urges the use of validated, evidence-based methods to diagnose the disease.

There’s currently a rift in the Lyme community over the best ways to address the disease. Some advocates are looking to guidelines put out by the International Lyme and Associated Diseases Society, which they believe are more accurate ways to test. But those standards are not endorsed by the Centers for Disease Control and are regarded with skepticism by many in the medical community.

Alexis Chesney, a naturopathic Lyme specialist, said the best way to address Lyme is to prevent it.

She pointed out a number of recommendations to help prevent the disease’s spread, including treating clothes with tick repellent, showering within two hours of being outdoors, checking pets to make sure they don’t carry ticks inside, and drying clothes on hot for 10 minutes as soon as you get inside to make sure any ticks — which are often as small as poppy seeds — are gone.

“I would love for people to stop getting tick bites,” Chesney said. “Then we could really solve this tick epidemic.”

_________________

**Comment**

Those getting the rash varies from 25-80% – hardly something to bank on. The myth that everyone gets the “classic” EM rash needs to be dropped like a bad habit.

The skepticism of smaller CLIA-certified labs is unwarranted. They undergo the most strenuous lab requirements and specialize in bacteriology and virology. Lyme has always been a clinical diagnosis.

Being told to “wait and see” after a tick bite is asinine. Insanity is doing the same thing over and over and expecting different results. We all know early treatment is everything – SO, WHY WAIT?

Doctors desperately need to become educated on tick borne illness.  And yes, Lyme/MSIDS can cause psychological symptoms:  https://madisonarealymesupportgroup.com/2018/08/25/neuropsychiatric-lyme-borreliosis-an-overview-with-a-focus-on-a-specialty-psychiatrists-clinical-practice/

https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/

https://madisonarealymesupportgroup.com/2019/02/16/lyme-is-all-in-your-head-a-wake-up-call-to-mental-health-professionals/

The fact doctors are STILL afraid to treat patients is telling. This is wrong on so many levels and indicates a huge problem: https://madisonarealymesupportgroup.com/2018/12/15/everything-about-lyme-disease-is-steeped-in-controversy-now-some-doctors-are-too-afraid-to-treat-patients/

Do you hear of doctors being afraid to treat diabetes, cancer, or syphilis?

No. Why? Because insurance companies aren’t pulling strings on those diseases.

Managed care is the problem: https://madisonarealymesupportgroup.com/2017/08/19/dr-liegner-guidelines-used-by-managed-care-causing-lyme-deaths/

https://madisonarealymesupportgroup.com/2019/08/01/why-we-need-to-stop-treating-lyme-disease-like-a-typical-infectious-disease/

https://madisonarealymesupportgroup.com/2018/06/14/corruption-human-rights-violations-against-lyme-doctors-scientists-and-parents-now-on-united-nations-record/