Archive for the ‘Testing’ Category

The History Of Lyme Disease – Dr. Burrascano

https://www.ilads.org/dr-burrascano-happy-holidays/?  Approx. 43 Min.

The History of Lyme Disease

Dr. Burrascano explains and debunks much of what is accepted and blindly promoted in main-stream medicine about Lyme.

For a summary of the video go hereGo here for an article that presents a bird’s-eye view of the entire issue.

He also shares what he discovered worked with patients, including himself, often by trial and error.

Important takeaways:

  • Burrascano found that blood levels of various drugs in some patients was low or even undetectable.  In other words, the level of doxycycline in the blood for instance, was too low to kill anything, which helps explain why some fail antibiotic therapy.  (Scroll to 17:30 for this information.)  He also cringes because the CDC guidelines state all patients should receive 200mg of doxycycline, which sets some patients up for failure.  Doctors should do blood levels on patients to determine if it’s working.
  • He, as well as ILADS, recommends being symptom-free for 2-4 months before stopping treatment.  Then, wait until symptoms return and go back on treatment.  This is called Cycling.  He found that cycling 3-4 times typically worked for most patients.  Ironically, the 3rd cycle yielded the worst herx.  Pam Weintraub wrote about this in, “Cure Unknown:  Inside the Lyme Disease Epidemic,” way back in the 90’s, yet few doctors do this.
Please share this with family, friends, doctors, and researchers.

Relapsing Fever Spirochete Uniquely Adapted to Highly Oxidative Salivary Glands of Soft-bodied Tick

https://www.ncbi.nlm.nih.gov/pubmed/30489694

2018 Nov 29:e12987. doi: 10.1111/cmi.12987. [Epub ahead of print]

The relapsing fever spirochete Borrelia turicatae persists in the highly oxidative environment of its soft-bodied tick vector.

Abstract

The relapsing fever spirochete Borrelia turicatae possesses a complex life cycle in its soft-bodied tick vector, Ornithodoros turicata. Spirochetes enter the tick midgut during a bloodmeal, and during the following weeks spirochetes disseminate throughout O. turicata. A population persists in the salivary glands allowing for rapid transmission to mammalian hosts during tick feeding. Little is known about the physiological environment within the salivary glands acini in which B. turicatae persists. In this study, we examined the salivary gland transcriptome of O. turicata ticks and detected the expression of fifty-seven genes involved in oxidant metabolism or antioxidant defenses. We confirmed the expression of five of the most highly expressed genes including glutathione peroxidase (gpx), thioredoxin peroxidase (tpx), manganese superoxide dismutase (sod-1), copper-zinc superoxide dismutase (sod-2), and catalase (cat) by reverse-transcriptase droplet digital PCR (RT-ddPCR). We also found distinct differences in the expression of these genes when comparing the salivary glands and midguts of unfed O. turicata ticks.

Our results indicate that the salivary glands of unfed O. turicata nymphs are a highly oxidative environment where reactive oxygen species (ROS) predominate, while midgut tissues comprise a primarily nitrosative environment where nitric oxide synthase is highly expressed. Additionally, B. turicatae was found to be hyperresistant to ROS compared to the Lyme disease spirochete B. burgdorferi, suggesting that it is uniquely adapted to the highly oxidative environment of O. turicata salivary gland acini.

___________________

**Comment**

Much can be learned about Borrelia turicatae by reading this case study:  https://wwwnc.cdc.gov/eid/article/23/5/16-2069_article

We learn:

  • Ornithodoros turicata soft bodied ticks, are endemic to Texas and Florida
  • They are found in caves and ground squirrel or prairie dog burrows  https://madisonarealymesupportgroup.com/2018/04/23/tick-borne-relapsing-fever-found-in-austin-texas-caves/
  • Once infected, they remain infected for the rest of their lives, which can be up to ten years.
  • Attachment is painless
  • They are rapid night feeders (5-60min)
  • Due to their rapid feeding they are rarely found or leave lesions
  • Patient in study suffered with headache, nausea, & pain behind knees
  • Had numerous lesions which resolved after 6 days (without treatment)
  • Developed persistent fever
  • Developed thrombocytopenia (low platelets)
  • Developed elevated Erythrocyte sedimentation rate & C-reactive protein
  • Improved rapidly with doxycycline
  • Platelet count normalized within 2 weeks
  • Asymptomatic soldiers with similar exposure were treated prophylactically
  • TBRF is a neglected and probably underdiagnosed disease
  • Published cases in Texas have been supported by serology for the TBRF group, exposure location, and tick collections, but the authors state successful identification of B. turicatae in a human has not been reported
  • Military training groups in Israel have declared certain caves off limits because of heavy tick presence https://madisonarealymesupportgroup.com/2017/10/27/israeli-kids-get-lyme-disease-from-ticks-in-caves/ and have prophylactically administered doxycycline to those suspected to have been exposed
  • Asymptomatic patients given doxy don’t have a Jarisch-Herxheimer reaction but those with active illness do
Another study demonstrating the wily and adaptable nature of spirochetes.


Baggio-Yoshinari Brazil’s Lyme-Like Illness From Ticks That Shouldn’t Transmit it

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6218955/

. 2018; 73: e394.
Published online 2018 Nov 6. doi: 10.6061/clinics/2018/e394
PMCID: PMC6218955
PMID: 30462754

Passage of Borrelia burgdorferi through diverse Ixodid hard ticks causes distinct diseases: Lyme borreliosis and Baggio-Yoshinari syndrome

Abstract

Baggio-Yoshinari syndrome is an emerging, tick-borne, infectious disease recently discovered in Brazil. This syndrome is similar to Lyme disease, which is common in the United States of America, Europe and Asia; however, Brazilian borreliosis diverges from the disease observed in the Northern Hemisphere in its epidemiological, microbiological, laboratory and clinical characteristics. Polymerase chain reaction procedures showed that Baggio-Yoshinari syndrome is caused by the Borrelia burgdorferi sensu stricto spirochete. This bacterium has not yet been isolated or cultured in adequate culture media. In Brazil, this zoonosis is transmitted to humans through the bite of Amblyomma and Rhipicephalus genera ticks; these vectors do not belong to the usual Lyme disease transmitters, which are members of the Ixodes ricinus complex. The adaptation of Borrelia burgdorferi to Brazilian vectors and reservoirs probably originated from spirochetes with atypical morphologies (cysts or cell-wall-deficient bacteria) exhibiting genetic adjustments, such as gene suppression. These particularities could explain the protracted survival of these bacteria in hosts, beyond the induction of a weak immune response and the emergence of serious reactive symptoms. The aim of the present report is to note differences between Baggio-Yoshinari syndrome and Lyme disease, to help health professionals recognize this exotic and neglected zoonosis.

___________________

**Comment**

This abstract shows a Bbss spirochete NOT YET isolated or cultured in adequate culture media, i.e., is invisible to current lab techniques.  Also, please note that the ticks mentioned are not TYPICALLY thought of as transmitting Lyme.

Two commonly touted myths busted to smithereens.

The plot thickens with the mere mention of ATYPICAL morphologies (cysts or cell wall deficient) bacteria as well as GENETIC ADJUSTMENTS WITH GENE SUPRESSION, and the ability of these bacteria to SURVIVE FOR A LONG TIME.  

To this day, the CDC/IDSA refuses to recognize the persistent nature and pleomorphism of Bb.

Researchers who talk about pleomorphism are almost always from outside the U.S.:  https://www.frontiersin.org/articles/10.3389/fmicb.2017.00596/full  There’s only a handful of U.S. researchers taking on pleomorphism.  All the IDSA-authors (The Cabal) report about Lyme as if it were a mere nuisance, which it is not.

In short, we have a LYME-LIKE Illness that:

  • can’t be picked up with common lab techniques
  • coming from ticks that don’t normally transmit it
  • caused by a bacteria that shape-shifts
  • makes genetic adjustments to survive

Now add other potential pathogens to this stew and it’s quite clear why patients are so ill and why it takes far more than 21 days of the mono-therapy of doxycycline.

Please spread the word!

For More:  https://madisonarealymesupportgroup.com/2018/10/30/study-shows-lyme-msids-patients-infected-with-many-pathogens-and-explains-why-we-are-so-sick/  This international group of researchers state that:

“Our findings recognize that microbial infections in patients suffering from TBDs do not follow the one microbe, one disease Germ Theory as 65% of the TBD patients produce immune responses to various microbes.”

They also point out that 83% of all commercial tests focus only on Lyme (borrelia), despite the fact we are infected with more than one microbe.

They too mention the pleomorphism of borrelia:

“In addition to tick-borne co-infections and non-tick-borne opportunistic infections, pleomorphic Borrelia persistent forms may induce distinct immune responses in patients by having different antigenic properties compared to typical spirochetes32,33,34,35. Nonetheless, current LD diagnostic tools do not include Borrelia persistent forms, tick-borne co-infections, and non-tick-borne opportunistic infections.”

It’s all right here in bright purple crayon.


Ehrlichiosis Presenting as Severe Sepsis & Meningoencephalitis in an Immunocompetent Adult

https://www.ncbi.nlm.nih.gov/m/pubmed/30425837/

Ehrlichiosis presenting as severe sepsis and meningoencephalitis in an immunocompetent adult.

Buzzard SL, et al. JMM Case Rep. 2018.

Abstract

Introduction: Ehrlichia are obligate intracellular pathogens transmitted to vertebrates by ticks.

Case presentation: We report the case of a 59-year-old man who presented to the University of Kentucky Albert B. Chandler Medical Center (Lexington, KY, USA) after being found fallen down in the woods. A lumbar puncture revealed what appeared to be bacterial meningitis, yet cerebrospinal fluid cultures, Gram stains and a meningitis/encephalitis panel were inconclusive. However, an Ehrlichia DNA PCR of the blood resulted as being positive for Ehrlichia chaffeensis antibodies. The patient received a 14 day course of doxycycline, and recovered from his multiple organ failure. The aetiology of the ehrlichial meningoencephalitis was likely transmission through a tick-bite, due to the patient’s outdoor exposure.

Conclusion: While it is rare to see Ehrlichia as a cause of meningitis, this illness can progress to severe multisystem disease with septic shock, meningoencephalitis or acute respiratory distress syndrome (ARDS). Those with compromised immunity are at a higher risk of developing the more severe form of the disease and have higher case fatality rates.

__________________

**Comment**

Nothing about this monster is rare – it’s just not in the literature yet.  Again, researchers would be wise to remember that just because something isn’t found in the literature, doesn’t mean it doesn’t happen, particularly in a disease complex that testing misses half the cases and much goes unreported because it’s undiagnosed or misdiagnosed.

Notice this poor man was found flat on his face in the woods – that’s how serious this stuff can be.  Please notice his immune system was fine.

Meningeal involvement (brain swelling) is NOT rare.  Why would it be?  When these pathogens can cross the blood/brain barrier, it makes complete, logical sense that people would deal with swelling.  They deal with swelling in their elbows, knees, fingers, wrists, and about every other place in the body.  Dr. Phillips talks about Balanitus, a painful swelling of the foreskin, or head of the penis in males here:  https://madisonarealymesupportgroup.com/2018/12/22/s-e-x-lyme-msids/

I had swelling in my head so great that I wondered if I’d ever go a day without excruciating headaches that honestly felt like I’d been kicked by a horse, but the pain was completely all over in the lining of my head (meningeal).  I had an MRI, which came back normal, but I’ve met numerous folks with a Lyme and Chiari diagnosis:  https://madisonarealymesupportgroup.com/2016/04/02/chiari/

Warning – some with Lyme/MSIDS go through with the Chiari surgery but continue to have symptoms because until the pathogens are dealt with, symptoms will not resolve.  

Now, I’m just a crazy gray-hair, but doesn’t it seem quite logical to have swelling in the brain with Lyme/MSIDS?

For more:  https://madisonarealymesupportgroup.com/2018/12/02/everything-thats-known-about-ehrlichiosis/

https://madisonarealymesupportgroup.com/2018/10/15/ehrlichiosis-masquerading-as-thrombotic-thrombocytopenia-purpura/

https://madisonarealymesupportgroup.com/2018/10/02/north-carolina-ehrlichia-often-overlooked-when-tick-borne-illness-suspected/

https://madisonarealymesupportgroup.com/2018/07/24/oklahoma-ehrlichiosis-central/

https://madisonarealymesupportgroup.com/2018/11/11/gestational-lyme-other-tick-borne-diseases-dr-jones/

https://madisonarealymesupportgroup.com/2018/03/09/dogs-ehrlichiosis/

Diagnosing LD in Children With Neuropsychiatric Illness

https://www.rheumatologyadvisor.com/lyme-disease/lyme-disease-diagnostic-uncertainty-in-children-with-neuropsychiatric-illness/article/783880/

Diagnosing Lyme Disease in Children With Neuropsychiatric Illness

Please see comment at end of article
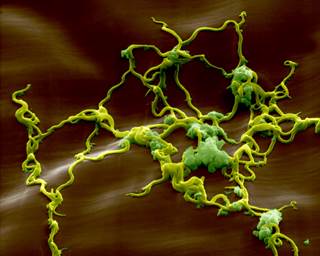
There is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize in children. <i>Credit:Eye of Science/Science Source</i>
There is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize in children. Credit:Eye of Science/Science Source


Lyme disease can present with a multitude of symptoms that often mimick other diseases, making differential diagnosis difficult. Neurologic involvement has been reported in up to 15% of untreated Borrelia burgdorferi infection,1 which can be devastating, particularly in children and young adults, who have been reported to be more at risk. According to the US Centers for Disease and Control and Prevention (CDC), Lyme disease is on the rise.2 Each year, at least 300,000 people in the United States are diagnosed with Lyme disease, with the highest infection rates occurring in children age 5 to 10 years.2,3

Lyme neuroborreliosis can affect any part of the nervous system, and there are a wide range of neurologic and psychiatric symptoms that can manifest weeks, months, or even years after the initial infection. For example, memory impairment, irritability, and somnolence have been reported months to years after the initial classic presentation of Lyme disease, and encephalopathy has been reported to occur more than 10 years after the onset of the disease.4,5 The presenting neurologic symptoms, including facial palsy, debilitating fatigue, various levels of cognitive loss, psychiatric symptoms, behavior changes, and learning difficulties have a significant and negative effect on the critical stages of child development, including school attendance and decline in school performance.6,7

Full recovery from Lyme neuroborreliosis can be achieved when the disease is diagnosed promptly and accurately and appropriate treatment is initiated. However, there is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize and diagnose in children. Shannon Delaney, MD, MA, director of child and adolescent research and evaluation at the Lyme and Tick-Borne Diseases Research Center at Columbia University Medical Center in New York told Rheumatology Advisor that,

“Neuroborreliosis can be missed because it is not considered in the differential [diagnosis] and because spinal taps are often not [performed] unless a child has very obvious symptoms of encephalitis or meningitis.”

The overlap of symptoms with other neurologic, cognitive, and psychiatric symptoms contributes to the delayed diagnosis or the misdiagnosis. For example, case reports of neuropsychological manifestations of Lyme disease include Tourette syndrome, acute delirium, catatonia, and psychosis.8

Dr Delaney advises that,

“Any child with acute onset neuropsychiatric symptoms, such as [obsessive-compulsive disorder], psychosis, restricted eating, sensory issues, urinary frequency, anxiety, cognitive dysfunction, or extreme fatigue should be given a set of lab tests to rule out typical infectious causes of Pediatric Acute-onset Neuropsychiatric Syndrome/Pediatric Autoimmune Neuropsychiatric Disorder Associated with Streptococcal Infections.”

Dr Delaney added,

“Testing should include a Lyme ELISA [enzyme-linked immunosorbent assay], preferably Borrelia burgdorferi C6 peptide, and a Lyme Western blot to evaluate for exposure to Lyme disease.”

Because symptoms of Lyme neuroborreliosis affect the joints, muscle, and the central and peripheral nervous systems, health professionals from many disciplines, including neurology and psychiatry, need to be able to recognize the clinical presentations, know the essential diagnostic tests, and understand the treatment approach. Erythema migrans is a distinct early presentation of localized Lyme disease,8 and for the experienced physician, this presentation can be sufficient for a clinical diagnosis. Serologic testing at this early disease stage is of limited diagnostic value because of the high incidence of false negative results.

When serologic testing is indicated, the Infectious Diseases Society of America (IDSA) recommend enzyme immunoassay for Lyme-specific antibodies, confirmed with Western immunoblot assay for immunoglobin G; however, many physicians struggle with the correct interpretation of Western blot results.9,10 Dr Delaney cautions,

“Clinicians should be aware that the 2-tier method of testing (ELISA and Western blot), while informative, can have false negative [results] and, less frequently, false positive [results].” Furthermore, although several tests for Lyme disease are available commercially, many are not validated for clinical use, and the CDC strongly warns against their use, as they have been associated with high levels of misdiagnosis.8  

The IDSA recommends antibiotics for the treatment of Lyme disease for a period of 10 to 21 days for early disease and 2 to 4 weeks for late disease.9 Despite the recommendations, studies that distinguish the treatment of Lyme disease from that of Lyme neuroborreliosis are lacking.9 In fact, a systematic review that examined antibiotic treatment for Lyme neuroborreliosis in 450 participants included no trials conducted in the United States.11 The review found no clear evidence for the additional efficacy of repeated antibiotics beyond the initial treatment.11

In addition, prolonged use of antibiotics to treat post-Lyme disease symptoms has not been shown to be efficacious and is generally not recommended, as fatalities from Clostridium difficile and Candida parapssilosis have been reported.8

Clinically, we do recognize that there are a subset of patients who only get better after a repeated course of antibiotics,” said Dr Delaney, adding, “In the future as the science progresses, hopefully, we will be able to make use of blood tests that provide biomarkers indicating who needs additional antibiotic therapy and who needs another approach. This is the age of precision medicine and our goal at Columbia is to help in the identification of these essential biomarkers that will help guide treatment.”

The need for additional research is evident to better define the optimal use of antibiotics for the treatment of Lyme neuroborreliosis.11 The effect of long-term use of antibiotics also deserves attention. Inappropriate antibiotic use can alter the balance of the gut microbiome and may lead to side effects. The effect of long-term antibiotics on the gut microbiome is an area of emerging study and should provide very useful information in the future regarding whether or not the alterations themselves are contributing to ongoing symptoms. Until more research is available to better guide the management of the neurologic manifestations of B burgdorferi infection, it is important that physicians have heightened awareness of Lyme disease. They must also have a clinical suspicion of Lyme neuroborreliosis in children who present with neuropsychiatric illness and must diagnose the disease promptly and provide appropriate treatment, which may include referral for appropriate symptom management.

References

  1. Marques AR. Lyme neuroborreliosis. Continuum (Minneap Minn). 2015;21(6):1729-1744.
  2. US Centers for Disease Control and Prevention. Lyme disease. Lyme disease graphs. https://www.cdc.gov/lyme/stats/graphs.html. Updated November 1, 2017. Accessed July 17, 2018.
  3. US Centers for Disease Control and Prevention. Lyme disease. How many people get Lyme disease? https://www.cdc.gov/lyme/stats/humancases.html. Updated September 30, 2015. Accessed July 17, 2018.
  4. Bloom BJ, Wyckoff PM, Meissner HC, Steere AC. Neurocognitive abnormalities in children after classic manifestations of Lyme disease. Pediatr Infect Dis J. 1998;17(3):189-196.
  5. Szer IS, Taylor E, Steere AC. The long-term course of Lyme arthritis in children. N Engl J Med. 1991;325(3):159-163.
  6. Lyme Disease Action. Neurology and Psychiatry. Involvement of the Central and Peripheral Nervous System. https://www.lymediseaseaction.org.uk/about-lyme/neurology-psychiatry/. Updated November 26, 2016. Accessed July 17, 2018.
  7. Cameron D. Adolescents with Lyme disease. http://danielcameronmd.com/adolescent-lyme-disease/. 2018. Accessed July 17, 2018.
  8. Koster MP, Garro A. Unraveling diagnostic uncertainty surrounding Lyme disease in children with neuropsychiatric illness.Child Adolesc Psychiatr Clin N Am. 2018;27(1):27-36.
  9. Wormser GP, Dattwyler RJ, Shapiro ED, et al. The clinical assessment, treatment, and prevention of Lyme disease, human granulocytic anaplasmosis, and babesiosis: clinical practice guidelines by the Infectious Diseases Society of America. Clin Infect Dis. 2006;43(9):1089-1134.
  10. Conant JL, Powers J, Sharp G, Mead PS, Nelson CA. Lyme disease testing in a high-incidence state: clinician knowledge and patterns. Am J Clin Pathol. 2018;149(3):234-240.
  11. Cadavid D, Auwaerter PG, Rumbaugh J, Gelderblom H. Antibiotics for the neurological complications of Lyme disease. Cochrane Database Syst Rev. 2016;12:CD006978.

__________________

**Comment**

A few points of contention:

  1. While the EM rash IS an early symptom that clinically proves the person has Lyme, many never see or have a rash at all or it is certainly not a “typical” EM rash.  Clinicians need education in this.
  2. Numbers are notoriously low on all things Lyme/MSIDS, including this supposed 15% who have neurologic involvement.  Everyone I work with is in this category so I’m either just a lucky-duck or the numbers are far higher in the real world.  I suspect the latter.
  3. Testing for Lyme/MSIDS IS ABYSMAL.  Absolutely worthless.  It misses over half of all cases.  I’m thankful the article states professionals need to be educated because this is a CLINICAL DIAGNOSIS.  Anyone who says otherwise is smoking something.  Again, clinicians need education.
  4. Where the article really falls apart is in the treatment section.  This article ONLY discusses the IDSA approach which is essentially 21 days of doxycycline despite the presentation.  I couldn’t disagree more.  If you read the ILADS guidelines, you will discover that treatment is far more complex.  There are many who have gotten well or improved dramatically with this approach.  The reason for this is numerous:  1) we are typically infected with more than borrelia, necessitating numerous drugs 2) all of these pathogens are stealthy and many are persistent requiring far longer treatment courses than appreciated 3) these pathogens work together to suppress the immune system and complicate the picture requiring numerous treatments
  5. The Cochrane review of antibiotics for neuro-Lyme mentioned had numerous flaws: none included a placebo control, only ONE was blinded, most were not adequately powered for non-inferiority comparison, they ONLY investigated four antibiotics:  penicillin G & ceftriaxone in 4 studiesdoxycycline in 3 studies, cefotaxime in two studies, and amoxicillin vs. placebo for only 3 months following initial treatment with IV ceftriaxone.  (I consider many of these antibiotics poor choices for Lyme and I’ve never taken two of them.  I had to look one up as I’d NEVER even heard of it!) The trials measured efficacy using heterogeneous physician‐ or patient‐reported outcomes, or both.  None of the studies reported on the proposed primary outcome, ‘Improvement in a measure of overall disability in the long term (three or more months).’ The quality of adverse event reporting was low.  So, as far as I’m concerned this “review” is extremely weak yet it’s presented as evidence that long-term antibiotics do not work.  Please see this article for comparison:  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/  Also, I would not be writing this article without the judicious use of long-term antibiotics.
  6. It’s interesting that although the author disses long-term antibiotics using the IDSA clap-trap and an extremely weak and flawed review, she did include the quote from Dr. Delaney,

“Clinically, we do recognize that there are a subset of patients who only get better after a repeated course of antibiotics,” said Dr Delaney

Hmmm….that appears to be a cognitive disconnect.

To clear the record:  nearly all of us out here in Lymeland HATE taking antibiotics.

We take them because they often work better than other things we’ve tried.  They are also more affordable than other many other options.

But, if we could press some magic button, believe me –  we would.  

I find it interesting that people with acne can take antibiotics forever, yet patients with life-threatening tick-borne illness are told extended antibiotics can give them C-diff, therefore they are bad and shouldn’t be considered.  Period.

 This disconnect is wholly unacceptable.