Archive for the ‘Testing’ Category

Borrelia Miyamotoi Infection Leads to Cross-Reactive Antibodies to the C6 Peptide in Mice & Men

https://www.clinicalmicrobiologyandinfection.com/article/S1198-743X(19)30418-5/fulltext

Borrelia miyamotoi infection leads to cross-reactive antibodies to the C6 peptide in mice and men

Joris Koetsveld1,,'Correspondence information about the author Joris Koetsveld
Alexander E. Platonov2
Konstantin Kuleshov2
Alex Wagemakers1
Dieuwertje Hoornstra1
Wim Ang3
Sandor Szekeres4
Gilian L.A. van Duijvendijk5
Erol Fikrig6
Monica E. Embers7
Hein Sprong4
Joppe W. Hovius1,∗∗,'Correspondence information about the author Joppe W. Hovius

Abstract

Objectives

Borrelia miyamotoi is a relapsing fever Borrelia, transmitted by hard (Ixodes) ticks, which are also the main vector for Borrelia burgdorferi. A widely used test for serodiagnosis of Lyme borreliosis is an EIA based on the C6 peptide of the B. burgdorferi sl VlsE protein. We set out to study C6 reactivity upon infection with B. miyamotoiin a large well-characterized set of Borrelia miyamotoi disease (BMD) patient sera and in experimental murine infection.

Methods

We performed in-silico analyses, comparing the C6-peptide to immunodominant B. miyamotoi variable large proteins (Vlps). Next, we determined C6 reactivity in sera from mice infected with B. miyamotoi and in a unique longitudinal set of 191 sera from 46 BMD patients.

Results

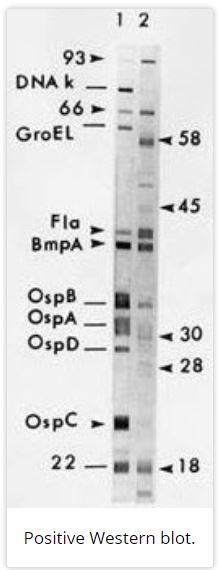
In-silico analyses revealed similarity of the C6-peptide to domains within B. miyamotoi Vlps. Cross-reactivity against the C6-peptide was confirmed in 21/24 mice experimentally infected with B. miyamotoi.Moreover, 35/46 BMD patients had a C6 EIA Lyme-index higher than 1.1 (positive). Interestingly, 27/37 patients with a C6 EIA Lyme-index higher than 0.9 (equivocal) were negative when tested for specific B. burgdorferi sl antibodies using a commercially available immunoblot.

Conclusions

We show that infection with B. miyamotoi leads to cross-reactive antibodies to the C6-peptide. Since BMD and Lyme borreliosis are found in the same geographical locations, caution should be used when relying solely on C6-reactivity testing. We propose that a positive C6 EIA with negative immunoblot, especially in patients with fever several weeks after a tick bite, warrants further testing for B. miyamotoi.

_________________

**Comment**

For a great read on cross -reactivity in testing:  https://lymemd.blogspot.com/2014/08/labcorp-and-lyme-western-blot.html  Written by Dr. Jaller

The article makes some excellent points:

  • As of 2014 Labcorp no longer allows physicians to order Western Blots for Lyme disease. The only test available is the ELISA with reflex to Western Blot if positive.
  • They have also taken away the C6 peptide.  The results are presented as only negative if less than 0.91
  • Some ID doctors are inappropriately applying the HIV testing paradigm in the case of Lyme testing
  • The IDSA claims, without reference, there’s a lot of false positive Lyme Western Blots because of cross reactivity
  • The test was developed based on a meeting 20 years ago for surveillance (an epidemiology or research tool) not for diagnosis
  • The long arm of the IDSA has managed to promote its agenda by manipulating the CDC and now Labcorp
  • CDC’s Dr. Beard’s s comment to the author was an admission that politics have trumped reason, logic and science when he stated about the flawed testing, “Well, that’s the party line.”
The testing stronghold dilemma continues unabated in the topsy-turvy world of Lymeland.

Remember….

64357008_10217935576008450_2638357839671721984_n

“I am Barbara Johnson. I am a biochemist by training and I am speaking today on behalf of the Centers for Disease Control and Prevention concerning serodiagnosis of Lyme disease. Specifically, my statement is in support of (the) IDSA recommendation in the guidelines to use two-tiered serology (an ELISA screening test followed by Western Blots if ELISA positive) to support the diagnosis of Lyme disease in patients who have manifestations other than acute erythema migrans.  – IDSA Lyme Disease Review Panel Hearing, July 30, 2009

For more dirty deeds done dirt cheap: ConflictReport
 

New Alzheimer’s Blood Test 94% Accurate

https://www.medscape.com/viewarticle/916372

New Alzheimer’s Blood Test 94% Accurate

Megan Brooks

August 02, 2019

A new blood test to detect brain changes emblematic of early Alzheimer’s disease (AD) has moved one step closer to reality and could be a “game changer” for the field.

Researchers found that measuring the ratio of β-amyloid (Aβ) 42 and Aβ40 in blood using a high-precision assay is 94% accurate in diagnosing brain amyloidosis, using amyloid PET or CSF phosphorylated (p-tau) 181/Aβ42 as reference standards.

“Right now we screen people for clinical trials with brain scans, which is time-consuming and expensive, and enrolling participants takes years,” senior investigator Randall J. Bateman, MD, professor of neurology, Washington University School of Medicine in St. Louis, said in a statement.

“But with a blood test, we could potentially screen thousands of people a month. That means we can more efficiently enroll participants in clinical trials, which will help us find treatments faster, and could have an enormous impact on the cost of the disease as well as the human suffering that goes with it,” he added.

The study was published online August 1 in Neurology.

Easy Screening Tool

Using an immunoprecipitation and liquid chromatography–mass spectrometry assay, the researchers measured Aβ42/Aβ40 in plasma and CSF samples from 158 older, mostly cognitively normal individuals (94% with Clinical Dementia Rate [CDR] = 0) that were collected within 18 months of an amyloid PET scan.

Plasma Aβ42/Aβ40 correlated highly with amyloid PET status (receiver operating characteristic area under the curve [AUC], 0.88; 95% confidence interval [CI], 0.82 – 0.93) and CSF p-tau181/Aβ42 (AUC, 0.85; 95% CI, 0.79 – 0.92), the researchers report.

The combination of plasma Aβ42/Aβ40, age, and apolipoprotein (APOE) ε4 status had “very high” correlation with amyloid PET (AUC, 0.94; 95% CI, 0.90 – 0.97), “suggesting that plasma Aβ42/Aβ40 may be used as a screening tool for those at risk of AD dementia,” the researchers write.

In addition, individuals with a positive plasma Aβ42/Aβ40 but negative amyloid PET scan have a 15-fold higher risk of converting to amyloid PET-positive (P = .01).

“The sensitivity of the plasma Aβ42/Aβ40 assay to amyloid PET-negative individuals who convert to amyloid PET-positive suggests that plasma Aβ42/Aβ40 becomes positive earlier than the established amyloid PET threshold used for this study,” Bateman and colleagues note in their report.

“Therefore, a positive plasma Aβ42/Aβ40 with a negative amyloid PET scan may represent early amyloidosis rather than a false-positive result in some individuals,” they add.

As reported by Medscape Medical News, the study builds on earlier work by the same researchers.

________________

For more: https://madisonarealymesupportgroup.com/2019/07/10/lyme-alzheimers-enbrel-new-potential-treatment/

https://madisonarealymesupportgroup.com/2019/04/09/the-diagnosis-is-alzheimers-but-thats-probably-not-the-only-problem/

https://madisonarealymesupportgroup.com/2019/03/09/researchers-identify-herpes-1-chlamydia-pneumoniae-several-types-of-spirochaete-as-major-causes-of-alzheimers/

https://madisonarealymesupportgroup.com/2017/01/18/a-bug-for-alzheimers/

https://madisonarealymesupportgroup.com/2016/06/09/alzheimers-byproduct-of-infection/

https://madisonarealymesupportgroup.com/2016/11/17/antibiotics-and-alzheimers/

https://madisonarealymesupportgroup.com/2016/06/03/borrelia-hiding-in-worms-causing-chronic-brain-diseases/

https://madisonarealymesupportgroup.com/2018/03/25/a-brief-history-of-neuroborreliosis-research-dementia-an-inside-look-at-two researchers/https://madisonarealymesupportgroup.com/2016/11/17/alzheimers-lyme

The Basics of Serology

https://www.galaxydx.com/the-basics-of-serology/

The Basics of Serology

Mom Urges Daily Tick Inspections After Lyme ‘Nightmare’

Mom Urges Daily Tick Inspections After Lyme ‘Nightmare’

Published on Aug 1, 2019

‘It was a nightmare’: Kemptville mom relives stress of her 5-year-old’s missed diagnosis

Mother warns parents to include tick inspections in daily routine for children

Five-year-old Chase Green is seen here at CHEO. (Supplied by Mandy Green)

The mother of a five-year-old boy from eastern Ontario now recovering from Lyme disease and meningitis says some doctors still aren’t recognizing the symptoms, and is calling for better education about them.

Mandy Green said that last week, an emergency room doctor and a family doctor mistook her son Chase’s condition for the flu or an allergy and sent him back to their home in Kemptville, south of Ottawa.

Days later, Chase ended up in a hospital bed at the area’s children’s hospital, hooked up to heart monitors and an IV to pump antibiotics through his system.

A spinal tap and blood tests at CHEO had revealed Chase was suffering from early disseminated Lyme disease with meningitis, an inflammation of the lining of the brain.

“It was a nightmare, it was awful,” said Green, “and it could have been prevented.”

Spot, circles

It began innocuously enough.

On July 20, Green noticed a small red spot on Chase’s face that got bigger and turned a brighter red by the evening. When her son woke up the next day, there was a perfect red circle on his shoulder.

“My first thought was it’s a bull’s-eye, it’s Lyme disease,” said Green, who had no recollection of her son being bitten by a tick. A bull’s-eye rash surrounding a tick bite is one of the early symptoms of Lyme disease.

The family drove to the emergency department at Kemptville District Hospital, where they waited for several hours as four more circles appeared on Chase’s wrist, stomach and back.

By then, Green assumed Chase was having an allergic reaction, because nothing she’d ever seen or read about Lyme disease said anything about multiple bull’s-eye rashes.

CBC News
‘It’s the saddest thing I’ve ever experienced’
Mandy Green’s five-year-old son was diagnosed with early disseminated Lyme disease and meningitis after doctors initially mistook his condition for the flu or an allergy. 0:51

Sent home with antihistamine prescription

The family grew tired of waiting and Chase was becoming impatient, so they decided to return home and administer allergy medication.

But by July 22, Chase was feverish, lethargic and complaining of headaches and a sore neck, so they headed back to the hospital.

After almost five hours they saw a doctor who Green said seemed stumped by the symptoms. The physician ordered blood tests and sent them home with a prescription for antihistamines.

Chase’s condition worsened that night, and a visit to the family doctor the morning of July 23 didn’t come up with any more answers. The doctor encouraged the parents to wait for the blood test results.

A map produced by Public Health Ontario shows various Lyme disease risk areas across the province. The Ottawa area is one of those areas estimated to be at risk. (Public Health Ontario)

By the afternoon of the 23rd, Green knew something was wrong when Chase screamed in pain and laid down on the couch.

“As soon as he laid on the couch and didn’t get up, I knew. This isn’t Chase. This is something wrong.”

The parents took Chase to CHEO, where he was quickly given the proper diagnosis.

“He was in so much pain and couldn’t stop crying. I curled up in his hospital bed with him,” Green said.

Chase received antibiotics intravenously and was sent home with a prescription for oral antibiotics.

But that wasn’t the end of it.

On Saturday, Chase appeared to relapse and was readmitted to CHEO, where he underwent surgery to have a catheter inserted into his chest so he could get more antibiotics intravenously at home, monitored by health-care workers. 

Chase required surgery to enable him to continue getting antibiotics intravenously at home, and he’s starting to feel better. (Supplied by Mandy Green)

Dr. Jason Brophy, a pediatric infectious disease specialist at CHEO who did not treat Chase, said he’s seeing an increase in cases of Lyme disease among children in the Ottawa area.

“In the past five years Ottawa has become an endemic area, meaning the ticks in our region carry Lyme disease over 20 per cent of the time,” he said.

A lot of people who contract Lyme can get over it without treatment, but for others it can lead to complications if there’s no medical intervention.

The form of meningitis associated with Lyme disease may occur several weeks after a tick bite, Brophy added.

Full recovery expected

As for Chase, a full recovery is expected.

His mother said she doesn’t blame the medical system for what happened to her son, but she’s calling for better information about the symptoms of Lyme disease to be distributed to health facilities.

She’s also warning parents to keep an eye out for ticks on their children, so they can avoid her son’s painful experience.

On a widely distributed Facebook post about the ordeal, she wrote: “Check your kids for ticks, check yourself. We never found the tick that caused this, so listen to your gut, get second opinions, advocate for yourself and your children.”

___________________


News video- Lyme More Common in UK than Thought

Interview with Janey Cringean – Channel 5 News

Lyme Disease is more common in the UK than thought.

July 31, 2019