Archive for the ‘research’ Category

TBI’s Increasing and Spreading

Tick Borne Infections (TBI’s) were tested in 9 national parks in this study.

As a patient and advocate, I wish researchers would carefully choose their wording when reporting results.  For instance the authors state:  “Ba. microti occurred at just 20% of the parks.   http://jme.oxfordjournals.org/content/early/2016/12/28/jme.tjw213.  That wording will bias people into thinking it isn’t significant, but 20% is nothing to sniff at, particularly when you are one of the 20%.  Also, that is what they discovered.  Someone else may discover something else and if time is any indicator, that number will probably rise.  I would also like to see Bartonella strains added to the pathogen list.  Interesting to note: there are 210 cases of locally acquired Zika in the Continental U.S., yet Congress is considering appropriating billions of dollars toward it.   https://www.cdc.gov/zika/intheus/maps-zika-us.html, http://www.usatoday.com/story/news/2016/01/28/who-warns-zika-spread/79451430/, http://www.usatoday.com/story/news/politics/2016/05/25/zika-funding-mired-congress/84914934/

Abstract

Tick-borne pathogens transmitted by Ixodes scapularis Say (Acari: Ixodidae), also known as the deer tick or blacklegged tick, are increasing in incidence and geographic distribution in the United States. We examined the risk of tick-borne disease exposure in 9 national parks across six Northeastern and Mid-Atlantic States and the District of Columbia in 2014 and 2015. To assess the recreational risk to park visitors, we sampled for ticks along frequently used trails and calculated the density of I. scapularis nymphs (DON) and the density of infected nymphs (DIN). We determined the nymphal infection prevalence of I. scapularis with a suite of tick-borne pathogens including Borrelia burgdorferi, Borrelia miyamotoi, Anaplasma phagocytophilum, and Babesia microti. Ixodes scapularis nymphs were found in all national park units; DON ranged from 0.40 to 13.73 nymphs per 100 m2. Borrelia burgdorferi, the causative agent of Lyme disease, was found at all sites where I. scapularis was documented; DIN with B. burgdorferi ranged from 0.06 to 5.71 nymphs per 100 m2. Borrelia miyamotoi and A. phagocytophilum were documented at 60% and 70% of the parks, respectively, while Ba. microti occurred at just 20% of the parks. Ixodes scapularis is well established across much of the Northeastern and Mid-Atlantic States, and our results are generally consistent with previous studies conducted near the areas we sampled. Newly established I. scapularis populations were documented in two locations: Washington, D.C. (Rock Creek Park) and Greene County, Virginia (Shenandoah National Park). This research demonstrates the potential risk of tick-borne pathogen exposure in national parks and can be used to educate park visitors about the importance of preventative actions to minimize tick exposure.

In the eastern United States, the blacklegged tick, Ixodes scapularis Say, is the primary vector of Borrelia burgdorferi, the causative agent of Lyme disease, which is the most commonly reported vector-borne disease in the United States (Mead 2015). Ixodes scapularis also vectors other pathogens that can cause potentially serious disease, including Borrelia miyamotoi, Anaplasma phagocytophilum, and Babesia microti (Barbour and Fish 1993, Homer et al. 2000, Jin et al. 2012, Krause et al. 2015). Established blacklegged tick populations are nearly continuous across counties in the Northeastern and North-Central United States where the majority of I. scapularis-borne disease cases are reported (Mead 2015, Eisen et al. 2016). The risk of acquiring Lyme disease is influenced by spatio-temporal variation in the density of host-seeking infected nymphs (Diuk-Wasser et al. 2012). This metric often correlates with Lyme disease incidence, though to varying degrees (Mather et al. 1996, Stafford et al. 1998, Falco et al. 1999, Pepin et al. 2012). Human behavior, including time spent in tick-infested areas or engaged in behaviors that enhance or reduce the likelihood of encounters with ticks (Orloski et al. 2000, Connally et al. 2009), also influences the likelihood of acquiring Lyme disease and may explain some of the lack of concordance between measures of density of infected host-seeking nymphs and Lyme disease incidence (Pepin et al. 2012).

Understanding where people may come into contact with infected vector-competent ticks is central to mitigating tick-borne disease risk. For example, in the Mid-Atlantic and Northeastern United States, peridomestic exposure to I. scapularis likely occurs frequently (Falco and Fish 1988, Maupin et al. 1991, Klein et al. 1996, Connally et al. 2006, Feldman et al. 2015), whereas in the North-Central United States, recreational exposures are believed to be more common than peridomestic exposures (Kitron and Kazmierczak 1997, Paskewitz et al. 2001). Regardless of geographic region, previous studies have demonstrated a risk of human exposure to infected host-seeking I. scapularis nymphs in recreational settings (Falco and Fish 1989, Schulze et al. 1992, Oliver and Howard 1998, Paskewitz et al. 2001, Han et al. 2014, Prusinski et al. 2014, Ford et al. 2015). National parks are popular recreation destinations and may represent areas of elevated acarological risk, yet one cannot adequately infer the risk of tick-borne disease for park visitors or employees from the epidemiological surveillance conducted at the county spatial scale (Eisen et al. 2013). National parks often vary ecologically from surrounding areas, and thus the density of infected ticks may differ between settings; further, human behavior within the parks may differ from behavior in surrounding communities.

In this study, we sought to characterize the acarological risk, that is, the risk of human exposure to tick-borne pathogens, in national parks in the Eastern United States. We surveyed frequently used trails in national park units across six Northeastern and Mid-Atlantic States and the District of Columbia, ranging from Maine in the north to Virginia in the south. Our collection efforts focused on the nymphal stage of I. scapularis. This stage likely poses the greatest threat of transmission of B. burgdorferi and other pathogens to humans, as peak activity of questing nymphs occurs in late spring and early summer which coincides with peak onset of human disease (Piesman 1989, Fish 1993, Falco et al. 1999, Mead 2015). Here, we describe the diversity of ticks collected by drag sampling during summer months, density of host-seeking I. scapularis nymphs, and diversity and prevalence of B. burgdorferi, B. miyamotoi, A. phagocytophilum, and Ba. microti infection in I. scapularis nymphs.
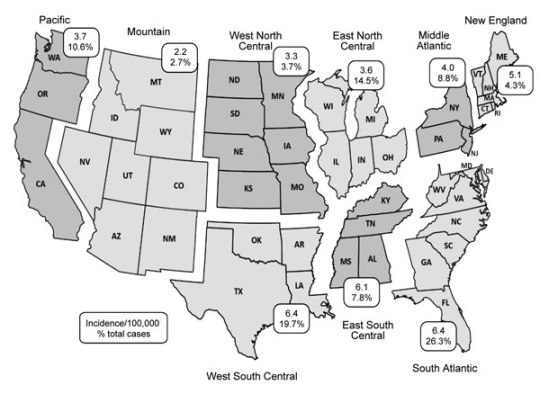
Cardinal state = Bartonella

16-0115-f2

https://wwwnc.cdc.gov/eid/article/22/10/16-0115-f2  Figure 2. Geographic distribution of cat-scratch disease by US census division, United States, 2005–2013. Rates are reported as average incidence per 100,000 population per year. During the study period, there were <10 cases in Alaska and <10 cases in Hawaii.  https://wwwnc.cdc.gov/eid/article/22/10/16-0115_article

http://www.northcarolinahealthnews.org/2016/12/19/north-carolina-ranks-as-high-risk-zone-for-cat-scratch-disease/  By Thomas Goldsmith

“North Carolina cat owners who have a child between 5 and 9 are among groups with the highest national household risk of cat scratch disease.

CDC guidelines recommend that owners keep cats inside at all times as part of guidelines to reduce incidence of cat scratch disease. 

That was among the takeaways from a talk by Centers for Disease Control epidemiologist Christina Nelson, who presented results from the paper, “Cat Scratch Disease in the United States: Sinking Our Claws into the Data,” at the One Medicine conference this month at Research Triangle Park.

‘Efforts should target cat owners in the South, with children in the household, and/or people with immunocompromised conditions,’ Nelson said when talking about ways to combat the disease.

Cat scratch fever, or bartonella, as it’s known to scientists, attracts a lot of attention, perhaps because three of 10 American households have cats, perhaps because of its mention in a risque 1970s rock song, Nelson said. No matter the reason, an edition of Emerging Infectious Diseases in which the Nelson’s article on the disease ran attracted the largest number of online visits in the academic journal’s history.

Cat scratch disease often runs its course within two to four months, but related disorders can require antibiotics or other treatment.

The disease is caused by the spread of the bacterium Bartonella henselae through cat fleas, then to humans via animals’ scratches and sometimes bites. Primary symptoms include fever and enlargement of lymph nodes near the scratch site, but other manifestations can include swelling of the retina or Parinaud oculoglandular syndrome (swollen eye accompanying swollen nodes) as well as bone, brain or heart infections, according to the paper.

Because physicians are not required to report cat scratch disease to public health authorities, Nelson and colleagues examined diagnoses based on an insurance industry resource, Truven Health MarketScan. The database details diagnoses of company-insured employees and their families. That meant people over 65, insured by Medicare, were not included.

‘There were about 35 million people involved,’ Nelson said. ‘It’s an enormous database.’

They found more than 500 inpatients and more than 12,500 outpatients are treated for cat scratch disease annually.

Among the findings of the study:

With an incidence of 6.1-6.4 per 100,000 population, North Carolina lies in the geographic region, the South Atlantic, with the highest U.S. incidence of cat scratch disease. More than one in four U.S. cases occurs in this region.
An average of 4.5 patients out of 100,000 received outpatient treatment for the disease; 19 patients out of 100,000 required inpatient treatment, for an average of three days.
Children age 5 to 9 accounted for the highest incidence of cat scratch fever cases — 9 outpatient cases and .4 inpatient cases per 100,000.
Females made up more than six in 10 outpatients and 55.6 percent of inpatients.
Mean cost of care per inpatient was $244, with inpatient treatment and followup costing $13,663. Overall disease costs nationally were nearly $10 million.
Nelson noted that researchers were puzzled by an increase in cat scratch disease cases in January. Attendees at the RTP conference immediately suggested an answer.

“Christmas kittens!” they chorused.

Among the things the study did not say: That people can get the disease from kissing cats.

Nonetheless, news outlets took the CDC study and ran with it, in some cases, a bit too far. NPR had to run a correction: noting that people cannot get the disease from kissing cats.

‘This is incorrect. People can get the disease if an infected cat licks a scratch or wound,’ the correction read.

How to keep incidence down

Speakers at the conference suggested using the Healthy Pets Healthy People site as a resource for dealing with cat scratch disease.

The CDC suggested these means to reduce incidence:

People bitten by cats should Immediately clean the bite with soap and water
People, especially those with weakened immune systems, should wash their hands with soap and water after playing with cats.
Because kittens less than a year old are more likely to harbor the bacterium, people who have weakened immune systems should adopt cats older than one year.
People shouldn’t play with or pet feral cats.
Cats shouldn’t be allowed to lick open wounds.
Cats should have nails trimmed, use vet-approved flea products, and be checked regularly with a flea comb.
Cats should stay indoors to reduce exposure to fleas and to avoid fights with flea-infected animals.
‘Some shelters will not adopt a cat out unless the owners pledge never to let the cat outside,’ audience member Marcia Herman-Giddens, a Triangle area teacher and researcher, noted during a discussion period.

CSD belongs to the disease group Bartonellosis
‘Bartonellosis is a group of emerging infectious diseases caused by bacteria belonging to the Bartonella genus.
Bartonella includes at least 22 named species of bacteria that are mainly transmitted by carriers (vectors), including fleas, lice, or sandflies. Both domestic and wild animals can be infected with Bartonella species by these vectors.
Among the Bartonella species, at least 14 have been implicated in diseases that can be transmitted from animals to people (zoonotic disease). Of these zoonotic species, several may be transmitted to humans by companion animals (dogs and cats), typically through a bite or scratch.’
Source: National Organization for Rare Disorders

http://www.columbia-lyme.org/patients/tbd_bartonella.html  “Bartonella are also found in numerous arthropods, biting flies, and ticks.  The evidence for ticks as vectors is circumstantial but fairly strong. Recent studies in both the United States and Europe have found that Ixodes ticks harbor B. henselae in addition to Borrelia, Babesia and Anaplasma organisms; in fact, a 2004 PCR analysis of I. Scapularis ticks in New Jersey discovered that a higher percentage of ticks were infected with B. henselae than any of these other pathogens. In addition, B. henselae has been detected in the spinal fluid of patients co-infected with Borrelia burgdorferi, the agent of Lyme disease.”

For more on Bartonella:

https://madisonarealymesupportgroup.com/2011/09/25/the-bartonella-checklist-copyrighted-2011-james-schaller-md-version-11/  (Checklist)

https://madisonarealymesupportgroup.com/2016/01/03/bartonella-treatment/ (Treatment)

https://madisonarealymesupportgroup.com/2016/08/09/a-bartonella-story/

https://madisonarealymesupportgroup.com/2016/02/08/new-bartonella-species/

https://madisonarealymesupportgroup.com/2015/07/23/understanding-bartonella/ (Webinar by Galaxy Labs and leading Bart expert Dr. Breitschwerdt, DVM and B. Robert Mozayeni, MD.

https://madisonarealymesupportgroup.com/2016/04/24/gardasil-and-bartonella/


Dr. Zhang on Persisters


  24 Min.

Made possible by Canadian Lyme Disease Foundation:  https://canlyme.com

Published on Oct 7, 2016

Ottawa Conference:  Dr. Ying Zhang MD PhD
Challenges of Post-Treatment of Lyme Disease
Syndrome (PTLDS); Will Persister Drugs Help Cure

Excellent presentation by Dr. Zhang on the importance of specific drug combinations to effectively kill all forms of Lyme (borrelia).

For more information on Lyme (borrelia) research and treatment:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

https://madisonarealymesupportgroup.com/2015/07/07/promising-new-research-for-persisting-lyme/

https://madisonarealymesupportgroup.com/2016/05/09/leprosy-drug-for-lyme/

https://madisonarealymesupportgroup.com/2016/10/09/mycobacterium-drugs-for-ld/

https://madisonarealymesupportgroup.com/2016/11/14/10-million-for-lyme-research/

***If you are seeing a doctor that is not a part of ILADS (International Lyme and Associated Diseases Society) I highly recommend you get this crucial information into their hands and encourage them to become members, where they will learn the most cutting edge research and treatments.  Your very life depends upon it.


Microbiologist Tom Grier

  Approx. 1.5 hours

Presented by:  Minnesota Lyme Association   http://mnlyme.org

Grier dispels Lyme/MSIDS myths

Grier, infected himself, has done cutting edge work and we need to listen to it. He shows autopsy results – demonstrating Borrelia Burgdorferi (Bb) in numerous tissues, including the brain (glial cells, neurons, endothelial cells), kidneys, placenta, and much more.

More on Grier:

https://madisonarealymesupportgroup.com/2016/08/09/dr-paul-duray-research-fellowship-foundation-some-great-research-being-done-on-lyme-disease/

Lyme on the Brain, part 1:  https://madisonarealymesupportgroup.com/2010/08/09/tom-grier-lyme-lecture-outline/

Lyme on the Brain, part 2:  https://madisonarealymesupportgroup.com/2010/08/18/lyme-on-the-brain-part-2-by-tom-grier/

Lyme on the Brain, part 3:  https://madisonarealymesupportgroup.com/2010/08/29/lyme-on-the-brain-by-tom-grier-part-3-b-lecture-notes/

Lyme on the Brain, part 4:  https://madisonarealymesupportgroup.com/2010/08/30/lyme-on-the-brain-by-tom-grier-part-4-lecture-notes/

LDN

  Published on Dec 20, 2012 Approx. 5 min.

Low Dose Naltrexone (LDN) is widely used for autoimmune disorders such as multiple sclerosis (MS), Crohn’s disease, fibromyalgia, Hashimoto’s thyroiditis, and other inflammatory and chronic disorders. LDNscience produced this video explaining how it works. LDNscience.org, launched in 2009, is a public information project of the MedInsight® Research Institute.

http://www.lowdosenaltrexone.org

You may remember the use of Naltrexone in the treatment of those with alcohol and opioid addictions; however, those dosages are much higher (50-300mg) than for Low Dose Naltrexone (LDN) (1.5-4.5mg). LDN works by blocking opioid receptors for 3-4 hours, telling your body to increase endorphins that relieve pain and also activate the immune system by directing activity of stem cells, macrophages, killer cells, T and B cells and other immune cells. It also modulates an overactive immune system so there is less inflammation and release of neurotoxins.

Interesting historical note

http://www.westonaprice.org/health-topics/moods-and-the-immune-system/  Wise Traditions in Food, Farming and the Healing Arts, the quarterly journal of the Weston A. Price Foundation, Winter 2008.  Tom Cowan, MD.

Naltrexone at 50 mg prohibits heroin addicts from getting high. Those working with addicts and using Naltrexone uncovered the fact that addicts have low endorphins – which is why addicts reach for things that increase endorphin levels, such as heroin.  Heroin works temporarily but it also causes horrific side effects and it ends up lowering endorphin production, which of course causes the addict to keep reaching for a fix, but it takes more and more to achieve the same results.

And, unfortunately, heroin overdoses are on the rise, killing more people than HIV, melanoma, or firearms, and in 2015 killed at least 13,150, according to the CDC: http://abcnews.go.com/Health/heroin-overdoses-killed-people-us-hiv-melanoma-firearms/story?id=44087454

So what does having low endorphins and addictions have to do with MSIDS (multi systemic infectious disease syndrome – or – Lyme with friends)?

Over 90% of immune cell receptors are endorphin receptors, so when we have low endorphin levels, our immune systems are hugely compromised and we feel….well, crappy. Feeling crappy is your body’s way of telling you that something isn’t right.  MSIDS patients can’t sleep at night but we are exhausted all day long.  We have temperature dysregulation and alternate from sweating to shivering.  We suffer with pain that is unbelievable and have cognitive issues such as memory loss and word search, and neurological issues such as tingling, burning, and twitching.  (Oh, isn’t it fun when your body acts on its own volition!)  

When we are infected with a long train of pathogens that are experts at subverting our immune response, we suffer with a veritable laundry list of symptoms and often need to take various supplements, including neurotransmitters, to help our hijacked immune systems.

According to Cowan, there are 4 ways to increase your endorphins.

1)  High intensity exercise – the proverbial “runner’s high,” which frankly isn’t possible when you have MSIDS.
2) Acupuncture
3) Chocolate – the constituent I-Phenylalanine keeps endorphins from breaking down. But it doesn’t last – leading to wanting more chocolate, so this isn’t a great one for MSIDS patients either unless you like gaining weight.
4) LDN – while history found that 50mg blocks endorphin receptors all day making addicts feel lousy, taking only 2-4.5mg right before bed only blocks receptors about an hour. The block wears off which tells the body to make more. LDN is a telegram sent to your body to create more endorphins.

A beautiful connection: The Gut and the Brain (something we can do something about)

Rudolf Steiner once said, “The brain is just smooched up guts.” The brain and the gut both have the same receptors – including serotonin.  Dr. Natasha Campbell-McBride has successfully created the Gut and Psychology Syndrome (GAPS) diet. http://www.doctor-natasha.com.  Gluteo-morphines (gluten in grains) and caseo-morphines (casein in dairy) alter our immune function and our neurological function by creating imperfect chemicals which ultimately cause immune dysfunction.

What this means is that we can tweak our diets and avoid gluten and casein, talk over LDN with our medical practitioner, and help our guts, our brains, and our immune systems all in one fell swoop.

Cowan states that creating natural endorphins and healing the leaky gut which is causing gut and neurological issues are two key issues.  

LDN helps many disease processes.

http://articles.mercola.com/sites/articles/archive/2011/09/19/one-of-the-rare-drugs-that-actually-helps-your-body-to-heal-itself.aspx  For cancer patients, LDN targets the opioid growth factor receptor pathway – which means it regulates the growth of cancer cells. It also interacts with your endorphins, which means pain relief.

Dr. Bernard Bihari has treated more than 450 cancer patients with LDN and has noted at least a 75% reduction in tumor size, and nearly 60% of his patients demonstrated disease stability. He also found people with autoimmune diseases such as Lupus often showed quick stabilization. When his HIV/AIDS patients took LDN were typically spared deterioration of helper T cells (CD4+).

http://www.westonaprice.org/health-topics/moods-and-the-immune-system/   Bihari also treated 44 MS patients. Forty two went into remission for 15 and more years. When they discontinued LDN their symptoms returned within a month.

Dr. Burton Berkson states:  “It is difficult for many to believe that one drug can accomplish so many tasks. But LDN does not treat symptoms as most drugs do. It actually works way ‘upstream’ to modulate the basic mechanisms that result in the disease state.”

  Published on Jun 22, 2015   Approx. 1 hour

Hear from several practitioners on how they use LDN with their patients and witness 2 remarkable stories on how LDN has changed the lives of a 8 year old Jacob Valazquez in Miami and Sarah Morton in the UK who was suffering from Fibromyalgia.

LDN helps MS. An Excerpt from “Low Dose Naltrexone Therapy in Multiple Sclerosis,” in Med Hypotheses states: “The use of low doses of Naltrexone for the treatment of multiple sclerosis (MS) enjoys a worldwide following amongst MS patients. There is overwhelming anecdotal evidence, that in low doses naltrexone not only prevents relapses in MS but also reduces the progression of the disease. It is proposed that naltrexone acts by reducing apoptosis of oligodendrocytes. It does this by reducing inducible nitric oxide enthuse activity…. It is crucial that the medical community respond the patient needs and investigate tis drug in clinical trial.”

LDN helps PTSD.  Post Traumatic Stress Disorder significantly improved with LDN. An Excerpt from “Low Dose Naltrexone in the Treatment of Dissociative Symptoms”:

“The low dose treatment with Naltrexone proved to be effective whereby 11 out of 15 patients reported immediate positive effects and 7 described a lasting helpful effect. The majority of patients who felt positive effects reported a clearer perception of both their surroundings and their inner life.  Assessment of reality and dealing with it improved as did the perception of their own body and affects as well as self-regulation. The treatment was very low in side effects….Treatment with low dose naltrexone may be a helpful element in the treatment of patients with complex post traumatic stress disorder.”

LDN helps Pain. http://link.springer.com/article/10.1007/s11481-013-9451-y/fulltext.html

Abstract
Complex Regional Pain Syndrome (CRPS) is a neuropathic pain syndrome, which involves glial activation and central sensitization in the central nervous system. Here, we describe positive outcomes of two CRPS patients, after they were treated with low-dose naltrexone (a glial attenuator), in combination with other CRPS therapies. Prominent CRPS symptoms remitted in these two patients, including dystonic spasms and fixed dystonia (respectively), following treatment with low-dose naltrexone (LDN). LDN, which is known to antagonize the Toll-like Receptor 4 pathway and attenuate activated microglia, was utilized in these patients after conventional CRPS pharmacotherapy failed to suppress their recalcitrant CRPS symptoms.

LDN helps Crohn’s Disease.
https://www.ncbi.nlm.nih.gov/pubmed/17222320  Dr. Jill Smith found that two-thirds of patients in her pilot study went into remission and 89% responded to treatment to some degree.

LDN reduced pro-inflammatory cytokines in fibromyalgia:  https://madisonarealymesupportgroup.com/2017/06/12/ldn-reduced-pro-inflammatory-cytokines-in-fm-after-eight-weeks/

LDN shows promise in helping:

Hepatitis C
Lupus
Ulcerative colitis
Autism
Chronic Fatigue
Irritable bowel
Diabetic neuropathies
Dermatomyositis
MS
Crohn’s
Alzheimer’s
Hasimoto’s
Parkinson’s
Tick borne Illness
Common Colds
Emphysema
HIV/AIDS
Lyme Disease (Late Stage)
ALS
PTSD
Transverse Myelitis
Behcet’s
Celiac
Dystonia
Endometriosis
Hashimoto’s
Psoriasis
RA
Sjogren’s
Cancers
and more

So why haven’t you or your doctor heard of LDN? Although it has been FDA approved for over two decades, the lower doses used to help the immune system have not been submitted for FDA approval as big pharma wants nothing to do with a drug that costs between $15-$40/month.

“LDN substantially reduces health care costs and improves treatment of a wide array of diseases. Unfortunately, because naltrexone has been without patent protection for many years, no pharmaceutical company will bear the expense of the large clinical trials necessary for FDA approval of LDN’s new special uses. It is now up to public institutions to seize the opportunity that LDN offers.” David Gluck, MD

There are virtually no side-effects; however, occasionally and only during the first week of use, some may have trouble sleeping. Some do report vivid dreams. It’s important to start with the lowest dose (1.5-2mg) for a month before going higher. It’s also important NOT to use the time-release form as you want a spike in the blood stream for therapeutic effect.

The therapeutic dosage range for LDN is from 1.5mg to 4.5mg every night. Dosages below this range are likely to have no effect at all, and dosages above this range are likely to block endorphins for too long a period of time and interfere with its effectiveness.

*Those taking narcotics should NOT take LDN until it is completely out of the body.

*Those taking thyroid hormone for Hashimoto’s thyroiditis with hypothyroidism need to start at the lowest dose as there may be a decrease in their disorder which may necessitate a rapid reduction in thyroid medication in order to avoid hyperthyroidism.

*Folks with organ transplants and taking permanent immunosuppressive drugs should avoid LDN as it will counter the effects of those meds.

*Do not use LDN that has employed the filler calcium carbonate as it has been found to interfere with absorption of the capsule. It is recommended that the fillers be Avicel, lactose (if lactose intolerance is not a problem), or sucrose fillers as useful fast-release fillers.

Please use a reputable compounding pharmacy. The LDN Homepage  http://www.lowdosenaltrexone.org  recommends these:

Irmat Pharmacy, New York, NY
(212) 685-0502
(212) 532-6596
Belmar Pharmacy, Lakewood, CO
(800) 525-9473
(866) 415-2923
The Compounder Pharmacy, Aurora, IL
(630) 859-0333
(800) 679-4667
(630) 859-0114
The Pharmacy Shop and
Compounding Center, Canandaigua, NY
(585) 396-9970
(800) 396-9970
(585) 396-7264
McGuff Compounding Pharmacy,
Santa Ana, CA
(714) 438-0536
(877) 444-1133
(877) 444-1155
Skip’s Pharmacy, Boca Raton, FL
(561) 218-0111
(800) 553-7429
(561) 218-8873
The Medicine Store Pharmacy, Concord, NH
(603) 225-2747
(877) 926-7637
(603) 224-3661
Smith’s Pharmacy, Toronto, Canada
(416) 488-2600
(800) 361-6624
(416) 484-8855
Dickson Chemist, Glasgow, Scotland
+44-141-647-8032
+44-800-027-0673
+44-141-647-8032

**I have successfully used and highly recommend Women’s International Pharmacy in Madison, WI.
Phone: 800.279.5708
Fax: 800.279.8011
They also provide a 24-Hour Automated Phone Service with which you may leave your orders.
https://www.womensinternational.com/connections/index.html  Excellent articles put out by WIP on hormone-related conditions and therapies. You can also sign up for their monthly e-letter. The pharmacists will be happy to answer any questions you or your practitioner may have.

**The only filler in WIP’s LDN is olive oil. They also sell a compounded form of T3 or (L-triiodothyronine or LT3) much cheaper than the Brand Name Cytomel (which has undesirable fillers such as calcium sulfate, gelatin, starch, stearic acid, sucrose, and talc.  Make sure you ask for the compounded form. More info: https://www.restartmed.com/cytomel-side-effects/

The following videos were created by the LDN Research Trust

https://vimeo.com/182274779
Eva shares her experience of LDN for Lyme Disease, Fibromyalgia, CFS/ME, and Pain
https://vimeo.com/189672998?ref=em-v-share
Dr. Kathleen MacIsaac, LDN prescriber shares her experience.

https://vimeo.com/187793166
Dr. Craig Hauser, LDN prescriber shares his experience.  

For a list of Clinical Trials, Research, and Surveys: http://ldners.org/evidence/