Archive for the ‘research’ Category

Chronic Lyme Disease – A Case Definition at Last

fulltext_chronicdiseases-v4-id1025  Published: May 03, 2017 Stricker RB and Fesler MC.   Chronic Lyme Disease: A Working Case Definition. Chronic Dis Int. 2017; 4(1): 1025.

Abstract

Although Lyme disease is the most common tickborne illness in the USA and Eurasia, the pathophysiology and clinical course of chronic Lyme disease (CLD) have not been formally defined. The purpose of this paper is to present a working case definition of CLD based on analysis of more than 700 peerreviewed publications. According to this definition, CLD is a multisystem illness with diverse musculoskeletal, neuropsychiatric and/or cardiovascular manifestations that result from ongoing infection with pathogenic members of the Borrelia spirochete complex often associated with other tickborne disease (TBD) pathogens. To qualify for the diagnosis of CLD, patients must have Lyme compatible symptoms and signs that are either consistently or variably present for six or more months. Two subcategories of CLD include untreated chronic Lyme disease (CLD-U) and chronic Lyme disease following a limited course of antibiotic treatment (CLD-T). The symptom patterns and optimal therapy of CLD require further study.  ______________________________________________________________________

While a relatively short course of appropriately directed antimicrobials may be adequate for individuals who are treated early in the Lyme disease process, treatment is frequently not curative, raising the possibility of TBD pathogen survival [88-96]. Persistent TBD infection in animals and humans involves potential roles for multiple mechanisms: (1) Immune evasion via physical seclusion of pathogens within immunologically protected tissue sites such as the central nervous system, joints, eyes, connective tissue and genital tract [88-96]. (2) Alterations in Outer surface protein (Osp) profiles of pathogens through antigenic variation [95-99] and alteration in pathogen morphology (including cell-wall deficient forms, spherocytes, round bodies and biofilm aggregates) [100-107]. (3) Immune modulation via complement interference, neutrophil and dendritic cell dysfunction and cytokine/chemokine alterations [108-115]. (4) Generation of antibiotic-tolerant “persister cells” in some pathogen populations [116-118].

Clinical Manifestations of CLD Lyme disease is a multisystem illness that is often referred to as the “new great imitator” due to the diversity of its clinical manifestations that are reminiscent of syphilis [119-123]. The wide spectrum of clinical features can range from an EM rash to severe arthritis, carditis or neuropsychiatric symptoms [4,5]. Another clinical feature often associated with this condition is the Jarisch- Herxheimer reaction whereby symptoms increase after exposure to antimicrobials [124-131]. This is a phenomenon associated with the treatment of spirochetal diseases such as syphilis, louseborne relapsing fever, leptospirosis and Lyme disease [124-131]. Recent studies suggest that the Jarisch-Herxheimer reaction is triggered by rapid uptake of damaged spirochetes by neutrophils and mononuclear cells with release of lipoproteins and pyrogens that increase inflammatory cytokines [131]. To date, the complete mechanism of this phenomenon remains undefined. Since clinical features of Lyme disease may change following exposure to antimicrobials, we have proposed two categories for this working case definition of CLD, as outlined above.

**For CLD-U, the natural course without antimicrobial intervention has been described by Steere et al. in the USA [19,132]. Prior to recognition of the importance of antimicrobial therapy, untreated patients with EM rash displayed the following clinical characteristics over six years of follow-up: 62% developed intermittent or persistent arthritis; 18% developed arthralgias; 11% developed neurologic abnormalities; 4% developed cardiac complications; 33% developed fatigue; and 33% developed other symptoms and signs including headache, stiff neck, morning stiffness, myalgias and abdominal pain [132]. Further characteristics of CLD-U patients have been described by Wormser et al. in the 2006 IDSA Lyme guidelines [4]. Based on clinical diagnosis with serological confirmation using CDC surveillance criteria, later stages of Lyme disease may feature prominent multisystem symptoms and signs as described above [1,4,5].

**In contrast to CLD-U, CLD-T is a term used to describe individuals who have been treated for TBDs with a limited course of antibiotics (generally < four weeks) and within six months develop persistent or recurrent and functionally significant fatigue, musculoskeletal pain, cardiovascular disease and/or neuropsychiatric dysfunction that persists for six months or more [133,134]. CLD-T acknowledges the extensive published evidence for persistent TBD infection despite a limited course of antibiotic therapy. In contrast, the research case definition for PTLDS proposed by IDSA includes the following statement: “There is no convincing biologic evidence for the existence of symptomatic chronic B. burgdorferi infection among patients after receipt of recommended treatment regimens for Lyme disease” [4]. Based on animal models and human studies, however, we propose that treatment with limited antibiotic regimens may not consistently clear the infection, and we have provided evidence to support potential mechanisms by which this persistent infection occurs (see above). Thus Lyme patients who remain symptomatic following a limited course of antibiotic therapy likely have an ongoing, active TBD infection similar to CLD-U patients. We characterize this group as having CLD-T. Other conditions that can mimic the clinical presentation of CLD must be ruled out. However, the diagnosis of “idiopathic” conditions such as multiple sclerosis, motor neuron disease, fibromyalgia or chronic fatigue syndrome is insufficient to rule out the presence of CLD. We analyzed more than 700 peer-reviewed publications featuring symptoms and signs associated with both forms of CLD from a MEDLINE search (Appendix A). From this list, we chose 16 studies that describe symptoms and signs in patients with CLD-U and 13 studies that describe symptoms and signs in patients with CLD-T (Appendix B). In these 29 studies, persistent Bb infection was documented by culture, PCR and/or microscopy, while other studies without this stringent documentation were excluded. The symptom profiles in patients with persistent Bb infection are indicative of the protean manifestations of CLD. In our representative sample, patients with CLD-U appeared to have relatively more musculoskeletal and cardiovascular symptoms and signs, while patients with CLD-T appeared to have relatively more neuropsychiatric symptoms and signs (Tables 1 and 2). The broader pathology in untreated patients versus more restricted pathology following limited treatment is reminiscent of the immunopathology patterns in untreated versus initially-treated syphilis [134]. To date, however, the number of studies with stringent documentation of persistent Bb infection is too small to draw definitive conclusions about patterns of symptoms and signs in CLD patients. Further comparison of symptom profiles associated with the two forms of CLD is warranted.

Co-Infections

In both categories of persistent Bb infection, the presence of of other TBD pathogens may complicate the diagnosis and treatment of Lyme disease. Ixodes ticks are known to carry more than 237 types of bacteria and at least 26 viruses [136,137]. Some of these organisms, frequently referred to as co-infections, may alter the manifestations of Lyme disease and make it more difficult to eradicate the spirochete.  The interplay of other infectious agents with Bb may complicate the clinical presentation of Lyme disease and prolong the duration of infection, as noted in animal models [145-147].

Functional Impact of CLD

A community-based study of CLD patients found that the Quality of Life (QoL) of these patients was the same or worse compared to that of individuals with depression, diabetes, heart disease, osteoarthritis and rheumatoid arthritis [148]. Using a CDC metric of health-related QoL, a second survey of more than 5,000 respondents with CLD supported this analysis, revealing that 71.6% rated their health as fair or poor. The functionality scores of CLD patients were worse than those of other chronic diseases including congestive heart failure, fibromyalgia, post-stroke syndrome, post-myocardial infarction, diabetes and multiple sclerosis [149]. Further support for the adverse health impact of CLD was recently provided by Adrion et al [150]. Based on retrospective data from medical claims over five years in the USA, 52,795 individuals treated for Lyme disease were compared to 263,975 matched controls with no evidence of TBDs. The study found that as many as 63% of treated Lyme disease patients had persistent symptoms of CLD, and that Lyme disease was associated with $2,968 higher total health care costs (95% CI: $2,807- $3,128, p<0.001) and 87% more outpatient doctor visits (95% CI: 86%-89%, p<0.001) over a 12 month period compared to TBD-negative controls [150,151]. A more recent study from the Netherlands found that the annual cost of treatment for CLD was €5700 (about $6300) per patient or a total of €19.3 million ($21 million) per year in that country [152].

We recognize that there may be other contributing and at times independent causes for persistent symptoms in CLD patients. In essence, not all patients who remain symptomatic after being treated for Lyme disease suffer from an active, ongoing infection. Proposed mechanisms of persistent symptoms include immune dysregulation of various types, tissue injury, infection-induced secondary conditions and unrelated diseases [153,154]. Based on the clinical evidence, however, we assert that a potentially large number of individuals with CLD are adversely impacted by persistent TBD infection associated with significant functional limitations and financial burdens [148- 151]. We hope that technological advances in the characterization of ongoing TBD infection will improve our ability to deal with this condition.

Clinical Judgment

Until technological advances provide reliably sensitive and specific diagnostics, some patients will continue to have a diagnosis that remains unclear. Under these circumstances, the value of clinical judgment will remain an important component in treating these individuals. According to the American Medical Association Code of Medical Ethics, the primary responsibilities of clinical medicine are to alleviate patient suffering and prevent disease [155]. As previously described by Johnson et al [149] and Cameron et al [156,157]. patients with CLD are often quite ill, and physicians are charged with finding balanced and effective management strategies for such patients. Uncertainty about a CLD diagnosis may confound clinical decision making, but clinical uncertainty should not exclude that diagnosis. This process involves both inclusionary and exclusionary criteria. Patient care is dynamic, and clinical judgment requires vigilance in assessing clinical outcomes. As described by Kienle and Kiene, “Clinical judgment is a central element of the medical profession, essential for the performance of the doctor” [158]. Thus given the current absence of a “gold standard” test for Lyme disease, it is essential that healthcare providers should consider this condition if symptoms and/or clinical signs occur in patients with a history consistent with CLD, as summarized in the guidelines of the International Lyme and Associated Diseases Society (ILADS) [5].

**Please see link for Table 3 which outlines the proposed diagnostic criteria for CLD.

Conclusions

This is the first study that provides a working case definition of chronic Lyme disease (CLD) and its subcategories. We propose that CLD is the result of persistent, active infection by pathogenic members of the Borrelia spirochete complex often associated with other TBD pathogens. Infection with these organisms produces a wide array of symptoms and signs that may be expressed in a given individual during the course of the chronic illness [5,122]. Whether due to delayed diagnosis (CLD-U) or as a result of persistence after a limited course of antibiotic treatment (CLD-T), these symptoms and signs may fluctuate but are required to have cumulatively persisted for at least six months.

At this time, clinically available diagnostic testing does not consistently allow for identification of the pathogen(s) affecting individuals with CLD. As such, a hallmark feature of our working case definition is reliance on clinical judgment. This process includes the use of supportive diagnostics, but it does not require laboratory confirmation in light of present technological limitations of TBD testing. We recognize that as diagnostic testing evolves, the ability to define this entity should improve.

We also recognize that other diagnoses may be responsible for symptoms and signs that are similar to CLD and need to be considered in CLD patients. We hope that this outline will provide the clinician with a framework to weigh management options for these often significantly debilitated patients. We also hope to provide additional impetus for public policy to recognize the growing risk of the Lyme disease epidemic. Lastly, we encourage researchers to use the proposed definition of CLD to improve laboratory methodology for identifying patients with this condition, and to facilitate the development of new treatment options for CLD patients.

** See Link for references.

Body of Research Showing Borrelia Persists

55_chronic316x316 Lymestats.org

http://lymediseasechallenge.org/research-persistent-infection/

Is There Really Chronic Lyme Disease?

There is an abundant, growing body of research evidencing persistent infection after standard courses of antibiotic treatment for Lyme Disease, often leading to chronic, debilitating illness. Lyme patients desperately need research to develop more effective treatments.

36_no316x316

Health Care Costs, Utilization and Patterns of Care following Lyme Disease http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0116767

Severity of Chronic Lyme Disease compared to other chronic conditions:  A Quality of Life Survey  PeerJ Quality of Life Survey

An Optimized SYBR Green I/PI Assay for Rapid Viability Assessment and Antibiotic Susceptibility Testing for Borrelia burgdorferi  http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0111809

Drug Combinations against Borrelia burgdorferi Persisters In Vitro: Eradication Achieved by Using Daptomycin, Cefoperazone and Doxycycline   http://journals.plos.org/plosone/article?id=10.1371%2Fjournal.pone.0117207

Identification of novel activity against Borrelia burgdorferi persisters using an FDA approved drug library http://www.nature.com/emi/journal/v3/n7/full/emi201453a.html

Counterpoint: Long-Term Antibiotic Therapy Improves Persistent Symptoms Associated with Lyme Disease  https://academic.oup.com/cid/article/45/2/149/420106/Counterpoint-Long-Term-Antibiotic-Therapy-Improves

Resurgence of Persisting Non-Cultivable Borrelia burgdorferi following Antibiotic Treatment in Mice  http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0086907

Persistence of Borrelia burgdorferi in Rhesus Macaques following Antibiotic Treatment of Disseminated Infection  http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0029914

13_embers1316x316

Characterization of Biofilm Formation by Borrelia burgdorferi In Vitro  http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0048277

19_biofilms316x316

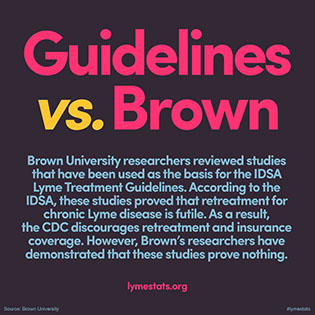
Researchers at Brown University poke holes in the Klempner study, which the IDSA uses to justify denying long-term treatment to Lyme patients  http://www.lymedisease.org/retreatment-study-flawed/

89_brown316x316

Identification of new compounds with high activity against stationary phase Borrelia burgdorferi from the NCI compound collection  http://www.nature.com/emi/journal/v4/n6/full/emi201531a.html

Eradication of Biofilm-Like Microcolony – Structures of Borrelia burgdorferi by Daunomycin and Daptomycin but not Mitomycin C in Combination with Doxycycline and Cefuroxime  http://journal.frontiersin.org/article/10.3389/fmicb.2016.00062/full

List of 700 articles citing chronic infection associated with tick-borne disease compiled by Dr. Robert Bransfield  http://www.ilads.org/ilads_news/2017/list-of-700-articles-citing-chronic-infection-associated-with-tick-borne-disease-compiled-by-dr-robert-bransfield/

102_700proof316x316

A Drug Combination Screen Identifies Drugs Active against Amoxicillin-induced Round Bodies of Borrelia burgdorferi Persisters from an FDA Drug Library  http://journal.frontiersin.org/article/10.3389/fmicb.2016.00743/full

44_10years316x316    97_1in5316x316

Lastly, microbiologist Holly Ahern points out that stating that only 10-20% go on to develop symptoms is inaccurate:  https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/

In short, the 10-20% is a group that was diagnosed and treated early.  There’s another larger group, approximately 30-40%, that was diagnosed and treated late that develops chronic symptoms.  When you add the two groups:

60% of all patients could go onto develop life-long symptoms


Powassan – Another Reason to Avoid Ticks

Powassan Virus Is the Scary New Reason to Avoid Ticks
Amanda MacMillan
May 04, 2017

For more, visit http://time.com/time-health/.

http://time.com/4767290/powassan-virus-ticks/ (Video here)

Lyme disease isn’t the only tick-borne illness that can come from a walk in the woods. Health experts are warning that another pathogen, Powassan virus, can cause dangerous inflammation in the brain and may be transmitted to humans much faster than Lyme. While it is rare, a recent study of ticks in Maine, along with a few widely reported cases of human infection, suggest that it may be becoming more common. /react-text

What is Powassan virus?

The virus causes encephalitis, or swelling of the brain, and it kills about 10% of people who become sick, https://www.cdc.gov/powassan/symptoms.html.
About half of people are left with permanent neurological problems.

Powassan virus was first identified in 1958 and was first recognized in deer ticks, the type that bite humans and also carry Lyme disease, in the mid-1990s. About 75 cases have been reported to the CDC over the last 10 years, and most have been in the Northeast and the Great Lakes region. https://www.cdc.gov/powassan/statistics.html

One of those cases, in 2013, was a woman in Maine who died a few weeks after being bitten by a tick and contracting Powassan virus. Her diagnosis, along with two subsequent cases in the same county, prompted scientists at the Maine Medical Center Research Institute to test ticks at various sites across the state.

The researchers released their preliminary findings in April and told Bangor Daily News that, “We were kind of surprised that we found as much as we did.” Out of 203 different pools of adult ticks—meaning all of the ticks collected from a given area—15 tested positive for Powassan. The researchers also found that populations of deer ticks were increasing in several areas in the state. http://vitalsigns.bangordailynews.com/2017/04/26/home/tick-researchers-found-powassan-virus-in-these-maine-towns/

Another recent CDC case report detailed the first-ever diagnosis of a human Powassan infection in Connecticut: a 5-month-old baby who was admitted to the hospital in November 2016 for vomiting, fever and seizures. The baby’s parents reported that he had been bitten by a tick about two weeks earlier and estimated that the tick bad been attached for less than three hours. The baby spent a week in the hospital, and it took several months for him to fully recover.  https://www.cdc.gov/mmwr/volumes/66/wr/mm6615a3.htm?s_cid=mm6615a3_w#contribAff

Should you be worried about Powassan virus?

This news, coupled with experts’ prediction that 2017 will be an especially bad year for ticks in the Northeast, is cause for concern. So is the fact that Powassan is deadlier than Lyme disease—and appears to be transmitted much faster. In animal studies, Powassan virus could be passed from tick to host after only about 15 minutes of attachment. For Lyme disease, it takes 24 hours. http://www.npr.org/sections/goatsandsoda/2017/03/06/518219485/forbidding-forecast-for-lyme-disease-in-the-northeast

***This statement about Lyme transmission time is not accurate.  Please see this article:  https://madisonarealymesupportgroup.com/2017/04/14/transmission-time-for-lymemsids-infection/***

But Rafal Tokarz, associate research scientist at the Columbia University Mailman School of Public Health, stresses that Powassan is still very rare, and says it’s too early to know for sure if Powassan is truly becoming more prevalent.

Tokarz’s own research, mostly on ticks in regions around New York City, has shown that only about 1% to 2% of ticks are infected with bacteria that cause the Powassan virus. That finding is consistent with most studies that have been done in other parts of the country, he says.  https://www.mailman.columbia.edu/public-health-now/news/scientists-uncover-details-rise-tick-borne-disease-long-island

MORE: A New Cause of Lyme Disease Has Been Discovered
http://time.com/4212500/a-new-cause-of-lyme-disease-has-been-discovered/?iid=sr-link6

The recent report from Maine suggests higher numbers, but Tokarz points out that the researches tested entire pools at once. So while about 7% of tick pools tested positive for the virus, “there is no way to know how many ticks in each pool were infected,” he says. “It could be one out of 100, or it could be all 100.”

Nicholas Bennett, medical director of infectious diseases & immunology at Connecticut Children’s Medical Center, says that an increase in reported Powassan cases may also be due to more doctors being aware of the virus and actually testing for it. Like all tick-borne diseases, he says, the CDC’s numbers are probably much lower than the actual number of infections that occur each year, because many go unsolved or misdiagnosed. In November, Bennett was instrumental in getting that 5-month-old baby tested and diagnosed at Connecticut Children’s. “I may have been the first doctor to pick up on a case of Powassan in this state, but I’m sure it wasn’t the first to see a case in this state,” he says. “This isn’t a virus that’s on our standard list of tests, or that we look for automatically.”

And while some Powassan infections become very serious, many other people only develop a mild illness or have no symptoms at all.

More research is needed to determine how worrying Powassan is. But, Bennett says, research does suggest that tick populations and tick-borne diseases in general are on the rise.

What to do if a tick bites you

If you are bitten by a tick, rushing to the doctor right away won’t do you much good, Bennett says. The tests for these viruses aren’t pleasant—they involve blood and spinal-fluid drawings—and may not show signs of infection for several days or weeks.

MORE: Why Bed Bugs Are Becoming So Much Harder to Kill
http://time.com/4733708/bed-bugs-insecticide-resistance/?iid=sr-link1

“It’s perfectly reasonable to wait and see if you develop symptoms,” he says. There’s not much doctors can do for people who aren’t seriously ill, anyway. Doctors do not have a cure for Powassan and can only monitor the symptoms and provide care like respiratory support and IV fluids.

“The good news is that if you or your child are feeling a little under the weather or have a low-grade fever, there’s a million other probably causes other than Powassan,” says Bennett. “But if there are neurological symptoms—weakness, dizziness, seizures—then it’s important to get to the doctor.”

How to avoid ticks

The CDC says that people should protect themselves from Powassan virus the same way they do other tick-borne illnesses: by wearing insect repellant when spending time in areas where ticks are present, inspecting clothing and skin afterward and bathing or showering upon returning home. If pets have been outdoors, make sure they’re inspected regularly as well.  https://www.cdc.gov/ticks/avoid/on_people.html

“Take precautions and be on the lookout for ticks whenever possible,” Tokarz says. “Whether it’s Powassan or something more common like Lyme or another tick-borne disease, you really don’t want to get any of them.”


Sick Lyme Patients Causing Scientists to Feel Threatened

This absolutely made my day.  Power to the sickies!

https://www.buzzfeed.com/stephaniemlee/lyme-disease-patient-registry?utm_term=.wbLADWmea#.ylXj5dzp4  Buzzfeed News, by Stephanie M. Lee

In late 2015, Lorraine Johnson was frustrated with what she felt was the slow progress of research on Lyme disease, the tick-borne rash that strikes thousands of Americans every year, in apparently increasing numbers. So as the head of LymeDisease.org, a leading advocacy group, she launched her own study: MyLymeData.org.

The site has since surveyed 7,000 people, Johnson reported this month at a conference in the San Francisco Bay Area. The site calls itself “the first national large-scale study of chronic Lyme disease.”

It’s one of the newest large online registries built by patients with rare or understudied conditions. Feeling ignored by academics and Big Pharma, they turn to the internet, where they can pool the collective wisdom of people who might otherwise never enroll in a clinical trial.

We don’t feel ignored, WE ARE IGNORED!  https://madisonarealymesupportgroup.com/2017/04/22/mylymedata-presentation/  Only 3 small clinical trials on the treatment of chronic Lyme disease were funded by the NIH – the most recent was 15 years ago.  Hello?

Scientists are increasingly relying on apps and websites like this one to conduct research. But as this approach becomes more popular, researchers have questions about its inherent lack of rigor and standardization.

Online surveys typically don’t require proof of a diagnosis, and self-diagnosis is often tricky. For example, the varied symptoms of Lyme disease — arthritis, fever, headaches, shooting pain, and memory problems, among others — crop up in many other conditions, making it difficult to identify conclusively, even for doctors. It’s also tough to keep people engaged in a study when they’re scattered across the country.

“The ability to get big data on large numbers of people fairly easily, that’s a strength,” said Dr. John Aucott, director of the Lyme Disease Clinical Research Center at Johns Hopkins University, who is not involved with MyLymeData. “The advantage is you’re getting patient symptoms — but the disadvantage is you don’t truly know they’re due to Lyme disease.”

Despite these potential issues, self-reported patient data could soon help pharma companies bring drugs to market faster. Under the 21st Century Cures Act, passed in December, companies applying for certain kinds of FDA drug approvals can submit data about how patients are reacting to drugs in the real world, rather than data collected from rigorously controlled clinical trials. Critics say this provision weakens regulatory oversight.

“In terms of generating really good evidence that you’re going to make people better off, [real-world data] is a good starting point, but it’s not the finish line,” said Vinay Prasad, a hematologist-oncologist at Oregon Health and Sciences University.

Around 300,000 people in the United States, almost entirely in the Northeast and upper Midwest, are diagnosed annually with Lyme, according to the Centers for Disease Control. The agency has clear criteria for diagnosing Lyme in its early days, including a tick bite, a bull’s-eye rash, and a lab blood test. A few weeks of antibiotics cures most patients. But some experience symptoms like headaches and joint and nerve pain for months, even years, after treatment.

The federal government has funded only a handful of Lyme disease studies, and one of the larger ones, published in 2001, enrolled just 130 people. All of the studies focused on patients who had symptoms even after taking antibiotics. Patients often call this advanced stage “chronic Lyme disease,” as does MyLymeData, though most doctors argue that this term has come to mean many things to different people and has no accepted definition. They and the CDC instead use “post-treatment Lyme disease syndrome.”

Johnson says that she created MyLymeData to make up for this dearth of research on patients with lingering symptoms. “The problem with Lyme disease is essentially there is no data,” she told BuzzFeed News.

She doesn’t know of any cures or treatments in the works for Lyme patients who don’t respond to antibiotics — but hopes her database will inspire pharmaceutical companies to develop some.

The people who have signed up for MyLymeData, she said, “were just very anxious to push forward research because research had really kind of left them behind,” she said

At a conference hosted last fall by the Lyme Disease Association and Columbia University, Johnson presented findings from an unpublished survey of more than 4,000 MyLymeData participants. The survey responses showed that people who were diagnosed at an early stage were more likely to report being healthy than those who were diagnosed later, and many claimed that their doctors had failed to accurately spot the disease. Johnson said at the time that the findings showed both the need for physicians to make diagnoses early on, and for “more effective treatments to help those patients who remain ill.”

But experts note that MyLymeData’s database may not accurately reflect Lyme patients, particularly those with persistent symptoms, the hardest stage to diagnose.

For Aucott of Johns Hopkins, making a diagnosis of post-treatment Lyme disease syndrome is a painstaking process. There isn’t one clear biomarker, like a genetic mutation or an X-ray reading, that proves someone has the condition. He and a nurse interview a patient, then review all of their medical records and lab reports, to establish both that they were healthy before getting diagnosed and showed Lyme symptoms after their antibiotic treatment. Aucott also tries to figure out if they might have anemia, thyroid disease, chronic fatigue syndrome, or something else with similar symptoms.

“I’ve seen 500 or 1,000 patients with decades of work,” Aucott told BuzzFeed News. “That’s the level of detail you need to really be convinced you have a uniform population.”

He and other experts told BuzzFeed News that they’re worried that MyLymeData allows, but doesn’t require, people to provide lab readouts and doctors’ notes to prove which stage of disease they’ve had, or even that they ever had the disease. To sign up, participants simply need to check boxes saying they live in the United States and have been diagnosed for Lyme by a health care professional. Then they answer a barrage of questions, such as how many times they’ve been infected, when they were first infected, and which symptoms they’ve had. (To test the service, a Lyme-free BuzzFeed News reporter successfully signed up and filled out responses about her nonexistent condition.)

“I’m not sure this kind of registry would be super helpful other than to tell you a little bit about what patients who have been labeled with ‘chronic Lyme’ complain about or have been treated for it,” said Paul Auwaerter, a professor of medicine and Lyme specialist at Johns Hopkins.

Others question how well the database represents actual patients.

“The problem with Lyme disease is essentially there is no data.”
“If the data are based on volunteered testimony, how do we know that those who choose to volunteer adequately represent those who don’t?” Paul Lantos, an assistant professor of internal medicine and pediatrics at Duke University School of Medicine, said by email. “If recruitment is promoted by advocacy groups, then how do we know those who volunteer represent Lyme disease patients more broadly?”

Johnson admitted that MyLymeData relies on the honor system, but pointed out, “I don’t think 7,000 people would take the time to go through and complete the surveys and do the follow-ups if they didn’t have a diagnosis.”

And, she said, the beauty of the database is that if a researcher wanted to study something about biomarkers, they could easily contact people through MyLymeData and ask for their lab reports and other medical records. She says that she and the academic researchers she’s working with, whose names she declined to share, will always be careful to point out the limitations of their research.

“It is possible to glean accurate insights about diseases from self-reported data,” says Ben Heywood, president and co-founder of PatientsLikeMe, a website where patients go to discuss their conditions. But, he added, “it takes ‘a fair amount of manual curation’ to make the data useful for research institutions that team up with the company, such as the FDA.”  PatientsLikeMe members have reported more than 30,000 treatments and symptoms for various illnesses, which staff then translate into medical terms (such as translating “chemo brain” into the more technical term, “cancer treatment-related cognitive impairment”).

“Doing real-world evidence or patient-generated health data in a rigorous scientific and methodological way, the way we do it, is hard,” Heywood said.

It’s understandable that chronic Lyme patients would want to take matters into their own hands after feeling ignored by mainstream doctors.

“I definitely think that many patients feel alienated from the ‘conventional’ medical community,” Lantos wrote. ‘This project may help us understand where our communication fails patients.”

Online patient registries like MyLymeData are becoming more and more common; by one count, there are 20. The earliest ones were dedicated to patients with rare, lethal diseases like cystic fibrosis and muscular dystrophy, and now there are ones about cardiovascular health and Alzheimer’s disease.

“Registries will likely proliferate under the 21st Century Cures Act,” says Kim McCleary, managing director of FasterCures, a think tank that was a key supporter of the legislation. And as for concerns that their kind of data threatens scientific standards, McCleary counters that it’s not an either-or question.

“I don’t think anyone expects [patient data] is going to replace double-blind placebo-controlled trials,” she said.

Stephanie Lee is a senior technology reporter for BuzzFeed News and is based in San Francisco.
Contact Stephanie M. Lee at stephanie.lee@buzzfeed.com.

Here’s the dealeo:  Start doing meaningful, unbiased research.  Problem solved.

US Soldier Acquires Tickborne Relapsing Fever Caused By B. Turicatae From a Ornithodoros Turicata Tick

https://wwwnc.cdc.gov/eid/article/23/5/16-2069_article

Christensen AM, Pietralczyk E, Lopez JE, et al. Diagnosis and Management of Borrelia turicatae Infection in Febrile Soldier, Texas, USA. Emerging Infectious Diseases. 2017;23(5):883-884. doi:10.3201/eid2305.162069.

Abstract

In August 2015, a soldier returned from field exercises in Texas, USA, with nonspecific febrile illness. Culture and sequencing of spirochetes from peripheral blood diagnosed Borrelia turicatae (a species of borrelia) infection. The patient recovered after receiving doxycycline. No illness occurred in asymptomatic soldiers potentially exposed to the vector tick and prophylactically given treatment.

Tickborne relapsing fever (TBRF) was first reported in the United States >100 years ago but is often difficult to identify, given its rarity and variety of clinical presentations (1,2). We describe a case of culture-confirmed TBRF caused by Borrelia turicatae acquired by an Army soldier during a military training exercise in Texas, USA.

The patient was a 31-year-old white man with no relevant medical history. In August 2015, he sought care at the Eglin Air Force Base Hospital (Valparaiso, Florida, USA) with a 5-day history of fever (102°F), chills, and myalgias. He reported headache and nausea but no vomiting or diarrhea. He denied localized joint pain, redness, or swelling but had discomfort in both popliteal fossae (back of both knees).

The patient had recently returned to Florida after a 30-day Army exercise under austere conditions in western Texas (Technical Appendix[PDF – 376 KB – 3 pages] Figure 1). Potential exposures included sleeping nude in a sleeping bag on the floor of an abandoned barn that had been cleared of infestation with rabbits, rodents, birds, and bats; having eaten boar that had been slaughtered, dressed, and cooked over an open flame; and consuming water procured from a well, bottled sources, and at times through a LifeStraw http://lifestraw.com/. Approximately 1 week before admission, he had noted multiple skin lesions, including scattered, presumed insect bites along his left leg and a small lesion at his urethral meatus (where urine exits). He denied any history of genital lesions and had not seen any biting insects. After 6 days, the lesions spontaneously resolved.

In a Texas emergency department, the initial diagnosis was viral syndrome, and a rapid influenza test result was negative. The fever persisted despite administration of antipyretics. After 2 days, the patient returned to the hospital, where he received only symptomatic treatment. No tests were ordered. After another 2 days, he sought care from his unit physician. Laboratory tests showed marked thrombocytopenia (low platelet count) with 16 × 109 platelets/L (reference range 150–400 × 109 platelets/L). Spirochetes were seen on peripheral blood smear (Technical Appendix[PDF – 376 KB – 3 pages] Figure 2). He was referred for hospital admission. Physical examination findings were unremarkable: no splenomegaly, hepatomegaly, or rash. Blood cultures and serologic testing for rickettsiae, HIV, dengue virus, Treponema pallidum, and plasmodia produced negative results. Erythrocyte sedimentation rate (58 mm/h) and C-reactive protein level (>19 mg/L) were elevated. Electrolytes and transaminase levels were within reference ranges.

Serum samples collected at admission and 3 weeks later (≈5 and 26 days after illness onset, S1 and S2, respectively) were tested in parallel at the Centers for Disease Control and Prevention, National Center for Emerging and Zoonotic Infectious Diseases, Division of Vector-Borne Infectious Diseases (Fort Collins, CO, USA) by enzyme immunoassay and Western blot (IgM and IgG) for TBRF antibody reactivity. Seroconversion was demonstrated by rising enzyme immunoassay values (S1 = 0.79, S2 = 2.41; equivocal range 0.64–0.91) and separate IgM and IgG Western blots (Technical Appendix[PDF – 376 KB – 3 pages] Figure 3). In addition, the samples demonstrated seroconversion (S1 = 0.91, S2 = 3.23; equivocal range 0.90 –1.09) against C6, an immunogenic antigen conserved among Borrelia spp. (Borrelia burgdorferi ELISA; Immunetics, Inc., Boston, MA, USA).

Spirochetes were successfully cultured, and genomic sequencing determined that B. turicatae was the causative agent (3). The patient improved rapidly with doxycycline, and platelet count normalized within 2 weeks. Ten asymptomatic soldiers with similar exposure were identified and prophylactically given doxycycline; 24 asymptomatic soldiers who had been in the area but not in the same barn as the patient were monitored closely. No additional illnesses were detected.

TBRF is a neglected and probably underdiagnosed disease. The vector, the Ornithodoros turicata tick (soft bodied tick – picture here:  https://en.wikipedia.org/wiki/Ornithodoros_turicata), is endemic to Texas and Florida (4); but although published cases in Texas have been supported by serology for the TBRF group, exposure location, and tick collections (4,5), to the best of our knowledge, successful identification of B. turicatae in a human has not been reported. Previously, B. turicatae has been isolated only from ticks and canids (foxes, wolves, dogs, jackals, and coyotes) in several areas of Texas (4–6).

The ecologic setting of the military exercises was predictable for high-risk exposure to the tick vector. TBRF attack rates >22% have been reported for group settings with sequelae severe enough to warrant hospitalization (7,8). Military training groups in Israel have declared certain caves off limits because of heavy tick presence (9) and have prophylactically administered doxycycline to those suspected to have been exposed (7). There has not been an association of Jarisch-Herxheimer reaction in asymptomatic patients receiving doxycycline (7), although this reaction is common during treatment of patients with active illness (9).

We identified several difficulties in epidemiologic awareness and diagnosis. There is overlap of bacterial, viral, and parasitic pathogens in location and nonspecific symptom presentations. The O. turicata tick bite is rarely noticed or reported because the vectors are rapid nocturnal feeders, attachment is painless, and often no lesions or ticks are discovered (10). This case report with successful isolation and genetic characterization of B. turicatae from the soldier (3) confirms that this spirochete species is a zoonotic pathogen. The initial misdiagnosis further indicates the neglected nature of this disease, especially in the military population.

Dr. Christensen is a second-year family medicine resident and medical officer in the US Air Force, stationed at Eglin Air Force Base, Florida. Her research interests include infectious diseases as they affect military and operational medicine.

Acknowledgment

We acknowledge the help of Dolli Lane, Christopher Boyd, and Michael McFall in identifying bacteria on peripheral smears and definitively identifying this case.

References

  1. Meader CN. Five cases of relapsing fever originating in Colorado, with positive blood findings in two. Colo Med. 1915;12:365–9.
    2. Dworkin MS, Schwan TG, Anderson DE Jr. Tick-borne relapsing fever in North America. [viii–ix.]. Med Clin North Am. 2002;86:417–33, viii–ix. DOIPubMed
    3. Kingry LC, Batra D, Replogle A, Sexton C, Rowe L, Stermole BM, et al. Chromosome and linear plasmid sequences of a 2015 human isolate of the tick-borne relapsing fever spirochete, Borrelia turicatae. Genome Announc. 2016;4:e00655–16. DOIPubMed
    4. Donaldson TG, Perez de Leon AA, Li AI, Castro-Arellano I, Wozniak E, Boyle WK, et al. Assessment of the geographic distribution of Ornithodoros turicata (Argasidae): climate variation and host diversity. PLoS Negl Trop Dis. 2016;10:1–19.
    5. Wilder HK, Wozniak E, Huddleston E, Tata SR, Fitzkee NC, Lopez JE. Case report: A retrospective serological analysis indicating human exposure to tick-borne relapsing fever spirochetes in Texas. PLoS Negl Trop Dis. 2015;9:e0003617. DOIPubMed
    6. Whitney MS, Schwan TG, Sultemeier KB, McDonald PS, Brillhart MN. Spirochetemia caused by Borrelia turicatae infection in 3 dogs in Texas. Vet Clin Pathol. 2007;36:212–6. DOIPubMed
    7. Hasin T, Davidovitch N, Cohen R, Dagan T, Romem A, Orr N, et al. Postexposure treatment with doxycycline for the prevention of tick-borne relapsing fever. N Engl J Med. 2006;355:148–55. DOIPubMed
    8. Jones JM, Schumacher M, Peoples M, Souders N, Horn K, Fox L, et al.; Centers for Disease Control and Prevention (CDC). Notes from the Field: tick-borne relapsing fever outbreak at an outdoor education camp. MMWR Morb Mortal Wkly Rep. 2015;64:651–2 Morb Mortal Wkly Rep..PubMed
    9. Assous MV, Wilamowski A. Relapsing fever borreliosis in Eurasia—forgotten, but certainly not gone! Clin Microbiol Infect. 2009;15:407–14. DOIPubMed
    10. Boyle WK, Wilder HK, Lawrence AM, Lopez JE. Transmission dynamics of Borrelia turicatae from the arthropod vector. PLoS Negl Trop Dis. 2014;8:e2767. DOIPubMed

For more on the military and Lyme/MSIDS:  https://madisonarealymesupportgroup.com/2017/03/21/military-veterans-suicide-and-lymemsids/