Archive for the ‘research’ Category

Babesia Symptoms Can Be Deadly: A Family’s Story

https://danielcameronmd.com/babesia-symptoms-can-be-deadly-a-familys-story/

BABESIA SYMPTOMS CAN BE DEADLY: A FAMILY’S STORY

babesia-symptoms-deadly
The number of Babesia cases appears to be rising and as a recent article in the Washington Post reports, the tick-borne infection can be deadly when symptoms go unrecognized.

Babesia symptoms can be wide-ranging and difficult to recognize by clinicians and a missed or delayed diagnosis can be deadly.

In hopes of raising awareness, one family shares their story of a Babesia diagnosis that came just a little too late.

Jeff, a 51-year-old husband and father, was hospitalized with symptoms of jaundice, agitation and inability to urinate. It took 3 days before he was diagnosed with Babesia. But his symptoms had been present for at least one month — unrecognized, as the infection progressed.

Tiny tick leads to deadly infection

As his wife tells writer Abby Schwartz from the Washington Post,¹ Jeff frequently hiked outdoors near their home in Bucks County, Pennsylvania. About a month prior to being admitted into the hospital, he had removed a tick, “no bigger than a poppy seed.”

In hindsight, “he may have had Babesia for a month,” Schwartz writes.

Diagnosis comes too late

For several weeks, Jeff reportedly had Babesia symptoms including fevers and night sweats. But clinicians presumed he had a kidney infection and prescribed a course of antibiotics. He improved briefly.

Then, he took a turn for the worst. “Jeff was weaker, sweating, unable to sleep,” his wife explains. “His breathing was labored. The whites of his eyes had yellowed, and his bilirubin was climbing, a sign that red blood cells were breaking down at an unusual rate or of liver trouble.”


READ MORE: Babesia cases among the elderly are rising, may require longer treatment


He was moved to the ICU and placed in a medically-induced coma and put on a ventilator. Doctors noted that his symptoms resembled malaria, but still did not suspect a tick-borne infection.

“His team periodically woke him, and he would squeeze his wife’s hand.”

On Tuesday, an infectious disease doctor shared some positive news. “We think we have a diagnosis.”

They suspected that Jeff had Babesiosis, a potentially deadly infection caused by parasites Babesia microti, which is typically transmitted through a tick bite.

He was prescribed an antibiotic (azithromycin) and antiparasitic (Atovaquone) medication for 7 to 10 days.

On Thursday, he died — just 2 days after starting treatment.

“If Jeff had been diagnosed early, when he first complained of night fevers, it might have been different for him,” writes Schwartz.

Since Jeff’s death, his wife and family have worked to raise awareness about Babesia.

Babesia signs and symptoms

Most people infected with Babesia do not show symptoms or have mild to moderate flu-like symptoms such as fatigue, chills, sweats, headache, body aches, nausea, and loss of appetite, which can appear days or even months later. (There is no telltale rash as with Lyme disease.)

Individuals most at-risk include the elderly and people with immunocompromised conditions. In fact, the death rate among those with an impaired immune system is as high as 20%, explains Peter Krause, a senior research scientist at Yale School of Public Health and Yale School of Medicine.

Although it is usually transmitted through a tick bite, Babesia can be acquired through a tainted blood transfusion.

Babesia cases are reported mostly in the Northeast and Upper Midwest but the disease is “increasing in frequency and geographic range,” warns Krause.

Babesia: Not recognized by all doctors

“It has to step up to the level of an infectious-disease specialist being brought in before it might get diagnosed, whereas in an area where it’s more prevalent, some of the front-line people, the emergency room doctors or urgent care doctors, might be a little more attuned to it,” says Sorana Segal-Maurer, an infectious-disease specialist at New York-Presbyterian Queens Hospital.¹

Editor’s notes:

I disagree with three statements made by doctors interviewed for the story:

  1. I have Babesia patients who do not improve with only 7 to 10 days of treatment.
  2. I have Babesia patients who are sick who do not meet the risk criteria described above.
  3. I have Babesia patients who removed the tick in less than 24 hours and still became ill.
References:
  1. Babesiosis, a dangerous tick-borne infection that attacks red blood cells, appears to be a growing problem. Abby Schwartz, Washington Post, 5/29/21.

______________________

For more:

Vaccine-Induced Thrombocytopenia & Thrombosis

https://www.nejm.org/doi/full/10.1056/NEJMoa2109908?

Clinical Features of Vaccine-Induced Immune Thrombocytopenia and Thrombosis

List of authors.

  • Sue Pavord, F.R.C.Path., 
  • Marie Scully, M.D., 
  • Beverley J. Hunt, M.D., 
  • William Lester, M.D., 
  • Catherine Bagot, M.D., 
  • Brian Craven, M.B., B.Ch., 
  • Alex Rampotas, M.R.C.P., 
  • Gareth Ambler, Ph.D., 
  • and Mike Makris, M.D.

Abstract

BACKGROUND

Vaccine-induced immune thrombocytopenia and thrombosis (VITT) is a new syndrome associated with the ChAdOx1 nCoV-19 adenoviral vector vaccine against severe acute respiratory syndrome coronavirus 2. Data are lacking on the clinical features of and the prognostic criteria for this disorder.

METHODS

We conducted a prospective cohort study involving patients with suspected VITT who presented to hospitals in the United Kingdom between March 22 and June 6, 2021. Data were collected with the use of an anonymized electronic form, and cases were identified as definite or probable VITT according to prespecified criteria. Baseline characteristics and clinicopathological features of the patients, risk factors, treatment, and markers of poor prognosis were determined.

RESULTS

Among 294 patients who were evaluated, we identified:

  • 170 definite cases of VITT
  • 50 probable cases of VITT
  • All the patients had received the first dose of ChAdOx1 nCoV-19 vaccine and presented 5 to 48 days (median, 14) after vaccination. The age range was 18 to 79 years (median, 48), with no sex preponderance and no identifiable medical risk factors
  • Overall mortality was 22%
  • The odds of death increased by a factor of
    • 2.7 (95% confidence interval [CI], 1.4 to 5.2) among patients with cerebral venous sinus thrombosis
    • 1.7 (95% CI, 1.3 to 2.3) for every 50% decrease in the baseline platelet count
    • 1.2 (95% CI, 1.0 to 1.3) for every increase of 10,000 fibrinogen-equivalent units in the baseline d-dimer level
    • 1.7 (95% CI, 1.1 to 2.5) for every 50% decrease in the baseline fibrinogen level
    • Multivariate analysis identified the baseline platelet count and the presence of intracranial hemorrhage as being independently associated with death
    • observed mortality was 73% among patients with platelet counts below 30,000 per cubic millimeter and intracranial hemorrhage
CONCLUSIONS

The high mortality associated with VITT was highest among patients with a low platelet count and intracranial hemorrhage. Treatment remains uncertain, but identification of prognostic markers may help guide effective management. (Funded by the Oxford University Hospitals NHS Foundation Trust.)

_____________________

**Comment**

The numbers don’t lie.  

A majority of these “vaccinated” patients had VITT which explains what is happening in reality – blood clotting issues.  

  • We’ve been warned by a Canadian doctor doing D-dimer tests on his “vaccinated” patients that 62% show microscopic blood clotting.
  • A pathologist also states these injections cause severe inflammation due to the “spike protein” which is a dangerous toxin that crosses the blood-brain barrier and disrupts blood vessels throughout the body and brain.  He also reiterates that these injections are not “vaccines.”

Please notice the overall mortality of 22% and significant increased odds of death on these fully “vaccinated” individuals that have been told ad nauseam that these injections will be protective and keep you from hospitalization and death.

For a mounting list of adverse reactions and death (with many examples of blood clotting & cardiovascular issues – even in young people):  https://madisonarealymesupportgroup.com/2020/12/21/warning-3150-injuries-in-1st-week-of-covid-vaccines-among-american-healthcare-workers-pregnant-women-included/

Double-Blind Study Shows Ivermectin Reduces Disease Duration & Infectiousness

https://m-jpost-com.cdn.ampproject.org/c/s/m.jpost.com/health-science/israeli-scientist-says-covid-19-could-be-treated-for-under-1day

MAAYAN JAFFE-HOFFMAN

Double-blind study shows ivermectin reduces disease’s duration and infectiousness • FDA and WHO caution against its use

Ivermectin, a drug used to fight parasites in third-world countries, could help reduce the length of infection for people who contract coronavirus for less than a $1 a day, according to recent research by Sheba Medical Center in Tel Hashomer.
Prof. Eli Schwartz, founder of the Center for Travel Medicine and Tropical Disease at Sheba, conducted a randomized, controlled, double-blinded trial from May 15, 2020, through the end of January 2021 to evaluate the effectiveness of ivermectin in reducing viral shedding among nonhospitalized patients with mild to moderate COVID-19.
Ivermectin has been approved by the US Food and Drug Administration since 1987. The drug’s discoverers were awarded the 2015 Nobel Prize in medicine for its treatment of onchocerciasis, a disease caused by infection with a parasitic roundworm.
Over the years, it has been used for other indications, including scabies and head lice. Moreover, in the last decade, several clinical studies have started to show its antiviral activity against viruses ranging from HIV and the flu to Zika and West Nile.  (See link for article)
____________________
**Comment**
The study found in MedRxiv, a health-research sharing site, has not yet been peer reviewed.  The study found:
  • Approx. 72% of the Ivermectin group tested negative and 13% were infectious after day six
  • 50% of the placebo group tested positive and 50%, almost 4 times as many, were infectious after day six
  • 5 patients were referred to hospitals, 4 of them were in the placebo group
  • One hospitalized patient complained of shortness of breath, continued on ivermectin and was sent back to the hotel a DAY later in good condition
“Our study shows first and foremost that ivermectin has antiviral activity,” Schwartz said. “It also shows that there is almost a 100% chance that a person will be noninfectious in four to six days, which could lead to shortening isolation time for these people. This could have a huge economic and social impact.”
The study author points out that while this study did not address ivermectin as a prophylactic, or address hospitalization reduction, other studies have shown such evidence.
Other studies have shown:
  • 27 studies demonstrate ivermectin’s ability to prevent COVID
  • a recent review found ivermectin reduced death by 75%

Please see:  

isummary

Interestingly, ivermectin is on the WHO’s list of essential medicines yet an Israeli professor states there’s significant risks with it and that ‘caution should be used on a virus that the vast majority of the public will recover from without treatment.’  He didn’t bother to mention anything about fast-tracked experimental “vaccines” that thousands have been maimed and killed from and that experts are warning against.
To date the WHO is not supporting any trials to determine ivermectin’s viability.
Researchers in other places worldwide began looking into the drug at around the same time. But when they started to see positive results, no one wanted to publish them, Schwartz said.
“There is a lot of opposition,” he said. “We tried to publish it, and it was kicked away by three journals. No one even wanted to hear about it. You have to ask how come when the world is suffering.”
“This drug will not bring any big economic profits,” and so Big Pharma doesn’t want to deal with it, he said.
The article points out that some of the loudest opposition has come from Merck, the manufacturer of ivermectin since the 80’s.  Merck was peddling COVID vaccines until it was discovered “the immune responses were inferior to those seen following natural infection and those reported for other SARS-CoV-2/COVID-19 vaccines.”  Now it’s peddling molnupiravir, which raked in 1.2 BILLION from a deal with the U.S. government.  It is currently in a phase 3 clinical trail.  So why make pennies when you can make BILLIONS?
For more:

Can Lyme Disease Trigger An Autoimmune Disease?

https://danielcameronmd.com/can-lyme-disease-trigger-an-autoimmune-disease/

CAN LYME DISEASE TRIGGER AN AUTOIMMUNE DISEASE?

elderly man with Lyme disease and autoimmune disease taking his temperature

An increasing number of studies indicate that Lyme disease may ignite an autoimmune reaction in some individuals or symptoms may mimic an autoimmune disease. In their report, “Lyme arthritis presenting as adult-onset Still’s disease,” researchers describe the first known case of Lyme disease triggering Adult-Onset Still’s Disease, an auto-inflammatory condition that can impact the entire body (systemic disease).

Adult-onset Still’s disease (AOSD) is often thought to be an autoimmune disease, but is, in fact, a systemic auto-inflammatory condition, believed to be caused by an over-reactive immune response to an infection, such as Lyme disease. As Cimmino points out, both diseases share several clinical characteristics.¹

Still’s disease can cause “a triad of high fever, salmon-colored nodular rash and arthritis and/or arthralgia,” explains Ocon in the British Medical Journal.² Lyme disease can also present with fevers, atypical rashes and arthritis and/or arthralgias.

Both conditions were first identified in children. Still’s disease was initially considered a severe version of juvenile idiopathic arthritis (JIA), while Lyme disease symptoms were originally attributed to juvenile rheumatoid arthritis (JRA).

Lyme disease and autoimmune diseases

A growing number of studies indicate that Lyme disease may trigger an autoimmune response in some individuals or symptoms may mimic an autoimmune disease.

The authors suggest, “[Lyme disease] could be a great mimicker of other autoimmune diseases like DM.”

Case Presentation: Still’s disease

A 61-year-old man presented with a “complaint of intermittent spiking fevers, night sweats, generalised malaise, as well as a history of erythematous circular rashes on his right upper extremity,” writes Ocon.²

He was diagnosed clinically with Lyme disease and received two 10-day courses of doxycycline, but continued to suffer from fevers, chest pressure, a dry cough, along with malaise and arthralgia.

The man was subsequently diagnosed with Still’s disease, as he met the criteria with a fever greater than 102.2°F for at least 1 week; a characteristic rash; a white cell count of at least 10,000; lymphadenopathy, and elevated liver transaminases.

He was treated successfully with intravenous steroids and anakinra (a humanised interleukin-1 receptor antagonist), which is used to modulate the immune system.

Author’s Takeaway:

“For the first time, we describe a case of AOSD precipitated by Lyme disease.”

“Lyme disease is a rare trigger of adult-onset Still’s disease, likely mediated via immune system inflammatory activation.”

“AOSD presented with a rare manifestation of haemorrhagic pericarditis and tamponade.”

“We believe that the immunological response to Lyme disease may have triggered AOSD via a hyper-activated immune system.”

UPDATED: July 1, 2021

References:
  1. Cimmino MA, Trevisan G. Lyme arthritis presenting as adult-onset Still’s disease. Clin Exp Rheumatol. 1989;7(3):305-308.
  2. Ocon AJ, Kwiatkowski AV, Peredo-Wende R, Blinkhorn R. Adult-onset Still’s disease with haemorrhagic pericarditis and tamponade preceded by acute Lyme disease. BMJ Case Rep. 2018;2018:bcr2018225517. Published 2018 Aug 16. doi:10.1136/bcr-2018-225517
  3. Cross A, Bouboulis D, Shimasaki C, Jones CR. Case Report: PANDAS and Persistent Lyme Disease With Neuropsychiatric Symptoms: Treatment, Resolution, and Recovery. Front Psychiatry. 2021 Feb 2;12:505941. doi: 10.3389/fpsyt.2021.505941. PMID: 33603684; PMCID: PMC7884317.

For more:

Ecologically Diverse Texas Needs County-Level Data For Tick-borne Diseases

https://www.lymedisease.org/maxwell-texas-tick-borne-diseases/

Ecologically diverse Texas needs county-level data for tick-borne diseases

Aug. 2, 2021

By Sarah Maxwell, PhD

Welcome to the complex world of tick-borne disease surveillance. But honestly, it should not be so difficult. Why does the public health system fail to inform schools, camps, parents, physicians, pediatricians, psychiatrists, and others about county-level risks of tick-borne disease? Why are prevention and diagnosis so difficult?

The answers are rooted in the lack of available, dis-aggregated, and comprehensive data. But they are also complicated  by the use of “Lyme” as a catch-all phrase encompassing a variety of tick-borne diseases, when Lyme may be less endemic in some areas than other tick-borne diseases.

From a health policy perspective, the importance of county-level data to prevention, diagnosis, and treatment cannot be overstated.  For almost all other diseases, sustainable and reliable county data are the foundations to building healthy communities. So why not tick-borne diseases?

Focusing on Texas

In a recent article, Drs. Connie McNeely, Kip Thomas, and Chris Brooks and I employed promising new approaches to tick-borne disease surveillance in Texas with the goal of linking differing forms of tick-borne disease surveillance data into a comprehensive picture. The Centers for Disease Control (CDC) supports the “One Health Model,” which considers people, animals, and the environment as interconnected in assessing and addressing zoonotic disease.

In our article in the journal Healthcare titled “Tick-Borne Surveillance Patterns in Perceived Non-Endemic Geographic Areas: Human Tick Encounters and Disease Outcomes,” we compared canine serological reports of Lyme, ehrlichiosis, and anaplasmosis; patient self-reported diagnoses and tick-bite recall; official reports of Lyme disease from the CDC; and ecosystem habitat suitability through multi-layer thematic mapping.

As noted in our study: “The overall purpose was to determine if clinically diagnosed and CDC-positive Lyme disease human reports are geographically similar in disaggregated form via county, bordering county, and ecosystem to canine and official CDC counts. Comparisons between patient self-reported disease and official counts of disease are not widely used methods of surveillance, but are important epidemiological tools when disease can be linked to an event, such as a tick bite.”

Texas is a large state and often perceived to be non-endemic for tick-borne diseases. However, at the county level, the picture is quite different. Numerous counties in Texas are endemic to tick-borne diseases. So why the dilemma?

Importance of county-level data

The need for such comprehensive and new surveillance techniques is imperative. Here is why: The CDC publishes county-level Lyme disease data for anyone to view. However, the CDC limits all other tick-borne diseases to state-level surveillance only. The public and researchers do not have access to these data.[1]

CDC’s Lyme disease spreadsheet, on the other hand, is updated annually and published on the CDC website. Therefore, public health officials should, in theory, have the data they need to design prevention campaigns and assess human disease risk. Nationally, however, those data are known to undercount the real presence of Lyme disease, as numerous scholars have demonstrated.

Additionally, some of the cases within the CDC dataset may not be locally acquired. Hypothetically, an individual may travel to the Northeast, return ill, and be listed in the CDC database as a case in Contra Costa, California. Researchers who study Lyme disease prevalence must dig, and dig hard, state by state to double check those cases that may not be locally acquired.[2]

In our paper in Healthcare, we did just that. However, our focus was Texas, so the digging was concentrated to one state, where we were able to remove non-locally-acquired cases.

Even if Lyme disease data were perfect, however, researchers and some public health officials are faced with a constant obstacle: Lyme disease is not the only tick-borne disease. Ticks can carry many different pathogens. Yet, the CDC does not publish county-level data for tick-borne diseases other than Lyme. Given many patients with Lyme disease report having multiple co-infections, knowing the disease risk is imperative for physician knowledge and adoption of prevention behaviors among local community residents.

“Lyme” is often a catch-all phrase

At the same time, “Lyme” is often used as a blanket term and adopted by national and state organizations to cover a host of possible other infections such as Babesia or ehrlichiosis. The catch-all phrase “Lyme” could potentially detract from the wide range and prevalence of other tick-borne diseases in the United States.

In our study, we attempted to improve surveillance of tick-borne diseases, including Lyme, using data drawn from a specialized survey—the Texans and Ticks Survey (TTS)—developed to collect state-, county-, and zip-code-level self-reported patient information.

TTS included the geographic location of tick bite encounters. All survey respondents reported a Lyme disease diagnosis by a medical professional. Survey respondents were asked if they had received a diagnosis, and if so, how they had been diagnosed. They could select: (1) Clinically (the doctor thinks you have Lyme disease based on your history and symptoms); (2) Western Blot, where some bands were positive; (3) Western Blot, where five or more bands were positive (“CDC-positive”); (4) IGeneX or other specialty lab; or (5) I do not know/Not sure.

Respondent tick bite encounters of those who self-reported a Lyme diagnosis were mapped at the county level. Since counties with higher populations would naturally experience more tick bites (all else held constant), by-county raw case frequencies were corrected with respect to the county’s population density, and standardized as the number of cases per 100,000 individuals.

Comparing maps

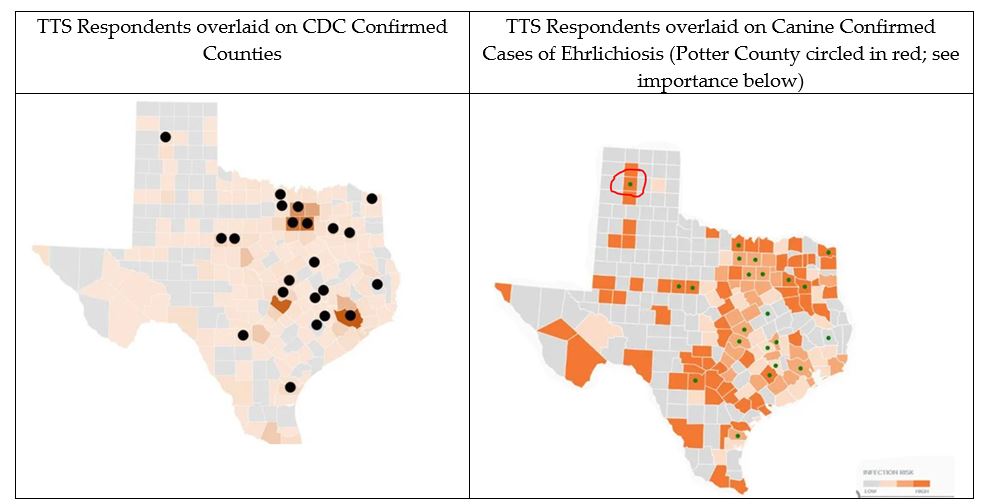
We overlaid survey respondents’ tick bite encounter locations on maps with official CDC human Lyme disease cases and canine cases of Lyme, ehrlichiosis, and anaplasmosis. Examples are below:

Overall, we found that the survey respondents only reported tick bites in areas known to be suitable to ticks and tick-borne disease transmission as shown via canine serological and official CDC human reports. These findings held true for all official human Lyme cases, as well as canine Lyme, ehrlichiosis, and anaplasmosis (not pictured).

Importantly, clinically diagnosed patients match known and official cases of Lyme and other tick-borne diseases in Texas. Without access to CDC cases of other county-level tick-borne disease, self-reported tick bite encounters, associated diseases, and a one-health approach to assess overlap with human and canine cases, proved to be a promising exploratory study that warrants further attention at the national level. We suggest that self-reported clinically diagnosed patient reports and serological canine reports can serve as proxies for assessing human disease risk.

These findings were not a result of simple population density, and also followed the same hot-spot clusters as human and canine cases. Additionally, they occurred in ecosystems suitable for ticks. If these respondents were randomly lying about their tick bite locations, chances of all the respondents making up tick-bite encounters only in suitable or endemic counties would be almost impossible.

Diverse ecosystems

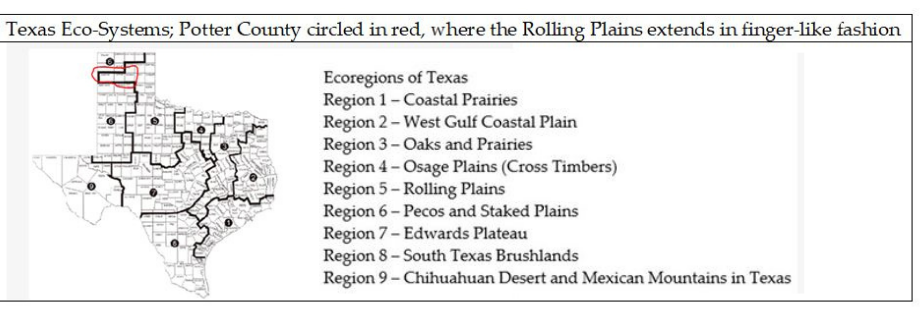
Back to our data dilemma: Why is providing only state level data insufficient? In states such as Texas, ecosystems are diverse and not all are suitable tick habitats. If the perception is that Texas is not endemic, we miss numerous counties where individuals have reported tick bites and a subsequent clinical Lyme diagnosis. Our study demonstrates that county-level data allow for more fine-tuned decision-making and risk assessment.

Take Potter County, Texas, as one example. The  drier northwestern area of the state, known as the Texas Panhandle, has an ecoregion suitable for tick habitat that extends into a drier, less tick-suitable ecosystem. The ecoregion that covers most of the panhandle is not as suitable for tick populations, However, the extension from the Rolling Plains into just a few counties does offer suitable tick habitat. We find overlap in Potter County with canine reports of tick-borne disease and CDC cases.

Did you know that in 2020, 1 in 20 dogs tested for ehrlichiosis in Potter County Texas was positive? However, only 1 in 1,000 canines in Potter County tested positive for Lyme disease. Should physicians test humans for ehrlichiosis in addition to Lyme disease in a few counties in the Texas Panhandle if the patient presents with tick-borne illness symptoms? I don’t have the answer to that. But I do know county-level data are desperately needed in tick-borne disease surveillance if public health officials hope to prevent disease.

Indeed, most diseases, for example West Nile, are incorporated into interactive, useful, county-level maps on the CDC webpage. Perhaps it is time to rethink the public health commitment to tick-borne disease surveillance so that both the general public and health officials can make informed and equitable decisions.

There are no sustainable, easy-to-access local tick-borne disease data that allow for communities to improve health outcomes for those who may be affected, including vulnerable populations who are the least likely to receive a diagnosis and care, especially in areas that are perceived to be “non-endemic.”

Click here to read the journal article.

Dr. Sarah Maxwell is an assistant provost and associate professor at the University of Texas at Dallas. Her research and grants focus on tick-borne disease surveillance and patient experiences with Lyme disease. She and her co-authors are founding members of ICI-Vector, created to Integrate, Communicate, and Inform others about tick-borne disease. She also serves on the scientific board of the Texas Lyme Alliance.

Footnotes

[1] Researchers may apply for these data from the CDC, but if granted access, are prohibited from publishing data at the county-level.

[2] My understanding is that not all states differentiate locally-acquired cases.