Archive for the ‘Lyme’ Category

LymeMIND Replay

https://www.lymedisease.org/lymemind-fb-replay/  See video here

Watch Facebook replay of Oct. 10 LymeMIND conference

IV Antibiotics for Lyme: Pros, Cons, and the Lived Experience

https://globallymealliance.org/intravenous-antibiotics-for-lyme-pros-cons-and-the-lived-experience/

September 3, 2020

MyLymeLife_2-26by Jennifer Crystal

HAS YOUR DOCTOR RECOMMENDED YOU GET A PICC LINE TO TREAT YOUR LYME DISEASE? HERE ARE THE PROS AND CONS OF IV ANTIBIOTICS FOR LYME.

When diagnosed right away, many cases of Lyme disease can be treated with a three-week course of oral antibiotics. Some 20% of patients, however, go on to experience continued symptoms—known as Post Treatment Lyme Disease Syndrome—and require more antibiotics. Still others, like myself, suffer with Late Disseminated Lyme Disease, which isn’t diagnosed until months or years after a tick bite. By that point, the Lyme bacteria, called a spirochete, has replicated and invaded many systems of the body, often crossing the blood-brain barrier.

This stage of Lyme disease is so advanced that Lyme Literate Medical Doctors (LLMDs) often recommend intravenous antibiotics, administered through a peripherally inserted central catheter (PICC line). A port is placed in your arm with a line that runs directly to your heart. The port remains in your arm for as long as your doctor recommends—in some cases months or even years—and you self-administer antibiotics. Just the idea of having a PICC line is understandably daunting to patients. Many write to me wondering if they should pursue this route. I responded briefly to this question in one of my “Dear Lyme Warrior…Help!” columns. In this blog, I will share more about my own experience with a PICC line, and outline pros and cons.

My Experience

I was bitten by a tick in 1997, but wasn’t diagnosed with Lyme disease and two of its co-infections, babesia and ehrlichia, until 2005. By that time the infections had crossed into my central nervous system, making them more difficult to treat. My LLMD had me start with oral antibiotics. At first, they caused a Herxheimer reaction, which told my doctor that the medication was working. However, after six weeks of treatment, he determined that it wasn’t working fast enough, and recommended a PICC line.

A nurse put the line in at the doctor’s office. It felt like getting a regular IV inserted; I could not feel the line moving from my arm to my heart. I had a chest x-ray to make sure the line was correctly in place, and then the nurse administered the first dose of antibiotics, to make sure I didn’t have a bad reaction. He also taught me how to administer the medication myself. Instead of a typical IV bag, the medication came in a bolus, a hard ball that needed to be refrigerated. The nurse showed me exactly how to wash my hands before touching my port; how to pinch the port with two fingers and clean it with an alcohol wipe; how to first flush the line with saline, and then how to attach the bolus; how to flush the line with saline and heparin (to prevent clots) once I’d finished infusing; and how to properly replace the port’s cap and safely wind it up, tucking it inside a mesh sleeve when I was done.

After a few days, I felt like a nurse myself. Armed with the right knowledge and my nurse’s phone number, I felt safe hooking my port up to a bolus twice a day. With my arm outstretched on the kitchen table, I read the paper in the morning and watched game shows at night to pass the hour that it took for the boluses to deflate. Once a week, the nurse came to my house to clean the line and draw my blood, so my doctor could run lab work to make sure I was reacting well to the medication.

When I wasn’t infusing medication, I generally was able to go about my day as normal (which, at that time of acute illness, didn’t include much beyond resting and taking the occasional trip to the pharmacy). I sometimes forgot the PICC line was even there. That said, I did have to take certain precautions with it. It was very important not to get even a drop of water on the line. Therefore, I wore a special sleeve to cover it when doing dishes or washing my hands; took baths instead of showers; and had someone else wash my hair in the sink. When out in public, I wrapped an ace bandage around the mesh sleeve that held my port in place, for extra protection; I had to be sure not to snag the line on anything. For that reason, I generally didn’t sleep on that side.

Despite these limitations and an unexpected gallbladder attack (which I’ll explain below), I am still glad I used a PICC line for the year that I had it in my arm. Would I have gotten better if I had stayed on oral antibiotics? Probably. Some LLMDs use them exclusively, even pulsing them on and off. But likely my recovery would have taken much longer. I saw great improvement in a year’s time, so the intravenous route was the right one for me.

When weighing whether it’s right for you, consider the following pros and cons:

Pros

  • Efficacy and efficiency: Intravenous antibiotics are stronger than oral antibiotics, so they can attack spirochetes faster and more effectively.
  • Pressure off the gut: Oral antibiotics can cause gastrointestinal issues such as candida. Intravenous antibiotics are a more direct route that doesn’t affect your stomach.
  • Different medication options: Some antibiotics can be offered both orally and intravenously, while others work better in one form or the other. Intravenous antibiotics give your LLMD more options with which to treat your infection(s), and sometimes changing up treatment is helpful when you’ve hit a plateau.
  • Medical know-how: Once you’ve had a PICC line and have self-administered intravenous antibiotics, other medical procedures seem like a snap. I learned so much from being my own nurse that I now feel better informed when asking doctors questions and advocating for myself, whether with Lyme or another illness. 
  • Weekly company: Lyme disease can be very isolating, especially when you’re too sick to leave the house. I looked forward to my nurse’s weekly visits for much-needed socialization.

Cons

  • More intense Herxheimer reactions: Because a PICC line allows you to get a higher dose of antibiotics into your system faster, the die-off of spirochetes can also be quicker. Your body may not be able to eliminate the dead bacteria as fast as the antibiotics kill them. This can cause some intense Herxheimer reactions. Your doctor may give you a few days off of treatment to allow your body time to detox.
  • Risk of gallstones: Gallstones are a rare side effect of certain intravenous antibiotics. I happened to get them, and had to undergo emergency gallbladder removal. That was in 2005. These days, LLMDs are more aware of which medications come with this risk (and tend to avoid them when possible), and are also able to prescribe proactive treatment against gallstones.
  • Risk of clots: Following the proper protocol is essential to keeping a PICC line clean, but even so, the line can clot. This happened to me one night (I noticed when I couldn’t push the heparin into the line) and requires a nurse to come immediately. In some cases you may have to get the line removed, though my line was able to be repaired at home.
  • Can’t get it wet: Having a PICC line means no swimming, and limitations on other activities like showering. There are special sleeves that you can wear when you’re near water (like when doing the dishes), but the arm absolutely cannot be submerged.

Only you and your LLMD can determine whether a PICC line is right for you. I hope this list will help you make an informed decision.


jennifer crystal_2

Opinions expressed by contributors are their own.

Jennifer Crystal is a writer and educator in Boston. Her memoir about her medical journey is forthcoming. Contact her at lymewarriorjennifercrystal@gmail.com.


_______________________

For more:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

Please know our public ‘authorities’ have maligned IV antibiotics:  https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/  This biased paper was made for one purpose only: to scare the bejesus out of doctors so they won’t utilize IV antibiotics.  

Dr. Waisbren, RIP, was a founder of the IDSA yet utilized potent IV antibiotics successfully with his Lyme/MSIDS patients:  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/

And we learn here that the most successful treatment according to patients is longer-term antibiotics:  

https://madisonarealymesupportgroup.com/2020/10/14/peer-reviewed-study-confirms-what-we-knew-all-along-longer-antibiotic-treatment-duration-is-associated-with-better-treatment-response-for-lyme-disease/

What is truly sad is this work was done by patients for patients. Nothing of help has come from mainstream medicine/research. These people are stuck in a time-warp of their own making and solely focus on the acute stage of Lyme, leaving those with chronic symptoms to rot. Their answer: “it’s all in your head.“

https://madisonarealymesupportgroup.com/2019/02/16/lyme-is-all-in-your-head-a-wake-up-call-to-mental-health-professionals/

https://madisonarealymesupportgroup.com/2017/09/21/its-all-in-your-head-until-finally-a-lyme-diagnosis/

Peer-Reviewed Study Confirms What We Knew All Along: Longer Antibiotic Treatment Duration Is Associated With Better Treatment Response for Lyme Disease

https://www.lymedisease.org/antibiotics-for-lyme-disease/

Antibiotics for Lyme Disease – Useful For Treating Chronic Lyme Patients?

By Lorraine Johnson

10/9/20

One of the thorniest issues in Lyme disease has to do with the use of antibiotics for Lyme disease. According to the Infectious Diseases Society of America (IDSA) and Centers for Disease Control and Prevention, 2-4 weeks of antibiotic treatment is more than enough to knock out the illness.

Here’s the problem with that. Every year, tens of thousands of people who take that prescribed short course of treatment remain ill.

This happens to some of those diagnosed early, and it happens more to those whose diagnosis is delayed. But the IDSA and CDC recommend no further treatment for them. They just say, “Don’t take any more antibiotics.”

Patients who still hope to recover their health often find their way to doctors willing to prescribe longer courses of antibiotics for Lyme disease. And as a result, some people get much better. Unfortunately, however, not everybody.

This is one of the questions we have sought to answer through our MyLymeData patient registry: Why do some people improve substantially with antibiotic treatment, while others do not?

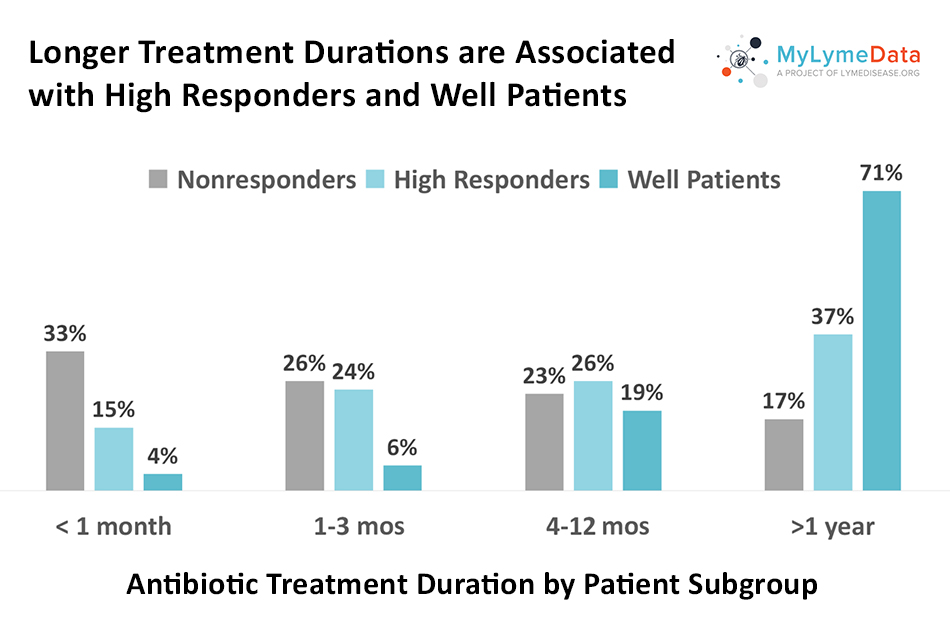
Longer antibiotic treatment durations were associated with better treatment response — with most high responders and well patients reporting treatment durations of four or more months and many reported durations exceeding a year.

Our recently published peer-reviewed study of over 2,000 participants from MyLymeData begins to answer those questions.

How do patients respond to treatment?

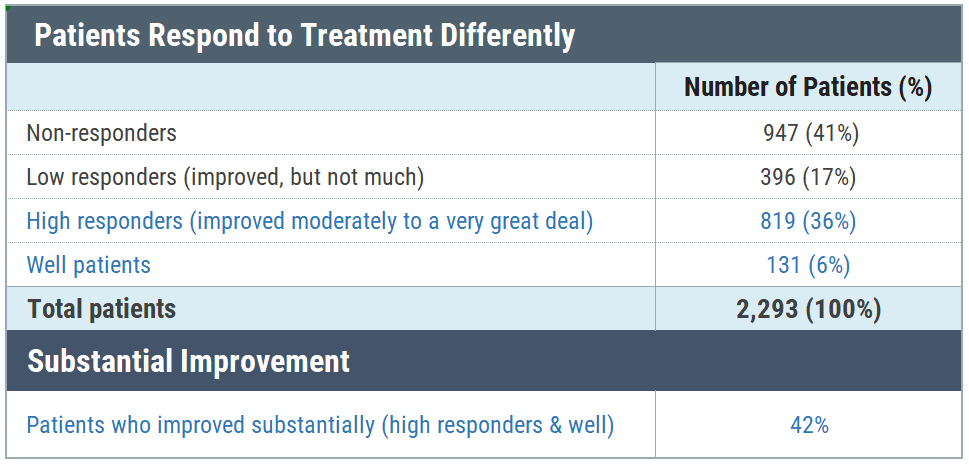
We looked at patients with chronic Lyme disease—those who remained ill for six or more months following treatment with antibiotics for Lyme disease (Shor 2019). The first thing we did was identify different patients as well, high responders, low responders, or non-responders. Well patients responded positively to a survey question asking if they were well or remained ill. Those who remained ill were asked whether their condition had changed as a result of treatment. Those who said they were unchanged or worse (41%) were categorized as non-responders. Patients who said that they were better or worse following treatment, were asked how much better or worse. Those who had improved substantially (moderate to a very great deal of improvement) were deemed high responders.

You can see the break-down of patients in the table below:
Lyme disease antibiotics patient response

59% of patients had improved with treatment and 42% were either well or high responders. The focus of our study was on this latter group. You might wonder whether 42% response is considered good compared to other drugs. (I know I did.) Here’s what the prior head of GlaxoSmithKline said about treatment effectiveness rates of drugs in general (Connor, 2003).

“The vast majority of drugs – more than 90 per cent – only work in 30 or 50 per cent of the people. Drugs out there on the market work, but they don’t work in everybody.”
— Dr. Allen Roses, GlaxoSmithKline

So you can see that a 42% rate of substantial improvement is within the range of most drugs on the market.

Compared to the general population and patients with other chronic diseases, chronic Lyme patients report a substantially lower quality of life and a significant symptom disease burden. In this study, high responders and well patients reported substantially better quality of life, a greater percentage of improvement, and reduction in symptom severity. Patients who identified as well reported their quality of life comparable to the US general population.

What factors determine how patients respond to treatment?

To find out what made some patient substantially improve or become well, we turned to our academic partners at the University of California at Los Angeles who specialize in artificial intelligence and machine learning. Their team looked at 215 features related to diagnostic factors, treatment approach, duration of individual antibiotics, alternative treatments, symptoms, type of clinician, and functional impairment to identify the 30 top predictive features for treatment response (Vendrow 2020). Most of the top 30 features identified in their study related to chronic Lyme disease treatment (20), symptom severity (9), and type of clinician treating Lyme disease. We analyzed three of these factors associated with treatment response:

  • Treatment approach (antibiotics, alternative, both or no treatment)
  • Treatment durations
  • Type of clinician overseeing the patients care

What treatment approach did well patients and high responders use?

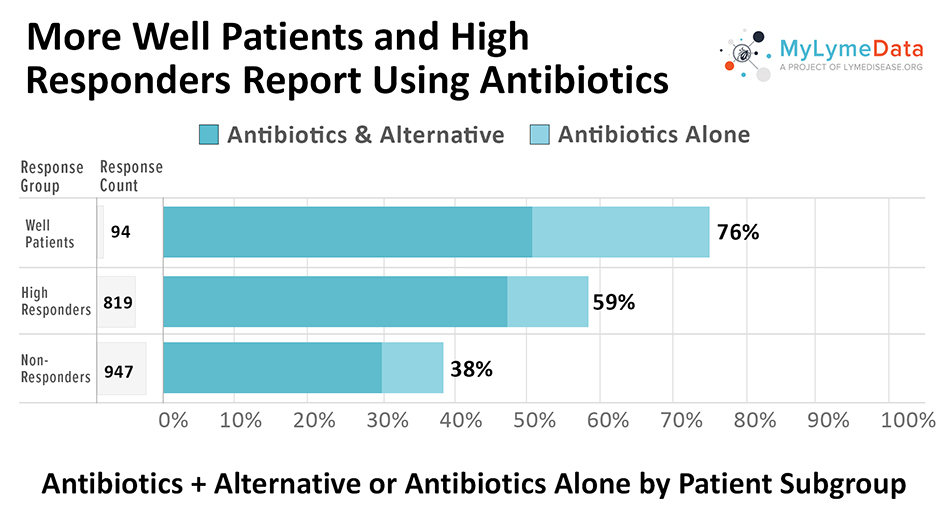
We asked patients what their treatment approach was and listed four options a) antibiotics, b) alternative treatments, c) both antibiotics and alternative treatments, and d) no treatment at all. High treatment response was most closely associated with the use of antibiotics compared to patients who were using alternative treatments alone or forgoing treatment altogether. Treatment with antibiotics for Lyme disease was far higher among well patients (76%) and high responders (59%) compared to non-responders (38%).

As you can see in the chart below, many patients who were taking antibiotics were also taking herbal supplements, which can be antimicrobial (kill bacteria and viruses). So it is possible that there was a synergistic effect between antibiotics and herbal supplements.

More well patients and high-responders report using antibiotics for Lyme disease

Why this is important

The use and duration of antibiotics for chronic Lyme disease treatment is controversial because there is no biomarker that can determine whether the Lyme bacteria has been eradicated in CLD patients. Patients are often told that either chronic Lyme disease does not exist or that it is “incurable.” If this were true, we would not expect more well and substantially improved patients to be taking antibiotics. Instead, we might have expected the percentage of people using antibiotics to be roughly the same among the patient subgroups.

Treatment duration

The optimal chronic Lyme disease treatment is unknown. The four retreatment trials by the National Institute of Health on small samples of patients have produced conflicting results—and most importantly — were all limited to 90 days of treatment (Krupp 2003, Fallon 2008, Klempner 2001, Delong 2012). The Infectious Diseases Society of America (IDSA) and the CDC generally do not recommend treatment for longer than a month (Wormser 2006).

However, a study by the CDC found that patients with Lyme disease generally reported longer treatment durations – with 60% of patients treated for five or more weeks and 36% treated for more than eight weeks (Hook 2015). Unfortunately, that study did not ask patients how long they had been ill. And, the CDC assumed these patients had acute disease – an assumption that may have been wrong. Without looking further, the CDC simply concluded that physicians needed to be better trained to shorten their treatment duration to less than a month.

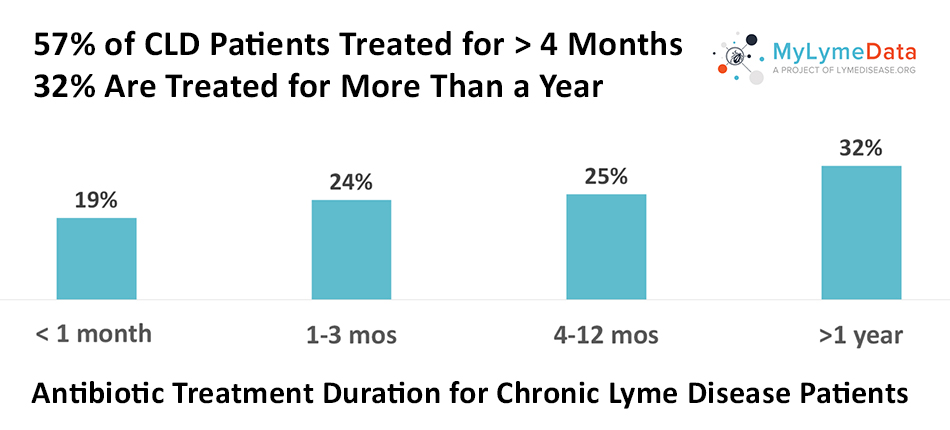
But, as the chart below illustrates, in the study longer chronic Lyme disease treatment durations were common. Most were treated for four or more months (57%), and 32% were treated for more than a year.

Lyme disease antibiotic treatment duration

More importantly, longer treatment durations were associated with better treatment response—with most high responders and well patients reporting treatment durations of four or more months and many reported durations exceeding a year. As the chart below reveals, those treated for less than a month were unlikely to report improvement.

Lyme disease antibiotic treatment duration by patient subgroup

Why this is important

Insurance companies often deny payment for extended antibiotic care for Lyme disease.  Furthermore, many physicians who prescribe long-term antibiotics have been targeted by medical boards. Yet, longer treatments are seen across the board here, with 57% exceeding four months and 32% exceeding one year. This means that these lengths of treatment are common for patients with chronic Lyme disease and reflect clinical practice in the community.

As many as 3 million people have chronic Lyme disease in the US, and nobody knows the best way to treat them,” said Lorraine Johnson, CEO of LymeDisease.org. “The key finding here is that patients who are now well or who report substantial improvement have taken longer courses of antibiotics.”

The fact that more patients who are well or have substantial improvement report longer treatment durations tells us that many patients improve with longer treatment durations. This suggests that the CDC’s conclusion that better clinician training is needed to curb treatment durations is off-base. Instead, it appears that doctors are using their clinical judgement and doing what works for their individual patients. This is the approach recommended by the International Lyme and Associated Diseases Society (ILADS) (Cameron 2014).

The implications of this are profound because they suggest that the legal “standard of care” for patients with chronic Lyme disease is for longer treatment durations. When patients with the most improvement in their health report the longest treatment durations, how can you argue that it should be denied?

Type of clinician overseeing care

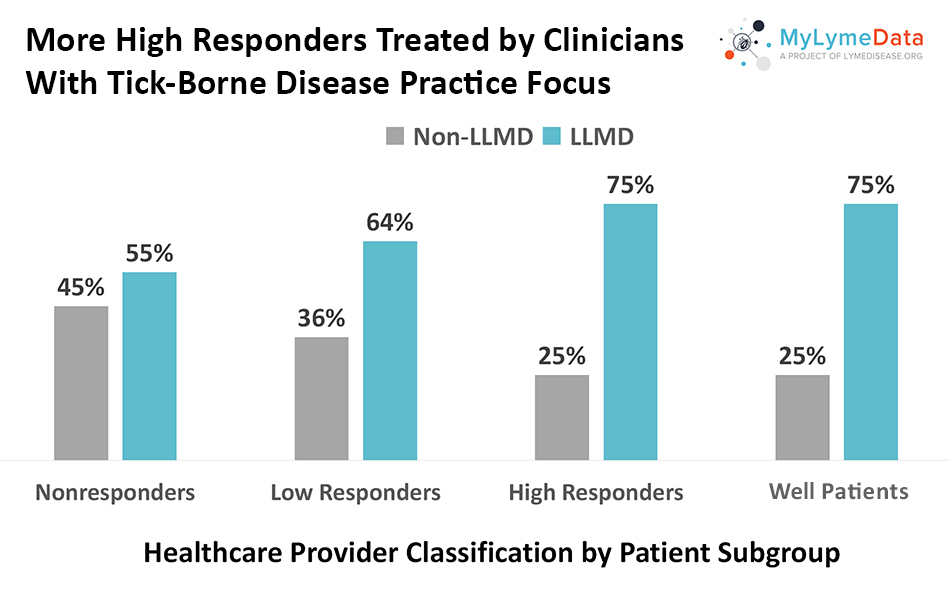
We asked patients to tell us the type of clinician overseeing their care. Choices included: family physicians, internists, rheumatologists, infectious disease specialists, and clinicians whose practice focused on tick-borne diseases (often referred to as Lyme Literate MDs or LLMDs). Very few patients (11%) selected an infectious disease specialist. Seventy-five percent of high responders and well patients report having their care overseen by an LLMD.

More High Responders Treated by Clinicians With Tick-Borne Disease Practice Focus

Physicians who treat Lyme disease as their primary focus might be expected to have better results than physicians who don’t simply because volume of cases handled means a greater experience level. It is commonly recognized in medicine that volume of cases is associated with better treatment outcomes (Joynt 2013). Just as patients with cancer commonly seek out physicians who specialize in that area, perhaps patients with chronic Lyme disease should also.

Why this is important

Medical boards, insurance companies, and the government often rely on the treatment guidelines of the IDSA on the basis that IDSA clinicians have the most expertise in infectious diseases and, accordingly, know what is best for patients with Lyme disease. However, patients with chronic Lyme disease are generally not treated by infectious disease experts. When short term treatment protocols fail, they find another physician to provide more individualized and longer term care. Many of these clinicians specialize in treating chronic Lyme disease and have developed greater experience and knowledge about what works. It is important that high responders and well patients more often report using LLMDs. This shows that LLMDs are associated with better patient outcomes and their expertise in this area should be more highly valued.

Main take-aways

Let me leave you with these three take-aways from the study. Chronic Lyme disease patients who improve substantially more often:

  • Use antibiotics as part of their treatment approach
  • Take antibiotics for more than 4 months and often for more than a year
  • Rely on LLMDs to oversee their care

A note of caution: None of this should be taken to suggest that patients should blindly take antibiotics for longer durations to get well. These findings are preliminary – observational studies like this do not have control groups and cannot prove cause and effect. What they can do is suggest approaches that may improve patient outcomes. Patients vary considerably in their treatment response. In chronic Lyme disease treatment, one size does not fit all. In fact, when patients who were not taking antibiotics were ask why, about 25% responded that antibiotics had never worked for them. And some responded that antibiotics “no longer” worked for them. But for now, it seems that doctors should be using individualized care based on their diagnosis and the response of this particular patient to treatments.

The other thing this study suggests is that we have a long way to go to determine optimal care for chronic Lyme patients. For example, why do some patients not respond to treatment and which antibiotics are the most effective?

Personal Reflections

Back in 2004, when I was just beginning to get well after being ill for about five years, I co-authored a commentary with Dr. Raphael Stricker about Lyme disease having “two standards of care.” Before becoming ill, I had a robust career as a lawyer. Thus, it was natural that I would address a legal topic as my first opportunity to give back to a community that had made it possible for me to recover. But at that time, I was thinking that the two standards of care related to the divergent guidelines of the IDSA and the International Lyme and Associated Diseases Society.

With this study, it now seems that the two standards of care still exist, but that they reflect how physicians are treating different stages of the disease. People treated under the IDSA guidelines are mainly those with acute disease—the rash, Bell’s palsy, or a flu-like illness after a recent tick bite. When patients remain ill after the short courses of antibiotics offered by the IDSA, they look for clinicians who are more experienced with treating chronic Lyme disease—typically LLMDs.

A few years ago, someone asked me whether it was important to be treated by an LLMD or if they should see someone who did not focus on Lyme disease. And, although I told the person “you know, I think you might do better with an LLMD,” I had no data to back up that suggestion. Now we do.

If you are a patient who is not enrolled in MyLymeData,  please enroll today. If you are a researcher who wants to collaborate with us, please contact me directly.

The MyLymeData Viz Blog is written by Lorraine Johnson, JD, MBA, who is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk.  If you have not signed up for our patient-centered big data project, MyLymeData, please register now.

MyLymeData Lyme Disease Research

About MyLymeData Lyme Disease Research

MyLymeData is one of the largest patient-driven registries in the nation, with over 13,500 patients enrolled. It was created by patients, is run by patients and will address the issues that Lyme disease patients care about. MyLymeData Viz provides the community with results from MyLymeData. If you are enrolled in MyLymeData, we thank you for providing the data that will accelerate the pace of research in Lyme disease. If you are not enrolled, please enroll today.

You might be interested in more MyLymeData results:

______________________

**Comment**

The results of this study are identical to my experience both as a patient and as an advocate working with many patients. When people solicit my advice, I immediately tell them mainstream medicine will not treat this appropriately. Period. That’s not to say it can’t be used for other side-issues that arise, but for any hope of recovering from tick-borne illness, they should get to an ILADS trained doctor with experience.

It’s truly saddening that polarization continues unabated with this complex illness, but that is the true state of things. I’ve watched similar issues arise with the COVID-19 debacle. Due to severe conflicts of interest our public ‘authorities’ are allowed to have, they completely malign any test or treatment they don’t control and obtain profits from:

https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/

I completely agree with Weiler:  https://madisonarealymesupportgroup.com/2020/09/01/it-is-time-to-reboot-public-health-time-for-a-cdc-niaid-fda-walk-away-movement/

Robert Kennedy identified that the CDC owns over 50 vaccine-related patents:  https://madisonarealymesupportgroup.com/2020/09/11/examining-rfk-jr-s-claim-that-the-cdc-owns-over-20-vaccine-patents-its-actually-over-50/

The CDC owns numerous patents regarding Lyme disease:

https://madisonarealymesupportgroup.com/2019/06/28/who-owns-the-elisa-patents/  (There is also a link within this one showing the many patents our ‘authorities” own)

The Future of Lyme Treatment: Inside the LymeMIND Conference (Oct. 10) – You Can Still Sign Up!

https://rawlsmd.com/health-articles/the-future-of-lyme-treatment-inside-the-lymemind-conference?

The Future of Lyme Treatment: Inside the LymeMIND Conference

by Jenny Lelwica Buttaccio
Posted 10/1/20

Keeping tabs on people with Lyme disease has always been tricky. The reasons are many: Cases of the illness often go unreported or misdiagnosed; the infection presents differently for each person; and some patients go on to develop long-term symptoms despite receiving the 10- to 21-day course of antibiotics recommended by the Centers for Disease Control and Prevention (CDC).

It’s these variables that make tracking and analyzing statistics for Lyme research complicated for any one person or a single group to tackle on their own. Wouldn’t it be helpful, then, if there was a mechanism — a “bigger brain” of sorts — that had the capacity to collect data on chronic Lyme while simultaneously researching it? The answers to creating innovative treatment options and improving patient outcomes just might be found in the field of data science.

Data science is where statistics and computer science meet. Data scientists use many skills such as statistics, programming, and algorithms to mine large sets of data (also called “big data”) in search of patterns.

Although it’s not a new methodology, data mining is relatively new to the Lyme community. It’s an approach being embraced by LymeMIND, an organization with a consortium of members and researchers that share a common goal of furthering the medical and scientific communities’ knowledge of Lyme disease, therapeutic interventions, and diagnostics.

For patients with the tick-borne illness, knowing that cutting-edge science is being applied to something that has inflicted months and years of suffering upon them presents new hope that change is coming to a disease so often fraught with controversy. To learn more about what kind of progress is being made at LymeMIND, we reached out to Savi Glowe, BA, Senior Director of Strategy and Operations in the Hasso Plattner Institute for Digital Health at the Icahn School of Medicine at Mount Sinai.

Savi Glowe speaking on stage at LymeMIND conference

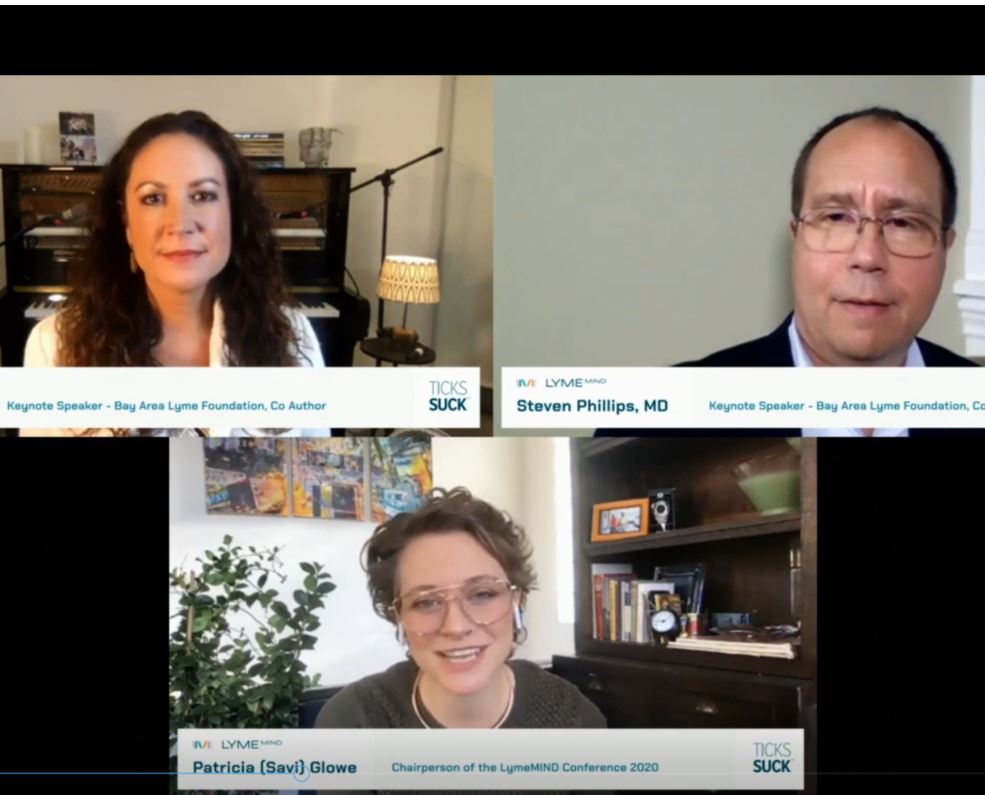
Glowe has been a part of LymeMIND since it was established five years ago, and she’s the chair of the annual LymeMIND conference. With the fifth conference quickly approaching on October 10th, we asked Glowe for an insider’s look at the work LymeMIND is doing, updates from previous years’ speakers, emerging developments that could impact Lyme patients, and the goal of the 2020 presentations. Here is what she had to say:

RawlsMD (RMD): Many people who get involved in Lyme research have a personal connection to the disease. Is this the case for you?

Savi Glowe (SG): Prior to joining the LymeMIND team, I had no personal tie-in to Lyme. I was a member of a team of data scientists looking to solve cool problems using data. The Lyme community was still new to the data science field, and it was exciting to have a novel challenge to tackle.

Since then, I’ve built a personal connection to the work and the patients I’ve encountered. I’ve also been building the LymeMIND conference since its inception. The event began with a desire to get all of our consortia members into the same room for a crash course on Lyme research to better understand the state of the field.

We were surprised when the event sold out and was well-attended by not just researchers and medical students but also patients, caregivers, and advocates. With every LymeMIND event I have managed, I’ve made it a point to create a more open, connected community.

RMD: The idea of “big data” and technology involved in healthcare could seem impersonal or overwhelming to some people. What gap in healthcare for Lyme does LymeMIND fill?

SG: To put it briefly, computers and big data give us a bigger playground. Lyme is a very complex, systemwide disorder. This has become clear to all researchers and doctors studying it. The goal of big data and the work of the LymeMIND is to elucidate a novel understanding of how the disease interacts with other pathogens, host systems, and vectors.

RMD: The 5th annual LymeMIND conference is taking place online due to the pandemic. How did you decide what topics to include this year?

SG: We wanted to keep as many of our topics as possible when we made the switch to a virtual event. The underlying focus of this year’s conference is patients and treatments. This is a change-up from previous years, where we also included panels and presentations on things like ecology and the global impact of the disease.

This year, we’re focused on the day-to-day impacts of the disease on patients and the community. We also made an effort to highlight patient advocacy opportunities and ways to get involved.

RMD: Can you give us any details on updates or breakthroughs that have occured since last year’s presentations?

SG: During the 2020 Conference, Dr. Richard Horowitz will be presenting updated information on his dapsone study, which he spoke on last year. [Dr. Horowitz is medical director of the Hudson Valley Healing Arts Center and founding member of the International Lyme and Associated Diseases Society. Dapsone is a drug historically used to treat leprosy and skin infections.] He’s conducted additional research on a few longitudinal patients and will share more details on those findings.

This year, our Mothers and Children panelists, Holly Ahern, MT(ASCP), Ms. Sue Faber, RN, Dr. Charlotte Mao, and moderator Ms. Phyllis Bedford, will be talking about new CDC recommendations around altered care regimens for pregnant women and young children.

Additionally, many of the researchers and clinicians featured during this year’s event have been working very deeply in COVID-19 over the past months. The broad COVID-19 response and research efforts have been a strong unifying factoramong everyone in the consortium and those participating in this year’s event.

RMD: Regarding COVID-19, do you expect that the same systems you have in place for Lyme, like aggregating data and conducting research, to be applicable to the virus as well? Have you begun to get involved with the COVID-19 patient population yet, particularly those who are long-term ill?

SG: COVID-19 has absolutely impacted the way Lyme researchers and patients look at both diseases. During the conference, Jason Bobe from the LymeMIND team will sit down with Dr. Horowitz and Dr. David Putrino, PhD to discuss commonalities and differences in persistent illnesses and identify opportunities to apply similar strategies in how we research these two diseases. [Dr. Putrino is a physical therapist and Assistant Professor of Rehabilitation Medicine at the Icahn School of Medicine.]

Other members of the LymeMIND consortium have been working on COVID-19 research on multiple fronts this year. For instance, Dr. Avi Ma’ayan, [professor of pharmacological sciences and director of the Mount Sinai Center for Bioinformatics], and the Ma’ayan Lab analyzed tens of thousands of pieces of published research on COVID-19, its life cycle, molecular mechanisms, and potential therapeutic drug compounds to create the COVID-19 Drug & Gene Set Library.

The database contains drug and gene sets related to the virus that users can view, download, analyze, and contribute to. The overall goal of the project is to identify community consensus, make researchers and clinicians aware of the development of new potential therapies as they become available, and allow the research community to work together towards a solution for COVID-19.

RMD: Is there anything you’re really excited about for this year’s event? Anything you can give us the scoop on?

SG: I’m particularly excited to hear our keynote speakers Dana Parish and Dr. Steven Phillips discuss their book Chronic: The Hidden Cause of Autoimmune Pandemic and How to Get Healthy Again. This book has been in development for a couple of years, and I believe it’s a fantastic representation of the bridge between clinicians and patients we hope to encapsulate with LymeMIND and our event.

As one of many team members who has been spending a lot of time diving into COVID-19 work for the past six months, I’m also excited for our COVID-19 in The Context of Lyme Disease panel.

RMD: Is there anything you can add about how LymeMIND is helping to shape the future understanding of Lyme disease?

SG: Our final panel this year, Looking Toward the Future, led by Ben Nemser of The Steven & Alexandra Cohen Foundation, will provide a fantastic look ahead at how the scientific breakthroughs of the consortium will be translated to improved patient care in the coming years. Translational research (research aimed at improving health outcomes) is something I’ve always been excited about, and I hope that our attendees will share in my excitement about what’s to come in this field.

RMD: In previous conferences, you’ve really encouraged participation from the Lyme community by showcasing Lyme artists and musicians and allowing people to share their stories on video. Why has that been important to you and the mission of LymeMIND? With a virtual conference, were able to find ways to include Lyme patients this year as well?

SG: Connecting patients with leaders in research and clinical work has always been at the core of our mission. This disease affects patients in dramatically different ways, and we believe it’s important for them to have a platform for sharing their experiences, questions, and frustrations. When this conversation includes professionals working on the frontlines of this disease, we aren’t just exchanging ideas and stories — we’re building a collaborative communitywhere patients are encouraged to share their experiences and stay informed, and researchers can see the impact of the disease firsthand and work to advance treatments.

This year, LymeMIND 2020 will feature a virtual art exhibit, both on our website and during the event. This year’s event also features two very special call-to-action-presentations that we hope will inspire patients to get involved in new ways:

  • Bonnie Crater, Co-Founder and Board Member at the Center for Lyme Action, a new 501(c)(4) focused on lobbying efforts in Congress, will elaborate on what the Center does and how to get involved.
  • Liz Horn, Principal Investigator at the Lyme Disease Biobank, will talk of the Biobank’s initiative and elaborate on how to donate to the repository.

Also, many of our panels and presentations are followed by a live Q&A session where patient attendees and others will be encouraged to submit questions and participate in the conversation.

RMD: What do you hope conference attendees take away from the conference this year?

SG: As this is our fifth annual conference, a big focus is looking back on how far we’ve come, and looking ahead to where we still have to go. We want our attendees to recognize and reflect on the substantial progress that has been made in understanding this disease, and how expanded collaboration between researchers, patients, and clinicians has played a role in this.

We also want attendees to be aware of challenges we must still overcome as a community. Our hope is that each attendee walks away with a greater understanding of the broader role they can play in the fight to understand the complexity of Lyme disease.

EVENT DETAILS:

 WHEN  Saturday, October 10th, 2020
 WHERE  A virtual event
 FEE  The event is free and open to the public. LymeMIND welcomes patients, advocates, researchers, clinicians, students, and anyone wishing to learn more and discuss the latest concerns and advancements in Lyme disease research.
 REGISTRATION  Interested attendees can register here, and more details on how to join our virtual event will follow.

LYME MIND logo

SCHEDULE OF EVENTS

9:00 am EDT
Opening remarks
by Savi Glowe

9:10 am EDT
Keynote address, “Chronic: The Hidden Cause of Autoimmune Pandemic and How to Get Healthy Again,”
by Steven Phillips, MD, and Dana Parish

10:10 am EDT
“COVID-19- in the context of Lyme disease”
with Jason Bobe, MSc, Richard Horowitz, MD, and David Putrino, PT, PhD

10:25 am EDT
“Insights from Data Mining of Lyme Disease Patients
by LymeMIND” with Avi Ma’ayan, PhD

10:40 am EDT
“Novel Treatments: Making sense of all the treatment options”
with John Aucott, MD, Tania Tyles Dempsey, MD, ABIHM, Andrew Petterson, DO, and Richard Horowitz, MD

11:20 am EDT
“Bartonella and Co-infections”
with Marna Ericson, PhD, Monica E. Embers, PhD, Edward Breitschwerdt, DVM, and Robert Mozayeni, MD

11:50 am EDT
“Lyme Disease – 5 years of progress”
with Jason Bobe, MSc

12:00 pm EDT
“Call to Action: Center for Lyme Action”
with Bonnie L. Crater

12:08 pm EDT
“Lyme Biobank’s tissue repository”
with Liz Horn, PhD, MBIP

12:10 pm EDT
“Looking towards the future”
with Bennett Nemser MPH, MBA, John Aucott, MD, and Brian A. Fallon, MD, MPH

12:25 pm EDT
“LymeX Innovation Accelerator”
with Bennett Nemser MPH, MBA, Eric D. Hargan, JD, BA, ADM Brett P. Giroir, MD, and Kristen Honey, PhD, PMP

12:40 pm EDT
Closing remarks
with Savi Glow

REFERENCES
1. Treatment. Centers for Disease Control and Prevention website. https://www.cdc.gov/lyme/treatment/index.html

Taking on Ticks: Some Lyme Disease Symptoms Can Be Mistaken for COVID-19

https://www.news4jax.com/health/2020/10/01/taking-on-ticks-some-lyme-disease-symptoms-can-be-mistaken-for-covid-19/  News Video Here

Taking on Ticks: Some Lyme disease symptoms can be mistaken for COVID-19

Fever, chills, shortness of breath, fatigue, muscle aches, body aches, headaches, nausea, vomiting — sounds like the symptoms of COVID. But actually, it’s Lyme disease.

And this year is expected to be an exceptionally bad year for ticks. In fact, because more people are spending time outdoors and in the wilderness, due to the pandemic, experts fear more people will come down with Lyme disease. (See link for article)

________________________

**Comment**

The article discusses Olivia Goodreau’s story. Barely able to walk, she saw 51 doctors before she was diagnosed.  She also never saw the tick or the rash, and ONE tick bite caused  5 other diseases.

Mainstream medicine STILL hasn’t embraced these facts that are more common than not.

Key quote:  

“You have migratory muscle pain or migratory nerve pain, tingling, numbness, burning, stabbing. That is the hallmark of Lyme,” said Dr. Richard Horowitz, a board-certified internist at Hudson Valley Healing Arts Center.

Despite increasing stories like this one and worse, hit pieces continue to pour forth denying the severity of the disease and maligning doctors who take a different approach:  https://www.businessinsider.in/science/health/news/reckless-lyme-disease-treatments-are-injuring-and-killing-patients-as-alternative-doctors-get-certified-to-treat-the-illness-report-finds

Do not kid yourself.  There is a political war that’s been going on for over 40 years regarding Lyme/MSIDS.  These public health ‘authorities’ are increasingly coming underwire for conflicts of interest and actual scientific fraud.  They are squirming in their seats.  I was not surprised to see the recent article that again regurgitated the 5 cases of IV antibiotic treatment for Lyme, published in the MMWR, that had poor outcomes. The CDC has a long and sordid history of maligning anything that competes with their lucrative interests:  .https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/

Regarding the 5 cases which were cherry-picked, it was discovered that one of the authors, a CDC epidemiologist, allegedly solicited IDSA doctors for evidence of harm from IV antibiotic treatments, essentially bribing them by offering co-authorship of the report if anecdotes were used. No such solicitation was made for IV treatment success stories – showing complete bias.  There has been hot debate on Lyme treatments for decades. The MMWR paper is only one example of bias which is embedded within the CDC. There are many success stories using IV therapy by a Wisconsin Doctor and IDSA founder who disagreed with his colleagues on how to treat Lyme disease.

The article then drags Dr. Sponaugle through the mud, insinuating that he caused a recent death of a patient because he was “previously flagged for Lyme disease-related malpractice in 2014.”

Again, I write about this common crucifixion of Lyme literate doctors here:  https://madisonarealymesupportgroup.com/2020/04/26/cdc-playbook-learning-from-lyme/

What you must understand is the CDC is a bully and can not and will not have opposition, so they do all in their power to dictate clearly to other doctors the accepted narrative by their draconian “guidelines” and making examples out of those who dare to draw outside the lines (investigations, hefty fines, medical license expulsion and loss of revenue and reputation).  These are not idle threats and have been used over and over worldwide.