Archive for the ‘Activism’ Category

Canadian Data: More Autism Where Vaccine Coverage is Highest

https://worldmercuryproject.org/news/official-canadian-data-show-that-there-is-more-autism-in-regions-where-vaccine-coverage-is-highest/

APRIL 26, 2018

Official Canadian Data Show That There Is More Autism in Regions Where Vaccine Coverage Is Highest

By the World Mercury Project Team

Rates of autism spectrum disorder (ASD) continue to soar worldwide, with average prevalence estimated to be around 1.5% in developed countries. This estimate appears to be spot-on for Canada, which reported in March 2018 that autism (as of 2015) affected 1 in 66 children and youth (1.52%). These numbers place Canada among the “top ten” for autism among North American, European and Asian countries.

The Canadian public had been expecting the Public Health Agency of Canada to release these first-ever nationally representative ASD numbers since 2016. The data come from the National ASD Surveillance System (NASS), which, according to the Public Health Agency, is intended to pinpoint the number of young people diagnosed with ASD “both across regions and over time.” The Agency’s report provides answers on both fronts—showing steady increases in ASD prevalence since 2003 and notable differences across regions—but the document declines to speculate on factors that might account for the regional differences.

What might explain the variation in ASD prevalence within Canada’s borders? … autism prevalence is highest in the Canadian provinces that also have the highest vaccination coverage.

ASD prevalence by province and territory

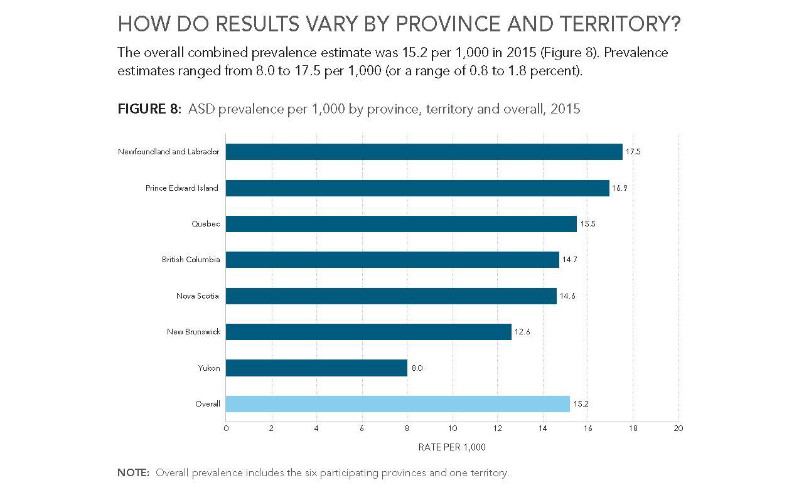
NASS compiles administrative data from the health, education and social services sectors for children and youth (aged 5-17 years) who have a confirmed ASD diagnosis. Seven of Canada’s 13 provinces and territories provided information for 2015, including six provinces (British Columbia, New Brunswick, Newfoundland and Labrador, Nova Scotia, Prince Edward Island and Quebec) and one territory (Yukon). As the figure below shows, ASD prevalence in 2015 varied among the seven regions, with the highest prevalence noted in the three provinces of Newfoundland and Labrador (1 in 57), Prince Edward Island (1 in 59) and Quebec (1 in 65). In comparison, prevalence was substantially lower in the Yukon territory (1 in 125).

The three high-prevalence provinces also provided retrospective data that allowed for an assessment of temporal trends. For the slightly narrower age group of 5-14 year olds, the historical data showed sizeable increases in ASD prevalence from 2003 to 2015 (Prince Edward Island and Quebec) and from 2003 to 2009 (Newfoundland and Labrador):

  • Newfoundland and Labrador: from 6 to 19.6 per 1,000 (a 227% increase)
  • Prince Edward Island: from 5 to 17.7 per 1,000 (a 254% increase)
  • Quebec: from 3.5 to 15.7 per 1,000 (a 349% increase)

Explaining the regional differences

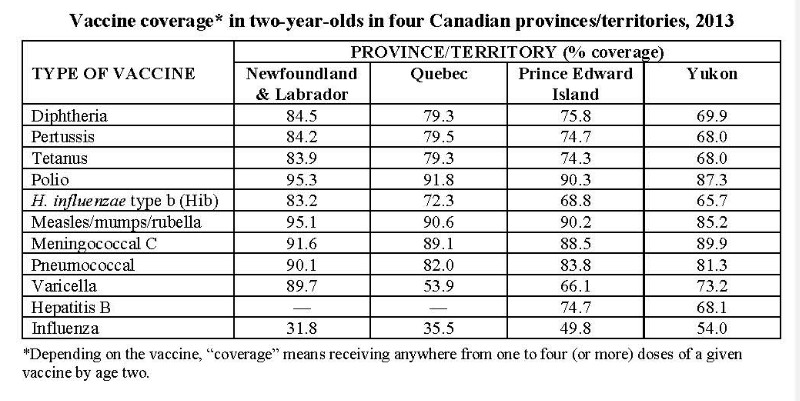
What might explain the variation in ASD prevalence within Canada’s borders? The NASS report does not offer any comments. However, an observant health practitioner in British Columbia has noticed a compelling parallel: autism prevalence is highest in the Canadian provinces that also have the highest vaccination coverage. This evidence comes from a 2013 survey carried out by the very same Public Health Agency of Canada, which examined vaccine coverage by province/territory and type of vaccine (see table). The survey showed that coverage by age two was generally lower (with a few exceptions) in Yukon territory than in the three high-autism provinces. For Newfoundland/Labrador and Quebec, the percentage point difference in vaccine coverage was anywhere from five to fifteen percentage points higher than in Yukon; Prince Edward Island’s lead in vaccine coverage compared to Yukon was less substantial.

Correlation is not causation but…

Any researcher worth their salt knows that while correlation is not the same as causation, a plausible association between two variables is often an important clue worth investigating. The substantially lower ASD prevalence in a region that happens to have markedly lower vaccine coverage is one such clue. Another strand of evidence that simply cannot be chalked up to coincidence are the tens of thousands of parental reports of children regressing into autism after receiving one or more vaccines. Unfortunately, Canadian parents who suspect that their autistic child was vaccine-injured have nowhere to turn, because Canada remains “one of few western countries that denies the reality of vaccine injuries and provides no avenue whatsoever to compensate vaccine injury victims and their families.” It would behoove Canada’s public health officials to take a closer look at their own data and start taking meaningful steps to prevent the country’s ASD numbers from climbing still further.

Note:  The CDC is due to release its latest ADDM surveillance numbers for the U.S.  Will our federal health agencies continue to downplay the numbers’ significance, as they have done each time the data show a rise in ASD prevalence? Or will they finally sound an alarm and make it a top priority to find out what is causing this epidemic in our children? 

_______________

For more:  https://madisonarealymesupportgroup.com/2018/06/01/immunoexcitotoxicity-as-the-central-mechanism-of-etiopathology-treatment-of-autism-spectrum-disorders-a-possible-role-of-fluoride-aluminum/

https://madisonarealymesupportgroup.com/2018/03/21/congress-receives-vaccine-safety-project-details-since-the-cdc-fda-ignore-their-own-data-and-proclaim-vaccines-do-not-cause-autism/

https://madisonarealymesupportgroup.com/2017/09/21/aluminum-flawed-assumptions-fueling-autoimmune-disease-and-lyme/

https://madisonarealymesupportgroup.com/2017/09/19/autism-aluminum-adjuvant-link-corroborated/

https://madisonarealymesupportgroup.com/2018/04/09/a-tale-of-3-metals-the-fate-of-western-civilization-what-we-can-do-about-it/

What You Need to Know About Bella Hadid’s Lyme Disease Diagnosis

https://www.cosmopolitan.com/entertainment/a21286398/bella-hadid-lyme-disease/

What You Need to Know About Bella Hadid’s Lyme Disease Diagnosis

Everything she’s said about her illness, and how she treats it.

GETTY IMAGES

Like her mother Yolanda Hadid, supermodel Bella Hadid has Lyme disease — a tick-borne illness that leads to exhaustion, joint pain, and fatigue (among other symptoms). Here’s what we know about Bella’s experience living with Lyme disease.

Yolanda Revealed That Bella Had Lyme Disease During an Episode of Real Housewives of Beverly Hills

The moment came with a lot of drama: Yolanda’s castmates were less than kind about her own struggle with Lyme disease, and they questioned whether or not Bella and her brother Anwar were truly suffering from it, too.

“Bella was diagnosed with Lyme disease and co-infections about three years ago,” explained Yolanda during the episode. “And Anwar shortly six months after that.”

Real Housewives mainstay Lisa Vanderpump sparked drama when she implied that Bella’s father Mohamed Hadid had told her that his children were fine — the not-so-subtle implication being that Yolanda wasn’t telling the truth about Bella and Anwar’s diagnoses.

Mohamad ended up issuing a statement in which he clarified, “I can only imagine that my response to a question asking how my kids are doing with ‘fine’ was misconstrued. I have too much respect for all five of my children to speak about them publicly … in a restaurant or otherwise. I won’t speak further on something that should now be put to rest.”

Bella Probably Got Lyme Disease on the Farm Where She Grew Up

Bella and her siblings spent the early part of their childhood on a farm, where Yolanda reckons they were bit by a tick. “There are millions of cases worldwide,” she explained on Real Housewives. “We lived on a horse ranch, we had ticks everywhere, every day of their life.”

She also took to her personal blog to explain that Bella “had to give up her lifelong dream of having a professional riding career and a shot at the Olympics due to her severe symptoms and inability to ride. This was the biggest heartbreak of her life and an extremely sensitive subject for her.”

What Bella Has Said About the Disease, and How She Treats It

The supermodel hasn’t shied away from talking about her health with the public, telling Evening Standard that “it was a dark time” when she first got sick. “I was exhausted all the time. It affected my memory so I suddenly wouldn’t remember how to drive to Santa Monica from Malibu where I lived. I couldn’t ride. I was just too sick. And I had to sell my horse because I couldn’t take care of it.”

She also told Porter, “I couldn’t get out of bed for six days. And my brain would get all foggy, and I couldn’t see. That was the hardest time of my life.”

Bella is intolerant of the antibiotics that are typically used to treat Lyme disease, so she takes alternative medicine. At the time of the Evening Standard interview in 2015, she explained that she still had Lyme “in all my joints and it goes up to my brain.”

Bella Was Honored at the Global Lyme Alliance and Gave a Moving Speech

During her speech at the 2016 gala, the supermodel spoke candidly about the effects of her illness: “Life isn’t always what it looks like on the outside, and the hardest part of this journey is to be judged by the way you look instead of the way you feel.” Bella added that she felt like her “teenage years were taken” from her.

She dedicated the award to “all the teenagers out there that have really gone through what I’m going through and have suffered from this disease without an end in sight.”

To find out more about Lyme disease, head here.


An Anthropologist’s View of Lyme Disease and Suicide

https://www.lymedisease.org/anthropologist-lyme-suicide/

An anthropologist’s view of Lyme disease and suicide

jackson-photos-300x201

By Aaron J. Jackson

It’s been almost a year since I tried to kill myself.

As a doctoral student living in the leafy suburb of Brookline, Massachusetts, in 2015, I chanced upon a tick—a tiny vampire the size of a poppy seed—that changed my life forever and nearly brought it to an end.

After being bitten by the tick, I was plagued with full-body joint pain, muscle twitching, night-time seizures, cardiac abnormalities, depression, fatigue, and other neurological disturbances. Early on, this confluence of symptoms confounded doctors.

Upon hearing my account, one neurologist shook his head. “That doesn’t make any sense,” he said, before suggesting that my caffeine intake might be responsible.

I was told repeatedly by various doctors that the mysterious ailment darkening my existence was psychological in nature, most likely due to stress. It took 12 months before I was finally diagnosed with Lyme disease.

But little changed after the diagnosis, contrary to what I had naively expected. My doctor prescribed four weeks of antibiotics and told me that if the medication didn’t work then it wasn’t Lyme. The antibiotics didn’t work.

Exiled from my body
Suddenly, I was alone—exiled from my body and others. My disease has been exacerbated by the social consequences of having a complex chronic condition. When an illness isn’t medically recognized or refuses to progress in a straightforward way toward better health, those around you often grow impatient or suspicious. People stop asking how you are or act as if your failure to recover is somehow a personal weakness. These silences and reactions can drive the chronically ill into isolation, despair, and existential confusion.

Sufferers are also often alienated by the unhealthy dynamics that characterize many doctor-patient interactions in the Western world today. The power imbalance between who can authoritatively describe what is going on in the body and who can’t has a deep impact on how illness is experienced and navigated.

Doctors hold the authority to determine which bits of a patient’s story are useful, which interpretations to act on, and which diagnostic tests are made available. The doctors and specialists I consulted consistently interrupted me, refused to order tests, and denied the severity of my symptoms. The subtle and oftentimes brutal rejection of my experiential knowledge and suffering slowly anesthetized me against hope.

I can see why this happens. Doctors face time and financial constraints, heavy workloads, and distrusting and contentious patients. They are taught to prioritize their technical capabilities and are faced with the challenging task of combing through irrelevant information for what is medically relevant. As a way to cope with a daily barrage of problems and complaints—and the deaths of some of their patients—some physicians become callous and numb.

The practice of medicine in the 21st century is a complex affair. But even under such conditions, appreciating the singularity of an individual’s life is essential to providing authentic care and good medicine. As the late neurologist and author Oliver Sacks wrote, practical scientific medicine and existential medicine are separate but inseparable—“not contradictory but complementary.”

Paternalism?
Paternalistic relationships between doctors and patients in today’s medical system cause harm to many individuals. For me, they delayed my diagnosis, protracted my illness, denied me a sense of being validated and understood, and conspired to push me deeper into the depths of my despair. The practice of modern medicine doesn’t have to be this way.

The bacterium responsible for Lyme disease has a long history in North America. Katharine Walter, who studies infectious diseases at Stanford University, and her team recently collected and sequenced 148 genomes of the microorganism and found that it has cycled through forests for at least 60,000 years.  https://natureecoevocommunity.nature.com/users/61817-katharine-walter/posts/19688-bacterial-genomes-reveal-ancient-history-of-lyme-diseasebacterial-genomes-reveal-ancient-history-of-lyme-disease-in-north-america-in-north-america

But it was only as recently as 1982 that medical entomologist Willy Burgdorfer identified the tiny corkscrew-shaped bacterium mysteriously afflicting some residents of Lyme, Old Lyme, and East Haddam, Connecticut, and Long Island, New York. In recognition of the discovery, the bacterial pathogen was christened in his name: Borrelia burgdorferi.
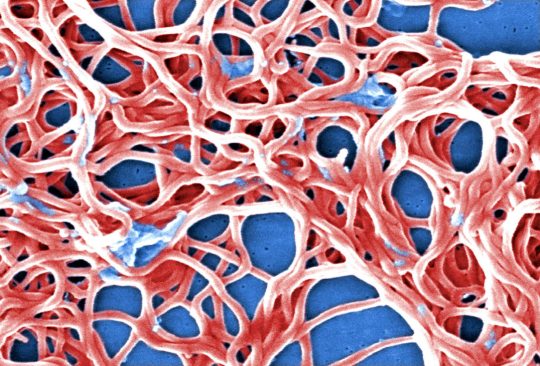
Digitally colorized scanning electron micrograph borrelia burgdoThe Borrelia burgdorferi pathogen causes Lyme disease. Janice Haney Carr/Pixniov

The Centers for Disease Control and Prevention (CDC) receives reports of approximately 30,000 cases of Lyme disease annually in the United States.

However, the organization estimates that about 300,000 people contract the illness each year. A variety of factors contribute to this significant disparity—but a dearth of reliable diagnostic tests is a key part of the problem.

The CDC recommends a two-tiered blood test to spot antibodies against the B. burgdorferi bacteria.

But this test is notoriously unreliable, in part because it was developed to track a group of Lyme patients, rather than for clinical diagnosis. Yet this inadequate test became the national standard for both doctors and insurance companies. As a result, there are many patients whose tests come back negative even though they have Lyme disease.  https://www.scientificamerican.com/article/tests-for-lyme-disease-miss-early-cases-mdash-but-a-new-approach-might-help/

IDSA vs. ILADS
After overcoming the first hurdle of diagnosis, most patients face a treatment protocol that is also controversial. According to the Infectious Diseases Society of America (IDSA), a course of up to 28 days of antibiotics is recommended for those diagnosed with Lyme.  http://www.idsociety.org/Updated_Guidelines_on_Diagnosis_Treatment_of_Lyme_Disease/

Yet according to the International Lyme and Associated Diseases Society, a short course of antibiotics is often insufficient for treating Lyme.  http://www.ilads.org/lyme/treatment-guideline.php  And some clinicians have found that longer treatments benefit patients.  https://academic.oup.com/cid/article/45/2/149/420106

While the IDSA does acknowledge the enduring pain of some sufferers and instances of “post–Lyme disease syndrome,” there is a great deal of controversy over the use of longer-term courses of antibiotics.

Research has shown https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3636972/ that Lyme spirochetes can take hold in a patient, even in the face of aggressive antibiotics, making Lyme a “recalcitrant and chronic relapsing infection.” Identifying those patients and how best to treat them remains a challenge, making chronic Lyme a complicated and disputed clinical beast.
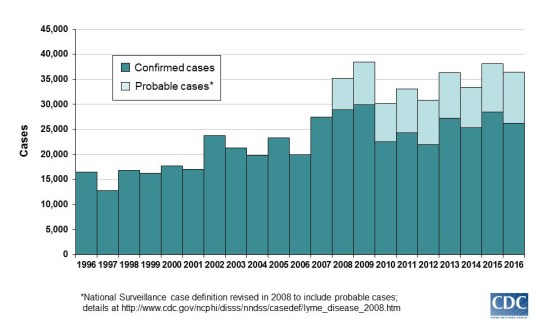
03-Casenumbers-graph-1996-2016

Reported cases of Lyme disease have increased since 1996—but these Centers for Disease Control and Prevention statistics only capture about 10 percent of all estimated cases of the disease.
Centers for Disease Control and Prevention

The IDSA’s recommendations are particularly controversial given an antitrust investigation undertaken by the attorney general of Connecticut.  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2901226/

In 2008, that investigation reported that the IDSA did not perform a conflict-of-interest review https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2435453/ for any of the panelists on the recommendation committee, and that several panelists had financial connections to insurance companies and Lyme vaccine manufacturers. Those who acknowledge the existence of chronic Lyme disease were blocked from appointment to the panel.

All this leaves many people like myself to fend for ourselves as we suffer the horrors of unrecognized or misunderstood illness. It’s hard to say how many around the world have chronic Lyme disease—but we need to recognize the potentially serious and disabling nature of Lyme and how it has been mismanaged by the U.S. medical system and the government. It’s critical we increase research for better diagnosis and treatment.

After a year and a half, I experienced a brief period of remission. I resumed my regular activities, spent time with my children, and started training again. (I was a kickboxer in my former life.) But the reprieve only lasted a few months. Before long, I was bedridden again by numbness, nerve pain, tremors, and bone-deep exhaustion.

One night, two years into my illness, I experienced heart pains that dropped me to my knees. My partner rushed me to the hospital, and the medical staff decided to keep me overnight. In the morning, the cardiologist dismissed my blood pressure of 144 as “slightly elevated.” He struck me as aloof, even sneering.

Statistical fragment
In my own eyes, I was a boxer with a normal resting heart rate of 55 and a blood pressure of 110—and I had an extreme and unusual set of symptoms that were cause for concern. But to him, I was just a statistical fragment; he saw no reason to give a second thought to my claim that this number was abnormally high for me. While interacting with him, I felt like I had lost an essential part of myself. The “healthy boxer” loomed behind me like a breathing phantom.

Shortly after this clinical encounter, my mental state and behaviors changed. I began spending considerable time picturing what my absence would look like, convincing myself that my loved ones would be better off without me. I didn’t want to end my life. I wanted to escape the terminal collapse of my world.

The sky was pale white with indifference on the morning I tried to kill myself. When I didn’t answer my phone, my partner instinctively felt that there was something wrong.

She headed home and called an ambulance. I spent the next weeks in a mental health facility in a state of depressive catatonia. I don’t remember much beyond the green walls, gray carpet, my neighbor’s singing sessions in the shower, and the smell of cigarette smoke.

I knew then, as I do now, that I had fallen prey to something darker, more powerful, and much more ancient than myself.

For the rest of my life, I will struggle to incorporate my attempted suicide into my sense of self. Trying to explain the medical, psychological, and sociocultural conditions surrounding it has been one way of working to come to terms with my illness and related experiences.

Connection between Lyme and suicide
Suicide and suicidal thoughts are not unusual in the village of the sick. It is estimated that around 44,000 people killed themselves in 2015 in the United States https://www.cdc.gov/nchs/fastats/suicide.htm; as many as 1,200 suicides annually might be attributed to Lyme and associated diseases, according to a study that scaled up one doctor’s chart review of more than 250 patients with Lyme.  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5481283/

There are plausible biological explanations for suicide and suicidal thoughts among those with Lyme: Studies have shown strong connections between brain inflammation, immune response, and suicide.  https://www.elsevier.com/about/press-releases/research-and-journals/inflaming-the-drive-for-suicide3

But just as important are psychological factors associated with the combination of pain, suffering, and frustration patients experience with inadequate care. In 2015, a 41-year-old man who likely had Lyme for nine years before finally being diagnosed with the disease took his own life. The anxiety and pain he experienced were relentless, his fiance said.  https://www.poughkeepsiejournal.com/story/news/health/lyme-disease/2017/07/19/lyme-disease-suicide-bransfield-study/483959001/

Gender differences
My own experiences with Western medicine confirm what many others have argued: Inadequate care is in part shaped by biased research, power imbalances, and mistaken perceptions. Biological differences between men and women, for example, are known to impact diagnostics and treatment.  https://theconversation.com/au/topics/gender-medicine-39178

The disproportionate study of men in clinical trials and other studies has skewed our medical knowledge. For instance, heart attacks are sometimes missed entirely in women because women are less likely than men to experience chest pain as a major symptom.  https://www.theatlantic.com/health/archive/2015/10/heart-disease-women/412495/

Inaccurate and gendered assumptions on the part of medical practitioners also impact the degree of autonomy and credibility that individuals are granted when recounting their illness experience. I have often wondered if stress was presumed to be at the helm of my alleged psychological disorder because I am a man—just as women are more often diagnosed with “conversion disorders,” formerly referred to as hysteria, in cases where psychic turmoil is attributed to unexplainable bodily dysfunction.  https://www.bbc.com/news/stories-41888146
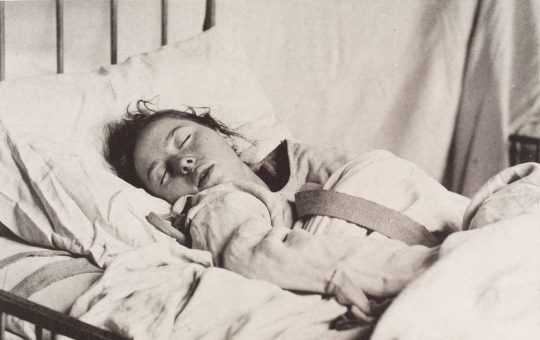
05-Sleep-Hysteria-Wellcome-Collection-1076x678In this photo from a 19th-century mental hospital, a woman diagnosed with hysteria-induced narcolepsy sleeps wearing a straitjacket.  Wellcome Collection

Those with inexplicable conditions often face a similar bias: a tendency for some doctors to dismiss out of hand individuals who have complex and unusual cases.  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5324700/

In cases of controversial illnesses, such as myalgic encephalomyelitis (a.k.a. chronic fatigue syndrome), patients can be belittled as “malingerers,” https://www.theguardian.com/society/2002/mar/30/health.lifeandhealth just as those with Lyme disease are sometimes disrespectfully called “Lyme loonies.”  https://www.poughkeepsiejournal.com/story/news/health/lyme-disease/2014/03/26/so-called-lyme-wars/6907209/

I am not suggesting these practices and behaviors are systematically carried out on purpose or maliciously, but rather that they are based on tacit assumptions that influence the ways medical practitioners act.

The doctors I met often struck me as arrogant and unwilling to really sit and listen, making it easy for the complexities surrounding my illness to be misconstrued or not even conveyed, despite my desire to communicate them. Perhaps these doctors would have blamed me for being a bad oral historian.

I grew increasingly nervous and insecure as doctors asserted their patriarchal authority. I developed iatrophobia, a deep dread of doctors. And I started to see myself as someone damaged, with an unreliable testimony.

My body, my medium for experiencing the world, was transmogrified during these clinical encounters into something without personal meaning. Doctors overlooked what my illness felt like to me and how I experienced it within the context of my life, foreclosing other possible lines of therapeutic options—and my need for understanding and care.

Medical empathy
I wonder what would have happened if I had met doctors early on in my illness who were committed to listening empathetically and to practicing a style of medicine informed by humility, receptivity, and compassion. I don’t believe such an approach requires additional resources or time (although those would help), just an adherence to a different set of social and cultural values.

Critics sometimes claim that doctors who recognize and treat chronic Lyme disease are doing so dishonestly, exploiting others’ suffering for their own gain.  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4489928/  Maybe there are some who do. But I believe many of these doctors, who risk sanctions by medical boards for treatment strategies that break conventional protocols, are practicing existential medicine: They acknowledge that patients need not just answers but also understanding and comfort. For them, medical care is not only about easing suffering but about becoming an empathetic witness to suffering.

At the moment, I am in a better place. Hyperthermia treatment at a clinic in Germany helped ease some of my symptoms. But I still struggle with debilitating symptoms from my illness and large debts from the costs of seeking treatment. I have had to shed some of my identities that were shattered by my illness and that once defined who I was. I have been forced to understand myself—and give meaning to the world and to my relationships—in new ways. Writing about my illness has helped with this ongoing process of self-remaking.

Almost three years after my tick bite, I now inhabit a space of hope that is every bit as tenuous as the future it anticipates. I know how fragile life is in the throes of illness and how easily it can be clipped with the shears of domination and misunderstanding.

Aaron J. Jackson is a doctoral candidate researching worlds of care, disability, and illness. Follow him on Twitter @Kodacruz. This work first appeared on SAPIENS under a CC BY-ND 4.0 license:  https://creativecommons.org/licenses/by-nd/4.0/

Read the original here:  https://www.sapiens.org/body/chronic-lyme-disease-treatment/


Tick-Borne Disease Working Group Subcommittee Reports – Comments due by June 18

https://www.hhs.gov/ash/advisory-committees/tickbornedisease/reports/index.html

Reports

The Tick-Borne Disease Working Group (Working Group) is required to submit a report on its activities and any recommendations to the HHS Secretary and Congress every two years. The first report is due December 2018.

The six subcommittees of the Working Group prepared reports to inform the Working Group and its 14 voting members. These reports offer insights into gaps, opportunities and potentials actions to be considered by the Working Group for the report to Congress and HHS Secretary. 

Report of the Access to Care Services and Support to Patients Subcommittee

Report of the Disease Vectors, Surveillance, and Prevention Subcommittee

Report of the Other Tick-Borne Diseases and Co-Infections Subcommittee

Report of the Pathogenesis, Transmission and Treatment Subcommittee

Report of the Testing and Diagnostics Subcommittee

Report of the Vaccine and Therapeutics Subcommittee


You may make comment either by writing or verbally by June 18th, for the next meeting on June 21st.

Go here for the June 21st meeting.
https://www.hhs.gov/ash/advisorycommittees/tickbornedisease/meetings/index.html


Depression: the Radical Theory Linking it to Inflammation

https://www.nature.com/articles/d41586-018-05261-3

BOOKS AND ARTS 29 MAY 2018

Depression: the radical theory linking it to inflammation

Alison Abbott considers a persuasive case for the link between body and mind.

d41586-018-05261-3_15785092
Collage of coloured sagittal MRI scans of the human brain.
Magnetic resonance imaging scans of the human brain.Credit: Simon Fraser/SPL/Getty

The Inflamed Mind: A Radical New Approach to Depression Edward Bullmore Short (2018)

Depression affects one in four people at some time in their lives. It is often difficult to treat, in part because its causes are still debated. Psychiatrist Edward Bullmore is an ardent proponent of a radical theory now gaining traction: that inflammation in the brain may underlie some instances. His succinct, broad-brush study, The Inflamed Mind, looks at the mounting evidence.

The book outlines a persuasive case for the link between brain inflammation and depression. Bullmore pleads with the medical profession to open its collective mind, and the pharmaceutical industry to open its research budget, to the idea. He provides a current perspective on how the science of psychiatry is slowly emerging from a decades-long torpor. He sees the start of a shift in the Cartesian view that disorders of the body ‘belong’ to physicians, whereas those of the more ‘immaterial’ mind ‘belong’ to psychiatrists. Accepting that some cases of depression result from infections and other inflammation-causing disorders of the body could lead to much-needed new treatments, he argues.

In 1989, during his clinical training at St Bartholomew’s Hospital in London, Bullmore encountered a patient whom he calls Mrs P, who had severe rheumatoid arthritis. She left an indelible impression. He examined her physically and probed her general state of mind. He reported to his senior physician, with a certain pride in his diagnostic skill, that Mrs P was both arthritic and depressed. Replied the experienced rheumatologist dismissively, given her painful, incurable physical condition, “You would be, wouldn’t you?”

Mrs P is a recurring motif, as is the rhetorical question. Bullmore draws on more than two millennia of medical history — from ancient Greek physician Hippocrates to the work of neuroanatomist and 1906 Nobel laureate Santiago Ramón y Cajal — to illustrate his points. At times they seem like intellectual meanderings, but these passages also show how medical science often progresses by means of bold theories that break away from received wisdom.

After his training, Bullmore specialized in psychiatry, and quickly experienced its limitations. He describes his growing awareness of how poorly science has served the field, using the development of selective serotonin reuptake inhibitors (SSRIs) as a prime example.

That long and winding road began with the antibiotic iproniazid. It was discovered through scientific logic: by screening chemicals for their ability to kill Mycobacterium tuberculosis in the test tube and in mice. Iproniazid transformed the treatment of tuberculosis in the 1950s. Patients clawed back from the jaws of death exhibited euphoria — well, you would, wouldn’t you? — and the drug was soon launched as an antidepressant. Soon the theory emerged (based more on supposition than evidence, says Bullmore) that its psychiatric effects were the result of boosting the neurotransmitters adrenaline and noradrenaline. Drug developers began to focus on neurotransmission more broadly.

Prozac (fluoxetine), which boosts serotonin transmission, was launched in the mid-1980s, and many pharmaceutical companies quickly followed with their own SSRIs. It seemed to be the revolution psychiatrists had been waiting for. But it soon emerged that only a modest subset of patients benefited (estimates based on trials vary widely). That is unsurprising in retrospect, with the new appreciation that depression can have many causes. Bullmore holds that the emergence of SSRIs bypassed scientific logic. The serotonin theory, he writes, is as “unsatisfactory as the Freudian theory of unquantifiable libido or the Hippocratic theory of non-existent black bile”. He notes that, after SSRIs failed to live up to the hype, time once again stood still for psychiatry.

Bullmore recalls a teleconference in 2010, when he was working part-time with British pharmaceutical giant GlaxoSmithKline. During the call, the company announced it was pulling out of psychiatry research because no new ideas were emerging. In the following years, almost all of ‘big pharma’ abandoned mental health.

Then a window seemed to open — one that shed a different light on the plight of Mrs P. Some of the textbook certainty that Bullmore had learnt by rote at medical school started to look distinctly uncertain.

In particular, the blood–brain barrier turned out to be less impenetrable than assumed. A range of research showed that proteins in the body could reach the brain. These included inflammatory proteins called cytokines that were churned out in times of infection by immune cells called macrophages. Bullmore pulls together evidence that this echo of inflammation in the brain can be linked to depression. That, he argues, should inspire pharmaceutical companies to return to psychiatry.

It seems unfair that someone struck down by infection should have depression too. Is there a feasible evolutionary explanation? Bullmore hazards that depression would discourage ill individuals from socializing and spreading an infection that might otherwise wipe out a tribe.

Other brain disorders might turn out to be prompted or promoted by inflammation. An exciting link with neurodegenerative diseases, including Alzheimer’s, is also being studied (see Nature 556, 426–428; 2018). But we need to learn from the rollercoaster history of brain research, and keep expectations in check. Beneath his bombastic enthusiasm, Bullmore acknowledges this, too.

Nature 557, 633-634 (2018)

doi: 10.1038/d41586-018-05261-

_________________

**Comment**

Lyme/MSIDS patients are often depressed.  I certainly was.  I found the worse I felt physically, the worse I felt mentally.  My mental state improved on appropriate anti-microbial treatment right along with my physical state.

I wholeheartedly believe the reason we are seeing suicides with Lyme/MSIDS is because patients are being abused at every juncture.  They are not believed and live an isolated existence where they can not speak honestly to those closest to them.  If you find yourself in this situation, please, for your mental health, get to a support group.  Once inside those doors you will be affirmed, believed, and listened to.  Don’t have a support group?  Start one!  With an estimated 1 million to contract Lyme/MSIDS this year (2018) there’s going to be a whole lot more of us!  https://madisonarealymesupportgroup.com/2018/02/24/one-million-predicted-to-get-lyme-in-2018-in-the-u-s/

For some other info linking infections to depression:  https://madisonarealymesupportgroup.com/2017/10/03/treat-the-infection-psychiatric-symptoms-get-better/

https://madisonarealymesupportgroup.com/2017/10/01/panspandas-steroids-autoimmune-disease-lymemsids-the-need-for-medical-collaboration/

https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/

https://madisonarealymesupportgroup.com/2017/01/17/lymemsids-and-psychiatric-illness/

https://madisonarealymesupportgroup.com/2017/10/08/misdiagnosed-how-children-with-treatable-medical-issues-are-mistakenly-labeled-as-mentally-ill/

https://madisonarealymesupportgroup.com/2017/06/30/child-with-lymemsidspans-told-by-doctors-she-made-it-all-up/

https://madisonarealymesupportgroup.com/2018/06/04/ld-diagnosis-took-forever-because-of-mental-health-stigma/

https://madisonarealymesupportgroup.com/2018/04/07/young-woman-with-lyme-takes-her-life/