A new study from medical researchers at UCLA and Stanford University found the chances of contracting or dying from coronavirus are much lower than previously thought. One America’s Pearson Sharp has the details.
‘We get these really large counts of deaths, and very large counts of cases, and they all seem to be growing, but what does that matter to me is not really answered by those questions.’
‘Even at [the pandemic’s] peak, except for very few places, the severe events were pretty rare events.
‘The perception given all of the data and the images and the emergencies, the war metaphors, the uncertainty, the lack of control, these were all factors that I think elevated the perception of risk. Dr Rajiv Bhatia
COVID-19 fatality rate “worst miscalculation in the history of humanity” says PhD candidate in epidemiology
August 22, 2020 | John C. A. Manley
Ronald B. Brown PhD
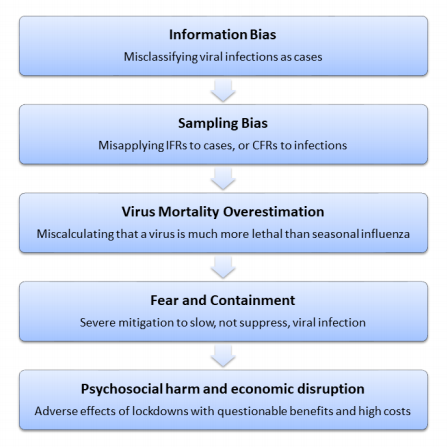
This month, Dr. Ronald B. Brown had a daring paper published in Disaster Medicine and Public Health Preparedness, conservatively entitled Public health lessons learned from biases in coronavirus mortality overestimation.
“The subject of this article is disruptive, to say the least, although it is not as obvious from the title,” Dr. Brown told me in an email. “The manuscript cites the smoking-gun, documented evidence showing that the public’s overreaction to the coronavirus pandemic was based on the worst miscalculation in the history of humanity, in my opinion. My manuscript underwent an intensive peer-review process. You are the first media guy who has responded to my invitation.”
Dr. Stella Emmanuel Cleared by Texas Medical Board for Complaint while Real Criminal Doctors Still Free After Murdering Millions
Comments by Brian Shilhavy Editor, Health Impact News
Houston physician Dr. Stella Emmanuel, part of the Frontline Doctors group that went to Washington D.C. last month, posted a copy of a letter she received from the Texas Medical Board to her Twitter account this week showing that the complaint against her had been dismissed.
The complaint was allegedly filed against her because she had a 100% success rate curing hundreds of COVID patients with hydroxychloroquine (HCQ), a drug with a 65-year safe history that Anthony Fauci, a bureaucrat politician doctor who does not treat patients, claims is ineffective against COVID.
The FDA also refuses to allow the drug’s use in a wide variety of settings for treating COVID patients.
Dr. Emmanuel is not alone in her reporting of success in treating COVID patients with HCQ. Hundreds of doctors around the world are reporting the same thing.
This has to be the biggest medical scandal in the history of the United States. These doctors are all claiming that no one has to die from COVID because their treatment of using HCQ, zinc, and an antibiotic has a near 100% success rate in the early stages of the illness.
From left to right: National Institute of Allergy and Infectious Diseases Director Anthony Fauci, CDC Director Robert Redfield, FDA Commissioner Stephen Hahn, Assistant Secretary for Health Brett Giroir. Image source CSPAN.
That makes those in government office handling the COVID response and denying life-saving treatments MASS MURDERERS.
Persistent infection a Religious Belief? WG Co-Chair Says Yes
SEP 3, 2020 —
The following letter was sent to Eugene Shapiro, member of the Tick-Borne Disease Working Group and defendant in the Lisa Torrey vs IDSA racketeering lawsuit with Cc: to the Group. I have asked the TBDWG to acknowledge this letter, to be included in the records and request a response from Shapiro and/or Dr. Walker, Chair of the Working Group. Perhaps you could prompt the TBDWG to demand a response from Shapiro and Walker who believe persistent infection is a “Religious Belief.”
Email: tickbornedisease@hhs.gov
———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net> To: eugene shapiro <eugene.shapiro@yale.edu>, “tickbornedisease@hhs.gov” <tickbornedisease@hhs.gov> Cc: (98 Undisclosed recipients) Date: 09/02/2020 11:28 AM Subject: Contentious 9 Hour WG Meeting: Persistent infection a Religious Belief? WG Co-Chair Says Yes
“Dr. Walker said there is “emphasis on belief…almost religious belief that it’s a persistent infection” and at various times said they probably didn’t have Lyme to start with.”
Sept 2, 2020
Yale New Haven Children’s Hospital 1 Park Street Ste West Pavilion – 2nd Floor New Haven, CT 06504 Attn: Eugene Shapiro, MD
Dr. Shapiro,
Below is an excerpt from my recent letter to the editor published in the BMJ. Could you please explain your motivation for suppressing evidence of persistent infection after extensive antibiotic treatment and then claiming there is no evidence?
Please hit “reply all” as I have carbon copied the Tick-Borne Disease Working Group. I am sure everyone is interested in your response.
In reference to “persistent infection after extensive antibiotic treatment,” an astute fifth grader with access to PubMed could find the following short list of publications: (there are actually hundreds) [1]
I would like to call attention to the following 1995 study from Stony Brook Lyme clinic. I understand the patient received thirteen spinal taps, multiple courses of IV and oral meds, and relapsed after each one, proven by CSF antigens and/or PCR. The only way this patient (said to be a physician) remained in remission was to keep her on open ended clarithromycin- was on it for 22 months by the time of publication.
aDepartment of Medicine, bDepartment of Neurology, and cDivision of Infectious Diseases, Albert Einstein College of Medicine, and dDepartment of Neurology, State University of New York at Stony Brook, New York, NY., USA
We report an unusual patient with evidence of Borrelia burgdorferi infection who experienced repeated neurologic relapses despite aggressive antibiotic therapy. Each course of therapy was associated with a Jarisch-Herxheimer-like reaction. Although the patient never had detectable free antibodies to B. burgdorferi in serum or spinal fluid, the CSF was positive on multiple occasions for complexed anti-B. burgdorferi antibodies, B. burgdorferi nucleic acids and free antigen. ___________________________________________________
Let’s review another early publication where persistent infection was recognized:
May 13, 1988
2. Fatal Adult Respiratory Distress Syndrome in a Patient With Lyme Disease Michael Kirsch, MD; Frederick L. Ruben, MD; Allen C. Steere, MD; et al
A dry cough, fever, generalized maculopapular rash, and myositis developed in a 67-year-old woman; she also had markedly abnormal liver function test results. Serologic tests proved that she had an infection of recent onset with Borrelia burgdorferi, the agent that causes Lyme disease. During a two-month course of illness, her condition remained refractory to treatment with antibiotics, salicylates, and steroids. Ultimately, fatal adult respiratory distress syndrome developed; this was believed to be secondary to Lyme disease.
The patient had active, systemic Borrelia burgdorferi infection and consequent Lyme hepatitis, despite antibiotic therapy. Spirochetes were identified as Borrelia burgdorferi by molecular testing with specific DNA probes.
Rudenko and colleagues reported culture confirmation of chronic Lyme disease in 24 patients in North Carolina, Florida, and Georgia. All had undergone previous antibiotic treatment
5. DNA sequencing diagnosis of off-season spirochetemia with low bacterial density in Borrelia burgdorferi and Borrelia miyamotoi infections. https://www.ncbi.nlm.nih.gov/pubmed/24968274
Faulty/misleading antibody tests landed a sixteen year old male in a psychiatric ward when his lab results did not meet the CDC’s strict criteria for positive results. His Western blot had only four of the required five IgG bands. Subsequent DNA sequencing identified a spirochetemia in this patient’s blood so his psychiatric issues were a result of neurologic Lyme disease misdiagnosed by antiquated/misleading serology. This patient was previously treated with antibiotics.
Autopsy tissue sections of the brain, heart, kidney, and liver were analyzed by histological and immunohistochemical methods (IHC), confocal microscopy, fluorescent in situ hybridization (FISH), polymerase chain reaction (PCR), and whole-genome sequencing (WGS)/metagenomics. We found significant pathological changes, including borrelial spirochetal clusters, in all of the organs using IHC combined with confocal microscopy.
“This pilot study recently identified chronic Lyme disease in twelve patients from Canada. All of these patients were culture positive for infection (genital secretions, skin and blood) even after multiple years on antibiotics so there was no relief from current antimicrobials. Some of these patients had taken as many as eleven different types of antibiotics.” ________________________
Persistent infection after extensive antibiotic treatment has been identified through the use of direct detection methods in academic centers and autopsy findings yet the average patient cannot obtain these tests to justify how sick they are with their chronic active infection. Serology cannot be used to gauge treatment failure or success which makes it the ideal tool for concealing persistent infection.
Serology has allowed the 30-year dogma to persevere [2] whereas direct detection methods are exposing the exact opposite.
We are dealing with a life-altering/life-threatening infection with faulty/misleading antibody tests, inadequate treatment, no medical training and absolutely no disease control whatsoever; a public health disaster. And what was the reason for the mishandling of this coexisting pandemic you might ask?
A chronic relapsing seronegative disease does not fit the vaccine model. The rush to create a vaccine here in the United States promoted the denial of persistent infection and focusing on the acute stage of disease hides the horribly disabled.
Questions: Is there a reason why Prof Kullberg did not include my seven references of persistent infection in his BMJ article?
The Nebraska Department of Health and Human Services (DHHS) received a report of a death related to Rocky Mountain Spotted Fever, a disease carried by ticks.
Monday, August 31st 2020, 3:45 PM CDT
By Press Release
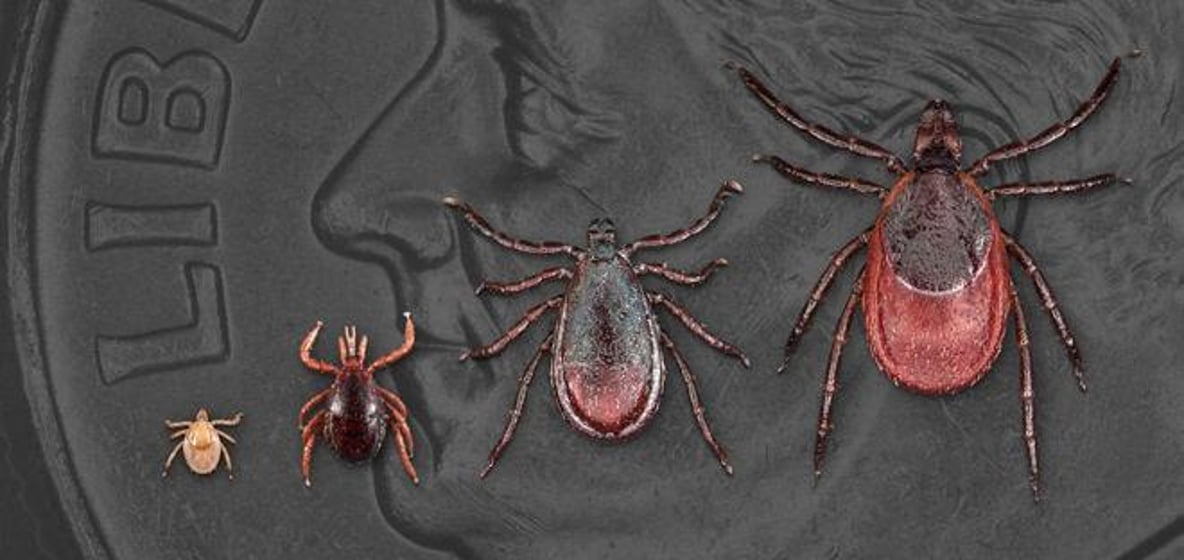
Deer ticks, a.k.a. black-legged ticks, at various stages of life. The ticks can carry Lyme disease. CDC
Lincoln – The Nebraska Department of Health and Human Services (DHHS) received a report of a death related to Rocky Mountain Spotted Fever, a disease carried by ticks. The man was in his 60s and lived in the West Central District Health Department (WCDHD), which includes Arthur, Hooker, Lincoln, Logan, McPherson and Thomas counties. DHHS has also seen an increase in reports of people with Ehrlichiosis, another tick-related illness. On average, the Department receives four reports of Ehrlichiosis in a year, nine reports have already been received to date.
“Ticks can be efficient carriers of disease and these tick-related illnesses can be serious and sadly, sometimes fatal,” said Dr. Tom Safranek, state epidemiologist for the Nebraska Department of Health and Human Services (DHHS). “In a year when many of us are spending more time outdoors due to the COVID-19 pandemic, Nebraskans need to practice the basics of tick prevention to reduce the risk of tick bites.”
“Although tick-related diseases are not seen frequently in our jurisdiction, ticks that can transmit diseases are still found here. It’s important for people to take simple steps to protect themselves and their families. It only takes one bite from an infected tick to make a person ill,” said Shannon Vanderheiden, Executive Director of WCDHD.
Protect yourself against tick bites:
Use a repellent with at least 20 percent DEET, picaridin or IR3535, or permethrin-treated clothing.
When outdoors, avoid contact with tall grasses and shrubs and keep commonly-used areas of yard free of tall grasses and shrubs, as well as deer and rodents, to help limit tick exposure.
Wear long-sleeved shirts, pants, socks, and closed-toed shoes outside.
Do a tick check after being outdoors, including coats, gear and pets, and remove any attached ticks promptly without squeezing.
Shower within two hours of coming indoors.
A relative to mites and spiders, ticks are generally found near the ground and in brushy or wooded areas where they climb tall grasses or shrubs and transfer to a host brushing against them. They attach and feed on blood. Engorged ticks are more likely to transmit pathogens that can cause diseases.
DHHS conducts surveillance on four medically-relevant tick species: the American dog tick, Rocky Mountain wood tick, Lone Star tick, and Blacklegged tick/Deer tick. Those concerned about possible infection from a tick bite should contact a healthcare provider. Suspected infections should be reported to a local health department or DHHS.
If you find an attached tick:
Remove the attached tick as soon as you notice it by grasping with fine-tipped tweezers, as close to the skin as possible, and pulling it straight out. Early removal can minimize and often eliminate the chance of infection.
Watch for signs of infection, and illness such as rash or fever in the days and weeks following a bite, and see a health care provider if these develop.
Additional information on tick-related diseases is available here – www.cdc.gov/ticks.
Some pets are also susceptible to tick-related disease. Learn more about tick bite prevention for your pets – www.cdc.gov/ticks/avoid/on_pets.html.