https://www.thechronicleherald.ca/opinion/doctors-public-left-in-the-dark-on-danger-to-babies-270535/

Dec. 21, 2018

The Chronicle Herald

OPINION: Doctors, public left in the dark on danger to babies

Jane Bailey

The following statement is false. You can only get Lyme disease from a black-legged tick. The next two statements are true. You can pass Lyme disease to your unborn baby. Your baby can suffer very serious adverse outcomes, including from miscarriage, stillbirth, and newborn death, as well as serious neurological development issues, and various other illnesses and developmental delays/issues as a result of Lyme infection during pregnancy.

Earlier this fall, on Nov. 12, a new, peer reviewed research article was published in the highly reputable science and medical journal PLOS ONE. It was authored by several senior Public Health Agency of Canada (PHAC) scientists and one Centers for Disease Control and Prevention (CDC) scientist. The paper unequivocally acknowledged mother-to-fetus (transplacental) transmission of Lyme disease as a fact.

This newly published paper also looked at case reports and studies from the past 30-plus years and found that there was a significant statistical difference in adverse outcomes for baby if the mother was infected with Lyme and had been untreated during pregnancy.

In their meta-analysis of several studies, 50 per cent of untreated women experienced fetal adverse outcomes compared to 11 per cent of treated women. In those cases, the authors state:

“Across 59 cases, negative outcomes for the fetus or newborn occurred in 61 per cent of pregnancies … (they) ranged from spontaneous miscarriage … fetal death and stillbirth … and death shortly following birth … to a range of congenital abnormalities and health issues.“

This is beyond alarming. It is an extremely important paper. And yet, not a word in the press, or notification to our doctors, nor, most importantly, to the public.

As far back as 1986, both the World Health Organization (WHO) and the CDC acknowledged mother-to-fetus transmission, and warned of possible adverse outcomes for baby. In June 1988, Health Canada released its own report acknowledging the same thing.

Nobody did anything. The information just sat there, hiding in plain sight.

In the summer of this year, the federal parliament of France, the Assemblée Nationale, issued a statement from the minister of health acknowledging mother-to-fetus transmission of Lyme disease.

And the WHO, after almost 10 years of considering the evidence, earlier this year (June 2018) issued a new International Classification of Diseases (ICD) code for congenital Lyme borreliosis (meaning babies born with Lyme disease) for physicians around the world. But on Monday (Dec. 17), the new WHO ICD-11 code for congenital Lyme borreliosis was the only code to be suddenly deleted from more than 55,000 new ICD-11 codes. At this point, it’s unclear why.

Something very strange and very unsettling is happening.

Where is Canada on this issue? Why isn’t Health Canada and the Public Health Agency of Canada saying anything? Why aren’t our public health departments and health authorities notifying doctors, women and parents-to-be of this very important issue? There should be national outrage over this appalling state of affairs regarding the non-notification of mother-to-fetus infection of Lyme disease. It is, actually, scandalous that the authorities have kept this from the public.

This mode of transmission changes everything.

Since 2014, I have corresponded on many Lyme issues with Dr. Robert Strang, chief medical officer for Nova Scotia, and Dr. Todd Hatchette, chief microbiologist for the Nova Scotia Health Authority and an infectious diseases doctor. They either denied that transplacental Lyme disease exists, or they refused to discuss it with me. They have both been provided with much of the 30-plus years of evidence, the same evidence considered by the scientists in the PLOS ONE article, the same evidence considered by the WHO, the CDC and PHAC.

At a meeting I attended at the Department of Health and Wellness on Sept. 1, 2016, I even had autopsy reports and photographs of babies with unequivocal evidence of the Lyme disease bacteria in their tissues and organs — everybody at the table declined to look at this evidence. As difficult and heartbreaking as such material is, this kind of behaviour from a department responsible for our health is unacceptable, and contributes to perpetuating the problem of no action.

It has been suggested by me, many times, that our doctors, and the public, be notified of the fact of mother-to-baby transmission of Lyme disease. All of my requests have been refused. On May 31, 2016, I was even told by Strang,

“I will no longer be responding to inquiries from you.”

It is despicable that the alarm has not been raised. And by not doing so, it could be argued, much unnecessary pain and suffering has been caused to many women, parents and children.

In a recent email (Oct. 23) Strang wrote to me regarding the above PLOS ONE research article, he stated,

“As you may be aware from the recent Lyme Hope meeting with PHAC, our national Public Health Agency has recently completed a comprehensive review of the evidence on Lyme disease in pregnancy. This review is undergoing peer review as part of possible publication. My public health practice will certainly follow the outcomes of this work.”

What Strang did not know when he sent me that email was that I was actually at that meeting with Lyme Hope and PHAC on Oct. 5 in Ottawa. I advised Strang of this fact, and of the fact that the scientists around the table, as well as one MD at that meeting, plus two MDs on the phone (a pediatric Lyme disease specialist, and an internal medicine specialist), the president of PHAC, and the director of the Infectious Diseases Branch, PHAC, all agreed that transplacental transmission was possible. Strang’s next response to me was, “I will not engage in an ongoing dialogue with you regarding this issue.” Appalling!

Strang is now silent on this issue. He has not made any public statement since the publication of the research article, neither has he responded to my last article on Lyme disease (“Lyme disease tunnel vision: Provincial authorities must expand horizons, review medial evidence”) published by The Chronicle Herald on Nov. 3. Why this silence? There is no getting around this, no “positive spin” can be put on this. The public, and our doctors, need to know. Shame on him. He, too, has the suffering of many on his conscience; or he should have.

With regard to mother-to-baby Lyme disease, doctors and women should know that babies and children present with symptoms very differently from adults.

For those of you reading who may have concerns regarding possible transplacental (mother-to-child) transmission of Lyme disease, I would direct you to the LymeHope.ca resources web-page. There you will find many credible and reputable resources and evidence that you can use to take to your doctor and discuss your concerns.

Jane Bailey lives in Wolfville. She has science and education diplomas and is a member of The Royal Society for Public Health.

__________________

**Comment**

AMEN!

PLOS ONE article:  https://madisonarealymesupportgroup.com/2018/12/12/systematic-review-on-gestational-lyme/

For more:  https://madisonarealymesupportgroup.com/2018/06/19/33-years-of-documentation-of-maternal-child-transmission-of-lyme-disease-and-congenital-lyme-borreliosis-a-review/

https://madisonarealymesupportgroup.com/2018/02/26/transplacental-transmission-fetal-damage-with-lyme-disease/

https://madisonarealymesupportgroup.com/2018/05/24/new-berlin-mom-given-life-altering-lyme-disease-diagnoses-after-pregnancy/

https://madisonarealymesupportgroup.com/2018/08/16/why-do-officials-continue-to-deny-gestational-lyme/

https://madisonarealymesupportgroup.com/2018/07/24/congenital-transmission-of-lyme-myth-or-reality/

https://madisonarealymesupportgroup.com/2018/10/05/canada-acknowledges-maternal-fetal-transmission-of-lyme-disease/

https://madisonarealymesupportgroup.com/2018/11/11/gestational-lyme-other-tick-borne-diseases-dr-jones/

https://madisonarealymesupportgroup.com/2018/08/16/why-do-officials-continue-to-deny-gestational-lyme/

https://madisonarealymesupportgroup.com/2017/10/15/pregnancy-in-lyme-dr-ann-corson/


https://m.facebook.com/story.php?story_fbid=296994284256306&id=673304082874974&_rdr  Approx. 10 Min

In the above link, Dr. Steven Phillips and Dana Parish take on the controversial subject of S E X & Lyme/MSIDS in an informative video.

  • Dr. Phillips discusses sexual dysfunction in both men and women due to tick borne illness
  • Dr. Phillips sees men with painful testicles with recurrent Bartonella
  • Prostatitis is also common, where the prostate becomes swollen, tender, and inflamed
  • Some patients get anal and/or vaginal fissures (little painful cracks)
  • There’s libido issues
  • Vaginal dryness
  • Psychological aspects
  • Low Testosterone levels
  • Extreme fatigue
  • Sexually induced severe headaches
  • There can be a Pavlovian response in that if sex causes pain, it trains you to no longer desire it
  • Pre-menstral flares are common
  • Some male patients struggle with Balanitus, a painful swelling of the foreskin, or head of the penis, which affects roughly 1 in 20 males.  It’s been linked to autoimmunity conditions.  Dr. Phillips believes this to be the result of an undiagnosed infection.  He’s also seen it as a herxheimer reaction. It can take time to resolve.

https://www.rheumatologyadvisor.com/lyme-disease/lyme-disease-diagnostic-uncertainty-in-children-with-neuropsychiatric-illness/article/783880/

Diagnosing Lyme Disease in Children With Neuropsychiatric Illness

Please see comment at end of article
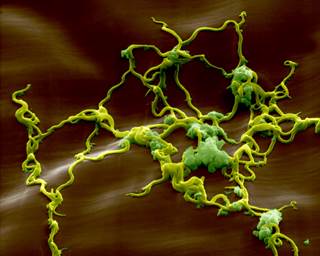
There is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize in children. <i>Credit:Eye of Science/Science Source</i>
There is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize in children. Credit:Eye of Science/Science Source


Lyme disease can present with a multitude of symptoms that often mimick other diseases, making differential diagnosis difficult. Neurologic involvement has been reported in up to 15% of untreated Borrelia burgdorferi infection,1 which can be devastating, particularly in children and young adults, who have been reported to be more at risk. According to the US Centers for Disease and Control and Prevention (CDC), Lyme disease is on the rise.2 Each year, at least 300,000 people in the United States are diagnosed with Lyme disease, with the highest infection rates occurring in children age 5 to 10 years.2,3

Lyme neuroborreliosis can affect any part of the nervous system, and there are a wide range of neurologic and psychiatric symptoms that can manifest weeks, months, or even years after the initial infection. For example, memory impairment, irritability, and somnolence have been reported months to years after the initial classic presentation of Lyme disease, and encephalopathy has been reported to occur more than 10 years after the onset of the disease.4,5 The presenting neurologic symptoms, including facial palsy, debilitating fatigue, various levels of cognitive loss, psychiatric symptoms, behavior changes, and learning difficulties have a significant and negative effect on the critical stages of child development, including school attendance and decline in school performance.6,7

Full recovery from Lyme neuroborreliosis can be achieved when the disease is diagnosed promptly and accurately and appropriate treatment is initiated. However, there is a general lack of understanding of Lyme disease among physicians, and Lyme neuroborreliosis is notoriously very difficult to recognize and diagnose in children. Shannon Delaney, MD, MA, director of child and adolescent research and evaluation at the Lyme and Tick-Borne Diseases Research Center at Columbia University Medical Center in New York told Rheumatology Advisor that,

“Neuroborreliosis can be missed because it is not considered in the differential [diagnosis] and because spinal taps are often not [performed] unless a child has very obvious symptoms of encephalitis or meningitis.”

The overlap of symptoms with other neurologic, cognitive, and psychiatric symptoms contributes to the delayed diagnosis or the misdiagnosis. For example, case reports of neuropsychological manifestations of Lyme disease include Tourette syndrome, acute delirium, catatonia, and psychosis.8

Dr Delaney advises that,

“Any child with acute onset neuropsychiatric symptoms, such as [obsessive-compulsive disorder], psychosis, restricted eating, sensory issues, urinary frequency, anxiety, cognitive dysfunction, or extreme fatigue should be given a set of lab tests to rule out typical infectious causes of Pediatric Acute-onset Neuropsychiatric Syndrome/Pediatric Autoimmune Neuropsychiatric Disorder Associated with Streptococcal Infections.”

Dr Delaney added,

“Testing should include a Lyme ELISA [enzyme-linked immunosorbent assay], preferably Borrelia burgdorferi C6 peptide, and a Lyme Western blot to evaluate for exposure to Lyme disease.”

Because symptoms of Lyme neuroborreliosis affect the joints, muscle, and the central and peripheral nervous systems, health professionals from many disciplines, including neurology and psychiatry, need to be able to recognize the clinical presentations, know the essential diagnostic tests, and understand the treatment approach. Erythema migrans is a distinct early presentation of localized Lyme disease,8 and for the experienced physician, this presentation can be sufficient for a clinical diagnosis. Serologic testing at this early disease stage is of limited diagnostic value because of the high incidence of false negative results.

When serologic testing is indicated, the Infectious Diseases Society of America (IDSA) recommend enzyme immunoassay for Lyme-specific antibodies, confirmed with Western immunoblot assay for immunoglobin G; however, many physicians struggle with the correct interpretation of Western blot results.9,10 Dr Delaney cautions,

“Clinicians should be aware that the 2-tier method of testing (ELISA and Western blot), while informative, can have false negative [results] and, less frequently, false positive [results].” Furthermore, although several tests for Lyme disease are available commercially, many are not validated for clinical use, and the CDC strongly warns against their use, as they have been associated with high levels of misdiagnosis.8  

The IDSA recommends antibiotics for the treatment of Lyme disease for a period of 10 to 21 days for early disease and 2 to 4 weeks for late disease.9 Despite the recommendations, studies that distinguish the treatment of Lyme disease from that of Lyme neuroborreliosis are lacking.9 In fact, a systematic review that examined antibiotic treatment for Lyme neuroborreliosis in 450 participants included no trials conducted in the United States.11 The review found no clear evidence for the additional efficacy of repeated antibiotics beyond the initial treatment.11

In addition, prolonged use of antibiotics to treat post-Lyme disease symptoms has not been shown to be efficacious and is generally not recommended, as fatalities from Clostridium difficile and Candida parapssilosis have been reported.8

“Clinically, we do recognize that there are a subset of patients who only get better after a repeated course of antibiotics,” said Dr Delaney, adding, “In the future as the science progresses, hopefully, we will be able to make use of blood tests that provide biomarkers indicating who needs additional antibiotic therapy and who needs another approach. This is the age of precision medicine and our goal at Columbia is to help in the identification of these essential biomarkers that will help guide treatment.”

The need for additional research is evident to better define the optimal use of antibiotics for the treatment of Lyme neuroborreliosis.11 The effect of long-term use of antibiotics also deserves attention. Inappropriate antibiotic use can alter the balance of the gut microbiome and may lead to side effects. The effect of long-term antibiotics on the gut microbiome is an area of emerging study and should provide very useful information in the future regarding whether or not the alterations themselves are contributing to ongoing symptoms. Until more research is available to better guide the management of the neurologic manifestations of B burgdorferi infection, it is important that physicians have heightened awareness of Lyme disease. They must also have a clinical suspicion of Lyme neuroborreliosis in children who present with neuropsychiatric illness and must diagnose the disease promptly and provide appropriate treatment, which may include referral for appropriate symptom management.

References

  1. Marques AR. Lyme neuroborreliosis. Continuum (Minneap Minn). 2015;21(6):1729-1744.
  2. US Centers for Disease Control and Prevention. Lyme disease. Lyme disease graphs. https://www.cdc.gov/lyme/stats/graphs.html. Updated November 1, 2017. Accessed July 17, 2018.
  3. US Centers for Disease Control and Prevention. Lyme disease. How many people get Lyme disease? https://www.cdc.gov/lyme/stats/humancases.html. Updated September 30, 2015. Accessed July 17, 2018.
  4. Bloom BJ, Wyckoff PM, Meissner HC, Steere AC. Neurocognitive abnormalities in children after classic manifestations of Lyme disease. Pediatr Infect Dis J. 1998;17(3):189-196.
  5. Szer IS, Taylor E, Steere AC. The long-term course of Lyme arthritis in children. N Engl J Med. 1991;325(3):159-163.
  6. Lyme Disease Action. Neurology and Psychiatry. Involvement of the Central and Peripheral Nervous System. https://www.lymediseaseaction.org.uk/about-lyme/neurology-psychiatry/. Updated November 26, 2016. Accessed July 17, 2018.
  7. Cameron D. Adolescents with Lyme disease. http://danielcameronmd.com/adolescent-lyme-disease/. 2018. Accessed July 17, 2018.
  8. Koster MP, Garro A. Unraveling diagnostic uncertainty surrounding Lyme disease in children with neuropsychiatric illness.Child Adolesc Psychiatr Clin N Am. 2018;27(1):27-36.
  9. Wormser GP, Dattwyler RJ, Shapiro ED, et al. The clinical assessment, treatment, and prevention of Lyme disease, human granulocytic anaplasmosis, and babesiosis: clinical practice guidelines by the Infectious Diseases Society of America. Clin Infect Dis. 2006;43(9):1089-1134.
  10. Conant JL, Powers J, Sharp G, Mead PS, Nelson CA. Lyme disease testing in a high-incidence state: clinician knowledge and patterns. Am J Clin Pathol. 2018;149(3):234-240.
  11. Cadavid D, Auwaerter PG, Rumbaugh J, Gelderblom H. Antibiotics for the neurological complications of Lyme disease. Cochrane Database Syst Rev. 2016;12:CD006978.

__________________

**Comment**

A few points of contention:

  1. While the EM rash IS an early symptom that clinically proves the person has Lyme, many never see or have a rash at all or it is certainly not a “typical” EM rash.  Clinicians need education in this.
  2. Numbers are notoriously low on all things Lyme/MSIDS, including this supposed 15% who have neurologic involvement.  Everyone I work with is in this category so I’m either just a lucky-duck or the numbers are far higher in the real world.  I suspect the latter.
  3. Testing for Lyme/MSIDS IS ABYSMAL.  Absolutely worthless.  It misses over half of all cases.  I’m thankful the article states professionals need to be educated because this is a CLINICAL DIAGNOSIS.  Anyone who says otherwise is smoking something.  Again, clinicians need education.
  4. Where the article really falls apart is in the treatment section.  This article ONLY discusses the IDSA approach which is essentially 21 days of doxycycline despite the presentation.  I couldn’t disagree more.  If you read the ILADS guidelines, you will discover that treatment is far more complex.  There are many who have gotten well or improved dramatically with this approach.  The reason for this is numerous:  1) we are typically infected with more than borrelia, necessitating numerous drugs 2) all of these pathogens are stealthy and many are persistent requiring far longer treatment courses than appreciated 3) these pathogens work together to suppress the immune system and complicate the picture requiring numerous treatments
  5. The Cochrane review of antibiotics for neuro-Lyme mentioned had numerous flaws: none included a placebo control, only ONE was blinded, most were not adequately powered for non-inferiority comparison, they ONLY investigated four antibiotics:  penicillin G & ceftriaxone in 4 studies, doxycycline in 3 studies, cefotaxime in two studies, and amoxicillin vs. placebo for only 3 months following initial treatment with IV ceftriaxone.  (I consider many of these antibiotics poor choices for Lyme and I’ve never taken two of them.  I had to look one up as I’d NEVER even heard of it!) The trials measured efficacy using heterogeneous physician‐ or patient‐reported outcomes, or both.  None of the studies reported on the proposed primary outcome, ‘Improvement in a measure of overall disability in the long term (three or more months).’ The quality of adverse event reporting was low.  So, as far as I’m concerned this “review” is extremely weak yet it’s presented as evidence that long-term antibiotics do not work.  Please see this article for comparison:  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/  Also, I would not be writing this article without the judicious use of long-term antibiotics.
  6. It’s interesting that although the author disses long-term antibiotics using the IDSA clap-trap and an extremely weak and flawed review, she did include the quote from Dr. Delaney,

“Clinically, we do recognize that there are a subset of patients who only get better after a repeated course of antibiotics,” said Dr Delaney

Hmmm….that appears to be a cognitive disconnect.

To clear the record:  nearly all of us out here in Lymeland HATE taking antibiotics.

We take them because they often work better than other things we’ve tried.  They are also more affordable than other many other options.

But, if we could press some magic button, believe me –  we would.  

I find it interesting that people with acne can take antibiotics forever, yet patients with life-threatening tick-borne illness are told extended antibiotics can give them C-diff, therefore they are bad and shouldn’t be considered.  Period.

 This disconnect is wholly unacceptable.


https://www.ncbi.nlm.nih.gov/m/pubmed/29943903/

Tick-borne relapsing fever as a potential veterinary medical problem.

Elelu N. Vet Med Sci. 2018.

Abstract

Tick-borne relapsing fever (TBRF) caused by the bacteria Borrelia, is poorly documented in veterinary medicine. Given the widespread presence of the soft tick vectors – Ornithodoros and the recently discovered hard tick vectors, as well as their close association with animal hosts, it is highly likely that infection occurs, but is rarely reported to be of veterinary importance. Sporadic reports of canine infection, some being fatal through to probable cause of abortion in horses have been published. Some of these pathogens exist in regions where there are limited diagnostic facilities, hence, they are likely to be missed and their impact on productivity may be unquantified. Here we review available literatures on cases of TBRF in domestic and wild animals in order to show their potential veterinary medical impact. Future efforts using field and laboratory surveys are needed to determine pathogenesis, vector competence and distribution in animals, their impact on animal health and productivity as well as to prevent further spill to the human population, where it is already a public health problem in some parts of the world.


WLN_At_A_Glance_December_15,_2018_Final

WLN-Logo-copy-300x84

Within the link from Wisconsin Lyme Network (WLN) you will learn about:

  • The facts about Permethrin
  • WLN is selling Permethrin-treated clothing
  • The upcoming Howard Young Medical Clinic in Minocqua
  • The upcoming Lyme conference in Lacrosse, WI on March 23, 2018
  • An upcoming Wisconsin Lyme Walk (TBD)
