Archive for the ‘Treatment’ Category

The Science of Fasting Podcast: Monday March 11, 2024

You can watch live in the WCH Newsroom or watch later when it is most convenient for you.

⏰ Please note: Daylight Saving Time begins in the US, Canada, some parts of Mexico, etc. this weekend, making Monday’s show one hour later than previously.

Time zone guide: 11 am PDT, 1 pm CDT, 2 pm EDT, 6 pm UTC / GMT, 8 pm CAT, 3 am JST (12 March), 5 am AEDT (12 March), 7 am NZDT (12 March)

For more:

The ‘New Norm:’ Authors Rewrite Positive Ivermectin Findings To Make Them Appear Negative

https://www.theepochtimes.com/health/people-who-received-ivermectin-were-better-off-study-finds-

People Who Received Ivermectin Were Better Off, Study Finds

Ivermectin recipients recovered faster than others.
3/7/2024

People who tested positive for COVID-19 and took ivermectin as a treatment recovered faster than a comparison group, a new study found.

The time to self-reported recovery was a median of two days faster among the ivermectin recipients, according to the large UK study.

The quicker recovery period was statistically significant.

People who received ivermectin were also less likely to be hospitalized or die, with 1.6 percent of ivermectin recipients being hospitalized or dying versus 4 percent of the comparison group, which received typical care, which in the UK is largely focused on managing symptoms.

Ivermectin recipients also enjoyed a reduction of severe symptoms and sustained recovery, according to the study.

The paper was published by the Journal of Infection on Feb. 29.  (See link for article)
_________________
SUMMARY:
  • Only in the topsy-turvy world of COVID do study authors rewrite positive findings into negative ones
  • The PRINCIPLE trial came up with an unneeded specified hazard ratio to make the findings appear insignificant. In the real world, if a HR is >1.0, and is statistically significant, it is a robust finding.
  • Further, the findings should be interpreted in the context of
    • recipients only receive ONE dose per day across three days
    • recipients were directed to refrain from eating food 2 hours before and after administration when previous research found that taking it with food increases plasma concentration
    • recipients received ivermectin a median of 5 days after symptom onset, a time some consider to be too late since the drug works best within 24 hours according to a meta-regression
  • There have been additional studies that found ivermectin works against COVID-19.
  • Dr. David Boulware who helped run the trial argued that faster recovery with ivermectin was similar to the open-trial findings of molnupiravir; however, according to James Lyons-Weiler, the FDA dropped the ball completely on this supposed ‘game changer’ which gave people higher live SARS-CoV-2 viral titers and more viral evolution two weeks after start of treatment, but was still FDA approved.
  • Go here for a quick review of costs between FDA approved and FDA unapproved COVID treatments.  This says it all.

https://worldcouncilforhealth.org/news/statements/principle-trial/

PRINCIPLE Trial Fails to Refute Evidence of Ivermectin’s Efficacy in Covid-19

Results from the Oxford-managed PRINCIPLE trial of ivermectin in out-patient Covid-19 were published in the Journal of Infection on 29 February 2024, over a year and half after the trial’s closure in July 2022, and over 2 years since the originally planned termination. The unexpected pause in January 2022 (said to be due to supply problems, denied by the supplier) remains unexplained. PRINCIPLE is funded by the NIHR, i.e. by the British taxpayer.

The trial design was criticised by FLCCC and BiRD International on 1 July 2021, because of enrollment up to 14 days of symptoms. The comprehensive summary of clinical evidence at c19ivm.org thus categorises this as a “Late Treatment” RCT. The protocol treatment, with weak dosing, short duration, fasting administration minimising serum concentrations, confined to a monotherapy with disregard of ubiquitous adjuncts, and of the concurrent corticosteroids indicated at later disease stages, did not correspond to any treatments adopted by clinicians using ivermectin with success. Overall the majority of patients were low-risk, after enrollment criteria were changed in July 2021 to accommodate all adults.

https%3A%2F%2Fsubstack post media.s3.amazonaws.com%2Fpublic%2Fimages%2Fc5127434 1c08 4610 8bf1

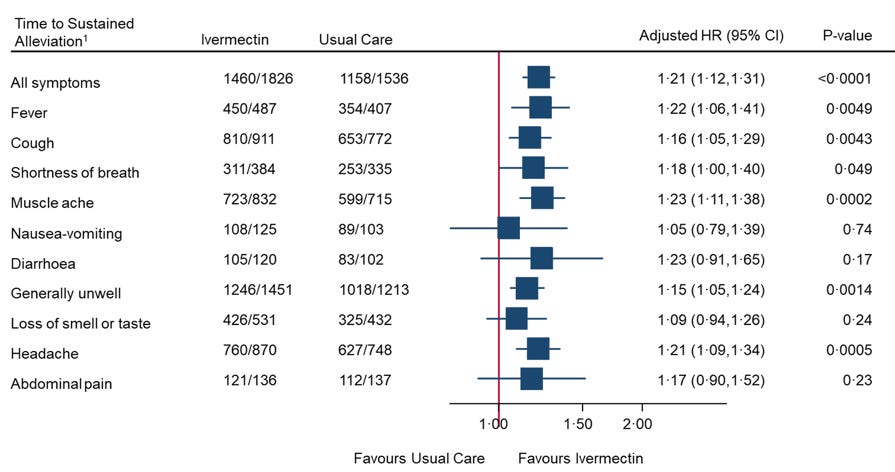
In spite of the low-risk population, under-dosing, and late treatment, statistically significant improvements in times to recovery on various metrics are found, Fig. S6(b) opposite, though not graphed in the main paper. The authors’ summary rejects these as not clinically significant, based on an arbitrary, pre-defined, metric:  –  “Ivermectin for COVID-19 is unlikely to provide clinically meaningful improvement in recovery, hospital admissions, or longer-term outcomes. Further trials of ivermectin for SARSCov-2 infection in vaccinated community populations appear unwarranted.” This does not follow from the evidence. A rational response to statistically significant improvement in recovery time, demonstrating a positive quantified effect, would be to seek to optimise the protocol. Also the alleviation of Post-Acute Sequelae of SARS-Cov-2 (PASC) i.e. “Long Covid”, as detailed here from data in the Supplementaries, is clear, and at variance with the negative conclusion on “longer term outcomes”.

BiRD International and the World Council for Health agree however that further trials of ivermectin alone are unwarranted, the weight of evidence summarised at covid19.org being so overwhelming that the remaining issues concern dosage, adjuncts, and mechanism, rather than further empirical evidence of clinical effect. The paper’s opening statement “The evidence … is contested” does not survive scrutiny of all available evidence, even after this report. Multiple critiques of design and implementation remain unanswered, data sharing is only offered subject to contracts, and an undeclared conflict of interest is Prof Chris Butler’s parallel PANORAMIC trial of molnupiravir, a proprietary drug.

We find the results unsurprising in view of the poor trial design; they do little or nothing to refute the accumulated worldwide evidence on the efficacy of ivermectin in Covid-19.

_______________

**Comment**

And there you have it.  Yet another manipulated study for a pre-determined outcome by an author with a vested interest in a treatment that competes with ivermectin.  Case closed.

For more:

Somatic Tracking for Pain

**DISCLAIMER**

Sorry for the monologue, but it’s important.

As anyone in Lymeland knows, ‘what works for one, doesn’t work for another.’  Please keep this in mind as you read the following information that I hope will help someone.  Further, I am in complete disagreement with any statements that Lyme/MSIDS can not be a persistent/chronic infection(s).  The doctor in the documentary, Dr. Howard Schubiner, admits there is controversy in the medical community over chronic Lyme/MSIDS, and that he has had the experience of seeing patients ‘overtreated’ with antibiotics for weeks, months, and years. While he states he is very happy for those who are doing well with long-term of treatment, he states patients should rethink their diagnosis if they are on a merry-go-round of costly and invasive treatments that aren’t working. To this doctor I would state: while you have had the unfortunate experience of helping ‘overtreated’ patients, there are thousands upon thousands in the real world who are dying from undertreatment.  Tread lightly.

While rethinking a diagnosis appears to be logically sane thinking, it’s imperative to understand treating Lyme/MSIDS is fraught with confusion, mystery, set backs, and pain. To my knowledge the only other diseases with Jarisch-Herxheimer reactions besides Lyme disease are syphilis, leptospirosis, and relapsing fever – which means unless you have had one of those diseases before, you have never experienced how confusing and relentless herxes are. They truly make you think you are losing your mind.

It is not uncommon at all for patients to hit plateaus in Lyme/MSIDS treatment. They might go through a period where they feel great only to have the dreaded symptoms, or even worse ones appear over night.  This is why Lyme literate doctors describe treating this similarly to peeling back the layers of an onion.  When one infection gets under control another one suddenly becomes visible.

This coinfection involvement never gets any air-play, but is crucial in understanding this beast. These infections require different medications entirely, but mainstream medicine doesn’t even consider them, so when a short course of doxy doesn’t make a person well, they simply fold up shop and declare, “you don’t have Lyme,” which could very well be true; however, they could also have Babesia, Bartonella, Relapsing Fever, or a whole host of other infections that look and act just like Lyme disease. Please go here to learn of the many issues surrounding why patients don’t get well.

So, once again, none of this is simple.  Keep an open mind.

One final note: I ended up using many aspects of this technique out of desperation, completely on my own.  I had no idea it was a ‘thing,’ but as they say, ‘necessity is the mother of invention.’

https://careclinic.io/somatic-tracking-pain/
Somatic Tracking for Pain: Unveiling Effective Techniques

somatic tracking pain

Living with pain can be a daunting and overwhelming experience. It can drastically affect our quality of life and prevent us from fully enjoying the activities we love. However, there is a technique called somatic tracking that can help us better understand and manage our pain. In this article, we will delve into the intricacies of somatic tracking, explore its benefits, and discuss how it can be implemented in our daily lives.

Understanding Somatic Tracking

Somatic tracking is a mindfulness-based technique that involves bringing awareness to our bodily sensations and learning to interpret them. By paying attention to our physical experiences, we can develop a deeper understanding of the underlying causes of our pain and explore ways to alleviate it.

When we talk about somatic tracking, we are referring to the practice of tuning in to the sensations and signals that our bodies send us. It’s like becoming fluent in the language of our own physical experiences. Just as we can learn to interpret words and phrases in a foreign language, we can learn to interpret the messages that our bodies are constantly sending us.

Imagine this: you wake up one morning with a dull ache in your lower back. Instead of dismissing it as just another discomfort, you decide to practice somatic tracking. You close your eyes, take a deep breath, and bring your attention to the area of your back that is bothering you. As you focus on the sensation, you start to notice subtle nuances – a tightness, a twinge, a warmth. These sensations become the building blocks of your understanding.  (See link for article)

________________

https://www.curablehealth.com/podcast/what-is-somatic-tracking  Podcast Here

A Podcast Where Real Chronic Pain Sufferers Meet Science-Backed Solutions 💫

Join us as our expert hosts help listeners overcome obstacles to healing through evidence-based techniques.

Go here for a Somatic Tracking exercise, and here for 10 best exercises

And here for an excerpt from The Way Out: A Revolutionary, Scientifically Proven Approach to Healing Chronic Pain by Alan Gordon and Alon Ziv, the speakers from the podcast above.

And here for one person’s successful experience with Somatic Tracking without using drugs or getting surgery.

It is described as physical therapy for the brain.

https://www.thismighthurtfilm.com/

This Might Hurt

A Film about a radical treatment for chronic pain

THE PROBLEM: CHRONIC PAIN

One in seven people around the world suffer from chronic pain, and nearly 80% of us will experience it at some point in our lives. The symptoms show up as back pain, neck pain, fibromyalgia, migraines, irritable bowel syndrome, anxiety, depression, fatigue, and a dozen others. The standard treatments are often ineffective, and one of the main remedies, opioids, has made the problem worse. What’s going on here?

THE FILM

This Might Hurt is a documentary that offers solutions to reduce and unlearn chronic pain. The film follows three chronic pain patients who have spent years searching for answers. Desperate for relief, they enter a new medical program — run by Dr. Howard Schubiner — that focuses on uncovering hidden causes of pain, and retraining their brains to switch the pain off.

This new paradigm for diagnosis and treatment was found to be effective in several randomized trials, and was listed as a “best practice” by the HHS’s task force to combat the opioid epidemic. This Might Hurt provides an intimate exploration and suggests a path to healing for millions.

Here are just some of the conditions that can be caused by “primary pain,” also know as brain-generated pain:

Brain Induced Conditions.gif

*These treatments are generally not recommended for people dealing with “secondary pain,” that is, pain that derives from cancer, fractures, muscle diseases, or infections.


NOT SURE IF THESE IDEAS APPLY TO YOUR SYMPTOMS?


HowardLecture3.jpg

5 STEPS TO UNLEARNING CHRONIC PRIMARY PAIN EXPLORED IN THIS MIGHT HURT

Meningitis Secondary to Lyme Disease: Case Report

https://danielcameronmd.com/case-report-meningitis-secondary-to-lyme-disease/

CASE REPORT: MENINGITIS SECONDARY TO LYME DISEASE

lyme-disease-meningitis

In this case report, “Meningitis in the Guise of Dementia: Lyme-Induced Normal Pressure Hydrocephalus,” Liu and colleagues review the case of an elderly patient with dementia, found to have Lyme meningitis in the setting of a normal pressure hydrocephalus (NPH). [1]

An 80-year-old man was admitted to a hospital in Pennsylvania, an area endemic for Lyme disease, due to increased weakness and confusion. He had “several days of nausea with decreased appetite, generalized malaise, fatigue, and weakness,” according to the authors.

Cerebrospinal fluid (CSF) studies suggested aseptic meningitis. And a CT scan showed dilated ventricles. Treatment for normal pressure hydrocephalus relieved his symptoms.

On the fourth day of hospitalization, the man tested positive for Lyme disease by Western blot on bands 23KD and 39KD.

“Healthcare providers treating patients with NPH should consider Lyme disease as a differential diagnosis because of the multiple reported cases of NPH secondary to Lyme disease.”

“The patient was subsequently diagnosed with aseptic meningitis secondary to Lyme,” the authors state.

He was treated with IV and oral doxycycline. But his dementia did not completely resolve, “likely due to primary dementia or other condition.”

“In the case of our patient, infectious meningitis was suspected due to this patient reportedly having had fevers and leukocytosis. Additionally, Lyme disease is among the most common reportable infections in Pennsylvania,” the authors state.

Authors Conclude:

“Lyme disease … can present with multiple complications, including arthritis, heart rhythm defects, facial nerve palsy, impaired memory, and meningitis. Hence, Lyme disease should be considered as part of the differential etiology of meningitis.

References:
  1. Liu R, Polly M, Lennon RP, Reedy-Cooper A. Meningitis in the Guise of Dementia: Lyme-Induced Normal Pressure Hydrocephalus. Clin Med Res. 2023 Dec;21(4):226-229. doi: 10.3121/cmr.2023.1829. PMID: 38296639.

_______________

**Comment**

Again, doxy is a great front-line drug but hardly a panacea.

Coinfections are never considered or talked about.

For more:

Chlorine Dioxide & Natural Medicine: Kerri Rivera

https://robertyoho.substack.com/p/298-kerri-rivera-returns-to-reveal?  Audio Here

KERRI RIVERA RETURNS TO REVEAL MORE SECRETS OF NATURAL MEDICINE

Kerri Rivera kindly returned for a second interview about chlorine dioxide and other natural medicines. She began studying natural health to save her vaccine-injured son from autism years before Kalcker or Humble appeared on the scene. This makes Kerri an OG, an Original Gangster. This phrase is a rapper complement that now means a respected or old-school source.

Kerri deserves to be heard because of her depth of experience and training with some of the best healers in the world. If you haven’t, listen to her first interview HERE. She helped me clear up some of my confusion about alternative medicine. Kerri is a homeopath who offers online consultations. Email her at kerri@kerririvera.com if you are interested.  (See link for article and interview)  Go here for the Rumble video version

______________

Important quote:

“Chlorine dioxide (CD) is foundational; methylene blue is adjunctive.”

A BIG THANKS to Dr. Yoho for summarizing the video in the link above.  Most people don’t do this and it frustrates me to no end as most of us don’t have time to listen to hour plus interviews!

He also lists dosages and frequency as well as other helpful tidbits.

Notice that desperation for her son’s health is what drove Rivera to find this treatment.  I have seen this play out over and over again.  People who are vested in finding real answers find things people who just get a paycheck don’t.

Please also see: