Suffering with anxiety while fighting MSIDS (multi systemic infectious disease syndrome) can be debilitating. I remember the days when my husband would literally start shaking while talking with people. He never knew when it would strike. He could be having lunch with a sales rep or standing in the foyer of someone’s home. He dreaded it, and I felt completely helpless. He is completely free of anxiety after three years of treatment. And while I feel treatment is truly the answer, there are often things we have to do to assist our bodies.
https://www.youtube.com/watch?v=rQS3oPTgDmM Published on Apr 23, 2015 Could diet and nutrition be central determinants of mental health? Find out when Trudy Scott, CN, provides evidence presented at The Anxiety Summit, seasons 1 and 2, which has showcased vitally important research now available to integrative practitioners and to people who suffer with anxiety, panic attacks, social anxiety and OCD. The gut-brain connection and microbiome, methylation, adverse effects of benzodiazapines, the role of inflammation, and controversial opinions about serotonin, GABA and urinary neurotransmitter testing are a few of the concepts that will be shared.
https://www.youtube.com/watch?v=5wP1xFcXFZo Published on Feb 21, 2014 “Using Targeted Individual Amino Acids to Overcome Anxiety, Panic, Worry, Negativity, Cravings and Emotional Eating” with Food Mood Expert Trudy Scott
Supplementing with specific individual amino acids can raise neurotransmitter levels and balance brain chemistry, alleviating anxiety, fear, worry, panic attacks, and feeling stressed or overwhelmed. They can also be supportive in addressing other issues that contribute to or exacerbate anxiety, such as sugar cravings, emotional eating and addictions. In addition, supplemental amino acids can help with depression, PMS, poor focus/ADHD and insomnia, which often co-occur with anxiety.
This presentation will cover symptoms of low serotonin, low GABA, low endorphins, and low catecholamine neurotransmitters. How to raise these neurotransmitter levels with the amino acids l-tryptophan, GABA, d- phenylalanine (DPA) and l-tyrosine, thereby improving mood and ending emotional eating will be taught. The use of glutamine to stabilize low blood sugar, leading to improved mood and gut health will also be addressed.
Trudy says: “The amino acids are key to the success of my practice. They help my clients eliminate stress-eating, and make food changes without feeling deprived and only having to use willpower. My clients feel calm and happy right away, giving them hope, while their other health and nutritional challenges are addressed. Many people suffering from various health concerns could receive tremendous relief with the proper use of amino acids”.
Quite often with MSIDS, we find ourselves dealing with side issues. Which came first, the infection of MSIDS or the condition? In nearly every case, the science is completely lacking, but unless dealt with will stop our healing. Pyroluria is perhaps one such condition. Normally considered an “inherited” condition associated with inner tension and anxiety, especially in social settings, and is made worse by stress, MSIDS sufferers should consider it.
Discuss all treatment information to your health care practitioner.
http://lymediseaseguide.org/lyme-disease-zinc-and-pyroluriaDr. Dietrich Klinghardt claims that most patients he treats for autism or Lyme disease have pyroluria, a defect in the synthesis of haemoglobin which causes excess excretion of zinc. His treatment for the condition is extremely high doses of zinc (200mg or more each day) although this level of zinc can cause nausea, adversely affect copper levels in the body (leading to anaemia), double the risk of prostate cancer, and result in diarrhoea, stomach pain, and vomiting in some. Patients should be extremely cautious regarding zinc supplementation whether suffering from Lyme disease or not as excess levels can build up quite quickly if pyroluria is not present.
Pyroluria is also known as kryptopyrroluria (KPU) or the Mauve Factor and is most commonly observed in women, possibly due to the more overt effects of chronic deficiency in B6 and zinc that may result in women during their teens and early twenties. Symptoms associated with pyroluria include halitosis (bad breath), severe stretch marks, fatigue, poor concentration, confusion, sleep disturbances, poor appetite or increased appetite, mood swings, pale skin, multiple food allergies, and changes in libido (raising or lowering). Some patients may be prescribed antidepressants such as Prozac as low levels of zinc and B6 can reduce the production of the neurotransmitter serotonin which regulates mood (amongst other things). Patients may be persistently depressed to some degree with symptoms exacerbated (in women) as part of the premenstrual syndrome (PMS).
The recommended daily allowances for zinc (in the US) are 8milligrams (8mg) for women and 11mg for men, although these used to be around 15mg a few years ago and have been lowered in recent years; anything over 50mg per day is considered excessive. Those with pyroluria however, may be advised to take supplements containing vitamin B6 and levels of zinc above the generally recommended levels but taking high levels of either nutrient is inadvisable without medical supervision (excessive B6 may lead to a kind of peripheral neuropathy when taken long-term).
• The associated signs and symptoms of this condition • The concerns with pyroluria urine testing, and why the pyroluria questionnaire may be a better option • Fatty acid testing • Concerns with low vitamin B6 and zinc markers • Food sources and supplemental forms of these nutrients • Additional supportive nutrients • Risk factors related with excess intake of some of the nutrients • Tips to enhance absorption • Review of a supportive protocol and its duration
This presentation will also examine the connection of pyroluria to gluten intolerance, inflammation, stress, heavy metals, low serotonin, insomnia, women’s hormonal health, methylation mutations and low histamine. Case studies will be discussed.
The HPU complex is a biochemical marker and neurotoxic substance frequently identified in the urine of patients with autism, learning disabilities, alcoholism, substance abuse, schizophrenia, ADHD, Down syndrome, depression, bipolar disorders, and even criminal behavior. Some estimate the incidence of KPU to be 40-70% in schizophrenia; 50% in autism; 30% in ADHD; and 40-80% in alcoholism and substance abuse. HPU may be an inherited condition but it can also be induced by childhood psychological trauma or chronic infections. Dr. Klinghardt has found the incidence of HPU in Lyme disease to be 80% or higher; in patients with heavy metal toxicity (lead, mercury, cadmium, and others) over 75%; and in children with autism over 80%. These are very significant percentages of the patient population with chronic illness that may benefit from a treatment program which addresses HPU. Normal, healthy controls do not test positive for HPU. Dr. Klinghardt believes that it is not possible to have chronic symptomatic Lyme disease as an adult without a preceding mold illness or the patient having developed HPU. He postulates that the biotoxins from microbes block one or more of the eight enzymes of heme synthesis. This leads to a significant loss of key minerals in white blood cells which effectively disarms cellular immunity.
Last year, Certified Nutritionist Trudy Scott interviewed researchers, doctors, psychiatrists, nutritionists, consumer advocates, and psychologists on natural solutions for anxiety.
http://www.theanxietysummit.com By going here, you can purchase recordings/transcripts, or contact Scott for any upcoming free on-line events.
Those suffering from MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) quickly discover that successful treatment is holistic. Killing pathogens is certainly an important arm of treatment, but so is detoxing those dead pathogens, as well as improving immune system function.
According to Frank M. Painter, D.C., studies demonstrate an accumulation of evidence that indicates spinal manipulation may influence the immune system‘s response to various stimuli and reduces production of pro-inflammatory mediators associated with tissue damage and pain. Some studies also give evidence that manipulation may induce and enhance production of the immunoregulatory cytokine IL-2 as well as the production of immunoglobulins. http://www.chiro.org/research/ABSTRACTS/Effects_of_Chiropractic.shtmlOther results show manipulative treatment may influence T and B lymphocyte numbers, NK cell numbers, antibody levels, phagocytic activity, and plasma beta endorphin levels.
Chiropractic care has been vilified since the 60’s with a “persistent tendency to suppress physicians from referring patients to chiropractors — so much so that Dr. Chester Wilk ended up filing an antitrust suit against the American Medical Association (AMA) in 1976.” Wilk eventually won and in 1987, the court ruled that the AMA had engaged in an unlawful conspiracy in restraint of trade to contain and eliminate the chiropractic profession.
According to chiropractors, chiropractic care is similar to seeing a dentist and needs to be done on a regular basis to maintain the health of your spine, because even regular activities can contribute to a less than optimal functioning.
One of the best ways to find a good wellness chiropractor is by word of mouth. You may also want to find out if he or she is trained in any other treatment modalities, such as muscle testing, applied kinesiology, or neuroemotional technique (NET). There are literally dozens of different techniques that can have a profound impact on addressing the bioenergetic component of disease, not just the structural.
Tips for Choosing a Wellness Chiropractor: Meet the doctor. Many chiropractors will agree to a no-cost consultation to determine whether you are a good match. To make this visit as productive as possible, here are a few things to consider: Does the practice focus on vertebral subluxation and wellness? Physical, biochemical, and psychological stress may result in spinal subluxations that disrupt nerve function and compromise your health.
Does the doctor “walk the talk”? If he or she is overweight, looks unhealthy, or does not live a healthy lifestyle, this speaks volumes regarding their commitment to wellness. Do the two of you “click”? Do you like each other? Do you communicate well? Avoid a doctor who seems rushed, talks down to you, or seems disinterested in listening to your concerns.
Does the doctor use objective assessments of nerve function? Since your care is not based just on addressing pain, your chiropractor should be using some form of objective assessment of your nerve function, as spinal subluxations can sometimes be asymptomatic. Non-invasive instruments that measure the electrical activity in your muscles, and/or a thermal scanner that evaluates the function of your autonomic nervous system can be used, for example.
What treatment techniques are used? Chiropractic techniques include low-force adjustments by hand, and more forceful adjustments using instruments. Ask which technique would be used on you, and if you have a preference, make sure the doctor is willing to use it.
On Saturday, April 9, from 2:30pm-4:45pm, Dr. Eileen Isom DC, CCST, Certified Spinal Trauma Specialist, of Madison Chiropractic, will be speaking at the Madison Lyme Support Group. Dr. Isom uses NUCCA technique which is unique because it frees the nervous system of interference by using a precise, non-invasive, gentle touch technique.
The NUCCA technique brings several generations of clinical research to correcting the serious problem of the Atlas (the bone your head sets on) Subluxation Complex. By using precise and objective x-ray views of the head and neck, mathematical measurement and analysis are made of the misalignment. There is no twisting, popping, or cracking with this gentle, yet effective procedure.
Some of the many symptoms that can be relieved by correction of the Atlas Subluxation Complex include but are not limited to:
Neck and back pain
Headaches and Migraines
Hypertension
Chronic pain or stress
Leg and arm numbness
Scoliosis
TMJ
Fibromyalgia
Sinus and allergy problems
Herniated disc
Seizures
Depression
Attention Deficit Disorder
Hormonal Imbalance
Athletic and auto injuries
Bed wetting
Cerebral Palsy
Multiple Sclerosis
Arthritis
Chiropractic care may be something you need to investigate further in your MSIDS journey as it can alleviate pain, help you structurally, as well as optimize your immune system.
http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article POW is a single-stranded RNA virus in the genus Flavivirus of the Flaviviridae family. There is substantial serologic cross-reaction with other flaviviruses (dengue, St. Louis encephalitis, yellow fever, Japanese B encephalitis, West Nile virus). RNA viruses generally have high mutation rates. Both prototypic (POWV) and deer tick virus (DTV) genotypes exist and are cousins to the tick-borne encephalitis virus causing significant illness in Europe. All sequenced strains in Minnesota are of the DTV genotype.
https://www.dhs.wisconsin.gov/tickborne/powa-april-2010-wmj.pdf Presence of POW-lineage viruses has been well documented in at least 38 mammal species including small and medium sized wild animals (rodents, woodchucks, skunks) and domestic animals (dogs, cats), with several species of ticks proven to be vectors at this time. Human infection with Powassan Virus has been documented in North America and Russia.
Selection bias in identifying the infection may exist, diminishing the reported incidence to only patients with severe disease.
http://www.cdc.gov/mmwr/preview/mmwrhtml/mm5035a4.htm Because of the lack of awareness and the need for specialized laboratory tests to confirm diagnosis, the frequency of POW encephalitis may be greater than previously suspected.POW encephalitis should be included in the differential diagnosis of all encephalitis cases occurring in the northern United States, especially the Northeast. Laboratory tests for POW virus infection are not commercially available but can be requested through state public health laboratories for testing at CDC; however, Coppe Laboratories, right here in Waukesha, Wisconsin, has a direct and indirect test for Powassan virus. It requires a simple blood draw. http://wisconsinwoodlands.org/study-of-wisconsin-ticks/ In this article Coppe Lab collected more than 2,000 ticks and found borrelia(the causative agent in Lyme Disease) in more than half as well as a high number of POW/deer tick viruses in ticks of hyper-endemic regions of NW Wisconsin, and that ticks carrying disease are in almost every county in WI.
The virus is becoming more common in humans and appears to differ from Lyme Disease (borrelia) in that it is transmitted much more quickly (within minutes) and fatally (10-15% of cases), with 60% of patients who survive have permanent neurological dysfunction; however, please know that there is disagreement in the medical community on transmission times and much remains unclear. It is warned that only a single strain of POW has been used to determine vector competence or transmission time or viral amount to cause clinical illness. http://labs.russell.wisc.edu/wisconsin-ticks/powassan-virus/
https://wwwnc.cdc.gov/eid/article/23/8/16-1971_article A study in Marshfield, WI showed that when 95 patients were tested for suspected tick-borne disease, 66% showed evidence of current or prior Lyme infection. Of those patients, 17% had serologic evidence of acute POWV infection, demonstrating that POWV may affect more patients than we know.
The biggest challenge in addressing the Powassan infection will be distinguishing it from Lyme disease. The similarity of their etiology and symptomatology is extraordinary. If symptoms exacerbate rapidly, then that may be the critical sign that a Powassan virus is present.
http://naturalsociety.com/powassan-virus-ticks-now-carrying-virus-worse-than-lyme-disease/ The Powassan virus attacks the nervous system and can infect the brain causing inflammation (encephalitis). It can also affect the lining of the brain (meningitis). Symptoms vary widely from none to death. http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article Patients with POW infection typically exhibit encephalitis after an incubation period of 1–4 weeks.Fever and headache are common. Mental status changes, cerebellar symptoms (trouble with motor control, attention, and language), and weakness or paralysis in half of the body (reported in 50% of cases) are also common and may be severe. Results of CSF testing and brain imaging are generally consistent with viral encephalitis. Reverse transcription PCR of CSF, serologic testing of CSF, and serologic testing of serum are the preferred diagnostic tests, but they are not widely available. Pathogenesis is due to lymphocytic infiltration of perivascular neuronal tissue with a predilection for gray matter, including thalamus, midbrain, and cerebellum. Other symptoms include but are not limited to: fever, headache, vomiting, weakness, and memory loss.
http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article Case Report: On May 30, 2011 a 67-year-old woman from Aitkin, Minnesota checked into the Abbott Northwestern Hospital in Minneapolis, complaining of dizziness, high fever, chills, nausea and malaise, as well as intermittent confusion with slurred speech. As an avid gardener and hiker, the woman had been exposed to a number of vectors endemic to her area, such as deer ticks and mosquitos. She also had a long history of medical issues, including colon cancer, hypertension, cutaneous lupus, and a remote cerebral aneurysm, which was treated surgically.Although the patient was alert upon arrival at the medical facility, by the next day her condition severely deteriorated. Within hours she became unresponsive. Over night her breathing stopped completely and she required intubation. The patient remained in her comatose state for nearly two weeks before the medical ventilator was removed and she died. It was not until after the patient’s death that serological testing was able to identify Powassan Virus (POWV) as the disease agent.
Arbovirus Infection MnLA Jan 2016-3 Very informative slide presentation by Dr. David Baewer, Chief Medical Officer, Coppe Laboratories, Waukesha, Wisconsin.
Please discuss all treatment options with your health care professional
Antibiotics are not effective against viruses, and no effective anti-viral drugs have been discovered for POW, hence there is no specific treatment; however, there is much that can be done to improve the immune system, thereby, lessoning the effects of the virus, as well as taking medications to reduce brain swelling, respiratory support, and IV fluids.
http://health-truth.com/our-program/health-articles/chronic-fatigue-syndrome/how-to-conquer-the-viral-bacterial-syndrome/ According to Michael Biamonte, C.C.D., the immune system uses nutrients from food to manufacture substances that attack and kill viruses. Viruses help bacteria by invading the cells in an area, and if the immune system is too weak, bacteria begin to swarm the damaged cells invaded by the virus. As the virus begins to die having gone through its life cycle, the bacteria then start a secondary infection. For an MSIDS (multi systemic infectious disease syndrome) patient, they might be fighting borrelia (Lyme), Babesia, Bartonella, and many more pathogens, on top of viruses. This makes their disease much more complex.
Biomonte says to avoid sugar as it reduces the number of white bloods cells which fight off infection. He states that garlic is the most effective food against all infections as well as Echinacea, Zinc, water-soluble vitamin A, protein (stimulates the adrenal and thyroid), and eggs (containlarge quantities of lecithin).
http://science.howstuffworks.com/life/cellular-microscopic/light-virus.htm Interestingly, a study done at Arizona State and Johns Hopkins shows strong, quick blasts of purple light from a low power laser can kill viruses by vibrating and damaging their outer shells, but unlike other treatments doesn’t cause mutatations leading to viral resistance. Blood UV radiation, similarly to the laser, also kills viruses by breaking down their cell walls.
Anti-virals:
Green Tea
Licorice (glycyrrhizin)
Pau D-Arco
Olive Leaf
Elderberry
Zinc
Garlic
Echinacea
St. John’s Wort
Coconut oil
Eucalyptus oil
Vitamin C
Due to space constraints this article will ONLY cover the treatment of borrelia, the causative agent of Lyme Disease. To see treatments for the various co-infections, type Bartonella, Babesia, Mycoplasma, Parasites, Toxoplasmosis, or Powassan Virus treatment into the search bar for those articles. I hope to add to this list in the future. Please know a tick’s gut is often filled with 19 and counting pathogens with the potential to infect you with only one bite. This is an important but overlooked issue as many of these pathogens will not respond to doxycycline – the drug of choice for most uneducated general practitioners following the CDC/IDSA treatment guidelines.
Current research indicates many are infected with more than Lyme: Key quote:
“Our findings recognize that microbial infections in patients suffering from TBDs do not follow the one microbe, one disease Germ Theory as 65% of the TBD patients produce immune responses to various microbes.”
I believe that two reasons keeping many from improving are due to polymicrobialism (infection with more than one pathogen) and pleomorphism (the ability of many pathogens to shape-shift which helps them evade and survive treatment).
Mainstream medicine does not acknowledge these issues for Lyme/MSIDS and pretty much throws doxycycline at it which is adkin to throwing sand into the ocean.
Lyme Disease or borreliosis is caused by a Gram-negative bacterium belonging to the class of Spirochaetes, which have flagella allowing it to migrate through fluids and burrow through tissues, making it highly invasive. Borrelia burgdorferi is known for its outer surface proteins OspA and OspC which have a role in transmission into the host cell, whose metabolism is limited requiring Bb to rely on its host for energy precursors. Bb is slow growing, with a doubling time of 12-18 hours, unlike Strep or Staph which doubles every 20-30 minutes, which factors into the difficulty of diagnosis. This also necessitates longer treatment time for Bb as most antibiotics kill bacteria only when they divide. There are at least 37 known species, 12 of which are Lyme Disease related to date, and an unknown number of genomic strains; however, these numbers are constantly changing due to greater strain diversity than previously thought. Further complicating things, the strains differ in clinical symptoms and/or presentation as well as geographic distribution; however, again, to put Bb strain diversity into a geographical box is a huge mistake as the bird, reptile, fox, rodents, and humans are never confined to one location and migrate freely. Further complicating things, borrelia exists in four different forms. These are the spirochete, L-form (lives in cells), microscopic cyst form (non cell wall), as well as biofilm (a protective colony) The form can change shape whenever it feels threatened and can lie dormant until conditions are beneficial. Source
This is another important point because effective treatment will address ALL of these forms as well as any coinfections. Doxycycline, again, the drug of choice for most uneducated GP’s only addresses two forms of borrelia and won’t touch many of the coinfections at all. Many practitioners feel biofilmneeds to be addressed with biofilm busters. (Things like garlic, NAC, xylitol, coffee, cranberry, enzymes, chelation, & more)
Another very real issue that few are acknowledging is the fact the non-cell wall form can lie dormant for an opportune time to emerge. There is a link between Lyme/MSIDS and dementia, Alzheimer’s, MS, Autism, PANS, and other autoimmuneconditions.
Lyme Disease (LD) is the most common vector borne disease in the U.S with the CDC estimating that there are at least 476,000 – 547,000 new cases of LD diagnosed yearly, with actual infection rates much higher.
This 2022 article statesat least 1 in 7 people globally have had or have Lyme disease.
http://www.cdc.gov/media/releases/2013/p0819-lyme-disease.html “We know that routine surveillance only gives us part of the picture, and that the true number of illnesses is much greater,” said Paul Mead, M.D., M.P.H, chief of epidemiology and surveillance for CDC’s Lyme disease program. “This new preliminary estimate confirms that Lyme disease is a tremendous public health problem in the United States, and clearly highlights the urgent need for prevention.”
Testing, by the way, is abysmal for ALL Tick borne infections including Lyme, and a clinical diagnosis is required. Current testing doesn’t measure actual pathogens but an antibody response to infection. They also are blood tests which are problematic due to borrelia’s preference for tissues allowing it to evade the immune system. The CDC’s current two-tiered testing (ELISA followed by the Western Blot) is highly insensitive. The fact that over 300,000 new cases a year are recorded bely the fact that these arbitrary and stringent tests miss over half or more of all cases. It’s a no-brainer that actual infection rates are much higher.
It’s important to see a Lyme literate doctor (LLMD) because they are educated in the nuances of testing and treatment. Many of these doctors use IGeneX lab tests and do a provocative antibiotics protocol developed by Dr. Alfred Miller to help borrelia be more detectable.
For 21 days take (this will require a prescription from a treating physician):
Azithromycin orally 500 mg once a day
Flagyl orally 500 mg daily after you eat. You can substitute Tinidazole or Tindamax if Flagyl causes gastrointestinal symptoms.
There are over 300 strains of Bb worldwide and 100 strains in the U.S. to date. Please note that the current two-tiered testing only uses ONE strain. To get a positive would be akin to winning the Lottery.
It has since been determined that Lyme disease (named for the town in which it was first identified) can be caused by any number of different species in the genus Borrelia, such as: B. andersonii, B. japonica, B. valaisiana, B. lusitanie, B. turdae. B. tunakii, B. bissettii, and B. lonestari, and the most recent discovery of B. mayonii.
If you’ve been bitten by a tick, please utilize this great resource.
Most experts agree that prompt treatment is key to regaining your health. Taking a “wait and see” approach has been maiming people and needs to end. ILADS recommends treating immediately after a tick-bite with at least 20 days of doxycycline, and refutes the notion that one or two doses will prevent illness.
Borrelia inhabits the lumen of a tick’s digestive tract. The disease is transmitted to humans from a tick bite when the bacteria migrates up to the ticks salivary glands, and through the opening created by the tick. Ticks increase salivation during gorging, prompting the migration of the saliva from the digestive tract. Because migration from the gut takes a few days, transmission of the disease usually does not happen until after the first 24 hours of attachment. Please keep in mind; however, if spirochetes are in the tick’s salivary glands, theoretically, transmission could happen immediately despite the common CDC rhetoric that a tick must be attached for 36 to 48 hours or more.
Great video on transmission time by Lyme Action Network explains that mimimum attachment time has NEVER been established.
In this article we learn of a little girl that within 4-6 hours of tick bite developed facial palsy and couldn’t walk or talk.
Clinical diagnosis must consider any skin rash, regardless of its resemblance to the bull’s-eye. Many people never recall a rash or tick bite. “Researchers note that multiple textbooks and websites prominently feature the bull’s-eye image as a visual representation of Lyme disease.” They write, “This emphasis on target-like lesions may have inadvertently contributed to an underappreciation for atypical skin lesions caused by Lyme disease.” — Some Visible Signs of Lyme Disease Are Easily Missed or Mistaken, Science Daily, Apr 22, 2013.
This article shows that the percentages seeing the rash range from 27-80%, hardly a sure thing, but a rash is diagnostic for Lyme disease – no testing required.Read comment after article
An excellent primer on LD by Lyme Action Network (Approx. 5 min)
It’s highly likely that ticks are not the sole perp
The CDC states there is NO EVIDENCE that Bb is sexually transmitted and that congenital transmission (mother to fetus) is extremely rare, despite the fact Bb is a cousin to Syphilis, is in the spirochete family, and has been found in semen and vaginal secretions:
They also emphatically state pets cannot spread the disease to their owners and that you can not become infected by air, food, water, or bites of other insects. Please glance at the following animal studies on Bb before you believe everything you are told:
Listen to this brief 3 min Youtube of Dr. Lida Mattman, an expert on cell wall deficient forms, and her belief that Bb is spread by numerous routes other than ticks. Mattman isolated living Borrelia spirochetes in mosquitoes, fleas, mites, semen, urine, blood, plasma and Cerebral Spinal Fluid. With her colleague JoAnne Whittacker, Mattman did groundbreaking work on Lyme testing. Her Gold Standard Culture Method has disappeared thanks to the concerted suppression on microscopy. In 2004 she already claimed that she could not find any uninfected blood in the USA anymore. She studied borrelia for decades and was nominated for the Nobel Prize.
Excellent video explaining the horrible testing, possible biowarfare agentsincluding Lyme Disease (Bb), lab workers becoming infected at work, Plum Island’s work with ticks, the anti-trust investigation with testimony at 18:50 by Dr. Phillip in case after case for persistent (chronic) Lyme, at 35:30 clips of pathologist Alan MacDonald who’s getting 100% positive Bb in autopsies of Alzheimer patients, testimony of a woman who miscarried due to Bb, and much more).
Why the CDC continues to make such bold claims is foreign to me when there is so much at stake and much that is unknown or unproven. Prudence would err on the side of caution. Just a year ago a doctor showed up in an airport donning a hazmat suit and sign that read, “The CDC is lying!”
The box of myths the CDC, NIH, and ISDA has conveniently thrown all of the factors of this complex illness(es) into are already beginning to claw their way out with a new species of Bb and Bartonella being “discovered” just this past week. I predict much more yet to come.
Because testing is so abysmal, many Lyme literate doctors use the Horowitz questionnaire that you can print, fill out and take to your doctor.
If you have a preponderance of symptoms it’s highly likely you are infected.
Excellent, excellent article by Global Lyme Alliance on why Lyme is hard to diagnose and treat.
And lastly, for a fantastic overview, listen to Dr. Burrascano on the history of Lyme, and important considerations in treatment. He reveals a lot of information that doctors are oblivious to.
Support the body through detoxification & protect the gut (no sugar diet & probiotics are a must)
Cycle treatment. This means, once you are symptom-free for 2-4 months, stop treatment. If symptoms return, retreat according to symptoms. Burrascano has found that it typically takes 3-4 Cycles before a person remains symptom-free. The 3rd cycle often yields the worst herx in his experience, although he admits this hasn’t worked for everyone.
FOR EDUCATIONAL PURPOSES ONLY. PLEASE DISCUSS ALL TREATMENT OPTIONS WITH YOUR HEALTH PROFESSIONAL.
Antibiotic Treatment
A successful treatment should treat all three forms of borrelia. There is disparity between LLMD’s as to the timing of this but many state you should treat all three forms at the same time. However, at the first treatment take care to avoid an intense die-off reaction by starting one prescription antibiotic only. Too much inflammation is unhelpful.
Singleton states there are five classes of antibiotics commonly used for Lyme Disease (borrelia).
Tetracyclines are commonly used due to their ability to penetrate cell walls.
doxycycline (100-300mg twice a day with food, but not with dairy or minerals)
minocycline (100mg) twice a day. Both of these must produce high blood levels and may require monitoring. If they are not tolerated due to side effects, doxy may be administered intravenously and the dosage for that is 300-400mg once a day. *NOT TO BE USED IN PREGNANT AND BREASTFEEDING WOMEN OR CHILDREN 8 AND UNDER (current information debunks this – talk to your doctor) *SPACE ANTACIDS, DAIRY, AND IRON AN HOUR OR MORE AWAY FROM TETRACYCLINES *Notify your LLMD if you experience a severely unrelenting headache upon taking a dose
Macrolides and Ketolides, similar to Tetracyclines penetrate cell walls and tissues.
Telithromycin (800mg/day) – need to check electrocardiogram and liver function regularly
Clarithromycin (1,000mg/day)
Azithromycin (250-600mg/day) IV dose: (500mg/day) *Blood tests are needed to monitor liver function and white blood cell count. *Macrolides can interfere with other drugs. Make sure to talk to your doctor and pharmacist about other medications you are taking prior to beginning macrolide treatment.
Cephalosporins ideally should be combined with antibiotic classes that target the L-form of borrelia and, ideally, the cystic form also.
Ceftin (500mg 2X/day – some require higher dosages)
Omnicef (600mg daily)
Rocephin (IV) 1-2gms every eight hours and Claforan (IV)- 2gms daily – high blood levels need to be reached and levels should be measured regularly. *Regular blood testing should be done to detect any adverse reactions. Ceftriaxone can cause gallstones, which can be prevented by using ursodiol.
*People allergic to penicillins are also allergic to cephalosporins.
Penicillins also should be combined with other antibiotic classes that target the L-form (such as macrolides & Ketolides) and cystic form (Metronidizole).
amoxicillin (1,000-2,000mg every eight hours) sometimes combined with probenecid (500mg) or
Augmentin helps to keep blood levels high.
IV penicillin (1,200,000 units 2-3X/week). The LA form of Bicilin is more effective but painful than the CR form *NEVER USE IF ALLERGIC TO PENICILLINS
Metronidazole kills borrelia in the cystic form. Use in combination with one or more of the above classes to kill all three forms.
Metronidazole (250-500mg 2-3X/day)
*Do NOT use Tetracyclines with metro because they inhibit metro’s effectiveness)
*Do NOT use if on blood-thinning medications
*Do NOT use if pregnant
*Do Not use alcohol while on this medication
Tinidazole does this as well. Please see Dr. Eva Sapi’s work.Metronidazole led to reduction of spirochetal structures by ~90% and round body forms by ~80%. Tigecycline and tinidazole treatment reduced both spirochetal and round body forms by ~80%–90%. In terms of qualitative effects, only tinidazole reduced viable organisms by ~90%. Following treatment with the other antibiotics, viable organisms were detected in 70%–85% of the biofilm-like colonies.
I must also add that for those with significant neuro issues, antibiotics that cross the blood/brain barrier are imperative. One that worked for me was minocycline.
According to Ross, a successful borrelia treatment needs to boost the immune system, kill the infections, protect and repair the negative effects upon the body, and speed recovery.
He recommends staying on each of the natural medicines until you have marked improvement, then you can stop all naturals but probiotics, curcumin, ashwagandha, and a good multi-vitamin.
SLEEP:
L-Theanine 100mg 1-6 pills a night an hour before bedtime. Do not exceed 1200mg a day, and/or
Herbal Combinations 1-4 pills one hour before bed (valerian, hops, yam, wild lettuce, l-theanine, and others)
Prescription: Zolpidem (Ambien) 10mg 1 pill 30 min before bed (use if you have trouble getting to sleep as it is short acting), and/or Clonazepam (Klonopin) 1 mg .5-2 pills 30 min to 1 hour before bed. (use if you have trouble staying asleep). If you have both getting to sleep and staying asleep issues, try Ambien first.
CYTOKINE CONTROL: (At the beginning of treatment and when you change antibiotics, an excessive amount of cytokines are made making you feel worse.)
Curcumin 500mg 1 pill 3X/day
Good multi vitamin
ADAPTOGEN: (based on animal studies, adaptogens improve energy, immune function, and adrenal/thyroid function)
Ashwagandha 400mg 1-2 pills am and 1-2 pills between 1-2pm. Taking late will disturb sleep.
HORMONES: A person could have normal range testing for each of the hormones but still have clinically low hormones. Because of the unreliability of testing, treatment for low hormones should occur if there are clinical symptoms of low hormones as long as treatment does not increase hormone levels above the upper end of normal. Hormones provide many functions in the body. Proper levels improve energy and help the immune system to work more effectively.
ADRENAL INSUFFICIENCY:
Symptoms: fatigue, recurrent infections, poor recovery from infections, low blood sugar with shakiness and irritability relieved by eating, low blood pressure and dizziness on standing, afternoon crashing, and sugar cravings.
Naturals – Ashwagandha (same dosage and timing as listed above in Adaptogen)
Prescription – Cortef 5mg 1-2 pills am and 1-2 pills from 1-2pm. Taking late will disturb sleep.
LOW THYROID:
Symptoms: Low thyroid: fatigue, achiness, low body temperatures averaging below 98.0 F, cold intolerance, weight gain, constipation, and changes in menstrual periods.
Naturals – good multivitamin to provide essential micronutrients for the thyroid
Prescription – Desiccated Thyroid 1/2 grain or Armour Thyroid 1/2 grain. 1 pill in the morning 30 min before anything else but water (empty stomach). Increase every 3-4 weeks by 1/2 grain if low thyroid symptoms persist.
According to Ross, “Low hormones occur often in chronic Lyme disease. Inflammatory cytokines made by white blood cells to fight Lyme decrease the effective functioning of an area of the brain called the hypothalamus and pituitary. This part of the brain produces chemicals that induce sleep and that regulate hormonal systems. Normally this part of the brain releases messengers such as thyroid stimulating hormone (TSH), adrenocorticotropin hormone (ACTH), and follicle stimulating hormone (FSH) to stimulate the thyroid, adrenal glands, and sex hormone organs respectively. Because of the dysfunction caused by the cytokines, these regulatory messengers are released based on an incorrect interpretation by the brain of the hormone environment. Thus measurements of these messengers is an unreliable way to determine the hormone status. Another way to check hormone status is to measure the actual hormone levels like T4/T3 (thyroid), or cortisol/dhea (adrenals), or estrogen/progesterone/testosterone (sex hormones). These tests give a broad range of normal, however.”
It has been my personal experience that most general practitioners do not think for themselves when it comes to hormones. Similarly to how they hide behind the CDC guidelines, they hide behind test results and refuse to diagnose and treat patients clinically.
For excellent information on thyroid disorders please watch: Dr. Brownstein.
ESSENTIAL MICRONUTRIENTS:
Multivitamin: Use a vitamin that has numerous amino acids, antioxidants, minerals, and various vitamin Bs including b12 and folate. He prefers vitamin powders from Thorne and Integrative Therapeutics.
YEAST:
Probiotics – use a product shown to repopulate the intestines in scientific studies. Take at least 10 billion live cultures 1 hour away from antibiotics. During an active yeast infection consider increasing to 20 billion cultures one time a day or divided in to two doses.
Antifungals:
Natural medicine: Herbal Combinations. 2 pills 2 times a day. (Common herbs found individually or mixed together include: pau d’arco, caprilic acid, rosemary oil, thyme oil, garlic, and grapefruit seed extract.) Will take 3-4 months to get yeast overgrowth under control.
Prescription medicine: Nystatin 500,000IU 2 pills 2 times a day.
*You may add Fluconazole (Diflucan) 200mg 1 time daily for 30 days combined with nystatin for prevent drug resistance for a yeast overgrowth problem.
BORRELIA TREATMENT:
(Take either the naturals or the prescriptions, but not both together at the beginning; however, you may do so later on)
First Month
Naturals (work 85-90% of the time)
Otoba Bark Extract and Cat’s Claw 5 drops 2X/day of each and increase every 2 days by 1 drop per dose till taking 30 drops 2X/day. Take on an empty stomach. Do not take 30 min before through 2 hours after having food, medicines, or supplements. If you Herx, do not advance dosage until it decreases.
Prescriptions
Doxycycline 100mg 2 pills 2X/day or 4 pills 1X/day. Take with food to prevent nausea. Do not take with calcium supplements or dairy or milk substitutes like rice milk. OR
Clarithromycin (Biaxin) 500mg 1 pill 2X/day
*Both of these antibiotics treat the L-form and the spirochete form. B. After First Month
Naturals
Remain on same as they kill all 3 forms of Lyme.
Prescriptions Work with LLMD to add additional antibiotics to treat all 3 forms of Lyme. You need to add an antibiotic to kill the cyst form of Lyme.
DETOXIFICATION:
Eat organic
Avoid gluten, alcohol and tobacco, and synthetic scents
Lower stress
Multivitamin to support liver detox
Drink good water (1/2 of your ideal body weight in lbs. as ounces)
2-3 servings of beans, legumes, or whole grains/day. Fiber helps you detox.
Exercise – at a tolerable level *Special Considerations for 6 months & beyond:
Detox treatments for MTHFR methylation defect, lyme and mold biotoxins, and heavy metals
Biofilm treatments
Chronic viral infection treatments
Autoimmune illness treatment such as Low Dose Naltrexone (LDN)
Yeast treatments
(Ups and downs in treatment is normal; however, if there is a significant decline after you are doing better, consider yeast (increased sugar cravings, intestinal gassiness or bloating, recent vaginal yeast infection, oral yeast, and/or vaginal or rectal itching), or a co-infection such as Bartonella, Babesia, or Mycoplasma. Please do Dr. Schaller’s checklists for these coinfections and discuss these possibilities with your health care professional)
Dr. Horowitz’s Lyme Treatment:
(Derived from his book Why Can’t I Get Better? Solving the Mystery of Lyme and Chronic Disease)
Combine antibiotics to address the 3 forms. Use enzymes to address biofilms, and continue until patient is symptom-free for 2 months.
Cell Wall form:
amoxicillin (500-875mg 2-3X/day) with probenecid 500mg 1X/day with meals. He states to check the peak (12-15 is optimal) and trough levels which may necessitate increasing the dose. Avoid probenecid if there is a sulfa sensitivity or use with caution if has kidney stones.
Augmentin (875-1,000mg 1-2X/day) alone or with amoxicillin.
IM Bicillin 1.2 million units 2-4X/week. Use Emla or lidocaine cream 1 hour prior to injection & massage area 2-3 minutes after and repeat several times per day.
Ceftin (500mg 1-2X/day)
Omnicef (300mg 1-2X/day)
Cedax (400mg 1-2X/day)
Suprax (400mg 1-2X/day)
*For those with significant CNS disease, or who have failed oral medications:
IV Rocephin (2g daily 5-7days/week, up to 2g every 12 pulsed 4-5 days/week). Use Actigall (300mg) 1X/day to prevent sludge and gallstones. Check CBC and CMP with liver functions every two weeks and use liver support (NAC, ALA, Hepa #2, milk thistle) as necessary.
IV Claforan (2g every 8-12 hours) may used instead of Rocephin if there are gallbladder problems. Check blood work as with Rocephin.
IV vancomycin (1-1.25gm/every 12 hours)
IV Primazin (500mg every 6 hours)
IV Cleocin (600mg every 8 hours or 900mg every 12 hours)
Cystic Forms: (also known as L forms, S-forms, spheroplasts, and non cell wall forms)
Plaquenil
Grapefruit seed extract (use when can’t take plaquenil or when have yeast issues)
Flagyl – pulse either several days in a row per week or two weeks on, two weeks off
Tindamax – pulse same as Flagyl
*Avoid alcohol when taking Flagyl and Tindamax
*Horowitz uses high doses of B6 and B12 and nystatin to decrease side effects
Intracellular Forms: Macrolides
Zithromax (250mg 1X/week with meals.
Biaxin or Biaxin XL (250mg 1X/day)
Tetracyclines: (Do not mix with dairy, antacids, or vitamins and minerals, avoid direct sunlight, and do not lie down within an hour of ingestion to avoid reflux esophagitis)
Doxycycline (100mg 2X/day with meals)
Minocycline (50-100mg 2X/day)
Tetracycline 250mg or 500mg 1-2 g per day total, 2X/day
Quinolones: (Do not use if pregnant, do not mix with antacids, or vitamins with minerals)
Cipro (500mg 2X/day)
Levaquine (500mg 1X/day)
Avelox (400mg daily)
Factive (320 daily)
*Check QT interval on Quinolones as well as drug interactions
*Advise patients of tendon issues and do not exercise vigorously. Discontinue if tendon pain starts. Take ALA, curcurmin, and magnesium to decrease side-effects.
*Consider pulsing these in 5 day cycles to reduce tendon damage.
Rifampin: (150mg to 300mg 2X/day) Do not use if pregnant. Use with another intracellular to avoid resistance.
**Update**
Dr. Horowitz has recently added Mycobacterium drugs (used for leprosy) on his most treatment resistant patients. Horowitz reports that the Dapsone and PZA protocols have been the most effective treatment additions for resistant Lyme and autoimmune symptoms, with PZA being the most effective for dermatological manifestations of Bahcet’s and arthritic/granulomatous changes.
Double-dose Dapsone Combination Therapy study: Case study of 3 patients with relapsing and remitting Lyme disease as well as a retrospective chart review of 37 additional patients undergoing DDD CT therapy (40 patients in total) was also performed, which demonstrated tick-borne symptom improvements in 98% of patients, with 45% remaining in remission for 1 year or longer.
For an excellent interview with Dr. Horowitz: https://on-lyme.org/en/sufferers/lyme-stories/item/255-is-there-hope-for-lyme-patients-interview-with-dr-richard-horowitzTakeaway: I do not have to put a PICC-line in or use IV ceftriaxone in many of these people because the dapsone protocol combined with doxycycline and rifampin is turning out to be an excellent protocol. It gets good penetration into the central nervous system. Many of my patient’s symptoms are getting better with this protocol, including resistant fatigue, joint/muscle and nerve pain, memory and concentration problems, as well as their sleep and mood disorders. Here he discusses this therapy and its effectiveness on biofilm.
Please remember that you can jump immediately to late disseminated Lyme without noticing any of the previous stages and while the literature often categorizes these stages with time frames, it is often the case that reality is far different. He also goes into co-infection treatment as well.
I can’t overemphasize the need to consider the coinfections that typically come with Lyme (borrelia). This fact is not being considered by mainstream medicine, to the detriment of patients. All the doxy in the world thrown like napalm is not going to cure this. For instance, if a person has parasitic involvement, they will need anti-parasitic medications. Some patients have nematode (worm) involvement which requires anthelmintics such as Ivermectin and Albenza. Research has shown that spirochetes have hidden in worms to go undetected. Until the worms are killed, the spirochetes can’t be touched by antibiotics. Borrelia is considered a stealth organism – quite adept at hiding within the human body.
Recently, due to its success for COVID, some are claimingivermectin with doxycyline‘cures’ Lyme disease. While doxy has been proven to be a good front-line drug for Lyme as well as numerous coinfections, as stated before, it alone is insufficient for treating this. Ivermectin, on the other hand, while a great anti-viral, and proven anthelmintic (dewormer), to my knowledge has no mode of action against gram negative bacteria – not to mention other parasites that typically come with this. Upon reflection, one possible mode of action is due to the fact since ivermectin kills worms, and borrelia has been found hiding in worms, perhaps killing the worms is exposing the spirochetes to the doxycycline to finally be killed or disabled, allowing for the immune system to do its work.
Dr. Makis Protocol for Tick-borne infections (TBIs):
24 mg of Ivermectin per day for 2 weeks
222 mg of Fenbendazole per day for 2 weeks.
If still seeing symptoms, do another regiment of:
36 mg of Ivermectin per day for 2 weeks
444 mg of Fenbendazole per day for 2 weeks.
One patient did 24 mg of Ivermectin and 300 mg of Fenbendazole per day for 2 weeks successfully and didn’t require the larger doses.
Personally, I will add that I too do not require high doses of ivermectin for COVID. 12mg for 5 days does the trick every time. My husband takes 24-36mg for COVID.
One of the most difficult issues is Lyme/MSIDS tricks the immune system into inaction. Ivermectin theoretically could be removing a hiding place for borrelia. I will be interested in following patients who are using ivermectin for tick-borne infections (TBIs). My son is one of them as he recently contracted STARI from a lone star tick. He was treated with minocycline(easier on the gut than doxycyline and crosses the blood, brain, barrier more effectively, is neuroprotective, anti-inflammatory, inhibits malignant cell growth, and more), diflucan(for any candida),pulsed tinidazole(only antibiotic with 90% effectiveness against viable forms of borrelia. Take for two successive days.), and EBOO, which not only is an antimicrobial but oxygenates the entire body assisting the immune system and detoxification. He also did red light therapy and frequent saunas.
Alternative Treatments
The Cowden Protocol:https://www.youtube.com/watch?v=DLuQk5Zs2Fo and http://www.nutramedix.ec/ns/lyme-protocol (PDF’s and videos to watch)
This herbal program utilizes 14 different Nutramedix products including 6 Microbial Defense herbals that are taken rotationally over at least 6 months. Richard Horowitz, MD in New York State has found the Cowden Support Program to be effective in markedly improving the condition of 70-80% of the advanced Lyme Borreliosis patients with co-infections over 4 to 6 months’ time, even if the patients had previously failed to improve on multiple courses of antibiotics.
Master Herbalist Stephen Buhner’s Herbal Protocol: http://buhnerhealinglyme.com (Please check this website for updates on treatments)
Japanese knotweed – Source Naturals Resveratrol with 500mg Polygonum cuspidatum per tablet) 1-4 tablets 3-4X/day for 8-12 months or for tincture dosage:
150lb – 1 tsp 3X/day
100lb – 2/3 tsp 3X/day
60lb – 1/3 tsp 3X/day
30lb – 1/5 tsp 3X/day
Cat’s claw (Uncaria tomentosa) Raintree brand, 1-4 tablets 3-4X/day for 2-3 months, then 2-3 capsules 3X/day or for tincture dosage: same as knotweed above.
Eleuthero (Eleutherococcus senticosus) HerbPharm tincture, 1/2 to 1 tsp upon rising and at lunch for all weights.
Astragalus (Astragalus membranaceus) 1,000mg daily (not to be used in chronic Lyme) or for tincture dosage: same as knotweed except for:
60lb – 1/2 tsp 3X/day
30lb – 1/3 tsp 3X/day
Ashwagandha (withania) 1,000g at night before bed for sleep issues and brain fog.
If you have questions, you may post them to Stephen at: www.PlanetThrive.com/category/experts/buhner/. I highly recommend all of Stephen’s books.
As to duration of treatment – this varies highly; however, according to the most experienced Lyme literate doctor in the state of Wisconsin, treatment cases in the 70’s resolved within a month to a year, while current cases are taking three and more years. Many LLMD’s (Lyme literate doctors) recommend a maintenance program for life.
I know this is overwhelming. Take a deep breath and put one foot in front of the other. One day at a time. Trust me, before long you will be a quasi expert in all things TBI (tick borne infections).
You do need to get to an LLMD(Lyme literate doctor). Regular practitioners at this point do not believe in the severity and complexity of MSIDS(multi systemic infectious disease syndrome or Lyme with friends). They will not treat you properly with various and extended antibiotics and/or naturals. Research shows that most are infected with more than borrelia, the causative agent of LD, and have various coinfections such as Bartonella and Babesia complicating our cases. According to Horowitz, research shows that a person with both Babesia and borrelia are three times sicker than if they just had LD. This is important to acknowledge and frankly, most GP’s are clueless on all of this. These stealth pathogens are experts at fooling your immune system and they work symbiotically together and actually morph inside your body by changing their outer surface proteins to be different than when they entered.
Realize you have a lot to learn. Learn it. Then, be your own advocate. This is not going to be a sprint, and it’s far from fun. It’s going to be a marathon, so strap yourself in for a wild ride. If you are able, get to a Lyme Support Group to learn and be around others on the same journey. We learn from each other. If you aren’t able to get to a physical support group, I highly recommend getting on an on-line support group. You can ask questions and read others’ experiences. On the right hand side of the website, scroll down until you see “On-line Support Groups.” Click and join. Also, if you want to receive an email each time I post educational materials or meeting times for the Madison Lyme Support Group, pop me an email, I’ll send you an invite, and you will get an email directly to you when I post. This is convenient because I always send reminders for meeting times! You can also type in words in the search bar for articles to help you learn. For instance, from here, I’d recommend “Tips for Newbies,” as this complex is far different than anything you’ve experienced. Also, if you are struggling with cognitive and/or psychological issues, please type “Psychological Aspects of Lyme,” into the search bar.
No, you aren’t crazy, you have a brain infection which makes you feel crazy. Treatment will resolve these issues.

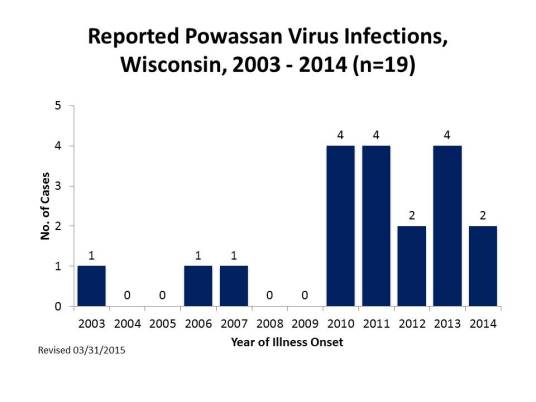
 Graphic from







 Madison Area Lyme Support Group
