Archive for the ‘Treatment’ Category

Why We Can’t Get Better

Most MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) sufferers are familiar with Dr. Horowitz, a famous and gifted LLMD (Lyme Literate Doctor) who wrote the book, “Why I Can’t Get Better?  Solving the Mystery of Lyme and Chronic Disease.”  I just noticed you can get it new for $7.99 – the best eight bucks you’ll ever spend!  I warn you; however, it’s deep and it’s wide, and you will be looking up a few terms unless you’re a M.D. http://www.amazon.com/Better-Solving-Mystery-Chronic-Disease/dp/1250019400

In fact, he’s the person who came up with the term MSIDS as it more adequately explains what’s going on in most patients diagnosed with “Lyme Disease,” as research shows we are typically infected with multiple pathogens making our treatment pictures far more complex than most GP’s realize and is also a very good reason why people don’t get better.  This issue is what he discusses in the following videos.  For some of you, you just can’t get on top of things – even after years of treatment.  There can be numerous reasons for this but the following videos may enlighten both you and your doctor.

Working with an LLMD is definitely a partnership.  In the beginning, unless you’ve watched someone go down this pot-hole riddled road, you know very little other than the fact that your body’s going to hell in a hand basket!  As time progresses, you talk to others, watch videos, read books, and become an on-line researcher learning things you never in your wildest dreams would have thought about learning (the life-cycles of ticks).

For those of you who are new to the journey, you want to get someone you know up to speed quickly, or if you need a refresher course, these videos will do it.  Horowitz is engaging, intelligent, and funny.  The first video is only 8 minutes long and explains the nuts and bolts of how he came to his current knowledge.

The second video is an hour long, but definitely worth watching.  In a much more detailed fashion, it explains many symptoms of the various coinfections that could be holding up your progress unless you are dealing with them.  Watch these videos, take notes, and go back to your doctor and discuss these possibilities.  Remember, testing for all of these pathogens is extremely poor and not to be solely relied upon for diagnosis.  It’s important to “study thy enemy,” so you understand him and know how to combat him.  In this case the more you know about the various pathogens and how they affect the human body the better.

Published on Nov 3, 2014
At the “Symposium on Tick-borne Diseases” held May 17, 2014 at the Hyatt in Cambridge, Maryland, Dr. Richard Horowitz provided insights into the many diseases humans are contracting from ticks, and he helps us to differentiate between the different illnesses. The event was hosted by the Lyme Disease Association of the Eastern Shore of Maryland (soon to be the Lyme Disease Association of Delmarva), a 501(c)(3) non-profit organization providing educational resources on tick-borne diseases. This and other videos from the Symposium were made possible by a very generous private donation for which we are very thankful to have received. The wonderful videographer/editor for the event was Bryan Krandle (krandle86@yahoo.com). If you enjoy having wonderful resources like the videos from this conference, please consider a donation to the LDAESM, P.O. Box 5360, Salisbury, Maryland 21802. Thank you!

Tick Removal

http://www.abc.net.au/health/features/stories/2015/02/12/4178721.htm

Some recommend using tweezers being careful to avoid squeezing the tick, which would cause it to inject its stomach contents into you; however, others are now recommending aerosol freezing sprays or ether-containing sprays that instantly kill the tick. This approach is recommended by the Australasian Society of Clinical Immunology and Allergy (ASCIA) for those with a known tick allergy. Since Australia contends with a tick that causes a severe allergy to red meat, they are recommending the ether sprays which will not disturb the tick, thereby lessening the chance of it injecting more of its allergen-containing saliva.  

Dr Cameron Webb, a medical entomologist at Westmead Hospital and clinical lecturer at the University of Sydney, has been looking into the various methods of tick removal and thinks we should all be following the advice of ASCIA, which recommends killing the tick in place by using ether-containing aerosol sprays that instantly freeze it (although some of these are not registered for use in humans). He suggests some over-the-counter products for freezing off warts may work.

Wartner may be the perfect fix.  http://www.wartner.eu/uk_en/warts-and-verrucas/treatments/wartner-wart-verruca-remover/

http://www.wartner.eu/warts-verrucas/treatments/wartner-cryotherapy/

PRODUCT CHARACTERISTICS

Freezes the tick to the core by –50°C  (lowest temperature available within self treatments), it says to press applicator firmly down for 3 seconds, then hold on tick for 40 seconds.  Let tick fall off naturally – takes approximately 10 minutes.               
Using DMEP gas mixture
New application steps to reach therapeutic temperature any time
http://www.walgreens.com/store/c/wartner-cryogenic-wart-removal-system%2c-original/ID=prod3984640-product

Ingredients:  Dimethyl Ether, Propane

Extremely Flammable. Contents Under Pressure Keep away from fire, flame and heat. Do not smoke while using this product. Protect from sunlight and do not expose to temperatures above 120°F. Store at room temperature away from heat.

Keep out of reach of children. Avoid contact with eyes. Do not inhale vapor/spray and use only in well-ventilated areas. Do not Swallow. For external use only. Use only as directed. If Wartner® is not used exactly as instructed or if you mistakenly apply it directly to the skin or use it on conditions that are not warts, it may cause serious burns and permanent scarring of the skin.

Wartner® should only be used in combination with the applicators provided. Use one foam applicator for session.  Do not reuse applicator.

I knew this product was it when I read a review:

“Pros: great if you want to torture your worst enemy”

How did they know?


Anaplasmosis Treatment

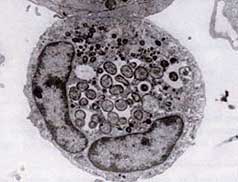
3-phagocytophilum

Ultrastructure of A.phagocytophilum by transmission
electron microscopy. Photo by V.Popov, reprinted
from Dumler JS et al. Human granulocytic
anaplasmosis and Anaplasma phagocytophilum.
Emerg Infect Dis;11:1828-34.

http://www.health.state.mn.us/divs/idepc/diseases/anaplasmosis/hcp.html

Human anaplasmosis (HA), formerly known as human granulocytic ehrlichiosis (HGE), is a small, obligate, gram-negative bacterial disease that is unusual in its tropism to neutrophils, and is caused by Anaplasma phagocytophilum, a rickettsial bacterium. It was first recognized in 1990, when a western Wisconsin patient developed a severe febrile illness following a tick bite and died two weeks later; however, it has been known to cause disease in animals since 1932. Human ehrlichiosis, a similar disease, is caused by Ehrlichia chaffeensis and is found throughout much of southeastern and south-central United States. Another related form of ehrlichiosis caused by the Ehrlichia muris-like agent was identified in Minnesota and Wisconsin patients in 2009. The median age of patients with HGA is around 50 years old. Over 4000 total cases have been reported in the CDC’s Morbidity and Mortality Weekly since the disease became nationally reportable; as with most tick-borne diseases, the true incidence is suspected to be considerably higher.

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC2882064/   Cases occur year-round, with a peak incidence during June and July, perhaps reflecting the shorter arthropod season in these northern states or the relative importance of the nymphal stage of Ixodes ticks in disease transmission. Given the ubiquity of the tick vector, it is not surprising that cases of HGA have been confirmed world-wide, including Europe and Asia (China, Siberian Russia, and Korea).

In dogs, persistent infection has been reported to last over 10 years and in the absence of treatment can persist for the life of the dog. Other strains persist for months and then are naturally cleared.

Transmission:
http://www.health.state.mn.us/divs/idepc/diseases/anaplasmosis/hcp.html
http://www.capcvet.org/capc-recommendations/ehrlichia-spp-and-anaplasma-spp1/ Anaplasmosis is known to be transmitted to humans by Ixodes scapularis (blacklegged tick or deer tick), the same tick that transmits Lyme disease (borrelia). It can also be transmitted via blood transfusion and contaminated needles or surgical instruments.  

Symptoms:

Onset of illness occurs 5 to 21 days after exposure to an infected tick. Infection can range from asymptomatic infection to fatal disease. Common signs and symptoms include fever (often over 102°F), chills, headache, and myalgias.  Nausea, vomiting, anorexia, acute weight loss, abdominal pain, cough, diarrhea, and change in mental status are reported less frequently. Highly suggestive laboratory findings include leukopenia – a decrease in white blood cells making you more susceptible to infection (WBC< 4,500/mm³), thrombocytopenia  – a decrease in platelets causing bruising and bleeding (platelets <150,000/mm³), and increased aminotransferase levels – relating to liver damage. Most of the damage it causes appears to be related to host inflammatory processes, as there is little evidence of a correlation between the number of organisms and host disease severity.

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html

Compared with HME (human monocytic ehrlichiosis), HGA (human granulocytic anaplasmosis) appears less likely to involve the central nervous system, but peripheral neuropathies are more common and can last weeks to months. Among the neurologic findings reported in the medical literature are facial palsy, demyelinating polyneuropathy and brachial plexopathy. Respiratory distress syndrome and a septic or toxic shock-like syndrome have been reported, but appear to be less common than in HME. The overall fatality rate from HGA also seems to be slightly lower than that of HME, with most of the deaths resulting from opportunistic infections (for example, herpes simplex esophagitis, Candida pneumonitis, and pulmonary aspergillosis) in immunocompromised patients.

Unusual presentations may be the result of coinfections with Borrelia burgdorferi (Lyme disease agent) and/or Babesia microti (babesiosis agent), as a single feeding tick may transmit multiple disease agents.

Cases of HA acquired through blood transfusions have been documented. Include HA in the rule-out for patients who develop a febrile illness with thrombocytopenia following blood transfusion. Suspected transfusion-associated anaplasmosis should be reported.

Prevalence:

A large survey by Lymedisease.org found that 53% stated they had coinfections and 30% responded they had two or more coinfections.  Similar results were found in Canada.  While the most common coinfections found in Canada were Bartonella (36%) and Babesia (19%), Anaplasma took third place (13%).  https://www.lymedisease.org/lymepolicywonk-study-finds-coinfections-in-lyme-disease-common-2/ Here in the U.S. the results showed that 5% of patients with Lyme also had Anaplasmosis; however, please realize most doctors are not looking for this, the testing is poor, many states don’t require reporting and many cases go unreported. In 2014, there were 2800 confirmed cases of HA.  Rhode Island, Minnesota, Connecticut, Wisconsin, New York and Maryland are the hotbeds.  https://www.cdc.gov/mmwr/volumes/65/rr/pdfs/rr6502.pdf

Master Herbalist, Stephen Buhner, in his book Natural Treatments for Lyme Coinfections (Anaplasma, Babesia, and Ehrlichia states on page 24, “In other words, if you want to successfully treat someone who is infected with a vector-borne infection you need to realize up front that it is usually the case that coinfection has occurred and you have to look at the interactive picture, not merely single infectious agents.”  Demonstrating another unique interplay, one study found that ticks express an antifreeze type substance to enhance survival when they are infected with Anaplasma. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2929727/  In the world of microbes there is definitely a “You scratch my back, I’ll scratch yours.”

Tests:

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html
Standard blood tests in HGA usually reveal findings similar to those seen in HME: leukopenia, thrombocytopenia and liver function abnormalities (elevated transaminases). However, the hematological abnormalities frequently resolve by the second week of symptoms, so their absence should be interpreted in that context if patients are presenting later in the course of their illness. In general, empiric antibiotic treatment should be considered for patients in endemic areas who present with an acute febrile illness suggestive of HGA. For specific diagnosis, Wright or Giemsa-stained blood smears have a slightly higher yield than with HME, but are still not optimal for general clinical utility, given that there appears to be a wide variation (25-75%) in the sensitivity of these tests in visualizing morulae in host neutrophils. More helpful, but not always available, are polymerase chain reaction (PCR) tests, which are estimated to have a sensitivity of 67-90%. Prior antibiotic therapy dramatically reduces the sensitivity of both  of these diagnostic methods. Serologic testing is useful to confirm the diagnosis of anaplasmosis. The most commonly used method is indirect immunofluorescence (IFA) of IgM and IgG anti-A. phagocytophilum antibodies. Seroconversion is perhaps the most sensitive laboratory evidence of A. phagocytophilum infection, but is not always obtained in a timely enough manner to provide useful input on clinical (i.e., treatment) decisions.

According to the CDC:
Any two of the following three tests for evidence of infection with Anaplasma phagocytophilum are recommended:
*An indirect immunofluorescence assay (IFA) is the principal test used to detect HA infection. Acute and convalescent phase serum samples can be evaluated to look for a four-fold change in antibody titer to A. phagocytophilum.
*Intracellular inclusions (morulae) also may be visualized in granulocytes on Wright- or Giemsa- stained blood smears.
*Polymerase chain reaction (PCR) assays are being used increasingly to detect A. phagocytophilum DNA.

According to animal studies, morulae are usually difficult to find in blood smears, even during the acute stage of disease. It is also stated that serology may be helpful in identifying antibodies but may not detect early infections during the acute phase of disease.

88_anaplasma316x316Courtesy of Lymestats.org

Treatment: Discuss all treatments with your health care professional

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html
The optimal dose and duration of antibiotic treatment for anaplasmosis has not been definitively established, but it is clear that A. phagocytophilum is highly sensitive to tetracyclines. Thus, oral doxycycline is the recommended treatment, at the same dose used for Ehrlichia infections: 200 mg/day in two divided doses. The usual treatment duration is 5-10 days, which is extended if there is suspected coinfection with B. burgdorferi, the agent of Lyme disease. In any case, treatment should continue for at least three days after the patient’s fever resolves. Response to treatment is usually rapid; if the patient remains febrile more than two or three days after initiation of doxycycline therapy, the diagnosis should be revisited.
As with Ehrlichia infections, rifampin is used in cases where doxycycline is contraindicated, such as pregnancy or allergy. Rifampin has also been used successfully in pediatric cases, and thus is sometimes employed in mild cases of pediatric A. phagocytophilum infection. If coinfection with B. burgdorferi is suspected in a pediatric case, doxycycline is sometimes used as an initial treatment for 3-5 days, with another antibiotic employed thereafter to complete the somewhat longer recommended treatment period for early Lyme disease.

Treatment according to the CDC: (Notice the dose is lowered)

http://www.cdc.gov/rmsf/doxycycline/index.html

HA patients typically respond dramatically to doxycycline therapy (100 mg twice daily until the patient is afebrile for at least 3 days). Other tetracycline drugs also are likely to be effective. In general patients with suspect HA and unexplained fever after a tick exposure should receive empiric doxycycline therapy while diagnostic tests are pending, particularly if they experience leukopenia and/or thrombocytopenia.
http://www.jpeds.com/article/S0022-3476(15)00135-3/pdf?ext=.pdf

According to the CDC, Doxycycline is the most effective antibiotic for the treatment of suspected rickettsial infections for all ages, including Rocky Mountain Spotted Fever, and delay in treatment may lead to severe illness and/or death. Children are five times more likely than adults to die from RMSP and a new study found that short courses of doxy can be used in children without causing tooth staining or weakening of tooth enamel. Prior to this, doctors were reticent using Doxy due to studies in the 50’s showing a link between Tetracycline (binds to calcium) use in young children and tooth weakening and staining. Doxy, a newer medication, binds to calcium less readily and, according to the CDC, if used in the correct dose and duration for rickettsial diseases, should cause no harm. It’s also the treatment of choice according to the American Academy of Pediatrics (AAP). Doxycycline treatment should be continued for at least 3 days after fever resolves, and the usual duration of therapy is 7-10 days.  Chloramphenicol is considered a second-line therapeutic agent, as it is significantly less effective at preventing fatal outcome; other broad-spectrum antimicrobial agents typically used to treat sepsis are not effective at preventing fatal outcome due to RMS.

http://www.ilads.org/lyme/what-to-do-if-bit-by-tick.php
According to ILADS (International Lyme and Associated Diseases Society) Doxycycline has the advantage of treating numerous tick borne illnesses such as Lyme (borrelia), Ehrlichia, Anaplasma, Q Fever, and Rocky Mountain Spotted Fever. They state the downside is that Doxy causes significant sun sensitization, can be hard on the stomach, and the usual dosing may not reach therapeutic levels.
Recent data suggests that treatment may not clear organisms in animals.

If you find a doctor willing to become properly educated on tick borne illness, please give them this link:  https://madisonarealymesupportgroup.com/2017/06/20/help-doctors-get-educated-on-lyme-and-tick-borne-illness/

Anxiety

Suffering with anxiety while fighting MSIDS (multi systemic infectious disease syndrome) can be debilitating.  I remember the days when my husband would literally start shaking while talking with people.  He never knew when it would strike.  He could be having lunch with a sales rep or standing in the foyer of someone’s home.  He dreaded it, and I felt completely helpless.  He is completely free of anxiety after three years of treatment.  And while I feel treatment is truly the answer, there are often things we have to do to assist our bodies.

https://www.youtube.com/watch?v=rQS3oPTgDmM  Published on Apr 23, 2015  Could diet and nutrition be central determinants of mental health? Find out when Trudy Scott, CN, provides evidence presented at The Anxiety Summit, seasons 1 and 2, which has showcased vitally important research now available to integrative practitioners and to people who suffer with anxiety, panic attacks, social anxiety and OCD. The gut-brain connection and microbiome, methylation, adverse effects of benzodiazapines, the role of inflammation, and controversial opinions about serotonin, GABA and urinary neurotransmitter testing are a few of the concepts that will be shared.

https://www.youtube.com/watch?v=5wP1xFcXFZo  Published on Feb 21, 2014  “Using Targeted Individual Amino Acids to Overcome Anxiety, Panic, Worry, Negativity, Cravings and Emotional Eating” with Food Mood Expert Trudy Scott

Supplementing with specific individual amino acids can raise neurotransmitter levels and balance brain chemistry, alleviating anxiety, fear, worry, panic attacks, and feeling stressed or overwhelmed. They can also be supportive in addressing other issues that contribute to or exacerbate anxiety, such as sugar cravings, emotional eating and addictions. In addition, supplemental amino acids can help with depression, PMS, poor focus/ADHD and insomnia, which often co-occur with anxiety.

This presentation will cover symptoms of low serotonin, low GABA, low endorphins, and low catecholamine neurotransmitters. How to raise these neurotransmitter levels with the amino acids l-tryptophan, GABA, d- phenylalanine (DPA) and l-tyrosine, thereby improving mood and ending emotional eating will be taught. The use of glutamine to stabilize low blood sugar, leading to improved mood and gut health will also be addressed.

Trudy says: “The amino acids are key to the success of my practice. They help my clients eliminate stress-eating, and make food changes without feeling deprived and only having to use willpower. My clients feel calm and happy right away, giving them hope, while their other health and nutritional challenges are addressed. Many people suffering from various health concerns could receive tremendous relief with the proper use of amino acids”.

Quite often with MSIDS, we find ourselves dealing with side issues.  Which came first, the infection of MSIDS or the condition?  In nearly every case, the science is completely lacking, but unless dealt with will stop our healing.  Pyroluria is perhaps one such condition.  Normally considered an “inherited” condition associated with inner tension and anxiety, especially in social settings, and is made worse by stress, MSIDS sufferers should consider it.

Discuss all treatment information to your health care practitioner. 

http://lymediseaseguide.org/lyme-disease-zinc-and-pyroluria  Dr. Dietrich Klinghardt claims that most patients he treats for autism or Lyme disease have pyroluria, a defect in the synthesis of haemoglobin which causes excess excretion of zinc. His treatment for the condition is extremely high doses of zinc (200mg or more each day) although this level of zinc can cause nausea, adversely affect copper levels in the body (leading to anaemia), double the risk of prostate cancer, and result in diarrhoea, stomach pain, and vomiting in some. Patients should be extremely cautious regarding zinc supplementation whether suffering from Lyme disease or not as excess levels can build up quite quickly if pyroluria is not present.

Pyroluria is also known as kryptopyrroluria (KPU) or the Mauve Factor and is most commonly observed in women, possibly due to the more overt effects of chronic deficiency in B6 and zinc that may result in women during their teens and early twenties. Symptoms associated with pyroluria include halitosis (bad breath), severe stretch marks, fatigue, poor concentration, confusion, sleep disturbances, poor appetite or increased appetite, mood swings, pale skin, multiple food allergies, and changes in libido (raising or lowering). Some patients may be prescribed antidepressants such as Prozac as low levels of zinc and B6 can reduce the production of the neurotransmitter serotonin which regulates mood (amongst other things). Patients may be persistently depressed to some degree with symptoms exacerbated (in women) as part of the premenstrual syndrome (PMS).

The recommended daily allowances for zinc (in the US) are 8milligrams (8mg) for women and 11mg for men, although these used to be around 15mg a few years ago and have been lowered in recent years; anything over 50mg per day is considered excessive. Those with pyroluria however, may be advised to take supplements containing vitamin B6 and levels of zinc above the generally recommended levels but taking high levels of either nutrient is inadvisable without medical supervision (excessive B6 may lead to a kind of peripheral neuropathy when taken long-term).

https://www.youtube.com/watch?v=yYlZWuclkFA&ebc=ANyPxKp7mcnAx12iMGs_zB6ubuX_HWBCznJrjwQzuJPm55chzcn2zv0w70pkVRRMStcznXtE8nJl  Published on Jun 19, 2014  Pyroluria is more common than we realize and has overlaps with social anxiety and introversion. Carl Pfeiffer did the initial research while working with schizophrenic patients and found that the key nutrients zinc, vitamin B6 and evening primrose oil reduced and often eliminated symptoms.

This presentation will review:

• The associated signs and symptoms of this condition
• The concerns with pyroluria urine testing, and why the pyroluria questionnaire may be a better option
• Fatty acid testing
• Concerns with low vitamin B6 and zinc markers
• Food sources and supplemental forms of these nutrients
• Additional supportive nutrients
• Risk factors related with excess intake of some of the nutrients
• Tips to enhance absorption
• Review of a supportive protocol and its duration

This presentation will also examine the connection of pyroluria to gluten intolerance, inflammation, stress, heavy metals, low serotonin, insomnia, women’s hormonal health, methylation mutations and low histamine. Case studies will be discussed.

http://www.publichealthalert.org/kpuhpu-a-major-piece-of-the-puzzle-in-overcoming-chronic-lyme-disease.html#at_pco=smlrebh-1.0&at_si=56c7495ab3bd3a80&at_ab=per-2&at_pos=3&at_tot=auto  Here is an excellent article written by Scott Forsgren on KPU/HPU.

The HPU complex is a biochemical marker and neurotoxic substance frequently identified in the urine of patients with autism, learning disabilities, alcoholism, substance abuse, schizophrenia, ADHD, Down syndrome, depression, bipolar disorders, and even criminal behavior. Some estimate the incidence of KPU to be 40-70% in schizophrenia; 50% in autism; 30% in ADHD; and 40-80% in alcoholism and substance abuse.  HPU may be an inherited condition but it can also be induced by childhood psychological trauma or chronic infections. Dr. Klinghardt has found the incidence of HPU in Lyme disease to be 80% or higher; in patients with heavy metal toxicity (lead, mercury, cadmium, and others) over 75%; and in children with autism over 80%. These are very significant percentages of the patient population with chronic illness that may benefit from a treatment program which addresses HPU. Normal, healthy controls do not test positive for HPU. Dr. Klinghardt believes that it is not possible to have chronic symptomatic Lyme disease as an adult without a preceding mold illness or the patient having developed HPU. He postulates that the biotoxins from microbes block one or more of the eight enzymes of heme synthesis. This leads to a significant loss of key minerals in white blood cells which effectively disarms cellular immunity.


Last year, Certified Nutritionist Trudy Scott interviewed researchers, doctors, psychiatrists, nutritionists, consumer advocates, and psychologists on natural solutions for anxiety.

http://www.theanxietysummit.com  By going here, you can purchase recordings/transcripts, or contact Scott for any upcoming free on-line events.


Chiropractic care and MSIDS

Those suffering from MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) quickly discover that successful treatment is holistic.  Killing pathogens is certainly an important arm of treatment, but so is detoxing those dead pathogens, as well as improving immune system function.

http://www.chiro.org/research/ABSTRACTS/Immune_Responses_to_Spinal_Manipulation.shtml

According to Frank M. Painter, D.C., studies demonstrate an accumulation of evidence that indicates spinal manipulation may influence the immune system‘s response to various stimuli and reduces production of pro-inflammatory mediators associated with tissue damage and pain.  Some studies also give evidence that manipulation may induce and enhance production of the immunoregulatory cytokine IL-2 as well as the production of immunoglobulins.  http://www.chiro.org/research/ABSTRACTS/Effects_of_Chiropractic.shtml  Other results show manipulative treatment may influence T and B lymphocyte numbers, NK cell numbers, antibody levels, phagocytic activity, and plasma beta endorphin levels.  

http://articles.mercola.com/sites/articles/archive/2016/02/28/wellness-chiropractic

Chiropractic care has been vilified since the 60’s with a “persistent tendency to suppress physicians from referring patients to chiropractors — so much so that Dr. Chester Wilk ended up filing an antitrust suit against the American Medical Association (AMA) in 1976.”  Wilk eventually won and in 1987, the court ruled that the AMA had engaged in an unlawful conspiracy in restraint of trade to contain and eliminate the chiropractic profession.

According to chiropractors, chiropractic care is similar to seeing a dentist and needs to be done on a regular basis to maintain the health of your spine, because even regular activities can contribute to a less than optimal functioning.

One of the best ways to find a good wellness chiropractor is by word of mouth. You may also want to find out if he or she is trained in any other treatment modalities, such as muscle testing, applied kinesiology, or neuroemotional technique (NET). There are literally dozens of different techniques that can have a profound impact on addressing the bioenergetic component of disease, not just the structural.

Tips for Choosing a Wellness Chiropractor:
Meet the doctor. Many chiropractors will agree to a no-cost consultation to determine whether you are a good match. To make this visit as productive as possible, here are a few things to consider:
Does the practice focus on vertebral subluxation and wellness? Physical, biochemical, and psychological stress may result in spinal subluxations that disrupt nerve function and compromise your health.

Does the doctor “walk the talk”? If he or she is overweight, looks unhealthy, or does not live a healthy lifestyle, this speaks volumes regarding their commitment to wellness.
Do the two of you “click”? Do you like each other? Do you communicate well? Avoid a doctor who seems rushed, talks down to you, or seems disinterested in listening to your concerns.
Does the doctor use objective assessments of nerve function? Since your care is not based just on addressing pain, your chiropractor should be using some form of objective assessment of your nerve function, as spinal subluxations can sometimes be asymptomatic.  Non-invasive instruments that measure the electrical activity in your muscles, and/or a thermal scanner that evaluates the function of your autonomic nervous system can be used, for example.

What treatment techniques are used? Chiropractic techniques include low-force adjustments by hand, and more forceful adjustments using instruments. Ask which technique would be used on you, and if you have a preference, make sure the doctor is willing to use it.

On Saturday, April 9, from 2:30pm-4:45pm, Dr. Eileen Isom DC, CCST, Certified Spinal Trauma Specialist, of Madison Chiropractic, will be speaking at the Madison Lyme Support Group.  Dr. Isom uses NUCCA technique which is unique because it frees the nervous system of interference by using a precise, non-invasive, gentle touch technique.

The NUCCA technique brings several generations of clinical research to correcting the serious problem of the Atlas (the bone your head sets on) Subluxation Complex. By using precise and objective x-ray views of the head and neck, mathematical measurement and analysis are made of the misalignment.  There is no twisting, popping, or cracking with this gentle, yet effective procedure.

Some of the many symptoms that can be relieved by correction of the Atlas Subluxation Complex include but are not limited to:

Neck and back pain
Headaches and Migraines
Hypertension
Chronic pain or stress
Leg and arm numbness
Scoliosis
TMJ
Fibromyalgia
Sinus and allergy problems
Herniated disc
Seizures
Depression
Attention Deficit Disorder
Hormonal Imbalance
Athletic and auto injuries
Bed wetting
Cerebral Palsy
Multiple Sclerosis
Arthritis

Chiropractic care may be something you need to investigate further in your MSIDS journey as it can alleviate pain, help you structurally, as well as optimize your immune system.

For more information on NUCCA, go to:  http://www.nucca.org/what-is-nucca/