Archive for the ‘Treatment’ Category

Why Docs Miss Lyme/MSIDS & Info on Wobenzym For Inflammation

https://www.envita.com/lyme-disease/is-fibromyalgia-the-real-diagnosis/

https://www.envita.com/lyme-disease/new-envita-study-explains-how-lyme-disease-evades-the-immune-system-forms-biofilm/

Is it fibromyalgia, Lupus, Chronic Fatigue, MS, or MSIDS?

The Envita Center has found by using detailed testing and a decade of experience that over 80% of the patients labeled with autoimmune diseases also have viral, bacterial, fungal, and parasitic infections, along with tick-borne infections like chronic Lyme disease complex or MSIDS (multi systemic infectious disease syndrome). To complicate matters, it is not uncommon for patients to also have chemical sensitivities or heavy metals toxicity.

These patients are sent to psychiatrists and prescribed psych meds instead of treating the root cause of the problem.

Why?

“Most physicians are not trained to look for latent infections in a ten minute office appointment.”

Due to a multitude of symptoms these patients are labeled as “hypochondriacs,”  because they suffer with multiple issues including but not limited to depression, short-term memory loss, possible autoimmune diseases, digestive problems, migrating joint pain, and hormonal imbalances.
Doctors coin these folks “difficult,” because nothing seems to work. In the case of fibromyalgia, the sequence of symptoms used to diagnosis it are: key trigger points, depression, and sleep disturbances. There is a reason that these are never present in a textbook manner. In fact, most patients have even more symptoms than what is covered in the basic diagnostic write-up for fibromyalgia and chronic fatigue syndromes; however, when a proper infectious work-up is conducted alongside chemical toxicity and heavy metal screening, the complete symptom picture for each patient becomes clear, which should lead to treating the real pathology that is causing the symptoms, instead of just masking the pain.

“There are no simple treatments or testing solutions in the conventional model. However, once Cymbalta, the anti-depressant, came to market with a target for fibromyalgia patients, doctors started to recognize and “treat” the condition.”

“The pharmaceutical drug model drives the healthcare industry and ignores the necessary personalized diagnostics and treatment to take care of the cause of the disease.”

Most fibromyalgia patients have lymphocytosis. This occurs when infection has penetrated into the lymphatic system and deep into the connective tissue or even the nervous system.
The infection itself is protected by layers of biofilm communities. When the infection is found by conventional methods, prescribed antibiotics, will only provide temporary action against the bacteria. These cases need specialized testing with LLMD’s (Lyme literate medical doctors) and an integrative approach to help patients reach proper health by treating the cause of the disease, not just the symptoms.

Imbalances in key hormones like testosterone, thyroid, and cortisol are seen regularly in fibromyalgia, chronic fatigue, and MSIDS patients due to constant competition occurring at the receptors sites on their cells for hormones and neurotransmitters versus the neurotoxin.  These patients start to see improvement once put on “bio-identical hormones,” but will not fully improve unless the infections, lack of sleep, and inflammation are treated.

For more information on bio-identical hormones, please listen to PhD, Kathy Lynch of Women’s International Pharmacy: https://madisonarealymesupportgroup.wordpress.com/2015/06/10/audio-on-hormones-and-adrenal-support/

Most of these patients have latent infections that are found deep in connective tissue, muscle, digestive tract, and nervous system including the brain.

The brain and spinal cord make up the central nervous system. Stimuli comes from the peripheral nervous system, which then comes back to the cord. The stimulus can become interrupted when nerve compression occurs, especially in the neck regions. This also impairs and delays the healing process for patients. The discs of the spine often become degenerative in fibromyalgia patients because of the infection. This occurs when the infection has impacted the disc. If you look closely, the patient’s pain is often found in the muscle and soft tissue regions and not really in the joint because of the neurotoxin impacting nerve innervation to muscle.

For more information on how chiropractic care can help with this, please read:  https://madisonarealymesupportgroup.wordpress.com/2016/02/28/chiropractic-care-and-msids/  and come hear Dr. Isom speak at our next Lyme Support Meeting https://madisonarealymesupportgroup.wordpress.com/2016/03/22/dr-isom-to-speak-4916/

Once a person has gone through a treatment that addresses all of these pieces of the puzzle and they are symptom-free for 3 months or have stopped herxing for 3 months, whatever symptoms remain could be due to inflammation which can cause lingering pain and other symptoms.  Some find help taking systemic enzymes which are unlike NSAIDS which can cause kidney and liver issues.

Please discuss all treatment and supplement options with your health care professional I am not a distributor and do not receive monies from any company.  The following information is just my experience that I hope will help someone else out there.

http://wobenzymps.net

It was found that when some Olympic teams used Wobenzym injuries were reduced by as much as 50% and that healing was enhanced after injury. Also, surgeons routinely prescribe it to prevent bruising and edema and the associated pain for their post-surgical patients.

Wobenzym n works by breaking down and destroying harmful proteins, known as Circulating Immune Complexes (CICs) which cause most joint inflammation.  http://n.wobenzymonline.com/wobenzym-research  Wobenzym must be taken on an empty stomach.  http://www.antiaging-systems.com/153-wobenzym

*On a personal note – my husband and I both tried WobenzymN when we are in treatment for MSIDS with no effect.  Once we went off all antibiotics as we hadn’t herxed in 3 months, we started a capsulated herbal program  https://vitalplan.com/shop/restore-program for maintenance and to rebuild our bodies.  During this time I still had excruciating pain in my spine, neck, and head.  To rule out Chiari, I got a brain MRI (with and without contrast) and a cervical MRI.  Just as was pointed out by Envita 4 paragraphs back, I was told I had Degenerative disk disease in the cervical spine, most pronounced at C3-4 with (sic) moderate left foraminal narrowing due to facet arthropathy and normal MRI brain, in particular, there are no features of Arnold-Chiari type 1 malformation. There are no abnormal signal characteristics seen on T2 or FLAIR imaging.”

For information on Chiari go to:  https://madisonarealymesupportgroup.wordpress.com/2016/04/02/chiari/

A bit of degenerative disk disease shouldn’t have caused the grueling pain I was experiencing.  I remembered we had some WobenzymN in the drawer from the past (expired by 2 years!) and decided to give it a another try.  I’m glad I did as it has taken nearly all pain away.

My theory is that it didn’t work earlier due to the pain being from an active infection.  Since I believe I’m on top of the infections what is currently driving inflammation and pain is a autoimmune response that needs dampening down.  Go here for two chiropractors who are saying the same thing: https://madisonarealymesupportgroup.wordpress.com/2016/03/09/ld-needs-a-new-approach/

**Update** 

Eventually that horrific pain returned.  Instead of increasing the Wobenzym, I decided to try MSM.  Within 3 days 70% of the pain was gone.  Within a month, 100% of the pain was gone.  I take 1/4 tsp of MSM (OptiMSM patent) powder in about 4 oz of water twice a day.  I’ve also made a home made MSM cream for topical pain.  For more on DMSO & MSM:  https://madisonarealymesupportgroup.com/2018/03/02/dmso-msm-for-lyme-msids/  (Depending upon the size of the area, I take about 1 tsp of the cream and add about 10 drops 99% DMSO to it, mix it, and apply to clean, dry skin.  It MUST completely dry before you let anything touch it.  DMSO is a carrier and will take anything else into your body so no clothing, dyes, perfumes – anything can touch your skin before it’s dried)  Please read the article in the link to be informed.  DMSO is powerful stuff but you need to understand it.

Here’s more on Wobenzym or Systemic/Proteolytic Enzymes:   https://madisonarealymesupportgroup.com/2016/04/22/systemic-enzymes/

https://madisonarealymesupportgroup.com/2018/03/05/how-proteolytic-enzymes-may-help-lyme-msids/

https://madisonarealymesupportgroup.com/2018/01/03/the-invisible-universe-of-the-human-microbiome-msm/

Another item on the list to try is LDN for pain, inflammation, sleep, and immune function: https://madisonarealymesupportgroup.com/2016/12/18/ldn/

The brand I use is found here (again, I’m not a distributor): https://madisonarealymesupportgroup.com/2019/01/16/ldn-cbd/

Combating Viruses


herpes-simplex-virus-01a-924x924

3-D animation by Bryan Brandenburg.  March 9, 2013

<a href=http://www.bryanmbrandenburg.com>Courtesy of Bryan Brandenburg </a>

http://science.howstuffworks.com/life/cellular-microscopic/virus-human.htm  A virus is a tiny particle – about 1,000 times smaller than bacteria and must be viewed using an electron microscope. It consists of:
Nucleic acid – set of genetic instructions, either DNA or RNA, either single-stranded or double-stranded (see How Cells Work for details on DNA and RNA)
Coat of protein – surrounds the DNA or RNA to protect it
Lipid membrane – surrounds the protein coat (found only in some viruses, including influenza; these types of viruses are called enveloped viruses as opposed to naked viruses)

Viruses are all over the place, just waiting for a host cell to survive and proliferate. They enter through our nose, mouth, or breaks in the skin. Once they’ve infiltrated, they take over the host cell and make copies of viral genetic instructions to make new viruses. Then they either break the cell open, destroying it or they pinch out and break away with a piece of the cell membrane surrounding them, but not destroying the host cell. Once freed, they attack other cells, and spread quickly.

When you catch a cold here’s what happens:
*An infected person sneezes near you.
*You inhale the virus particle, and it attaches to cells lining the sinuses in your nose.
*The virus attacks the cells lining the sinuses and rapidly reproduces new viruses.
*The host cells break, and new viruses spread into your bloodstream and lungs.
*Viruses in nasal fluid drips down your throat giving you a sore throat.
*Viruses in your bloodstream can attack muscle cells and give you muscle aches.

The immune system finally responds producing chemicals which cause you to have a fever. This fever helps by slowing down the rate of viral reproduction and continues until the viruses are eliminated; however, if you sneeze, you can spread it into the environment where they again lie in wait for another host.  This is why it’s wisest to not use fever reducers unless absolutely needed.  By using a fever reducer you are eliminating one of the most powerful interventions against viruses in your own body.

In viruses like herpes and HIV; however, they mix their genetic code into the host cell’s genetic instructions so when the host call reproduces, the new instructions get copied into the his cell’s offspring. These particular host cells can go through many rounds of reproduction and then some environmental or predetermined genetic signal will wake up the “sleeping” viral instructions that now take over the host’s machinery and make new viruses.
Some routes of viral transport:
*Carriers such as mosquitoes, fleas, and ticks
*The air
*Body fluids such as sailva, sweat, mucus, blood, semen, vaginal secretions
*Surfaces on which bodily fluids have dried

What helps?
Interestingly, viruses often change slightly, changing their genetic instructions and altering their protein coat, making vaccines ineffective. Vaccine proponents will say this is why they must continually make new vaccines. Those opposed to vaccines will say this is why they rarely work. Just like MSIDS (multi systemic infectious disease syndrome or Lyme with friends) there is a schism in the medical community over vaccines.

To read more on vaccines, please go here and be informed:  https://madisonarealymesupportgroup.wordpress.com/2015/06/19/a-word-on-vaccines/ and https://madisonarealymesupportgroup.wordpress.com/2015/07/15/vaccines-continued/ and https://madisonarealymesupportgroup.wordpress.com/2016/03/19/a-dozen-collapse-after-vaccine/

To combat viruses, we must look at the immune system and make ourselves tough targets.  http://health-truth.com/our-program/health-articles/chronic-fatigue-syndrome/how-to-conquer-the-viral-bacterial-syndrome/

According to Michael Biamonte, C.C.D., the immune system uses nutrients from food to manufacture substances that attack and kill viruses. Viruses help bacteria by invading the cells in an area, and if the immune system is too weak, bacteria begin to swarm the  damaged cells invaded by the virus. As the virus begins to die having gone through it life cycle, the bacteria then start a secondary infection. For an MSIDS (multi systemic infectious disease syndrome) patient, they might be fighting borrelia (Lyme), Babesia, Bartonella, and many more pathogens, on top of viruses. This makes their illness much more complex.

Biomonte says to avoid sugar as it reduces the number of white bloods cells which fight off infection. He states that garlic is the most effective food against all infections as well as Echinacea, Zinc, water-soluble vitamin A, protein (stimulates the adrenal and thyroid), and eggs (contain large quantities of lecithin).

http://science.howstuffworks.com/life/cellular-microscopic/light-virus.htm  Interestingly, a study done at Arizona State and Johns Hopkins shows strong, quick blasts of purple light from a low power laser can kill viruses by vibrating and damaging their outer shells, but unlike other treatments doesn’t cause mutations leading to viral resistance. Blood UV radiation, similarly to the laser, also kills viruses by breaking down their cell walls.

Anti-virals:
Green Tea
Licorice (glycyrrhizin)
Pau D-Arco
Olive Leaf
Elderberry
Zinc
Garlic
Echinacea
St. John’s Wort
Coconut oil
Eucalyptus oil
Vitamin C

Blood UV

Ozone

Monolaurin

Always check with your health care professional before starting any supplement.

wellnessresources.com.http://www.wellnessresources.com/health/articles/monolaurin_a_natural_immune_boosting_powerhouse/  Written by Byron J. Richards, Board Certified Clinical Nutritionist

“Monolaurin a 12-carbon long fatty acid, derived from coconut oil but prepared into a mono-ester of lauric acid, is another anti-viral with decades of research showing the germ-killing and disinfectant properties of this natural compound. Monolaurin is a component of breast milk, part of Mother Nature’s immune support that is passed from mother to child.

Research dating back 30 years first identified that the 12 carbon fatty acid2 of monolaurin was highly effective at combating gram positive bacteria and yeasts (like Candida albicans). The Candida killing ability of monolaurin3 has been established. The most research has been done on gram positive bacteria, as the compound can be used to reduce infections on poultry and help clean equipment involved in the production of food. And monolaurin is effective against many viruses. The nutrient has been in widespread use as an immune support dietary supplement for several decades.

Monolaurin has been found to incorporate itself into the cell membrane of gram positive bacteria and have the net effect of disturbing the integrity of its cell membrane, blocking replication and making it an easier enemy for your immune system to take care of. 

In 1992 University of Minnesota researchers demonstrated an additional way that monolaurin helps, showing that it could reduce the toxicityof Staphylococcus gram positive bacteria. More recently, another gram positive bacteria, Bacillus anthracis, has been thrust into public attention by the threat of its use in bioterrorism. Like many bacteria, it’s severity of infection is based on how much toxin it can produce. In 2005 the University of Minnesota researchers this time demonstrated that monolaurin inhibited the genes that enabled anthrax to generate toxins. In 2006 research they showed the mechanism of reducing gram positive infection toxicity applied to many organisms, indicating that monolaurin is likely to help reduce the toxicity of any gram positive infection by making it less severe. This research also found that healthy cells were made stronger by monolaurin, also helping them combat the toxicity.
Monolaurin has demonstrated some ability to help regulate gram negative bacteria, one of which is the common intestinal inhabitant known as Helicobacter pylori (H. pylori). If H. pylori starts getting out of balance and turns hostile, like a bad gang in the neighborhood, then a lot of stomach distress can follow. Researchers have shown that monolaurin has a direct and potent germ killing effect on H. pyloria, regardless of stomach pH. The H. pyloria germ killing ability of monolaurin has been confirmed by a second group of researchers. Exactly how monolaurin is able to kill these gram negative bacteria has not been identified.
Research has shown that monolaurin is not effective against most gram negative bacteria like Salmonella or E. coli, which have a different kind of outer cell membrane than gram positive bacteria. In contrast to this general finding, one study of bacteria cultured from the skin of children found that monolaurin inhibited the growth of gram positive and gram negative bacteria.
It has been generally observed that no gram positive bacteria are resistant to monolaurin. However, a recent study demonstrated that various super strains of gram positive Vancomycin Resistant Enterococcus (VRE) have developed partial (up to 70%) resistance to monolaurin. VRE is especially problematic to those with weak immunity. It is unknown if monolaurin is effective or not against Methicillin-resistant Staphylococcus aureus (MRSA). A detailed analysis in the VRE study showed that the mutated enterococcus bacteria had learned to tighten their cell walls, making it more difficult for monolaurin to get a toehold (the same problem antibiotics were having). Monolaurin has been shown to reduce the toxicity of gram positive infections, and has been shown to help Vancomycin work better against these super strains – meaning that monolaurin used along with appropriate medical care may produce a superior result.

Monolaurin and Viruses
Monolaurin is one of the most popular nutrients to assist in combating various viruses. It is believed to work by interacting with the lipids and phospholipids that form the envelope of the virus, causing it to weaken or disintegrate.  Research suggests that monolaurin exerts some degree of immune support for the following viruses:

• Human immunodeficiency virus HIV-1, HIV+ *Measles virus
 *Herpes simplex virus-1
 *Herpes simplex virus-2
 *Herpes viridae (all)
 *Human lymphotropic viruses (type 1)
 *Vesicular stomatitis virus
 *Visna virus
 *Cytomegalovirus
 *Epstein-Barr virus
 *Influenza virus
*Pneumonovirus
 *Sarcoma virus
 *Syncytial virus

One study showed that while monolaurin was effective against Cytomegalovirus it was not effective against rhinoviruses, the cause of the common cold.  There are many anecdotal reports of monolaurin helping combat the flu.  

Many of the types of viruses monolaurin helps are those that can be chronic low grade infections that deplete energy on a regular basis and flare up when you are stressed or down. If you have ever had a bad bug and never really got your energy back then monolaurin may help your immune system clean up the problem – even years later. Many find it useful for recurring mouth sores that are herpes-based problems.
The new discovery that many lipid coated viruses can live in your stored fat and disturb your metabolism, promoting obesity, opens the door for the use of monolaurin to assist weight management – though no specific studies have been done on this topic.
In summary, monolaurin is a nutritional fatty acid that is non toxic to humans and a friendly nutrient for human cell health. In contrast, it can be a knock out punch for gram positive bacteria and a number of difficult viral problems. It can also help to keep normal inhabitants of your digestive tract, such as H. Pylori and Candida albicans, in a better state of healthy balance.”

MSIDS sufferers need as many tools as possible in their toolbox as our bodies are in a war. Thankfully we have many aids at our disposal to assist our bodies along the way.

Why We Can’t Get Better

Most MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) sufferers are familiar with Dr. Horowitz, a famous and gifted LLMD (Lyme Literate Doctor) who wrote the book, “Why I Can’t Get Better?  Solving the Mystery of Lyme and Chronic Disease.”  I just noticed you can get it new for $7.99 – the best eight bucks you’ll ever spend!  I warn you; however, it’s deep and it’s wide, and you will be looking up a few terms unless you’re a M.D. http://www.amazon.com/Better-Solving-Mystery-Chronic-Disease/dp/1250019400

In fact, he’s the person who came up with the term MSIDS as it more adequately explains what’s going on in most patients diagnosed with “Lyme Disease,” as research shows we are typically infected with multiple pathogens making our treatment pictures far more complex than most GP’s realize and is also a very good reason why people don’t get better.  This issue is what he discusses in the following videos.  For some of you, you just can’t get on top of things – even after years of treatment.  There can be numerous reasons for this but the following videos may enlighten both you and your doctor.

Working with an LLMD is definitely a partnership.  In the beginning, unless you’ve watched someone go down this pot-hole riddled road, you know very little other than the fact that your body’s going to hell in a hand basket!  As time progresses, you talk to others, watch videos, read books, and become an on-line researcher learning things you never in your wildest dreams would have thought about learning (the life-cycles of ticks).

For those of you who are new to the journey, you want to get someone you know up to speed quickly, or if you need a refresher course, these videos will do it.  Horowitz is engaging, intelligent, and funny.  The first video is only 8 minutes long and explains the nuts and bolts of how he came to his current knowledge.

The second video is an hour long, but definitely worth watching.  In a much more detailed fashion, it explains many symptoms of the various coinfections that could be holding up your progress unless you are dealing with them.  Watch these videos, take notes, and go back to your doctor and discuss these possibilities.  Remember, testing for all of these pathogens is extremely poor and not to be solely relied upon for diagnosis.  It’s important to “study thy enemy,” so you understand him and know how to combat him.  In this case the more you know about the various pathogens and how they affect the human body the better.

Published on Nov 3, 2014
At the “Symposium on Tick-borne Diseases” held May 17, 2014 at the Hyatt in Cambridge, Maryland, Dr. Richard Horowitz provided insights into the many diseases humans are contracting from ticks, and he helps us to differentiate between the different illnesses. The event was hosted by the Lyme Disease Association of the Eastern Shore of Maryland (soon to be the Lyme Disease Association of Delmarva), a 501(c)(3) non-profit organization providing educational resources on tick-borne diseases. This and other videos from the Symposium were made possible by a very generous private donation for which we are very thankful to have received. The wonderful videographer/editor for the event was Bryan Krandle (krandle86@yahoo.com). If you enjoy having wonderful resources like the videos from this conference, please consider a donation to the LDAESM, P.O. Box 5360, Salisbury, Maryland 21802. Thank you!

Tick Removal

http://www.abc.net.au/health/features/stories/2015/02/12/4178721.htm

Some recommend using tweezers being careful to avoid squeezing the tick, which would cause it to inject its stomach contents into you; however, others are now recommending aerosol freezing sprays or ether-containing sprays that instantly kill the tick. This approach is recommended by the Australasian Society of Clinical Immunology and Allergy (ASCIA) for those with a known tick allergy. Since Australia contends with a tick that causes a severe allergy to red meat, they are recommending the ether sprays which will not disturb the tick, thereby lessening the chance of it injecting more of its allergen-containing saliva.  

Dr Cameron Webb, a medical entomologist at Westmead Hospital and clinical lecturer at the University of Sydney, has been looking into the various methods of tick removal and thinks we should all be following the advice of ASCIA, which recommends killing the tick in place by using ether-containing aerosol sprays that instantly freeze it (although some of these are not registered for use in humans). He suggests some over-the-counter products for freezing off warts may work.

Wartner may be the perfect fix.  http://www.wartner.eu/uk_en/warts-and-verrucas/treatments/wartner-wart-verruca-remover/

http://www.wartner.eu/warts-verrucas/treatments/wartner-cryotherapy/

PRODUCT CHARACTERISTICS

Freezes the tick to the core by –50°C  (lowest temperature available within self treatments), it says to press applicator firmly down for 3 seconds, then hold on tick for 40 seconds.  Let tick fall off naturally – takes approximately 10 minutes.               
Using DMEP gas mixture
New application steps to reach therapeutic temperature any time
http://www.walgreens.com/store/c/wartner-cryogenic-wart-removal-system%2c-original/ID=prod3984640-product

Ingredients:  Dimethyl Ether, Propane

Extremely Flammable. Contents Under Pressure Keep away from fire, flame and heat. Do not smoke while using this product. Protect from sunlight and do not expose to temperatures above 120°F. Store at room temperature away from heat.

Keep out of reach of children. Avoid contact with eyes. Do not inhale vapor/spray and use only in well-ventilated areas. Do not Swallow. For external use only. Use only as directed. If Wartner® is not used exactly as instructed or if you mistakenly apply it directly to the skin or use it on conditions that are not warts, it may cause serious burns and permanent scarring of the skin.

Wartner® should only be used in combination with the applicators provided. Use one foam applicator for session.  Do not reuse applicator.

I knew this product was it when I read a review:

“Pros: great if you want to torture your worst enemy”

How did they know?


Anaplasmosis Treatment

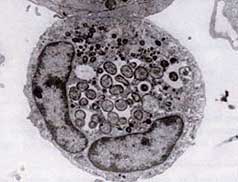
3-phagocytophilum

Ultrastructure of A.phagocytophilum by transmission
electron microscopy. Photo by V.Popov, reprinted
from Dumler JS et al. Human granulocytic
anaplasmosis and Anaplasma phagocytophilum.
Emerg Infect Dis;11:1828-34.

http://www.health.state.mn.us/divs/idepc/diseases/anaplasmosis/hcp.html

Human anaplasmosis (HA), formerly known as human granulocytic ehrlichiosis (HGE), is a small, obligate, gram-negative bacterial disease that is unusual in its tropism to neutrophils, and is caused by Anaplasma phagocytophilum, a rickettsial bacterium. It was first recognized in 1990, when a western Wisconsin patient developed a severe febrile illness following a tick bite and died two weeks later; however, it has been known to cause disease in animals since 1932. Human ehrlichiosis, a similar disease, is caused by Ehrlichia chaffeensis and is found throughout much of southeastern and south-central United States. Another related form of ehrlichiosis caused by the Ehrlichia muris-like agent was identified in Minnesota and Wisconsin patients in 2009. The median age of patients with HGA is around 50 years old. Over 4000 total cases have been reported in the CDC’s Morbidity and Mortality Weekly since the disease became nationally reportable; as with most tick-borne diseases, the true incidence is suspected to be considerably higher.

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC2882064/   Cases occur year-round, with a peak incidence during June and July, perhaps reflecting the shorter arthropod season in these northern states or the relative importance of the nymphal stage of Ixodes ticks in disease transmission. Given the ubiquity of the tick vector, it is not surprising that cases of HGA have been confirmed world-wide, including Europe and Asia (China, Siberian Russia, and Korea).

In dogs, persistent infection has been reported to last over 10 years and in the absence of treatment can persist for the life of the dog. Other strains persist for months and then are naturally cleared.

Transmission:
http://www.health.state.mn.us/divs/idepc/diseases/anaplasmosis/hcp.html
http://www.capcvet.org/capc-recommendations/ehrlichia-spp-and-anaplasma-spp1/ Anaplasmosis is known to be transmitted to humans by Ixodes scapularis (blacklegged tick or deer tick), the same tick that transmits Lyme disease (borrelia). It can also be transmitted via blood transfusion and contaminated needles or surgical instruments.  

Symptoms:

Onset of illness occurs 5 to 21 days after exposure to an infected tick. Infection can range from asymptomatic infection to fatal disease. Common signs and symptoms include fever (often over 102°F), chills, headache, and myalgias.  Nausea, vomiting, anorexia, acute weight loss, abdominal pain, cough, diarrhea, and change in mental status are reported less frequently. Highly suggestive laboratory findings include leukopenia – a decrease in white blood cells making you more susceptible to infection (WBC< 4,500/mm³), thrombocytopenia  – a decrease in platelets causing bruising and bleeding (platelets <150,000/mm³), and increased aminotransferase levels – relating to liver damage. Most of the damage it causes appears to be related to host inflammatory processes, as there is little evidence of a correlation between the number of organisms and host disease severity.

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html

Compared with HME (human monocytic ehrlichiosis), HGA (human granulocytic anaplasmosis) appears less likely to involve the central nervous system, but peripheral neuropathies are more common and can last weeks to months. Among the neurologic findings reported in the medical literature are facial palsy, demyelinating polyneuropathy and brachial plexopathy. Respiratory distress syndrome and a septic or toxic shock-like syndrome have been reported, but appear to be less common than in HME. The overall fatality rate from HGA also seems to be slightly lower than that of HME, with most of the deaths resulting from opportunistic infections (for example, herpes simplex esophagitis, Candida pneumonitis, and pulmonary aspergillosis) in immunocompromised patients.

Unusual presentations may be the result of coinfections with Borrelia burgdorferi (Lyme disease agent) and/or Babesia microti (babesiosis agent), as a single feeding tick may transmit multiple disease agents.

Cases of HA acquired through blood transfusions have been documented. Include HA in the rule-out for patients who develop a febrile illness with thrombocytopenia following blood transfusion. Suspected transfusion-associated anaplasmosis should be reported.

Prevalence:

A large survey by Lymedisease.org found that 53% stated they had coinfections and 30% responded they had two or more coinfections.  Similar results were found in Canada.  While the most common coinfections found in Canada were Bartonella (36%) and Babesia (19%), Anaplasma took third place (13%).  https://www.lymedisease.org/lymepolicywonk-study-finds-coinfections-in-lyme-disease-common-2/ Here in the U.S. the results showed that 5% of patients with Lyme also had Anaplasmosis; however, please realize most doctors are not looking for this, the testing is poor, many states don’t require reporting and many cases go unreported. In 2014, there were 2800 confirmed cases of HA.  Rhode Island, Minnesota, Connecticut, Wisconsin, New York and Maryland are the hotbeds.  https://www.cdc.gov/mmwr/volumes/65/rr/pdfs/rr6502.pdf

Master Herbalist, Stephen Buhner, in his book Natural Treatments for Lyme Coinfections (Anaplasma, Babesia, and Ehrlichia states on page 24, “In other words, if you want to successfully treat someone who is infected with a vector-borne infection you need to realize up front that it is usually the case that coinfection has occurred and you have to look at the interactive picture, not merely single infectious agents.”  Demonstrating another unique interplay, one study found that ticks express an antifreeze type substance to enhance survival when they are infected with Anaplasma. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2929727/  In the world of microbes there is definitely a “You scratch my back, I’ll scratch yours.”

Tests:

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html
Standard blood tests in HGA usually reveal findings similar to those seen in HME: leukopenia, thrombocytopenia and liver function abnormalities (elevated transaminases). However, the hematological abnormalities frequently resolve by the second week of symptoms, so their absence should be interpreted in that context if patients are presenting later in the course of their illness. In general, empiric antibiotic treatment should be considered for patients in endemic areas who present with an acute febrile illness suggestive of HGA. For specific diagnosis, Wright or Giemsa-stained blood smears have a slightly higher yield than with HME, but are still not optimal for general clinical utility, given that there appears to be a wide variation (25-75%) in the sensitivity of these tests in visualizing morulae in host neutrophils. More helpful, but not always available, are polymerase chain reaction (PCR) tests, which are estimated to have a sensitivity of 67-90%. Prior antibiotic therapy dramatically reduces the sensitivity of both  of these diagnostic methods. Serologic testing is useful to confirm the diagnosis of anaplasmosis. The most commonly used method is indirect immunofluorescence (IFA) of IgM and IgG anti-A. phagocytophilum antibodies. Seroconversion is perhaps the most sensitive laboratory evidence of A. phagocytophilum infection, but is not always obtained in a timely enough manner to provide useful input on clinical (i.e., treatment) decisions.

According to the CDC:
Any two of the following three tests for evidence of infection with Anaplasma phagocytophilum are recommended:
*An indirect immunofluorescence assay (IFA) is the principal test used to detect HA infection. Acute and convalescent phase serum samples can be evaluated to look for a four-fold change in antibody titer to A. phagocytophilum.
*Intracellular inclusions (morulae) also may be visualized in granulocytes on Wright- or Giemsa- stained blood smears.
*Polymerase chain reaction (PCR) assays are being used increasingly to detect A. phagocytophilum DNA.

According to animal studies, morulae are usually difficult to find in blood smears, even during the acute stage of disease. It is also stated that serology may be helpful in identifying antibodies but may not detect early infections during the acute phase of disease.

88_anaplasma316x316Courtesy of Lymestats.org

Treatment: Discuss all treatments with your health care professional

http://www.columbia-lyme.org/patients/tbd_ehrli-anapla.html
The optimal dose and duration of antibiotic treatment for anaplasmosis has not been definitively established, but it is clear that A. phagocytophilum is highly sensitive to tetracyclines. Thus, oral doxycycline is the recommended treatment, at the same dose used for Ehrlichia infections: 200 mg/day in two divided doses. The usual treatment duration is 5-10 days, which is extended if there is suspected coinfection with B. burgdorferi, the agent of Lyme disease. In any case, treatment should continue for at least three days after the patient’s fever resolves. Response to treatment is usually rapid; if the patient remains febrile more than two or three days after initiation of doxycycline therapy, the diagnosis should be revisited.
As with Ehrlichia infections, rifampin is used in cases where doxycycline is contraindicated, such as pregnancy or allergy. Rifampin has also been used successfully in pediatric cases, and thus is sometimes employed in mild cases of pediatric A. phagocytophilum infection. If coinfection with B. burgdorferi is suspected in a pediatric case, doxycycline is sometimes used as an initial treatment for 3-5 days, with another antibiotic employed thereafter to complete the somewhat longer recommended treatment period for early Lyme disease.

Treatment according to the CDC: (Notice the dose is lowered)

http://www.cdc.gov/rmsf/doxycycline/index.html

HA patients typically respond dramatically to doxycycline therapy (100 mg twice daily until the patient is afebrile for at least 3 days). Other tetracycline drugs also are likely to be effective. In general patients with suspect HA and unexplained fever after a tick exposure should receive empiric doxycycline therapy while diagnostic tests are pending, particularly if they experience leukopenia and/or thrombocytopenia.
http://www.jpeds.com/article/S0022-3476(15)00135-3/pdf?ext=.pdf

According to the CDC, Doxycycline is the most effective antibiotic for the treatment of suspected rickettsial infections for all ages, including Rocky Mountain Spotted Fever, and delay in treatment may lead to severe illness and/or death. Children are five times more likely than adults to die from RMSP and a new study found that short courses of doxy can be used in children without causing tooth staining or weakening of tooth enamel. Prior to this, doctors were reticent using Doxy due to studies in the 50’s showing a link between Tetracycline (binds to calcium) use in young children and tooth weakening and staining. Doxy, a newer medication, binds to calcium less readily and, according to the CDC, if used in the correct dose and duration for rickettsial diseases, should cause no harm. It’s also the treatment of choice according to the American Academy of Pediatrics (AAP). Doxycycline treatment should be continued for at least 3 days after fever resolves, and the usual duration of therapy is 7-10 days.  Chloramphenicol is considered a second-line therapeutic agent, as it is significantly less effective at preventing fatal outcome; other broad-spectrum antimicrobial agents typically used to treat sepsis are not effective at preventing fatal outcome due to RMS.

http://www.ilads.org/lyme/what-to-do-if-bit-by-tick.php
According to ILADS (International Lyme and Associated Diseases Society) Doxycycline has the advantage of treating numerous tick borne illnesses such as Lyme (borrelia), Ehrlichia, Anaplasma, Q Fever, and Rocky Mountain Spotted Fever. They state the downside is that Doxy causes significant sun sensitization, can be hard on the stomach, and the usual dosing may not reach therapeutic levels.
Recent data suggests that treatment may not clear organisms in animals.

If you find a doctor willing to become properly educated on tick borne illness, please give them this link:  https://madisonarealymesupportgroup.com/2017/06/20/help-doctors-get-educated-on-lyme-and-tick-borne-illness/