Archive for the ‘Treatment’ Category

Diagnosis and Management of Lyme Neuroborreliosis

https://www.ncbi.nlm.nih.gov/m/pubmed/29278020/

Diagnosis and management of Lyme neuroborreliosis.

Halperin JJ. Expert Rev Anti Infect Ther. 2018.

Abstract

The nervous system is involved in 10-15% of patients infected with B. burgdorferi, B. afzelii and B. garinii. This review will address widespread misconceptions about the clinical phenomenology, diagnostic approach and response to treatment of neuroborreliosis. Areas covered: Improvements in diagnostic testing have allowed better definition of the clinical spectrum of neuroborreliosis, with lymphocytic meningitis and uni- or multifocal inflammation of peripheral/cranial nerves predominating. Despite widespread concern that post-treatment cognitive/behavioral symptoms might be attributable to persisting infection or aberrant inflammation within the central nervous system a large body of evidence indicates this is extremely improbable. Importantly, recent studies show most neuroborreliosis can be treated with fairly brief courses of oral antibiotics. All high-level evidence confirms that prolonged courses of antibiotics carry harm with no commensurate benefit. Expert commentary: Lyme disease in the US, and corresponding disorders in Europe, are well defined neuro-infectious diseases that are highly responsive to antibiotic therapy. Although the nervous system is slow to recover after insults (e.g. persistent facial weakness after appropriately treated facial nerve palsy) there is no evidence that prolonged post-treatment neurocognitive symptoms are related to nervous system infection – either as a triggering event or as a cause of ongoing symptoms.

 _____________

**Comment**

While I would love to read this in its entirety for amusement, I refuse to pay $1 let alone $90 for 24 hour access.

Just from the abstract it is evident that it is another great example of why a medical condition never makes forward progress.  “Experts” like Halperin refuse to rethink the paradigm.

  • This article focuses only on borrelia, a formidable foe alone, an absolute shape-shifting beast on steroids when coupled with Babesia, Bartonella, Anaplasma, and other critters.  The one disease, one drug paradigm needs to go straight into the garbage can, and until this happens we are doomed.
  • The 10-15% patient statistic with nervous system involvement also needs to go straight into the can.  Nobody has a clue on numbers on any of this.  If the CDC goes from 30,000 new cases to over 300,000 new cases a year, I think we need to wave the white flag and admit our ignorance.
  • Without reading the entire faulty article, I have a deep rooted suspicion that this “review” is based on other deeply flawed articles and studies from the past made by the Cabal.  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/ and https://madisonarealymesupportgroup.com/2017/12/06/ahern-flawed-lyme-policies-diagnostics-and-treatment/
  • Diagnostic testing has not improved with the CDC even stating numerous tests might be needed:  https://madisonarealymesupportgroup.com/2017/07/01/good-morning-america-cdc-advises-multiple-lyme-tests-due-to-false-negative-results/
  • A recent study states that treating prophylactically if TBI’s are suspected is warranted: https://madisonarealymesupportgroup.com/2017/07/12/start-treatment-if-tbis-are-suspected/.  Also see:  https://www.lymedisease.org/lyme-basics/lyme-disease/diagnosis/, and https://madisonarealymesupportgroup.com/2017/09/02/microbiologist-holly-ahern-on-lyme-disease-how-did-we-get-here/.
  • The definition of the clinical spectrum of neuroborreliosis is not better.  While it is true that more is being reported on, there is absolutely no consensus on any sort of definition.
  • The persisting infection/aberrant inflammation issue is not over just because Halperin reviews old Cabal manuscripts and claims there is a “wide body of evidence.”  As they say, Garbage in, garbage out.
  • Brief courses of antibiotics do work for some people, typically acute cases; however, there is much to indicate that many relapse and continue to have symptoms.  To say otherwise indicates bias of the highest sort.
  • His usage of “high-level evidence” also indicates an extreme personal bias indicating that the rest of us poor fools have low-level evidence.  Please, I know a slam when I hear one.  Nobody in Lyme-land is arguing that antibiotics do not have risks.  Many if not most treatments have risks, including drinking water; however, as with any disease state, the doctor and patient must discuss and weigh the risk/benefit ratio for sure.  An IDSA Founder, Dr. Waisbren, successfully used high powered IV antibiotics and wrote a book on 51 tough cases.  All improved.  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/  Again, there are so few studies looking at long-term antibiotic benefit on Lyme/MSIDS that this statement is premature and misleading.  I work with people on a daily basis who state they wouldn’t be alive today without the very treatment he is slamming, and trust me, we would all love an effective treatment with fewer risks!  
  • The “expert commentary” is only expert in my opinion if it takes into account numerous physicians who have actually treated complicated Lyme/MSIDS cases over decades of time, who are open-minded, are willing to change, and are continually studying, listening and learning from others.  Halperin fails on many accounts.  Keep reading below to see why.
  • This review is nothing more than a regurgitation of ancient, unscientific, and biased opinion.

In this interview  Halperin repeats the common myth that Lyme takes 24-49 hours or more to be transmitted  https://madisonarealymesupportgroup.com/2017/04/14/transmission-time-for-lymemsids-infection/, that it is primarily an Eastern problem  http://steveclarknd.com/wp-content/uploads/2013/11/The-Confounding-Debate-Over-Lyme-Disease-in-the-South-DiscoverMagazine.com_.pdf (go to page 6 and read about Speilman’s maps which were faulty but have ruled like the Iron Curtain), and that you typically have flu-like symptoms https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/ (My initial symptoms were gynecological).  He treats everyone with 2-4 weeks of antibiotics.

A quick search reveals Halperin commonly serves as an “expert” witness in medical malpractice cases defending physicians accused of failing to diagnose Lyme.  

Here’s a lengthy article Article Kicking and LLMDs Personal View coauthored by Halperin which states,

“Advocacy for LD has become an increasingly important part of an anti science movement that denies both the viral cause of AIDS and the benefits of vaccines and that supports unproven (sometimes dangerous) alternative medical treatments.”  

Oh, and somehow patients, advocates, and their doctors pose a threat to public health.
 Here’s a few telling Halperin quotes:
QUOTE-  “When physicians who diagnose chronic Lyme disease obtain laboratory tests to provide support for their diagnoses, they often rely heavily on “Lyme specialty laboratories.” Such laboratories may perform unvalidated in-house tests that are not regulated by the Food and Drug Administration, or they may perform standard serologic tests interpreted with the use of criteria that are not evidence-based.1” Source
 
QUOTE-  “Antibiotic therapy can cause considerable harm to patients treated for chronic Lyme disease or post–Lyme disease symptoms.” Source
 
QUOTE-  “Although anecdotal evidence and findings from uncontrolled studies have been used to provide support for long-term treatment of chronic Lyme disease,18-20 a response to treatment alone is neither a reliable indicator that the diagnosis is accurate nor proof of an antimicrobial effect of treatment.” Source
 
QUOTE-  “It is highly unlikely that post–Lyme disease syndrome is a consequence of occult infection of the central nervous system.” Source

Lyme Disease Laid Bare

https://www.nature.com/articles/d41586-017-08442-8 Dec. 2017

Lyme disease laid bare

James G. Logan hails a study of the controversial tick-borne condition.
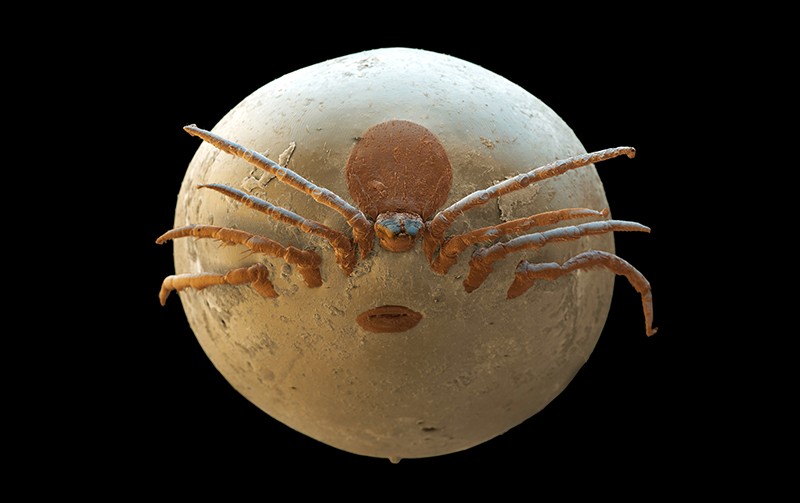
Blood filled sheep tick, SEM.

Ixodes ticks spread Lyme disease.Credit: Eye of Science/SPL.

Conquering Lyme Disease: Science Bridges the Great Divide Brian A. Fallon & Jennifer Sotsky Columbia University Press: 2017.

It occurs in more than 80 countries and is the most commonly reported vector-borne disease in the Northern Hemisphere. In the United States alone, it spawns 300,000 new cases each year. Yet Lyme disease — caused by species of Borrelia bacteria carried by ticks of the Ixodesgenus — remains one of the most poorly understood infections. It has divided researchers, clinicians and patients, and triggered intense public suspicion and confusion.

So what is science’s role in turning the corner on what some have labelled a “public health failure”? Physicians Brian Fallon and Jennifer Sotsky tackle this question in their insightful study Conquering Lyme Disease, in which they journey beyond the history, biology and symptoms of the illness. Their greatest accomplishment, by far, is delivering multiple viewpoints with minimal bias and great sensitivity: the clinician’s, the researcher’s and, particularly, the patient’s.

Although recent headlines make Lyme disease seem new, probably the first recorded case was in 1909: the Swedish dermatologist Arvid Afzelius associated a patient’s expanding rash (later named erythema migrans) with a tick bite. In the 1970s, a link was made to bacteria by rheumatologist Allen Steere; in 1981, the biologist Willy Burgdorfer discovered that the disease was caused by a type of bacterium called a spirochaete. The species complex was named Borrelia burgdorferi in his honour. But it was not until the 1990s that US cases were properly reported, through a surveillance system set up by the Centers for Disease Control and Prevention in Atlanta, Georgia.

Since that decade, the global incidence has increased and reporting has improved, as Fallon and Sotsky describe; in the United States alone, known cases have tripled since 1992. There is currently no human vaccine, and research on the disease has struggled to keep up.

The many presentations of an illness known as the “great imitator”, and its inherent complexities, are why medical communities have often failed to find common ground on diagnosis and treatment, as the authors explore. The manifestations range from no symptoms, or mild influenza-like ones, to severe complications such as inflammation in joints or the brain and persistent neurological problems.

One of the reasons Lyme is difficult to diagnose is that some non-infectious conditions, including fibromyalgia and Alzheimer’s disease, present with similar symptoms. The situation is further complicated because Ixodes ticks transmit a host of other pathogens, such as Rickettsia, other bacteria, viruses and protozoa, leading to diseases including typhus, relapsing fever, babesiosis and meningoencephalitis. Misdiagnosis is thus all too common.

Treatment is also far from straightforward. Although antibiotics can clear infection in some cases, Fallon and Sotsky describe how genetic differences in Borrelia bacteria found on different continents make treatment difficult. There are, for instance, three different species in the complex in Europe. The authors note that each can cause different symptoms in people with Lyme disease who develop neurological complications. So a treatment that works for one species of the bacterium may not work for another.

And spirochaetes can remain in the body even after courses of antibiotics (E. Hodzic et al. Antimicrob. Agents Chemother. 52, 1728–1736; 2008). Fallon and Sotsky hypothesize that they may “hide” inside human cells, for instance. A big question is whether the spirochaetes that hang on in this way can replicate and cause disease.

Whatever the mechanism, proof of the existence of persistent symptoms will pave the way for better diagnostics, treatment and care. Some patients have spent years trying to convince medical doctors that their symptoms remain after treatment. Fallon and Sotsky strikingly convey these people’s difficulties and frustrations. Clinicians, for instance, might fail to ask the right questions. People with chronic Lyme disease can feel abandoned, and even suicidal. That has led to protests and court hearings, notably in the United States. But these people, the authors argue, have played a significant part in moving understanding beyond conventional thinking, and ultimately driving research forward. Clinicians are now beginning to acknowledge both the complexity of Lyme disease and patients’ needs. Fallon and Sotsky end on a firmly positive note, reviewing avenues for new research across many disciplines, from diagnostics to vaccines and treatments. What’s particularly pressing is the need for a definitive test to detect the spirochaetes that cause this devastating disease.

 ______________

Duke Studying Alternatives to Antibiotics for Lyme

https://corporate.dukehealth.org/news-listing/lyme-study-uses-drug-discovery-methods-have-fueled-cancer-breakthroughs

Lyme Study Uses Drug Discovery Methods That Have Fueled Cancer Breakthroughs

Labs at Duke and other academic centers collaborate to identify alternatives to antibiotics

Published December 13, 2017 

Ticks can spread the bacterium that causes Lyme disease

DURHAM, N.C. – Antibiotics are currently the only treatments available for Lyme disease and other tick-borne illnesses, but researchers at Duke Health are working to expand the medical toolkit by identifying vulnerable areas of disease-causing bacteria that could lead to innovative therapies.

The research project, which recently received a $3.8 million grant from the Steven & Alexandra Cohen Foundation, relies on drug discovery methods that have proven successful in identifying treatments for cancer and viral diseases.

“Our goal is to find alternatives to antibiotics to treat Lyme disease, which is caused by the Borrelia burgdorferi bacterium, and illnesses that arise from the Bartonella pathogen,” said Neil Spector, M.D., the Sandra Coates Associate Professor Breast Cancer Research at Duke Cancer Institute and the study’s co-principal investigator.

“We’re hoping to move from isolating targets to identifying potential drugs to testing in animal models within three years – so a very aggressive timeline,” said Spector, who was a Lyme patient himself and nearly died from complications of disease. “Our goal is to identify drugs that will target the Achilles’ heel of these pathogens while sparing the normal gut microbiome.”

Spector and co-principal investigator Timothy Haystead, Ph.D., professor in the department of Pharmacology and Cancer Biology at Duke, are collaborating with scientists at Johns Hopkins School of Medicine and Tulane Medical Center to perform distinct functions of the study.

The Duke team will use technology Haystead’s lab has pioneered for cancer drug discovery, which will identify protein targets for the development of a completely new class of molecularly targeted therapies for Borrelia burgdorferi and Bartonella.

The team at Duke will then screen thousands of new compounds to identify those that target the desired proteins. The new compounds identified at Duke will then be tested at Johns Hopkins in a high-throughput assay to evaluate their effects on the viability of Borrelia burgdorferi and Bartonella.

The most promising drug candidates will then be sent to Tulane, where researchers will determine their efficacy in animal models of Bartonella illnesses and Lyme diseases, including in primates.

The Spector and Haystead labs have already identified more than 20 bacterial proteins that represent attractive targets for drug development. The protein targets are selected in part for their specificity to Borrelia burgdorferi, which would reduce the risk of adverse side effects such as the destruction of normal, healthy gut flora.

Duke researchers have begun screening a library of thousands of compounds looking for potential drugs that target a specific Borrelia burgdorferi protein that plays a key role in promoting the survival of the bacteria.

The research project represents a new exploration for Spector, a leading cancer researcher who was instrumental in the development of lapatinib, the first oral inhibitor of the HER2/neu cancer promoting protein approved by the FDA for the treatment of a subset of breast cancers. Spector’s interest in Lyme disease research stems from his personal experience with the infection, which he battled for years without a clear diagnosis. After suffering near-fatal heart failure, he underwent a heart transplant in 2009.

Spector said many features of cancer are also true of Lyme. For example, how and where tumors spread is not random. Similarly, Lyme affects different people in different ways, and Spector asserts that there are likely biological factors at play.

“I think there’s a way to capitalize on the lessons we’ve learned in cancer biology and basic research over the past 20 years and apply them to Lyme research,” Spector said. “We don’t have to reinvent the wheel.”

Contact

______________


Live Bb Found – Months After Doxy

https://www.news-medical.net/news/20171214/Study-Living-Lyme-disease-bacteria-found-months-after-antibiotic-treatment.aspx

Study: Living Lyme disease bacteria found months after antibiotic treatment

Bay Area Lyme Foundation, a leading sponsor of Lyme disease research in the US, today announced results of two papers published in the peer-reviewed journals PLOS ONE http://journals.plos.org/plosone/article?id=10.1371/journal.pone.0189071 and American Journal of Pathology, that seem to support claims of lingering symptoms reported by many patients who have already received antibiotic treatment for the disease.

Based on a single, extensive study of Lyme disease designed by Tulane University researchers, the study employed multiple methods to evaluate the presence of Borrelia burgdorferi spirochetes, the bacteria that cause Lyme disease, before and after antibiotic treatment in primates. The study also measured the antibody immune response to the bacteria both pre- and post- treatment, as this is how current diagnostics typically evaluate Lyme disease in humans.

The data show that living B. burgdorferi spirochetes were found in ticks that fed upon the primates and in multiple organs after treatment with 28 days of oral doxycycline. The results also indicated that the immune response to the bacteria varied widely in both treated and untreated subjects.

“It is apparent from these data that B. burgdorferi bacteria, which have had time to adapt to their host, have the ability to escape immune recognition, tolerate the antibiotic doxycycline and invade vital organs such as the brain and heart,” said lead author Monica Embers, PhD, assistant professor of microbiology and immunology at Tulane University School of Medicine.

“In this study, we were able to observe the existence of microscopic disease and low numbers of bacteria, which would be difficult to ‘see’ in humans but could possibly be the cause of the variable and nonspecific symptoms that are characteristic of post-treatment Lyme disease syndrome. Although current antibiotic regimens may cure most patients who are treated early, if the infection is allowed to progress, the 28-day treatment may be insufficient, based on these findings,” Embers said.

The findings also demonstrated:

  • All subjects treated with antibiotics were found to have some level of infection 7 – 12 months post treatment.
  • Despite testing negative by antibody tests for Lyme disease, two of 10 subjects were still infected with Lyme bacteria in heart and bladder.
  • Lyme bacteria which persist are still viable.

To better elucidate previous animal studies demonstrating that some B. burgdorferi bacteria survive antibiotics, the study explored Lyme disease infection in rhesus macaque primates treated with antibiotics and a control group who were also infected but not treated. This species has been shown to demonstrate a progression of Lyme disease most similar to humans, particularly related to erythema migrans, carditis, arthritis, and neuropathy of the peripheral and central nervous systems.

“Clearly, some medical practices governing diagnosis and treatment of Lyme disease should be reconsidered in light of this study. This study shows that we must reevaluate the current paradigm of antibody response tests for diagnosis and move away from the one size fits all approach to Lyme treatment,” said

In the study, ticks carrying B. burgdorferi spirochetes fed on ten primates. Four months post infection, half of the primates (five) received the antibiotic doxycycline orally for 28 days at a proportional dose to that used in human treatment. Five subjects were treated with placebo and all ten were evaluated by more than five different diagnostic methods to characterize any remaining infection. The researchers used several important techniques, including xenodiagnoses, to determine if the spirochete bacteria persisted.

The results show:

  • Few subjects displayed a rash. Although all subjects were infected, only one of the 10 displayed a rash with central clearing, the classical “bulls-eye” rash. The subject that developed this rash, interestingly, never mounted an immune response to five borrelia antigens throughout the study period, prior to and following treatment.
  • Organs may be infected even if antibody tests are negative. One subject which tested negative for B. burgdorferi by skin biopsy cultures, PCR and in vivo cultures, was found to have B. burgdorferi infecting the heart. Another untreated subject, who was ultimately shown to have residual Lyme bacteria in the bladder, showed a decrease in immune response over the course of infection, with a negative xenodiagnosis test in the late stage, which would signal that the animal self-cured.
  • Intact spirochetes were found in three of five treated and four of five untreated subjects based on xenodiagnosis results 12 months after the tick bite.
  • Immune responses to B. burgdorferi varied greatly post-treatment, with one subject’s antibody levels dropping to pre-bite levels for three antigens while another subject experienced elevated antibodies for the same antigens throughout the study period. This is significant because it demonstrates that subjects infected with the same strain of B. burgdorferi may have different immune responses to the same antigen. And, because humans, like primates, are genetically diverse, it underscores that testing antibody responses may be inherently unreliable as a singular diagnostic modality for Lyme disease.
  • Widespread and variable microscopic disease was observed in all infected subjects, despite antibiotic treatment. Compared to uninfected subjects of the same age, infected subjects in this study (treated and untreated) demonstrated Inflammation in and around the heart, in skeletal muscles, joints, and the protective sheath that covers the brain, and near peripheral nerves.
  • Rare, but intact B. burgdorferi spirochetes were found in the tissues of both the treated and untreated subjects. In two subjects treated with doxycycline, multiple Lyme bacteria were observed in the brain tissue. Others organs in which the spirochetes were observed included the heart, joints, bladder, skeletal muscle and adjacent to peripheral nerves.
    Source:
    http://tulane.edu/

_____________

For more:  https://madisonarealymesupportgroup.com/2017/11/03/lyme-bug-stronger-than-antibiotics-in-animals-and-test-tubes-now-study-people/

https://madisonarealymesupportgroup.com/2015/09/19/proof-of-borrelia-persistence/

https://madisonarealymesupportgroup.com/2017/08/18/drexel-prof-lyme-persists/

https://madisonarealymesupportgroup.com/2017/12/02/scottish-doctor-gives-insight-on-lyme-msids/   “If you look at major medical microbiology and infectious disease textbooks, they state that after 4 weeks you can’t find the Lyme bacteria anymore. Therefore Lyme is then categorised as ‘post infectious’. But I get back to the point I’ve made before: if you can’t culture it, you cannot know anything about its viability. You do not have a organism specific test (culture or PCR), that guides your ‘test of cure’. How do you say that a bacteria is killed, when you couldn’t grow and measure it in the first place?”  “One of the rules of infectious diseases medicine is that once you stop treatment and the patient stays better, they are cured. When they get worse, the infection has returned and they have relapse of infection and need repeat treatment. My ID colleagues live by that rule with most other infections, but not with Lyme.”


LDo’s Top 10 Lyme Research Questions

https://www.lymedisease.org/top-ten-lyme-priorities/

Top-Ten-Research-Questions-with-MLD-logo-1024x625

Press release:

LymeDisease.org releases “Top 10 Lyme Disease Research Questions,” as federal government weighs options in fight against growing epidemic.
