FEB 25, 2018 — Please see the following letter addressed to the Tick Borne Disease Working Group.
If you support a congressional investigation into the mishandling of Lyme disease as this petition is calling for please consider writing your own letter in support of this request to form a separate subcommittee.
Anyone wishing to contact the Lyme Disease Working Group can send an email to:
tickbornedisease@hhs.gov
Carbon copy to Dr. John Aucott, Chair of the TBD Working Group:
jaucott2@jhmi.edu
Richard Wolitski, Ph.D., Designated Federal Officer:
Richard.Wolitski@hhs.gov
Letter to the Working Group:
To the TBD Working Group,
Let’s not ignore the fact that a crime has been identified here!
Racketeering lawsuit: https://www.courthousenews.com/wp-content/uploads/2017/11/LymeDisease.pdf
A subcommittee should be appointed to uncover the motivation behind the deliberate suppression of evidence of persistent Borrelia infection so this travesty will never be repeated.
For example:
1. Why did the Centers for Disease Control suppress positive culture evidence of persistent infection (1991) in Lyme patient Vicki Logan as described in the letter to Brenda Fitzgerald, Director of the CDC?
Letter to Fitzgerald: https://www.dropbox.com/s/xaul84dqmqgbre0/Brenda%20Fitzgerald%20MD%20Director%20CDC.docx?dl=0
2. Why was the following 1995 case study out of Stony Brook Lyme Clinic ignored which describes seronegative recurrent Borrelia infection after repeated courses of IV and oral meds?
Seronegative Chronic Relapsing Neuroborreliosis.
https://www.ncbi.nlm.nih.gov/pubmed/7796837
________________
3. Why did the Centers for Disease Control promote Nordin Zeidner who published his study regarding single dose Doxycycline for tick bite?
Zeidner’s conclusion: https://www.ncbi.nlm.nih.gov/pubmed/18349366
“…..single dose doxy stopped Lyme disease not in 87% of mice, but rather, in 20 to 30 percent at most.”
Dr Gary Wormser of New York Medical College (who has controlled the Lyme disease narrative for the past three decades) published a study earlier promoting the use of single dose Doxy for tick bite. (See Wormser’s 2001 flawed NEJM article)
Source: http://www.nejm.org/doi/full/10.1056/NEJM200107123450201
I understand that it was Wormser who called Zeidner’s superiors at the CDC to put an end to Zeidner’s work. Zeidner was told to discard the mice sera instead of testing for antibodies as he had promised.
Zeidner’s research was terminated for “lack of industrial support” Paul Mead, and he was promoted, and his email address inactivated.
Wormser’s single dose Doxycycline is still promoted to this day.
Complaint filed with the Office of Special Counsel and Office of Inspector General:
https://www.dropbox.com/s/68fq6cit7ggqhdt/Single%20dose%20Doxy%20Complaint%20filed%20with%20the%20Office%20of%20Special%20Counsel.docx?dl=0
How many other researchers have been intimidated or have had their employment threatened by Wormser or the CDC?
___________________
4. Why have the Centers for Disease Control bankrolled Wormser’s junk science (1.5 million) where he compares Lyme to the “aches and pains of daily living”; essentially downgrading Lyme with its life-altering/life-threatening consequences to a simple “nuisance disease?”
The patient experience with this disease does not resemble the established disease definition (Wormser’s definition) as the destructive nature is seen in histopathologic findings of the autopsy results of Lyme patient Vicki Logan.
Complaint filed with the Office of Research Integrity:
https://www.dropbox.com/s/94jv3w2hb0z9lv7/Email%20sent%20to%20the%20Office%20of%20Research%20Integrity.docx?dl=0
Complaint filed with the U.S. Department of Justice, Criminal Division:
https://www.dropbox.com/s/8ts9v51pr2fn65b/Complaint%20filed%20with%20the%20U.S.%20Department%20of%20Justice%20Criminal%20Division.docx?dl=0
Scientific misconduct to support one’s bias is fraud which has had an impact on public health and clinical treatment. Wormser’s 1.5 million grant should be reclaimed from New York Medical College to support honest research.
________________
5. Why did the Centers for Disease Control end all communication with Dr. Sin Lee after he published his study identifying persistent Borrelia infection from the blind coded serum samples provided by the CDC’s Lyme Disease Clinical Sample Repository? A FOIA request identified Wormser’s lab which collected and categorized these samples. Dr. Lee’s laboratory used molecular diagnostics with sequencing confirmation.
Dr. Lee’s publication identifying chronic Lyme:
DNA sequencing diagnosis of off-season spirochetemia with low bacterial density in Borrelia burgdorferi and Borrelia miyamotoi infections.
https://www.ncbi.nlm.nih.gov/pubmed/24968274
Dr. Lee’s 57 million dollar claim against the CDC for suppression of an early detection test for Lyme disease:
https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/20864023
____________________
6. How many other laboratory tests for Lyme disease are sitting on the shelf?
Quantification of Borrelia burgdorferi membrane proteins in human serum is a new concept for detection of bacterial infection
Crystal S. F. Cheung, Kyle W. Anderson, Kenia Y. Villatoro Benitez, Mark J. Soloski, John N. Aucott, Karen W. Phinney, and Illarion V. Turko,
https://www.ncbi.nlm.nih.gov/pubmed/26491962
Perhaps Dr. Aucott could shed some light on the subject since he is a co-author of this 2015 paper?
7. For the past three decades, the patient experience with Lyme disease describes an illness producing horrific disability and financial ruin but those who control the narrative through editorial censorship have painted an entirely different picture. Why?
Here is a small sample of the published books on the subject of Lyme disease: (I listed these seven books for a reason!)
1. Cure Unknown: Inside the Lyme Epidemic by Pamela Weintraub
“Instead of just swollen knees and a rash, patients can experience exhaustion, disabling pain, and a “Lyme fog” that leaves them dazed and confused.”
2. In the Crucible of Chronic Lyme Disease: Collected Writings & Associated Materials
by Kenneth B. Liegner
“Documentational in nature and not written as a narrative, the materials, nonetheless, convey the intensity of the struggle to characterize the nature of Lyme disease and the desperate fight for proper diagnosis and treatment upon the outcome of which patients’ very lives depended.”
3. Lyme Madness: Rescuing My Son Down The Rabbit Hole of Chronic Lyme Disease by Lori Dennis
Chronic Lyme disease is a complicated, confusing, and terrifying abyss—a black hole of human suffering, conflicting views, widespread corruption, and unrelenting medical navigation. Lyme Madness chronicles the author’s and adult son’s medical odyssey while capturing the current landscape of immeasurable suffering,
4. Confronting Lyme Disease: What Patient Stories Teach Us by Rita L. Stanley, Karen P. Yerges
“In this book, fourteen patients reveal how their lives were changed by the debilitating effects of Lyme disease and its co-infections, and by unanticipated medical obstacles.”
5. “It’s All In Your Head,” Patient Stories From the Front Lines: Intimate Aspects of Chronic and Neuropsychiatric Lyme Disease by PJ Langhoff
“Imagine inaccurate diagnostic tests…Physicians ignoring patient symptoms…Insurance denying coverage…patients are told their illness is “fake”…Academic societies denying an epidemic…People are suffering needlessly…Sound like science fiction? It’s real and it’s happening right now…”
6. Believe Me: My Battle with the Invisible Disability of Lyme Disease By Yolanda Hadid
“She suffered from severe debilitating fatigue, migraines, joint pain, anxiety, insomnia, Bell’s palsy, tremors, muscle weakness, severe brain fog, word retrieval difficulty, memory loss and intermittent loss of eyesight.”
7. Bite Me: How Lyme Disease Stole My Childhood, Made Me Crazy, and Almost Killed Me by Ally Hilfiger, Tommy Hilfiger (Foreword by)
“Ally was at a breaking point when she woke up in a psych ward at the age of eighteen. She couldn’t put a sentence together, let alone take a shower, eat a meal, or pick up a phone.”
______________
There is evidence to suggest that the rush to create a vaccine for Lyme led to the mishandling of the disease. The Principle Investigators of the two previous Lyme vaccines: Allen C. Steere for SmithKlineBeecham’s LymeRix and Gary Wormser for Connaught’s vaccine (which never made it to market) have conceptualized a disease that would enable vaccine development.
A chronic relapsing seronegative disease does not fit the vaccine model.
The one-size-fits-all Lyme treatment guideline (lead author: Gary Wormser) matches the conceptualized disease. (Nuisance disease) This is a flagrant conflict of interest. Post-treatment Lyme disease syndrome is simply a fabricated medical condition disguising treatment failure.
Lyme disease testing parameters were manipulated at the 1994 Dearborn Conference in order to facilitate vaccine development. Outer surface proteins A and B of the Borellia spirochete were eliminated so the vaccinated would test seronegative. Removing Bands 31 and 34 from the commercial Western blot is the crime that should be exposed.
Letter to the World Health Organization regarding faulty/misleading antibody tests:
https://www.dropbox.com/s/olby3eb9276oj3r/11th%20email%20to%20the%20World%20Health%20Organization.docx?dl=0
8. Why did CDC Director Thomas Frieden refuse to answer Dr. David Volkman’s letter regarding the strict DEARBORN testing criteria?
Dr. Volkman’s letter to Frieden:
https://www.dropbox.com/s/sl5x3gzguowpj6n/Volkman%20letter%20to%20Frieden.doc?dl=0
_________________________
Might I remind everyone that this process of collecting data and recommending changes for how we diagnose and treat Lyme disease was previously completed in 2001 by the Institute of Medicine. What has changed since then? NOTHING!
IDSA Ignores IOM Recommendations in Lyme Disease Treatment Guidelines’ Development, According to the Lyme Disease Association & LymeDisease.org
May 06, 2015, 13:40 ET from Lyme Disease Association, Inc.
https://www.prnewswire.com/news-releases/idsa-ignores-iom-recommendations-in-lyme-disease-treatment-guidelines-development-according-to-the-lyme-disease-association–lymediseaseorg-300078777.html?tc=eml_cleartime
Excerpt:
“Unfortunately for 300,000 people who contract Lyme annually in the US, the last 25 years of research has not improved patient care. Instead, a small group of researchers have built their careers around a biased view of the disease that brings us no closer to cure. They have disregarded patients while pursuing dead- end research using tax payer funded grants.”
___________
What is the solution here?
The TBD Working Group subcommittee should recommend a congressional investigation (with subpoena power) into the deliberate mishandling of Lyme disease and present all of the evidence collected by the subcommittee members with the intent to prosecute those responsible for this crime against humanity as it would appear that the Centers for Disease Control is allowed to police themselves while answering to no one.
The disabled Lyme community believes that this TBD Working Group is little more than a pacifier while those in control march along with current agendas supporting the status quo.
For example:
Once again we see the CDC promoting antibody testing for Lyme even though it is well known that Lyme patients may not produce detectable antibodies for 4-6 weeks after a tick bite.
A multiplex serologic platform for diagnosis of tick-borne diseases
Published online: 16 February 2018
https://www.nature.com/articles/s41598-018-21349-2
Rafal Tokarz, Nischay Mishra, Teresa Tagliafierro, Stephen Sameroff, Adrian Caciula, Lokendrasingh Chauhan, Jigar Patel, Eric Sullivan, Azad Gucwa, Brian Fallon, Marc Golightly, Claudia Molins, Martin Schriefer, Adriana Marques, Thomas Briese & W. Ian Lipkin
Until the CDC, IDSA and all those named in the racketeering lawsuit have been removed from positions of authority and influence we will have another three decades of unimaginable pain and suffering.
A response to this inquiry is requested.
Respectfully submitted,
Carl Tuttle
Independent Researcher
Lyme Endemic Hudson, NH


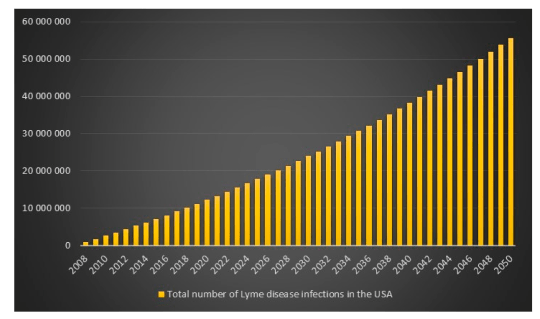 Given the same incidence rate of Lyme disease in Europe as in the USA, then 2.4 million people will get infected with Lyme disease in Europe in 2018.
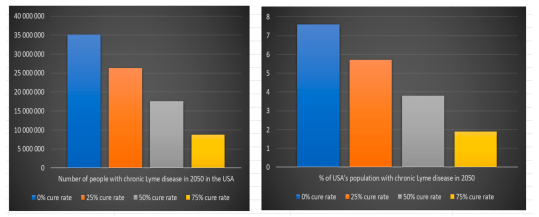
 Madison Area Lyme Support Group
